Working Within the LPN Scope of Practice in Colorado
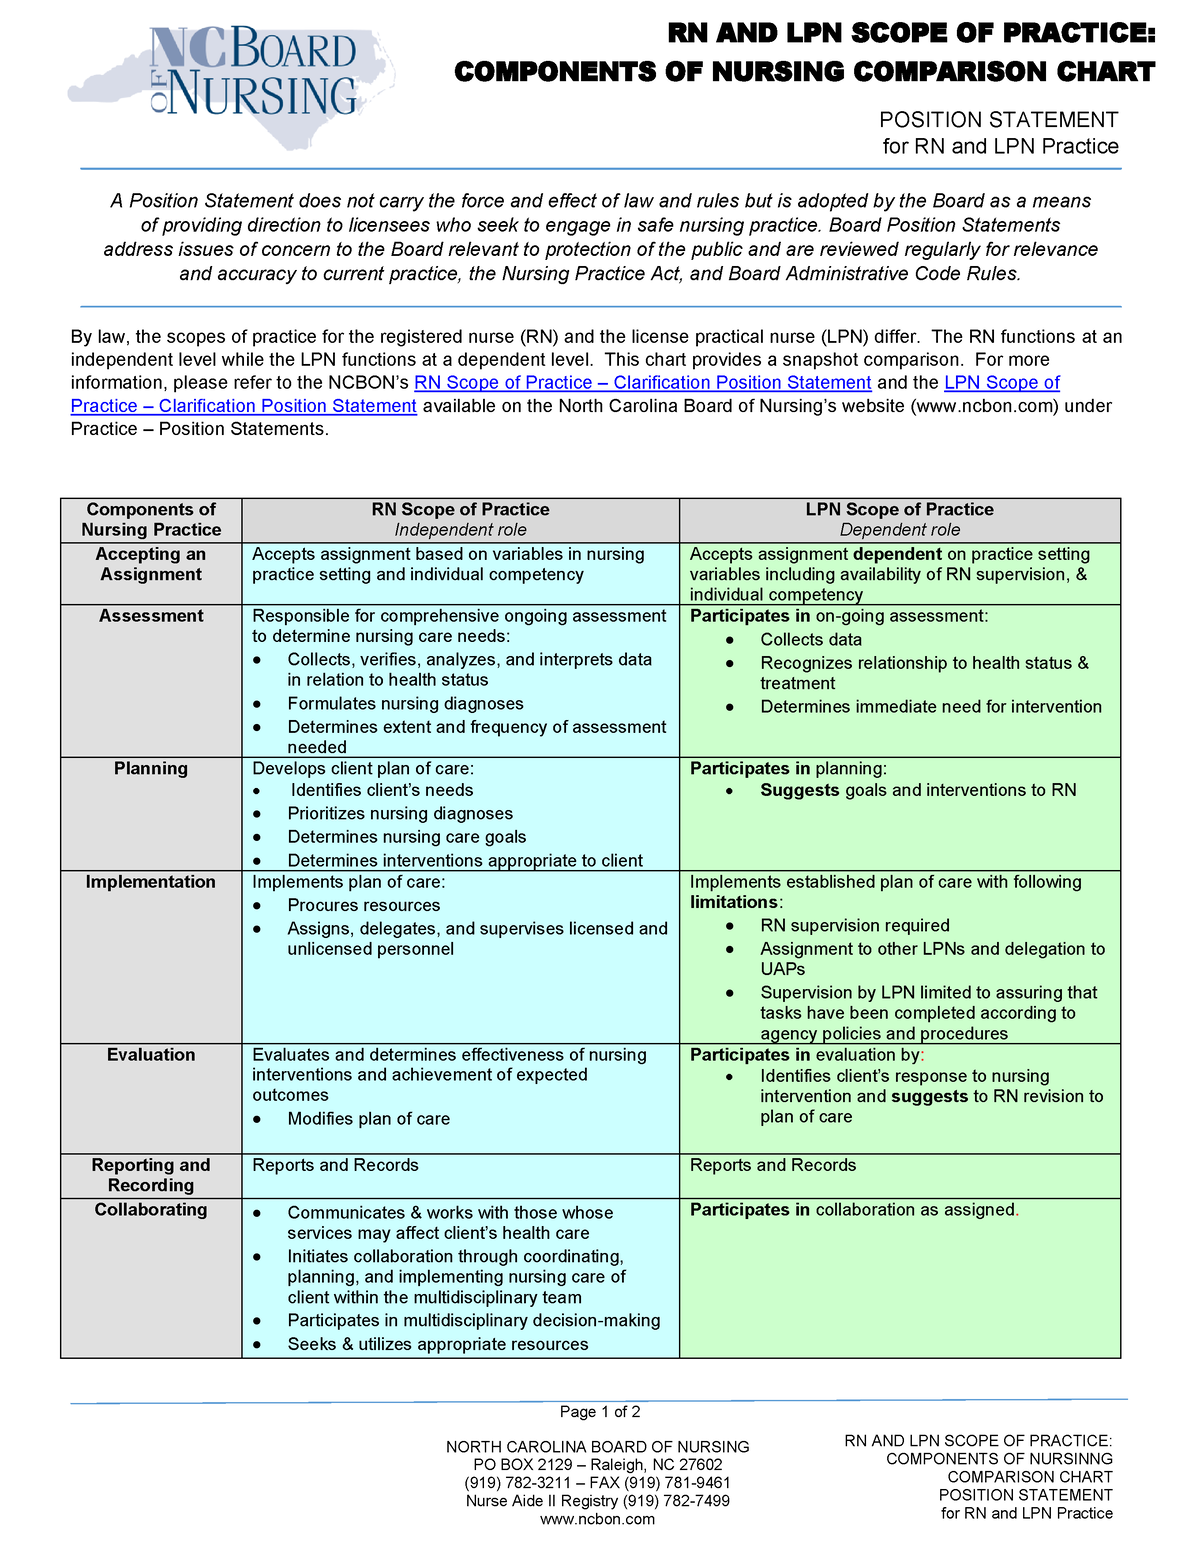
The Colorado Board of Nursing defines LPN scope through rules found in Article 31 of the Colorado Nurse Practice Act and the accompanying nursing rules. If you're trying to figure out what you can and cannot do on a real shift, the official language is dense and occasionally contradictory, so most people end up cross-referencing the board rules with their employer's policy manual. That second step matters more than people realize. Here is what the framework actually looks like when you pull it apart. LPNs in Colorado can perform focused assessments on stable patients. That phrase "stable patients" is doing a lot of work in the rules. It means you can take vitals, check intake and output, assess a healing wound, and document changes, but you generally cannot initiate a comprehensive admission assessment or develop a nursing care plan from scratch. That stays with the RN or the provider.
Medication administration is the area where people get the most confused. LPNs can give oral meds, intramuscular injections, subcutaneous injections, and certain topical medications. The tricky part is the IV therapy rules. Colorado allows LPNs to administer IV medications and fluids, but only if they have completed a board-approved IV certification course and the employing facility has a policy that permits it. Even then, there are medications you cannot push through an IV line. Vasopressors, chemotherapy, and blood products are off the table regardless of your certification status.
Delegation and Supervision
This is where the real world gets messy. The board rules say LPNs must work under the direction of a licensed physician, podiatrist, or dentist, or under an RN. In practice, that direction often comes through a charge nurse or a manager who is not physically present. You need to understand the difference between direct supervision and general supervision because it changes how much pushback you will get from nursing leadership when something goes sideways. I ran into a specific problem last year when a facility wanted an LPN to start a blood transfusion on a post-surgical patient. The policy manual said LPNs could administer blood products, but the Colorado board rules were ambiguous about whether that counted as a medication requiring IV certification or a separate procedure. The RN supervisor disagreed with my read of the rules and refused to co-sign. I ended up calling the Colorado Board of Nursing directly and got a written clarification stating that blood product administration falls under the IV certification scope, provided the LPN has completed the approved course. It took three hours and I had to submit the request in writing through their portal, but having that documentation meant the policy stood and the transfusion went forward. If you are ever in a situation like this, do not accept a verbal refusal as the final word. Put your question in writing and reference the specific rule number. The board responds to that faster than you would expect.
Get the Full Details

Limitations You Will Hit
LPNs cannot perform sterile procedures beyond basic wound irrigation and dressing changes on stable patients. They cannot administer intravenous push medications that are not on the facility's approved formulary list. They cannot teach patients about new diagnoses or new medication regimens as the primary educator. And they cannot delegate nursing tasks to unlicensed assistive personnel on their own authority. That decision belongs to the RN or the provider. The biggest pitfall I see people fall into is assuming that completing an IV certification course automatically expands their scope. It does not. The certification is necessary but not sufficient. Your facility policy, the attending provider's orders, and the specific patient condition all act as additional gates. An LPN can have perfect IV credentials and still be unable to run a drip on a particular patient because the provider has not written the appropriate order or the patient's acuity level requires RN-level monitoring. Another counter-intuitive detail is the skill of abdominal assessment. LPNs can listen to bowel sounds and note distension, but they cannot perform a full abdominal assessment that includes palpation for organomegaly. The distinction matters in documentation. If you write "abdomen soft and non-tender" after palpating, that crosses into RN territory in most audit reviews. Stick to observation and auscultation, or have an RN confirm your findings before you finalize the note.
Where the Rules Fall Short
The board rules are not perfectly updated to reflect modern practice. There are gaps around telehealth-related nursing tasks, advanced wound care with negative pressure devices, and the growing use of wearable monitoring technology in outpatient settings. If your job involves any of those areas, you are operating in a gray zone where the burden is on you to verify whether the board would consider your actions compliant. That is not a comfortable position to be in. For situations where the LPN scope creates real bottlenecks, the practical workaround is either pursuing RN licensure or working within a collaborative practice model where the provider has explicitly authorized expanded tasks through a standing order protocol. Some outpatient clinics in Colorado use the latter approach effectively, but it requires the physician to take on additional liability and not all practices are willing to do that. Be honest with yourself about whether you want to navigate those conversations or just move on to a different license track.
How to Check the Official Rules
You can find the full Colorado Nurse Practice Act and nursing rules on the Colorado Department of Regulatory Agencies website under the Board of Nursing section. The relevant rules for LPNs are in Title 18, Article 31, specifically rules C.A.R. 18-31-101 through 18-31-220. The board also publishes procedural guidelines that are not technically law but are treated as enforcement standards. Read both. The procedural guidelines will tell you how the board actually interprets the rules when they are unclear. The board rule numbers change occasionally during legislative sessions. If you are citing a rule in a formal complaint or policy dispute, always verify the current numbering against the latest adopted version. The printed code books lag behind by several months and I have seen people cite superseded language in written correspondence, which undermines their position immediately.