
IV Therapy for LPNs: What the Regulations Actually Say
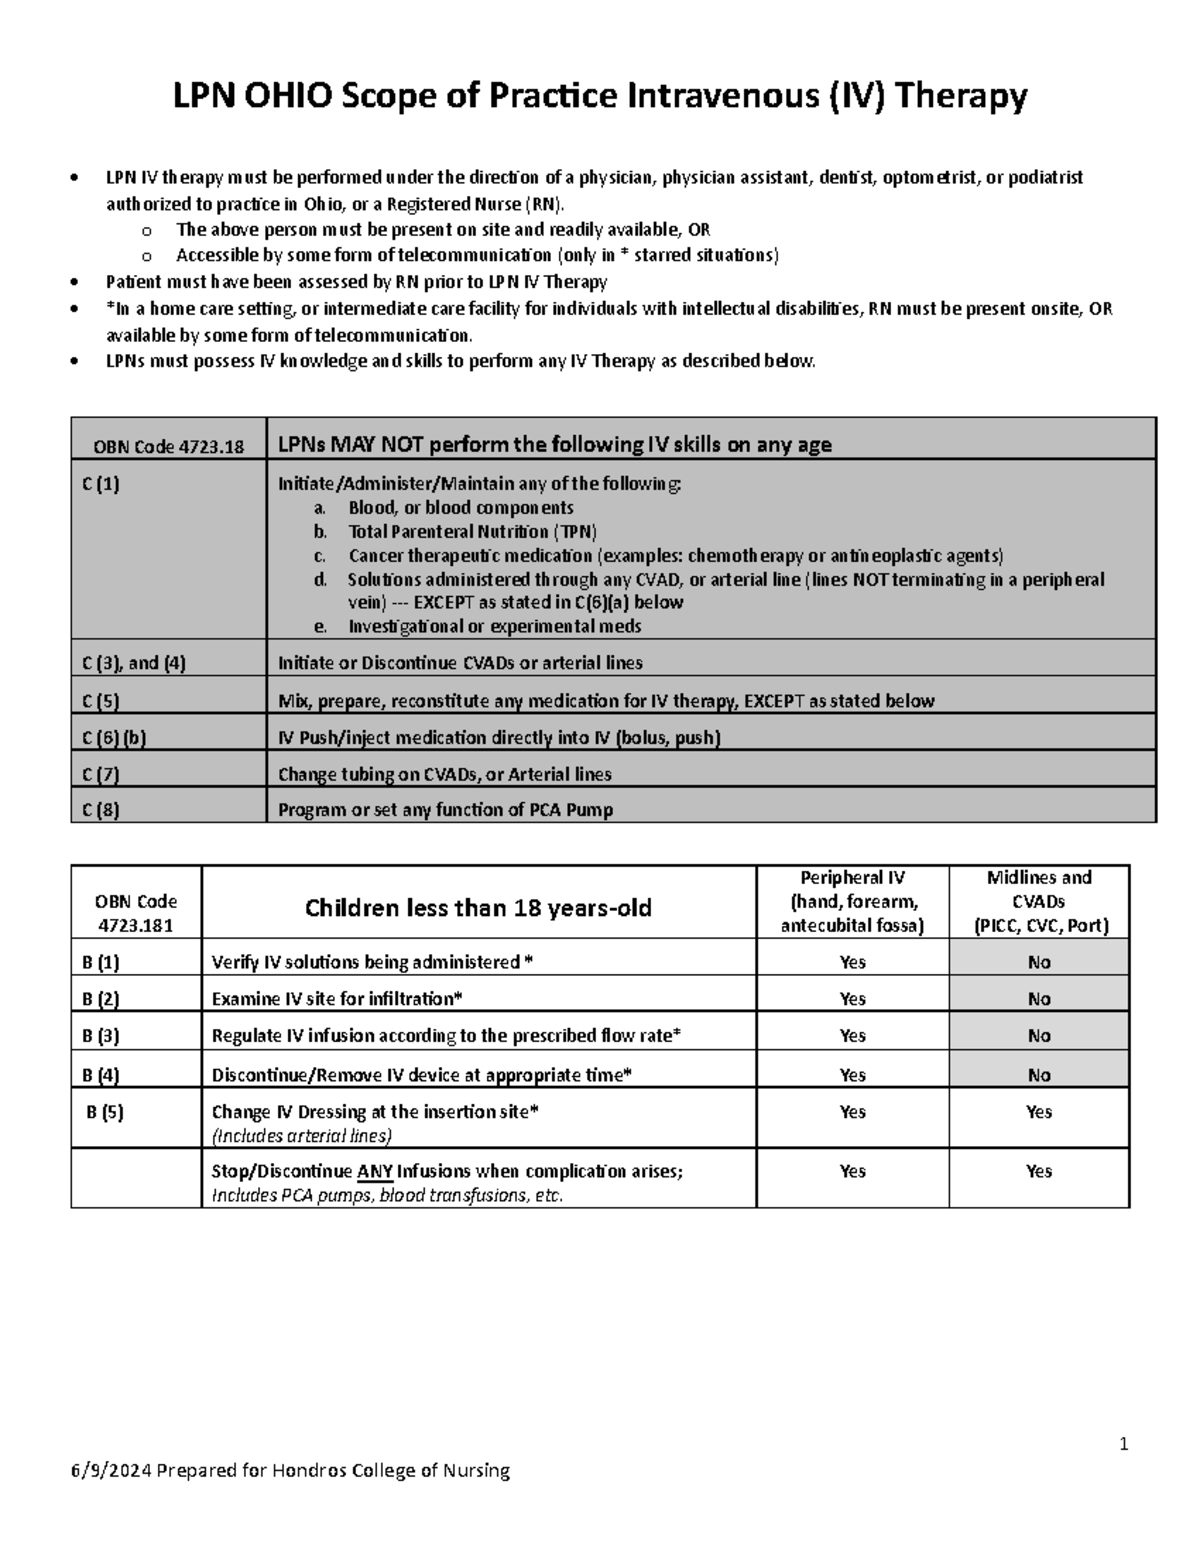
The scope of practice for LPN IV therapy varies significantly depending on your state's nursing board and the policies of the facility where you work. Most states allow licensed practical nurses to administer IV fluids and medications, but there are consistent restrictions that catch people off guard. You cannot initiate central lines, manage TPN through a central line, or administer blood products independently in nearly every jurisdiction. Those tasks require RN licensure or a physician order with specific delegation language. I spent years navigating this landscape across three different states, and the variations are frustrating enough that you will drive yourself crazy trying to memorize every distinction. The core pattern holds everywhere: LPNs can typically hang and regulate IV fluids, administer most IV medications through peripheral lines, and manage IV push medications within formulary limits. Where things get messy is with med-push dosing thresholds and whether your state requires an additional certification beyond the basic LPN license. In Texas, for example, the Board of Nursing allows LPNs to administer IV medications and fluids through peripheral or central lines after completing a board-approved course, but they cannot use certain high-alert medications independently. In Florida, the rules are tighter around IV push medications, and several facilities require a competency verification before they will let you touch an IV line at all. California takes a different approach where hospital policy largely governs what you can do regardless of what the state nurse practice act technically permits.
The Practical Reality of LPN IV Administration
Here is what nobody tells you during orientation: your ability to run IVs is almost entirely dependent on your charge nurse and your facility's standing orders, not just your license. I worked in a long-term acute care facility where the charge nurse could look at you like you were speaking Swahili if you suggested hanging a potassium bolus, even though state law permitted it. Conversely, I was in a small rural hospital where LPNs routinely ran vasopressors through central lines because that is simply how staffing worked there. The actual workflow involves more judgment calls than skills tests. You need to assess whether a peripheral IV is suitable for the medication you are giving, which means understanding vesicant properties and osmolarity. A medication labeled safe for peripheral administration by the manufacturer can become a tissue-destroying event if the IV infiltrates and you continue pushing. I learned this the hard way with a phlebitis case involving vancomycin that I missed because I was rushing between twelve patients and assumed the IV was fine based on a glance rather than a proper assessment. Understanding infusion rates matters far more than anyone admits. Pump programming errors account for a significant portion of IV medication incidents, and LPNs are on the front line for those calculations. When you are running multiple infusions through a multi-channel pump, double-checking the concentration on each bag against the order is non-negotiable. I have seen experienced nurses miss a decimal place in a midazolam drip because they were transitioning from one patient assignment to another without a proper handoff pause.
Common Pitfalls and What They Mean for Your Practice
The biggest mistake LPNs make is assuming that a physician order automatically gives them the authority to do something their scope does not cover. A doctor can order a medication, but if it falls outside your state's defined LPN scope, the order is invalid regardless of who signed it. I encountered this directly when a attending physician wrote an order for an LPN to administer a medication that required an RN assessment component under our state's regulations. The pharmacist caught it at verification, but not before there was confusion at the medication room. Another oversight involves IV site maintenance protocols. LPNs are often responsible for changing dressings, flushing lines, and assessing sites, but the initial insertion requirements differ by state. Some states allow LPNs to insert peripheral IVs after competency validation, while others restrict this exclusively to RNs. Knowing which category your state falls into determines whether you can independently place a new IV or whether you must defer to the nursing staff. There is also the documentation gap that trips up newer LPNs. Your scope may allow you to administer the medication, but the documentation requirements might expect RN-level assessment findings that you are not legally permitted to provide. This creates a situation where you are physically capable of doing the task but cannot fully complete the legal documentation loop. The workaround is straightforward communication with your charge nurse or the attending RN about co-signing requirements and clarification of assessment responsibilities before you start your shift.
Get the Full Details
Workarounds That Actually Work
When you encounter a gray area in your scope, the most reliable approach is to get written policy from your facility's nursing leadership rather than relying on verbal assurances from colleagues. Verbal guidance changes depending on who is having a bad day. A written policy from your director of nursing or clinical manager provides a paper trail and removes ambiguity. I started carrying a pocket reference of my state's nursing practice act provisions related to IV therapy, which helped during policy disputes with surprising frequency. For situations where your state scope is restrictive but patient needs are urgent, the standard protocol involves notifying the RN supervisor and requesting delegate administration or joint verification. This is not a sign of weakness. It is the correct chain of command, and doing it promptly prevents medication errors and protects your license. I once had a code situation where an LPN adminstered a medication outside our facility's defined scope because the attending told them to go ahead and the RN was pulled to another patient. The incident report that followed made it clear that the physician's verbal override did not shield the LPN from disciplinary action. If you are pursuing additional certification in IV therapy, verify what your state actually recognizes before enrolling. Some advanced certifications from private organizations carry weight in certain health systems and not at all in others. The infusion nursing certification from the Infusion Nurses Society is widely respected, but it may not expand your legal scope of practice in your particular state. Understanding the difference between a credential that broadens your legal authority and one that simply makes you more employable saves time and money.
When IV Therapy Scope Falls Apart Completely
There are scenarios where LPN IV practice is essentially nonexistent regardless of what the statute says. Critical care units, emergency departments, and procedural sedation settings frequently restrict IV therapy to RNs or higher through facility policy alone. These restrictions are legal and enforceable because employers can set standards above the minimum regulatory floor. Attempting to work around these limitations by leveraging state scope language will not succeed and can result in termination. Medication administration through existing central lines presents another area of collapse for LPN scope in many facilities. While your state may permit IV medication administration through central lines, hospital infection control and vascular access teams often designate these tasks as RN-only regardless of state law. The rationale usually involves the assessment complexity required before and after administration, which crosses into RN scope territory in their interpretation. The honest assessment is that LPN IV therapy scope exists in a narrow corridor between state regulations, facility policies, and individual competency validations. Narrow enough that continuous education and staying current with your state board's updates is not optional. I recommend setting a calendar reminder every six months to review your state's nursing practice act amendments and your facility's current policy manual. Things change faster than most nurses acknowledge.




