Understanding What You Can and Cannot Do as an LPN in Virginia
The Board of Nursing in Virginia oversees LPN licensure and scope, and it's one of those things that feels straightforward until you're actually standing at a patient's bedside trying to figure out whether a task falls in your lane or someone else's. The regulations are codified in the Virginia Administrative Code, specifically 18VAC90-60, and they map out what licensed practical nurses can perform without direct physician oversight versus what requires delegation or collaborative practice agreements. Most people enter this field knowing the basics: medication administration, wound care, basic assessments. What they don't realize is how much gray area exists between what's theoretically allowed and what your facility's policies actually permit you to do on a Tuesday shift.
Lpn Scope Of Practice In Virginia: The Core Rules
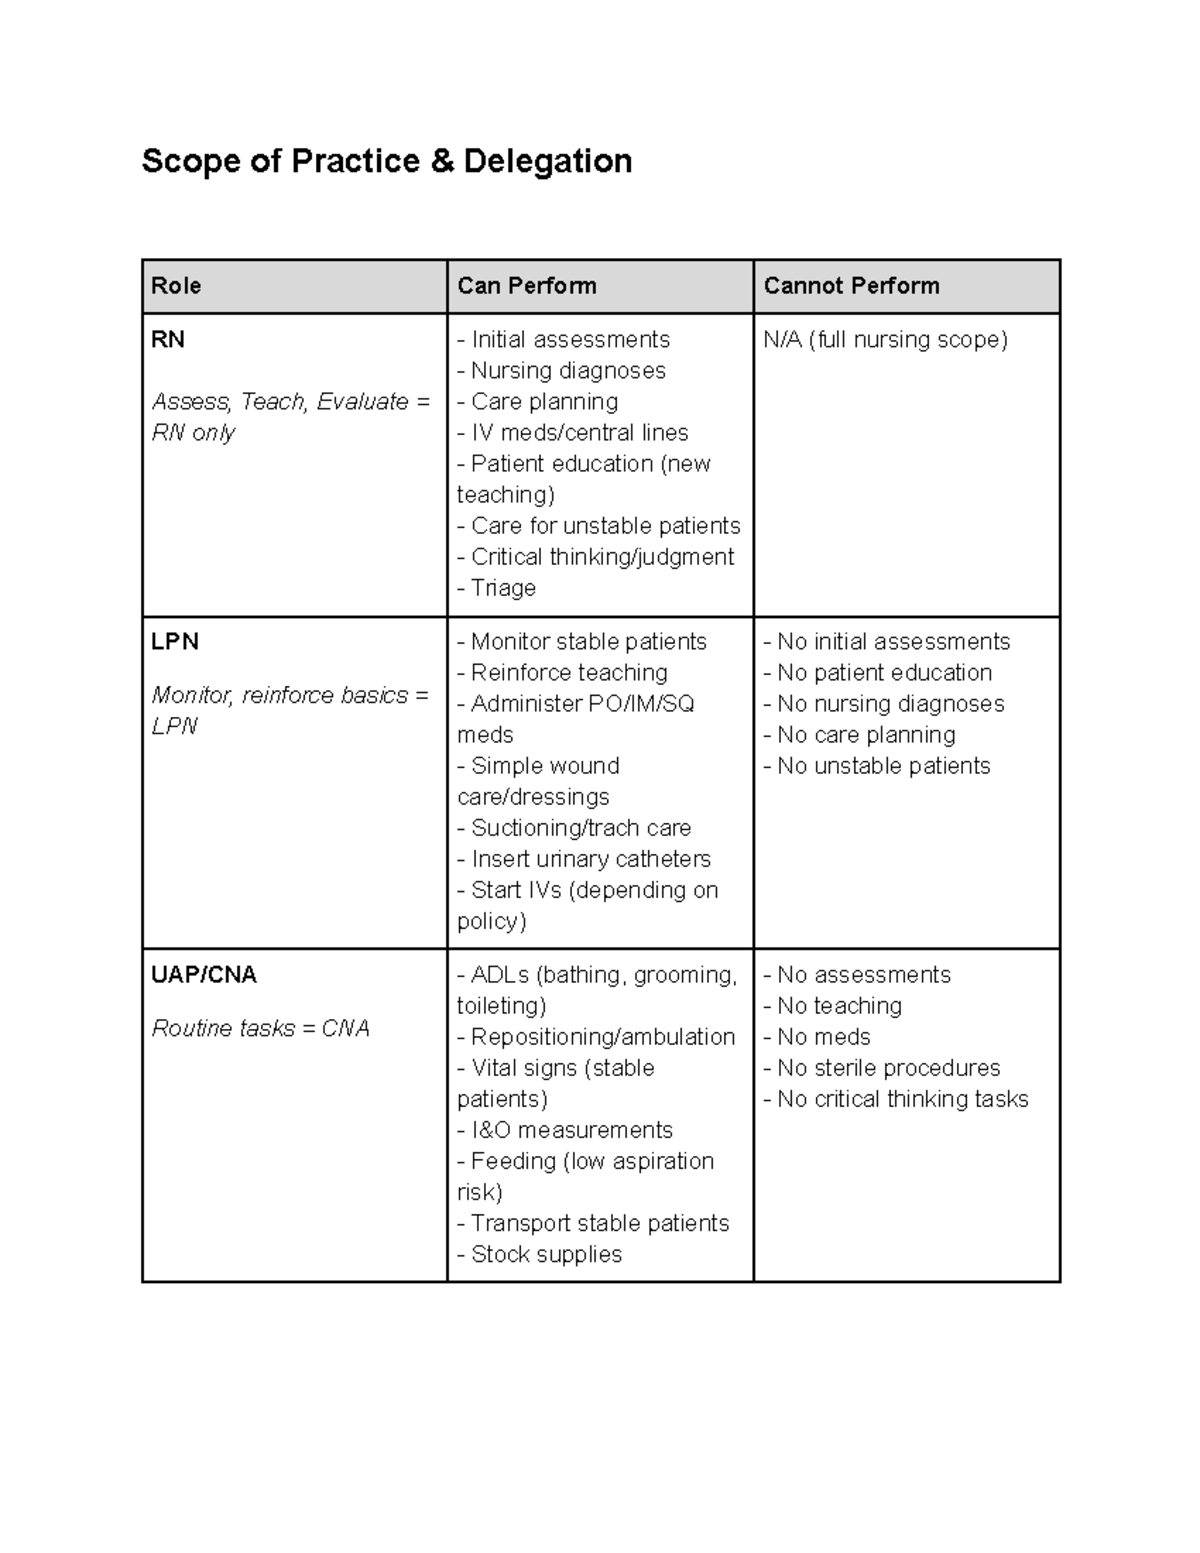
Under Virginia law, an LPN may perform tasks that require a standardized, non-varied procedure. This means predictable outcomes, established protocols, and minimal clinical judgment at the point of delivery. Medication administration falls squarely here. So does routine specimen collection. The key distinction the Board makes is whether the procedure demands ongoing nursing judgment that varies from patient to patient. If it does, you need either direct supervision or a specific order that covers the variance. Vital signs assessment is permitted, but interpreting those vitals and adjusting a care plan based on trends crosses into LPN practice in Virginia territory that gets murky fast. Documenting stable post-op vitals? Fine. Deciding that a dropping blood pressure trend means you should hold a scheduled antihypertensive and call the physician instead? That requires an order under the approved protocols or collaborative agreement framework. I ran into this exact problem last year. A patient on my unit had a series of blood glucose readings trending downward over three hours. The protocol allowed me to recheck and notify the provider, but it didn't explicitly authorize adjusting the insulin drip rate based on those readings. The RN was busy elsewhere, and the attending physician was two buildings away. I could have waited and risked the patient going hypoglycemic, or I could have acted within the delegated order from the admitting physician that covered sliding scale adjustments. I went with the delegated order, documented the rationale, and flagged it with the charge nurse. It took two minutes to verify the order was still active and four minutes to administer the adjustment. The alternative would have been a 45-minute delay while chasing down signatures.
Tasks Explicitly Permitted for LPNs
Medication administration is the big one, and it covers oral, topical, intramuscular, subcutaneous, and intravenous routes in most facility contexts. Virginia doesn't restrict IV meds by route alone, but the administering facility must have policies in place and the LPN must have demonstrated competency. That's why you'll see some hospitals allowing LPNs to run antibiotics through peripheral IVs while restricting them from vesicants or pressors. The Board doesn't dictate which medications you can give. Your employer does. Dressing changes on clean and surgical wounds are standard. The nuance comes with wound vacs and complicated debridement. Basic wound vac management, like changing the canister or noting alarm triggers, is generally acceptable. Initiating a new wound vac order or performing sharp debridement is not. I've seen LPNs in long-term care settings handle negative pressure therapy changes without issue because the SNF policy was clear and the nursing director had signed off on the training. Same setup in an acute care hospital and you'd get pushed back by the wound care team every time. Catheter insertion and urinary drainage management fall within scope. Starting a straight cath on a male patient? That's where it gets harder. Most facilities restrict that to RNs or PAs because of the anatomical complications that can arise. I worked with an LPN who successfully completed a separate certification course for male straight catheterization and got her facility to adopt a policy allowing it. It wasn't about the Board's rules, it was about convincing the medical staff that she had the competency documentation to back it up.
Get the Full Details

What Requires Direct Supervision or Delegation
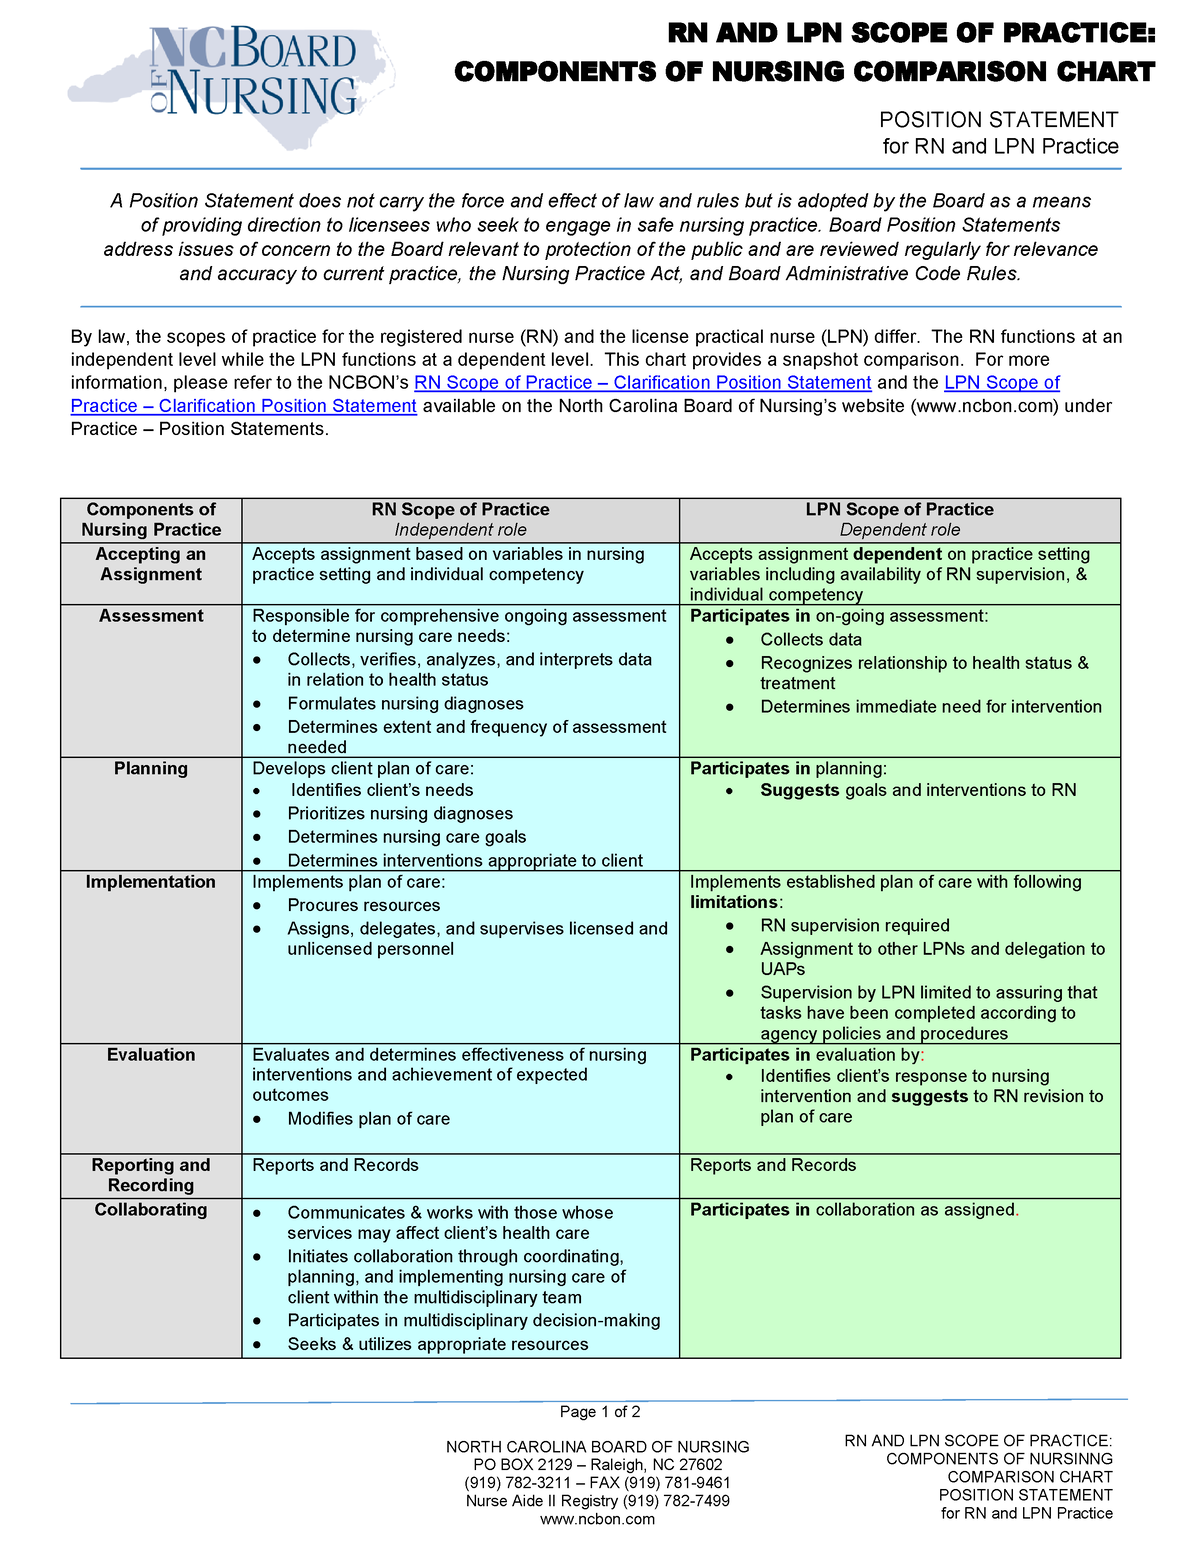
Initial patient assessments are the classic boundary. An LPN can collect data during an admission, but the comprehensive assessment that establishes the plan of care must come from an RN, physician, or NP. Here's the counter-intuitive part that trips people up: you can perform focused assessments all day long. Blood sugar checks, lung sounds, neurological screens on stroke patients, pain assessments. These are assessments. But they're not the initial comprehensive assessment that triggers the nursing care plan. The distinction matters because some newer LPNs think a focused neuro check after a fall constitutes an assessment they can document as the primary reason for physician notification. It's documentation, yes, but it's not the assessment that justifies changing the level of care or discharge planning. Teaching is another area where people misunderstand their role. You can reinforce teaching that someone else designed and delivered. Patient education on how to use an inhaler after the respiratory therapist has already done the initial session? That's reinforcement, and you're clear to do it. Creating a diabetes education curriculum from scratch and delivering it to a new diagnosis patient? That requires an approved program structure and usually delegated authority from an RN or educator. LPN practice in Virginia also intersects with medication reconciliation. You can assist with medication reconciliation by gathering current medication lists and verifying administration records. But the actual reconciliation process, which involves identifying discrepancies and making clinical recommendations to the prescriber, is an RN-level function. I've seen this cause problems at transition points. An LPN will compile the med list perfectly and then stop short of the reconciliation step because the policy says they need an RN sign-off. Meanwhile the patient sits on the unit for six hours waiting for the RN to complete the check before discharge can proceed. The workaround is having LPNs flagged in your EHR system so the charge nurse knows to prioritize routing their discharge packets to an RN for the reconciliation sign-off specifically.
Common Pitfalls That Get LPNs in Trouble
The biggest issue I see is scope creep that starts small and compounds. An LPN agrees to do something once because it seems reasonable and the RN is overwhelmed. Then it becomes the new normal. Six months later there's no formal delegation on file and a surveyor asks about it. The Board doesn't care that everyone thought it was fine. They care about the documentation trail. Another pitfall is assuming that working in a setting where other LPNs do a task means the task is within your scope. I found an LPN at a surgery center attempting pre-operative assessments that included IV site selection and fluid order verification. Her coworkers had been doing it for years, and the surgeon was fine with it. The problem was the facility's nursing policy explicitly reserved pre-op assessments for RNs. She got a written warning after a joint Commission survey pulled her charts. The precedent set by her peers didn't protect her because policy governs, not custom. Virginia also has specific rules about LPNs working in physician offices versus hospitals versus long-term care. The scope itself doesn't change between settings, but the allowable tasks are shaped by the facility type and the delegating physician's policies. An LPN in a family practice clinic might be allowed to do things that would be completely off-limits in a psychiatric hospital. The reverse is also true. Don't transfer assumptions from one work setting to another without verifying the local policies apply.
The documentation requirement is worth emphasizing because it's where most disputes get resolved or lost. If a task requires delegation, the delegation needs to exist in writing or in the electronic system before you perform the task. Verbal delegation from a charge nurse counts in the moment, but if it's not documented in the chart within the facility's timeframe, it effectively didn't happen during an audit. I keep a personal log of every delegated task I perform along with the delegating provider's name and the date. It takes thirty seconds per entry and has protected me twice when retrospective questions came up about tasks I performed months earlier.

When to Push Back
If someone asks you to do something outside your scope, the conversation doesn't have to be dramatic. You can say you need to verify the delegation or check the policy before proceeding. That gives everyone time to figure out whether it's actually permissible or whether it's just someone being convenient. I've had physicians ask LPNs to initiate central line care bundles, and the answer is always no unless there's a specific collaborative agreement that covers it, which is rare. The physician usually just needed the task done and didn't realize the scope boundary. A quick policy reference and a suggestion to assign it to an RN solves the problem without anyone feeling attacked. The one scenario where pushing back requires more assertiveness is when patient safety is clearly at risk because of scope violations. An LPN asked to administer a chemotherapeutic agent through a peripheral line without the appropriate training and verification should refuse and escalate. Not with drama, just with a clear statement that you're not credentialed for that task and it needs to go to someone who is. Documentation of the refusal and the escalation protects you more than going along with something you know isn't covered.
Resources for Staying Current
The Virginia Board of Nursing publishes the relevant regulations directly on their website. The administrative code updates periodically, and the Board sends notices to licensees about changes. You should sign up for those notifications rather than relying on memory or colleague advice. Policy drift is real, and what was acceptable three years ago may have been narrowed by a recent amendment. Your employer's policy manual is equally important and often more restrictive than the Board's rules. Always check both. The Board sets the floor, not the ceiling. Your facility can impose stricter limitations without violating any regulation, and they routinely do. Professional organizations like the Virginia Nurses Association provide scope guidance documents that translate the regulations into practical terms. They're not legally binding, but they reflect how the Board typically interprets the rules in enforcement situations. That interpretive guidance is worth more than the raw regulation text when you're facing a borderline question.