What You Actually Need to Know About LPN Scrub Nurse Training
LPNs cannot function as scrub nurses in most operating rooms. That is the baseline fact that trips people up every time this topic comes up. The scrub role requires passing instruments, maintaining the sterile field, and anticipating the surgeon's needs during an active procedure. Most states and hospital credentialing committees do not allow licensed practical nurses to fill that position. I have seen it happen anyway. A mid-sized surgical center in Texas hired an LPN with significant perioperative experience as a "scrub tech" because they were short-staffed on a Friday night. The circulating RN flagged it the same day, and the hospital's risk management team was in the room before the first incision was closed. The LPN had the hands for it, but legally they were practicing outside their scope. I had to write up a situation report that Monday. It was not fun.
Lpn Scrub Nurse Training Realities
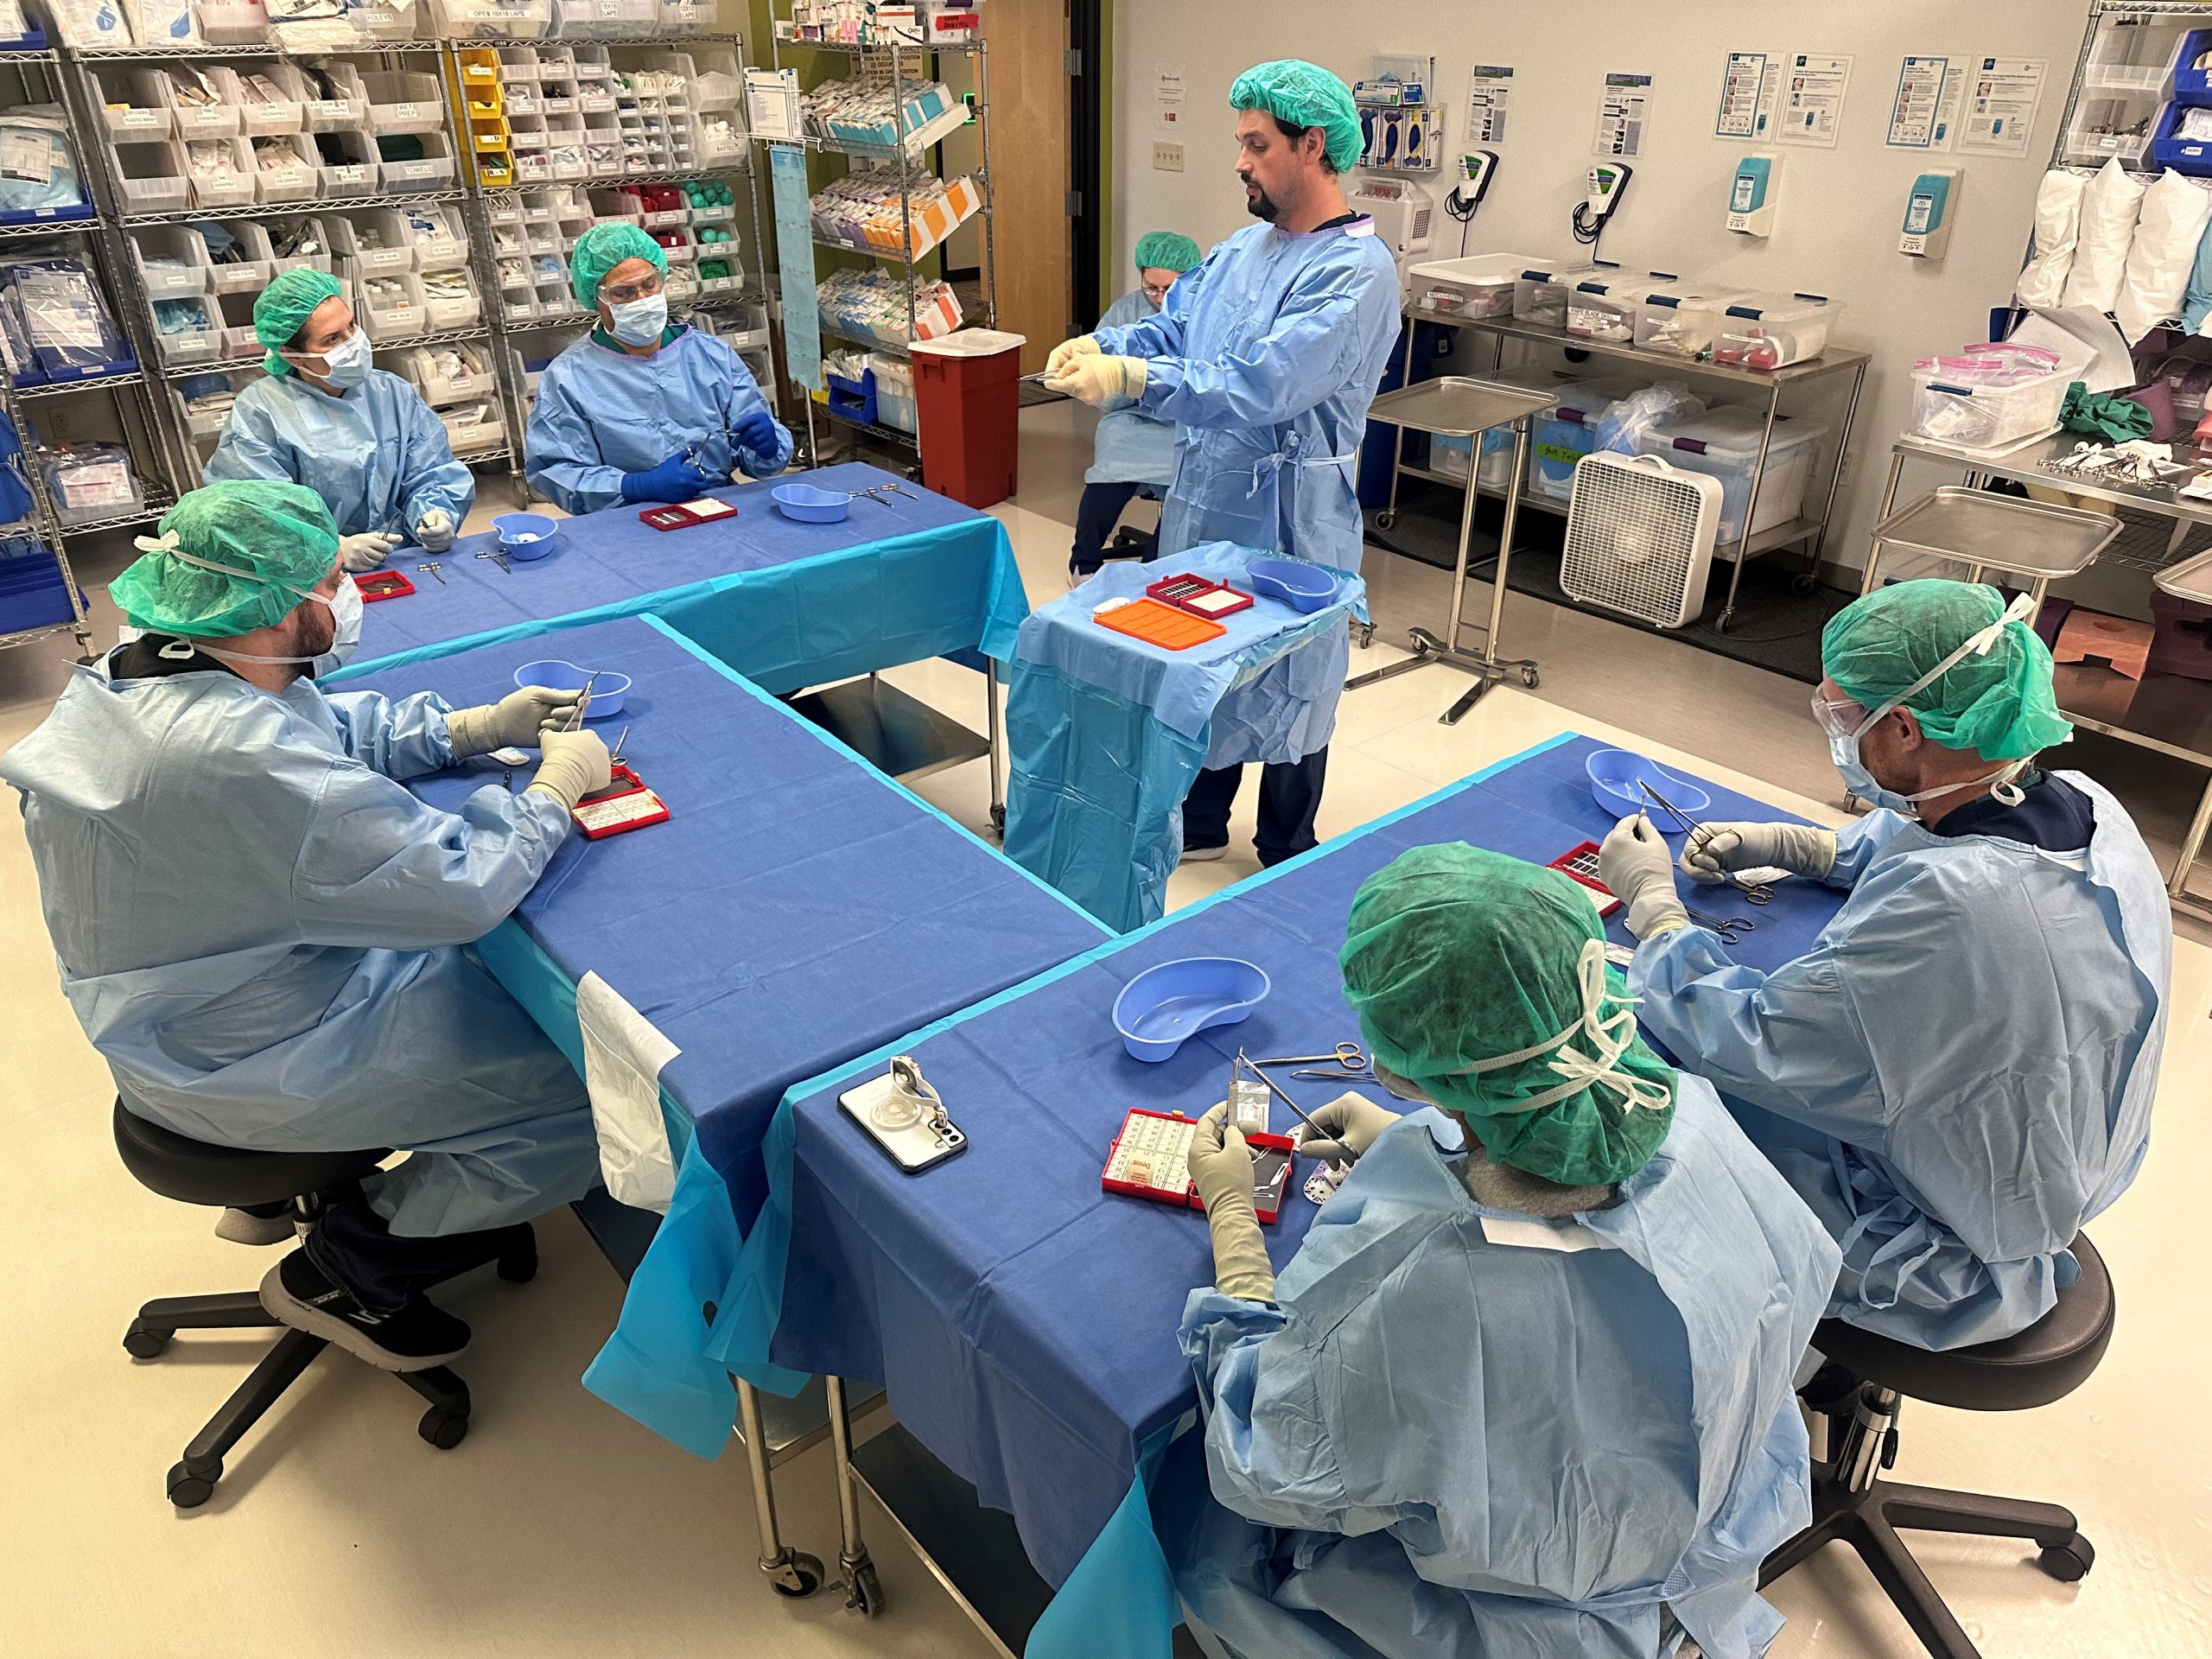
If you are looking at Lpn Scrub Nurse Training as a career pathway, the honest answer is that it depends entirely on your state's nurse practice act and the specific hospital's policy. There is no single national standard. Some states permit LPNs to scrub in ambulatory surgery centers under direct physician supervision. Others prohibit it completely across all facility types. The difference between "allowed" and "not allowed" often comes down to whether the procedure is classified as minor or major, and whether the facility holds an Accreditation Association for Ambulatory Health Care (AAAHC) certificate or a Joint Commission accreditation. The training itself, when it exists, typically covers instrument identification, surgical counts, draping techniques, and sterile technique maintenance. A standard program runs 16 to 40 hours depending on the employer. Some hospitals embed the training into an internal orientiation period that spans six to eight weeks. You will be paired with an experienced surgical technologist or RN scrub person who evaluates your competency before you are cleared to work independently. The evaluation usually involves watching you set up at least three different cases correctly, performing two full counts without errors, and demonstrating proper gowning and gloving under time pressure. Here is something most training materials do not emphasize. The instrument tray setup is only about thirty percent of the job. The remaining seventy percent is situational awareness. You need to know which suture a general surgeon prefers for a laparoscopic cholecystectomy before he asks. You need to recognize when the anesthesiologist is about to need a particular medication and have it ready on the back table without being told. This skill comes from repetition, not from a classroom module. I once trained someone who could recite every instrument name backward and forward but froze the first time the surgeon changed the plan mid-case and requested a different retractor. She stood there holding a Laparotomy Pad for twenty seconds before anyone noticed. We do not talk about that much, but it sticks with you.
There is a common misconception that scrubbing is just handing instruments in order. It is not. The physical positioning matters more than most newcomers realize. If you are standing too far forward, your elbow brushes the sterile field and you have compromised it. If you are standing too far back, you are reaching across open space and creating an unconscious tension that shows up as delayed instrument passes. The ideal stance is roughly twelve to eighteen inches from the instrument table, elbows bent at about ninety degrees, forearms parallel to the floor. Your hands stay above your waistline at all times. This is not theory. I have watched three separate new hires develop shoulder and neck issues within their first six months because they were hunched over the Mayo stand trying to compensate for poor table height. One advantage of LPN background in this role is medication administration experience. LPNs understand dosage calculations, IV access, and medication protocols better than most entry-level surgical technologists. In a busy orthopedic case where antibiotics need to be redosed or bone cement is being mixed, that knowledge translates directly. The limitation is that knowing how to prepare a medication does not authorize you to administer it in the sterile field. There is a hard boundary between what you can do as an LPN and what belongs to the RN or anesthesia provider, and crossing it during surgery is one of the fastest ways to lose your credentials and face a board complaint. If your goal is specifically to work in the scrub role and your state does not permit LPNs to scrub, there are alternative pathways. The Surgical Technologist certification through the National Center for Competency Testing (NBSTSA) is the most direct route. The pre-operative technician program at an accredited community college usually takes one academic year and covers the same core competencies. Some hospitals offer paid apprenticeship tracks where you work as a sterile processing technician first and transition into the OR over twelve to eighteen months. It is slower, but it keeps you employed while you train.
Get the Full Details

The compensation difference between an LPN working med-surg and an LPN working in sterile processing is roughly eight to fourteen dollars per hour depending on region. Breaking into the actual scrub role as an LPN where permitted typically adds another six to ten dollars on top of that. In metropolitan areas with surgical tech shortages, some facilities have been known to pay LPN scrubs competitively with CSTs just to keep bodies in the room. That market is tightening though, especially after the post-2022 staffing crisis forced several hospital systems to tighten their credentialing policies. The hardest part of this work is not the technical skill. It is the physical endurance. A twelve-hour case means standing the entire time, often in lead aprons for fluoro cases, with minimal breaks. The mental load of maintaining focus while simultaneously managing instrument flow, count accountability, and surgeon preferences is significantly higher than most people expect. I have seen competent LPNs leave the profession within the first year because they underestimated the stamina requirement, not because they could not learn the instruments. If you want concrete training resources, the Association of periOperative Registered Nurses (AORN) publishes free guideline documents on surgical counting and sterile technique that apply regardless of your credential. The AST (Association of Surgical Technologists) offers a foundational textbook that many programs use as their core reference. Several hospital systems also publish internal competency checklists online if you search for their perioperative onboarding materials. You will not find a single definitive "LPN scrub nurse training download" because no such universal program exists, but the component materials are widely available if you know where to look.