What LSVT BIG Actually Is and Why People Mess It Up
LSVT BIG is a motor retraining program for Parkinson's disease, derived from the same principles as LSVT LOUD. It targets hypokinesia — the inability to produce appropriately sized movements. The "Big" part isn't casual naming; it literally trains patients to recalibrate their internal perception of what normal movement looks like. Most people who hear about LSVT Big Daily Exercises just look up a YouTube video and try to copy it. That's where things fall apart quickly. The core concept is amplitude-based training with a specific emphasis on effortful, large-range movements repeated enough times to create a new baseline. In practice, this means every activity — walking, standing up, reaching, turning — gets performed at a consciously amplified scale during the intensive treatment phase. The daily home practice is non-negotiable if you want retention. Without it, the gains from therapy sessions dissipate within weeks.
The Lsvt Big Daily Exercises Breakdown
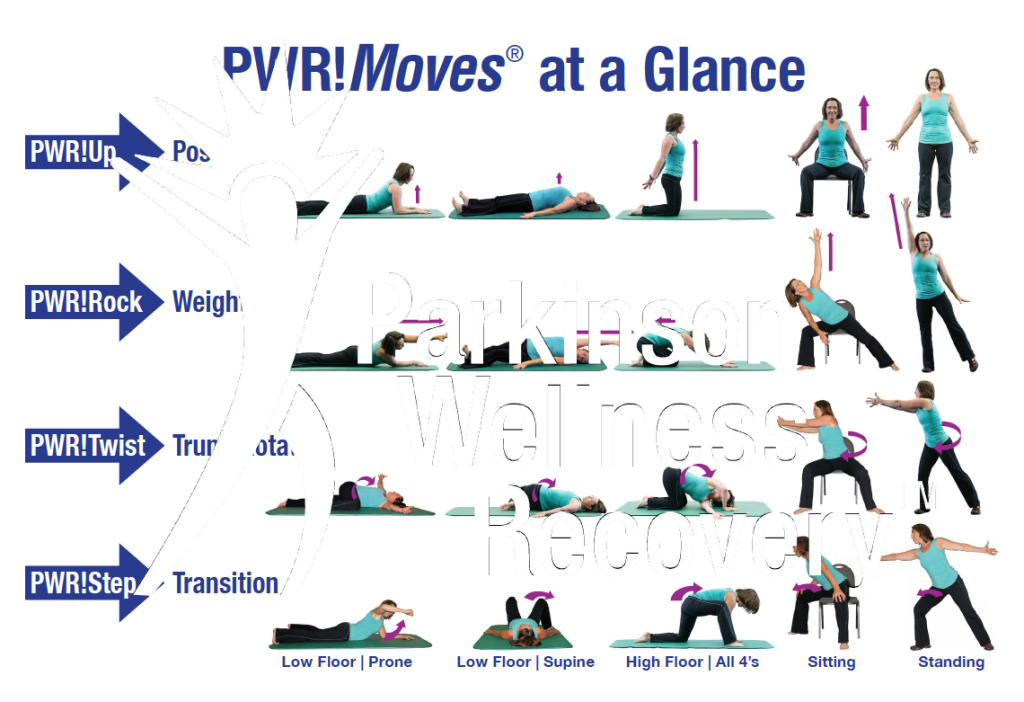
The daily exercise routine typically includes a set of core movement patterns repeated multiple times per day. Here's what that actually looks like in real life, not the brochure version. Big walks: take steps that are noticeably larger than your normal gait. Not a power walk. Just bigger. Aim for 30 big steps, twice a day minimum. The key is heel strike first, then a full roll through to toe-off. Most people skip the heel strike and just lunge forward, which defeats the purpose and puts shear stress on the knees. Big stands: practice rising from a chair without using your arms if you can manage it, or at least using minimal arm support. Stand up tall, hold for three seconds, sit back down with control. Do five repetitions. The controlled descent matters as much as the rise. Lowering yourself quickly is the default pattern for someone with bradykinesia, and reinforcing that pattern daily is why some people don't see progress.
Big arm swings: while walking, swing your arms with amplitude that feels exaggerated. I've seen patients swing their arms so hard they end up sore in the shoulders because they're using momentum rather than muscle control. The swing should come from the hip and torso rotation, not from yanking your arms around like you're trying to shake water off your hands. Big reaches: stretch your arms overhead or forward to a point that feels like you're one more inch away from touching something. Hold for two seconds. Return with control. Ten repetitions. This one gets skipped the most because it feels silly doing it in front of other people. That's fine. Do it in private until the neural pathway has had enough repetition to feel normal again. Big turns: pivot deliberately. Small tight turns are the enemy. Wide arcs, shift your weight fully onto one foot before rotating, plant the other foot clearly. Three big turns in each direction. People with Parkinson's tend to do miniature U-turns that don't actually relocate the center of gravity, which means they're still balanced precariously the whole time.
Get the Full Details

I had a patient once who did all of these but kept her eyes locked on the floor the entire time. She was so focused on foot placement that she wasn't engaging the full-body awareness the protocol requires. The fix was simple but frustrating for her: she had to practice while looking straight ahead at a fixed point on the wall. It felt terrifying at first. After a week, her balance actually improved because she was using visual feedback instead of compensating with tension.
Why Repetition and Effort Are the Actual Mechanism
LSVT BIG works on the principle of dose-dependent neuroplasticity. You need high repetitions at high effort levels to retrain the basal ganglia's movement scaling. The number isn't arbitrary. The original protocol calls for at least 150 repetitions of key movements per session, and the home practice is designed to keep that volume going between clinic visits. Here's a detail most guides skip: the effort has to be genuinely effortful. If you're going through the motions without feeling like the movement requires actual work, you're not hitting the amplitude threshold needed for recalibration. The movement should feel too big. If it feels normal, you're underdoing it. This is the perceptual distortion that Parkinson's creates, and it's the exact thing the treatment targets. I measured this once with a patient who insisted she was doing "big" movements. Using a phone accelerometer, her arm raises were averaging 45 degrees of elevation. The target was 90 to 110. She genuinely perceived her movements as large. That's the hypokinesia talking, and it's why self-report is unreliable in this program. Objective measurement matters more than you'd expect.
Pitfalls That Kill Progress
Skipping days. The home practice is four times a day, fifteen minutes per session, during the four-week intensive phase. That's sixty minutes total per day. People underestimate how hard that is to sustain. Consistency beats intensity. Doing thirty minutes spread across the day is better than one ninety-minute marathon on Sunday. Compensating with momentum. Swinging too hard, using furniture for support when you don't need it, rushing through repetitions. All of these shortcuts bypass the neural retraining. The program only works when you're doing the movement the hard way, slowly, with controlled amplitude. Stopping when it stops feeling hard. As you progress, movements that used to require maximum effort start feeling easier. That's the program working. But some people interpret that as a signal to reduce the amplitude, which reverses the gains. The rule is simple: if it feels easy, make it bigger. The amplitude target doesn't drop just because your perception catches up.

Another thing I've noticed repeatedly: people focus on the big movements and ignore the subtle ones. Bed mobility. Rolling over. Getting out of bed. Transferring from lying to sitting. These are where falls actually happen, and they don't get the same attention in home practice routines. I added a specific "big roll" and "big sit-up" sequence to my patient's routine after she had a near-fall getting out of bed one morning. It took two weeks of deliberate practice before she stopped gripping the nightstand like a lifeline.
When LSVT BIG Doesn't Work Well
Advanced Parkinson's with significant postural instability. If someone is already falling regularly and has poor trunk control, the high-amplitude movements can increase risk before they improve it. In those cases, a modified approach with smaller amplitude targets and more balance-focused exercises is safer. Physical therapists familiar with Parkinson's can adjust the protocol accordingly. Cognitive impairment that prevents consistent home practice. The program requires understanding, memory, and self-monitoring. If someone can't track their own movement size or remember to do the exercises multiple times a day, the benefits drop significantly. Caregiver involvement can partially offset this, but it's not the same as intrinsic motivation driving the repetitions. Non-Parkinsonian atypical parkinsonism. LSVT BIG was specifically designed and studied for idiopathic Parkinson's disease. Cases like MSA, PSP, and CBD respond differently to amplitude training, and pushing hard on big movements in those populations can sometimes worsen symptoms or cause fatigue without meaningful carryover. That's not a flaw in the program, it's a limitation of the evidence base.
A Practical Scheduling Approach
Don't try to do everything at once. Anchor your sessions to existing routines. Morning big stands right after you brush your teeth. Big walks during your afternoon coffee break. Big reaches while waiting for the microwave. Big turns when you're moving from room to room. This isn't about adding more time to your day, it's about embedding the exercises into movement you're already doing. Track your repetitions. Not with a clinical timer, just a mental count or a simple notebook. If you're not doing the numbers, you're not getting the dose. Thirty big walks a day split into two sessions is a realistic minimum. Anything less is maintenance at best. The program takes about four months to show stable, long-term results if you do the home practice consistently. After the intensive four-week phase, you transition to a maintenance schedule, but even then, dropping below a few sessions per week will cause regression. This isn't a quick fix. It's a sustained behavioral change that requires treating movement retraining as a daily priority, not an occasional reminder.