Understanding Lumb O Medical Term in Clinical Practice
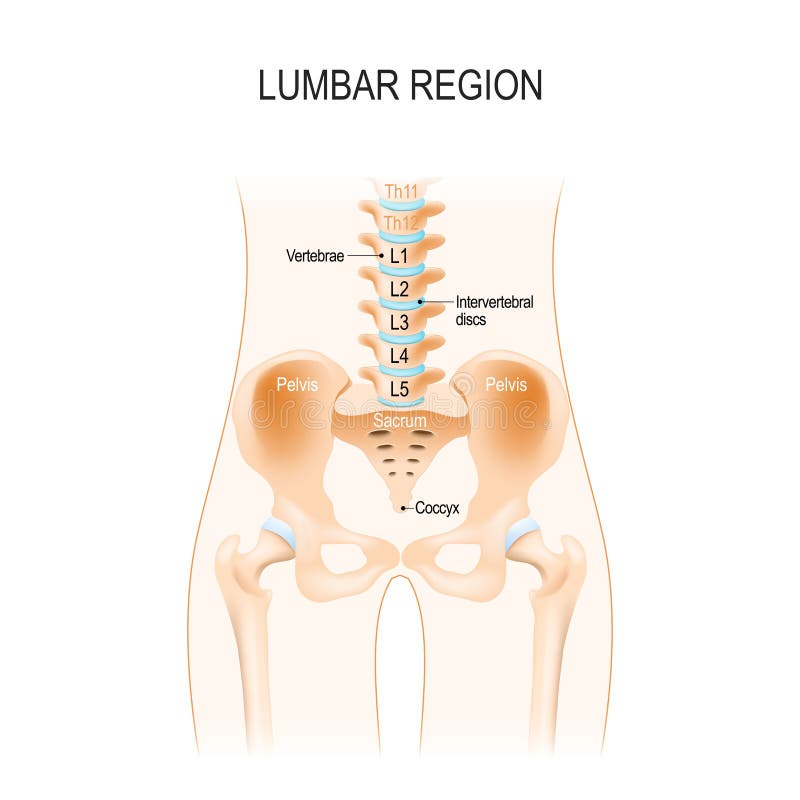
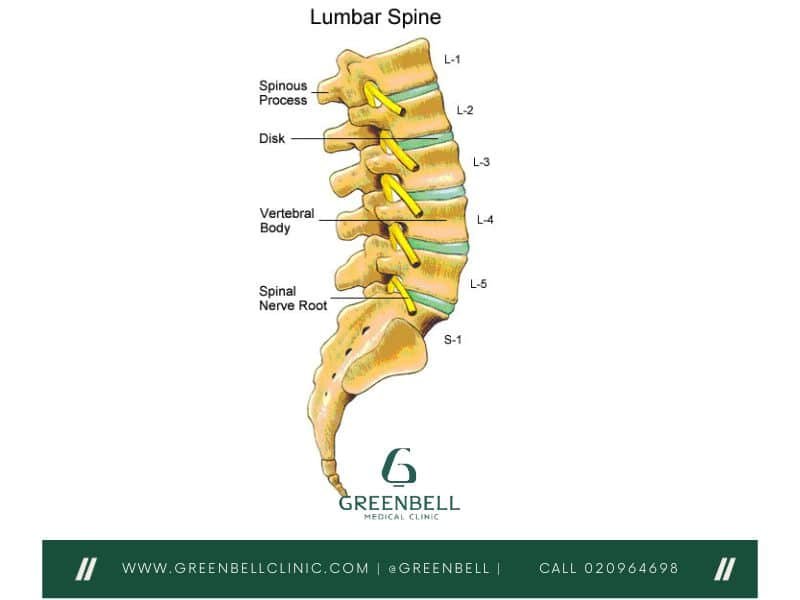
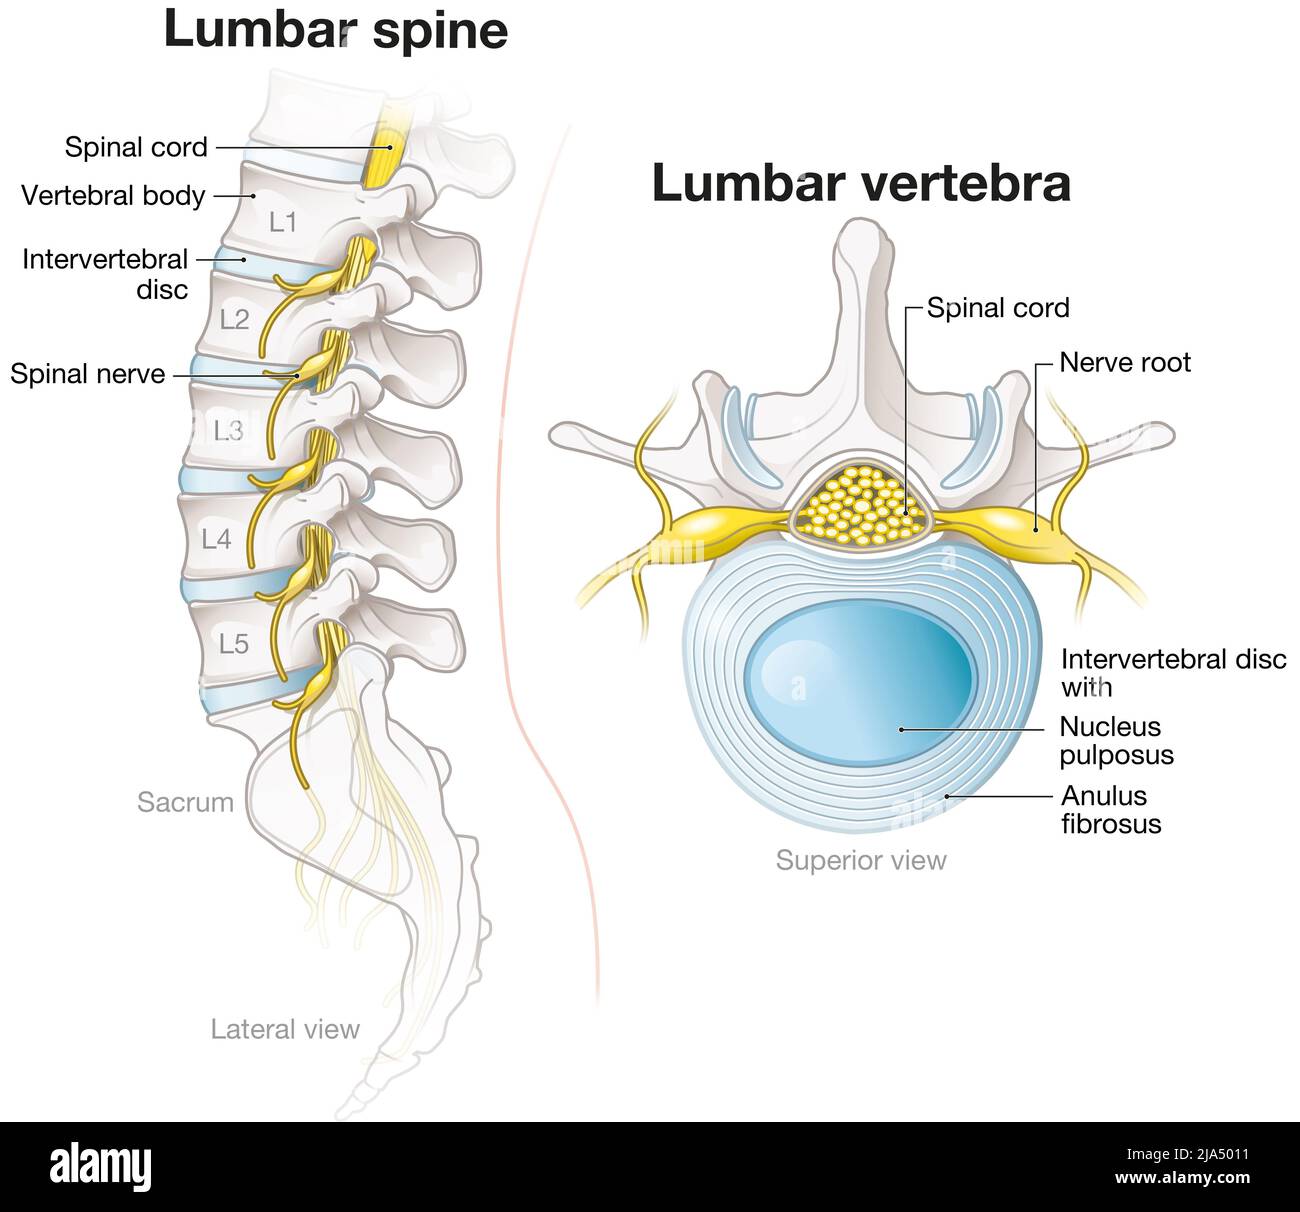
The term comes up occasionally in specialty clinics where documentation standards vary between institutions. I first encountered it while reviewing a chart that used non-standard abbreviations across multiple departments. The patient had been seeing three different specialists who each documented the same condition differently, creating confusion about the actual diagnosis and treatment plan. In most contexts, this refers to lumbar region assessments or lower back evaluations. The abbreviation appears in some electronic health record systems, though it is not part of standard medical coding like ICD-10 or SNOMED CT. When you see it in documentation, it typically indicates imaging orders, physical therapy referrals, or surgical consultations related to the lumbar spine. The term gained some traction in regional hospital systems during the early 2020s when several healthcare networks attempted to standardize their internal documentation. The problem was that different institutions interpreted it differently. Some used it for diagnostic imaging only. Others applied it to treatment procedures. This inconsistency created billing complications and insurance claim denials that I dealt with regularly.
How to Use Lumb O Medical Term Correctly
If your organization uses this terminology, there are specific protocols to follow. Documentation should include the full clinical context, not just the abbreviation. When ordering lumbar MRI studies, specify the exact vertebral levels being evaluated. For physical therapy referrals, include functional limitations and expected outcomes. This level of detail reduces ambiguity and prevents the kind of back-and-forth communication that delays patient care. I learned through experience that generic documentation using only Lumb O Medical Term without supporting details creates problems during peer reviews and audit processes. One particular case involved a patient who needed surgical consultation. The referring physician documented only the abbreviated term. The surgeon requested additional imaging and clinical notes before proceeding. This added three weeks to the patient's timeline and created unnecessary frustration for everyone involved.
Common Pitfalls and How to Avoid Them
The biggest mistake is assuming universal understanding. Not all providers recognize this terminology. When communicating with outside specialists, include the complete clinical picture. Document the specific symptoms, duration, response to previous treatments, and any red flag findings. This approach takes slightly more time initially but prevents the delays that occur when receiving providers need clarification. Another issue involves billing and coding compliance. Insurance companies require specific documentation to process claims related to lumbar spine evaluations. Using non-standard abbreviations without proper supporting documentation can result in claim denials or requests for additional information. I have seen claims delayed by two to four weeks because the initial documentation did not meet payer requirements. Including detailed clinical notes and standard coding terminology alongside any organizational abbreviations helps avoid these problems.
Get the Full Details

Limitations and When to Use Alternatives
This terminology has significant limitations. It is not recognized by major medical classification systems. Many electronic health record platforms do not have built-in templates or order sets for it. Cross-institutional communication becomes difficult when different organizations use conflicting definitions. For these reasons, I recommend using standard terminology like lumbar spine evaluation, L-spine imaging orders, or lower back assessment in most clinical situations. When standard terms are not appropriate, such as in institutional documentation where Lumb O Medical Term has established meaning, ensure all providers understand the definition. Create clear documentation guidelines. Train staff on proper usage. Review charts periodically to maintain consistency. These steps reduce errors and improve communication, though they require ongoing effort to sustain. The reality is that medical documentation should prioritize clarity over brevity. Abbreviations may save time in individual chart entries, but they create problems during care transitions, legal reviews, and quality assurance processes. Using complete, unambiguous language protects both patients and providers. This approach may feel slower initially, but it prevents the complications that arise from miscommunication.
Practical Tips for Implementation
If your organization continues using this terminology despite the limitations, establish clear protocols. Document the definition in your clinical glossary. Include examples of proper usage. Review charts monthly for compliance. Address inconsistencies promptly. These practices help maintain standards, though they require administrative oversight to be effective. For individual providers, develop a personal checklist for lumbar spine documentation. Verify that all necessary components are included before finalizing orders. Confirm that receiving providers understand the clinical context. Follow up on results and recommendations. This systematic approach reduces errors and improves care coordination, even when organizational terminology creates challenges.