What lumbar traction actually does to your spine
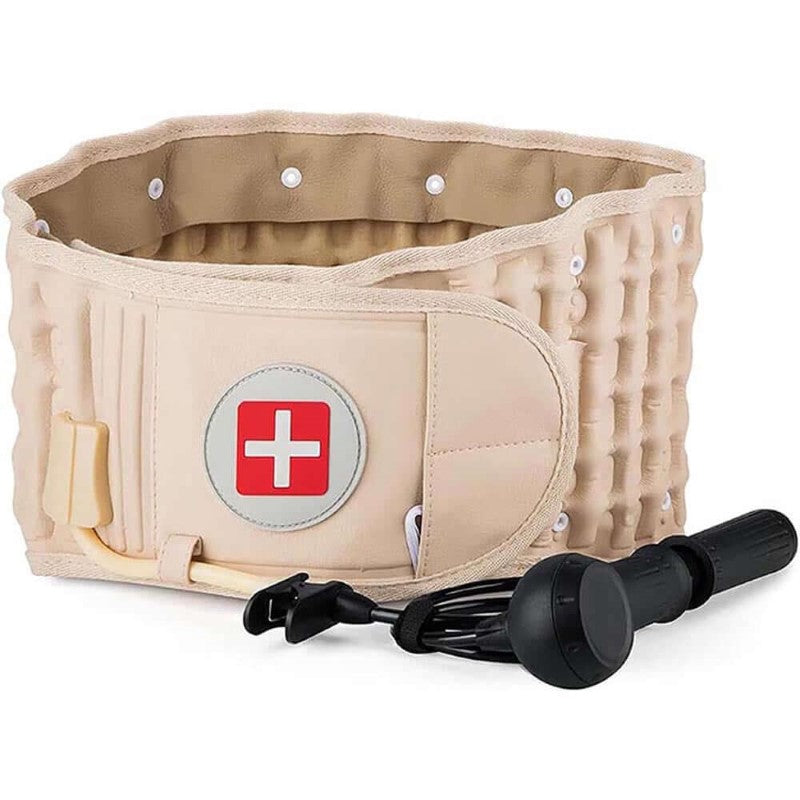
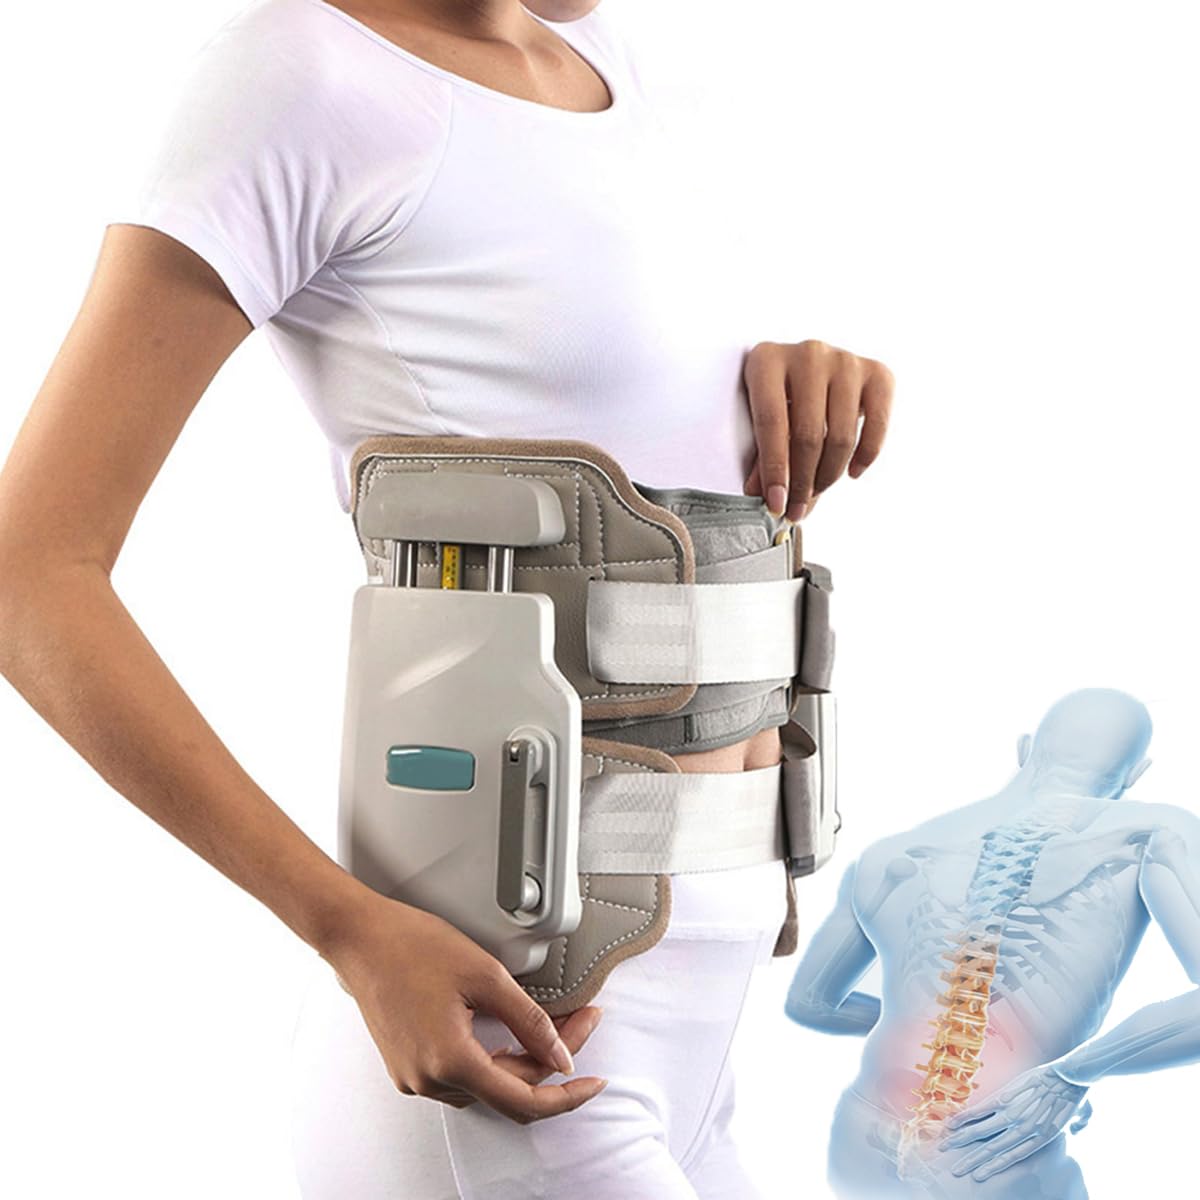
A Lumbar Traction Belt applies a sustained or intermittent pulling force along the axis of your lower spine. That force creates negative intradiscal pressure, which can temporarily reduce the load on compressed disc structures and relax guarded paraspinal muscles. It doesn't fix anything permanently, but it can give you a workable window of relief when used correctly. I used to sell a lot of these to physical therapy clinics back in the day. Most patients who bought them ended up using them wrong and wondering why nothing changed. The problem isn't the belt. It's how people dial in the settings.
How to set up a Lumbar Traction Belt properly
Start by measuring the widest part of your pelvis, not your waist. Most belts anchor around the iliac crests and the lower rib cage. If the strap sits too high, you're pulling on your ribs and the force doesn't transfer down to the lumbar segment you actually want. I had one patient who complained of zero relief for three weeks straight. Turns out her belt was anchored completely above L4. After repositioning it so the center pad sat right over the lumbar curve, she reported significant improvement within two sessions. Here's the part nobody tells you: traction force is not linear with discomfort. More force does not equal better results. The typical effective range for home units sits between 25 and 50 pounds of pull force. I've seen people crank theirs to the max setting and end up with aggravated symptoms because the surrounding musculature just braced harder against the stretch. Start at the lowest setting that produces a mild pulling sensation in the lower back. Hold for 15 to 20 minutes. Work your way up gradually over several weeks, not days. The cycle pattern matters more than most people realize. Intermittent traction with a duty cycle of roughly 10 seconds on and 2 seconds off tends to produce better muscle relaxation than continuous pull. The brief release periods allow the tissues to adapt rather than trigger a protective spasm response. If your unit doesn't have an intermittent mode, just manually ease off the tension every minute or so.
Posture during the session is another overlooked variable. Lying supine with knees elevated on a chair or a couple of pillows reduces lumbar lordosis and lets the traction force work more effectively on the posterior disc structures. Sitting upright while using the belt mostly just stretches the abdominal wall and produces a sensation that feels like relief but isn't doing much mechanical work on the spine itself.
Get the Full Details

Who should and shouldn't use one
Lumbar traction can be genuinely helpful for select disc-related conditions, particularly those involving posterior disc bulges or mild facet joint irritation. It's also reasonable for someone dealing with chronic paraspinal muscle guarding where the tension itself is creating a secondary pain loop. It is absolutely not appropriate for spinal instability, spondylolisthesis beyond grade one, acute fracture, spinal infection, malignancy, or cauda equina syndrome. Those are hard stops. I once watched a patient with an undiagnosed L5 spondylolisthesis use a high-force belt and walk into the emergency room two days later because the instability worsened significantly. That's the kind of thing that happens when people treat traction as a generic back pain solution rather than a targeted intervention. Contraindications also include pregnancy, severe osteoporosis, abdominal aortic aneurysm, and recent spinal surgery unless your surgeon specifically cleared it. These aren't minor caveats. They're reasons the device can actively cause harm if applied indiscriminately.
Common mistakes that waste your money
The biggest mistake I see is treating the belt as a cure. It is a symptom management tool at best. If you have a structural problem that requires surgical intervention, no amount of daily traction sessions will resolve it. You might delay the pain long enough to keep functioning, but you're not fixing the underlying issue. That applies equally to serious herniations, severe stenosis, and progressive neurological deficits. Another frequent error is using the device immediately after injury. Acute inflammatory phases respond poorly to aggressive traction. The tissues are already irritated and swollen. Adding a mechanical pull at that stage often increases local inflammation and worsens the pain. Wait until the acute phase settles, usually three to five days for minor strains, before introducing any traction protocol. Cheap no-name belts with inconsistent tension mechanisms are also a real problem. Some of the budget models on Amazon have traction forces that vary by as much as 30 percent from the displayed reading. You think you're applying 30 pounds when you're actually applying 40. This inconsistency makes it nearly impossible to track progress or find your effective dose. Invest in a unit from a reputable medical equipment manufacturer and verify the force output with a simple scale if you're uncertain about calibration.
I also want to note that traction doesn't work for everyone. Roughly 40 to 60 percent of patients with lumbar disc issues will report meaningful temporary relief. The remaining portion either experience no benefit or get worse. There's no reliable predictor beforehand. You just have to try it carefully and monitor your response over a two-week trial period. If you're not seeing improvement by then, the device probably isn't the right tool for your specific condition and you should explore other options like targeted strengthening, manual therapy, or a consultation with a spine specialist. Proper use of a Lumbar Traction Belt requires patience, correct positioning, and realistic expectations. It's a useful tool in the right situation but far from a universal solution for lower back pain.