What an LVAD Actually Is
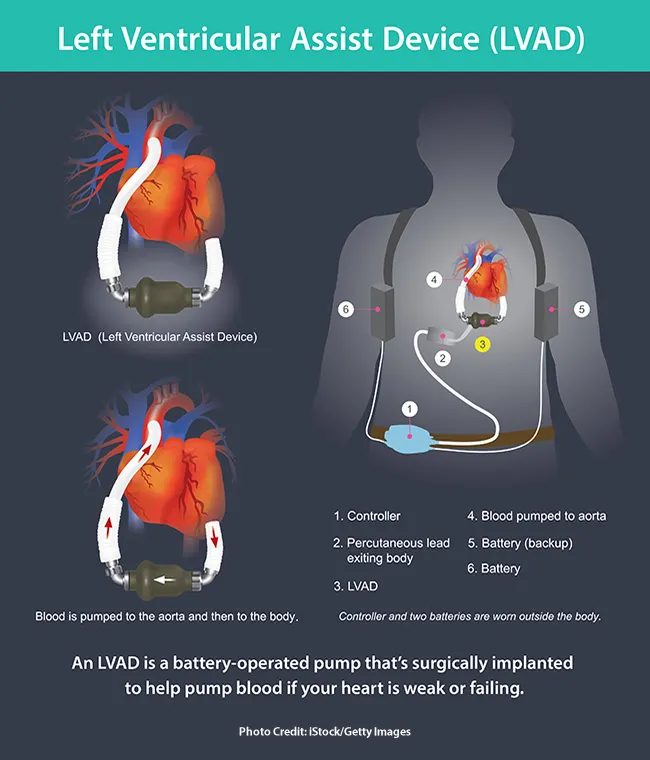
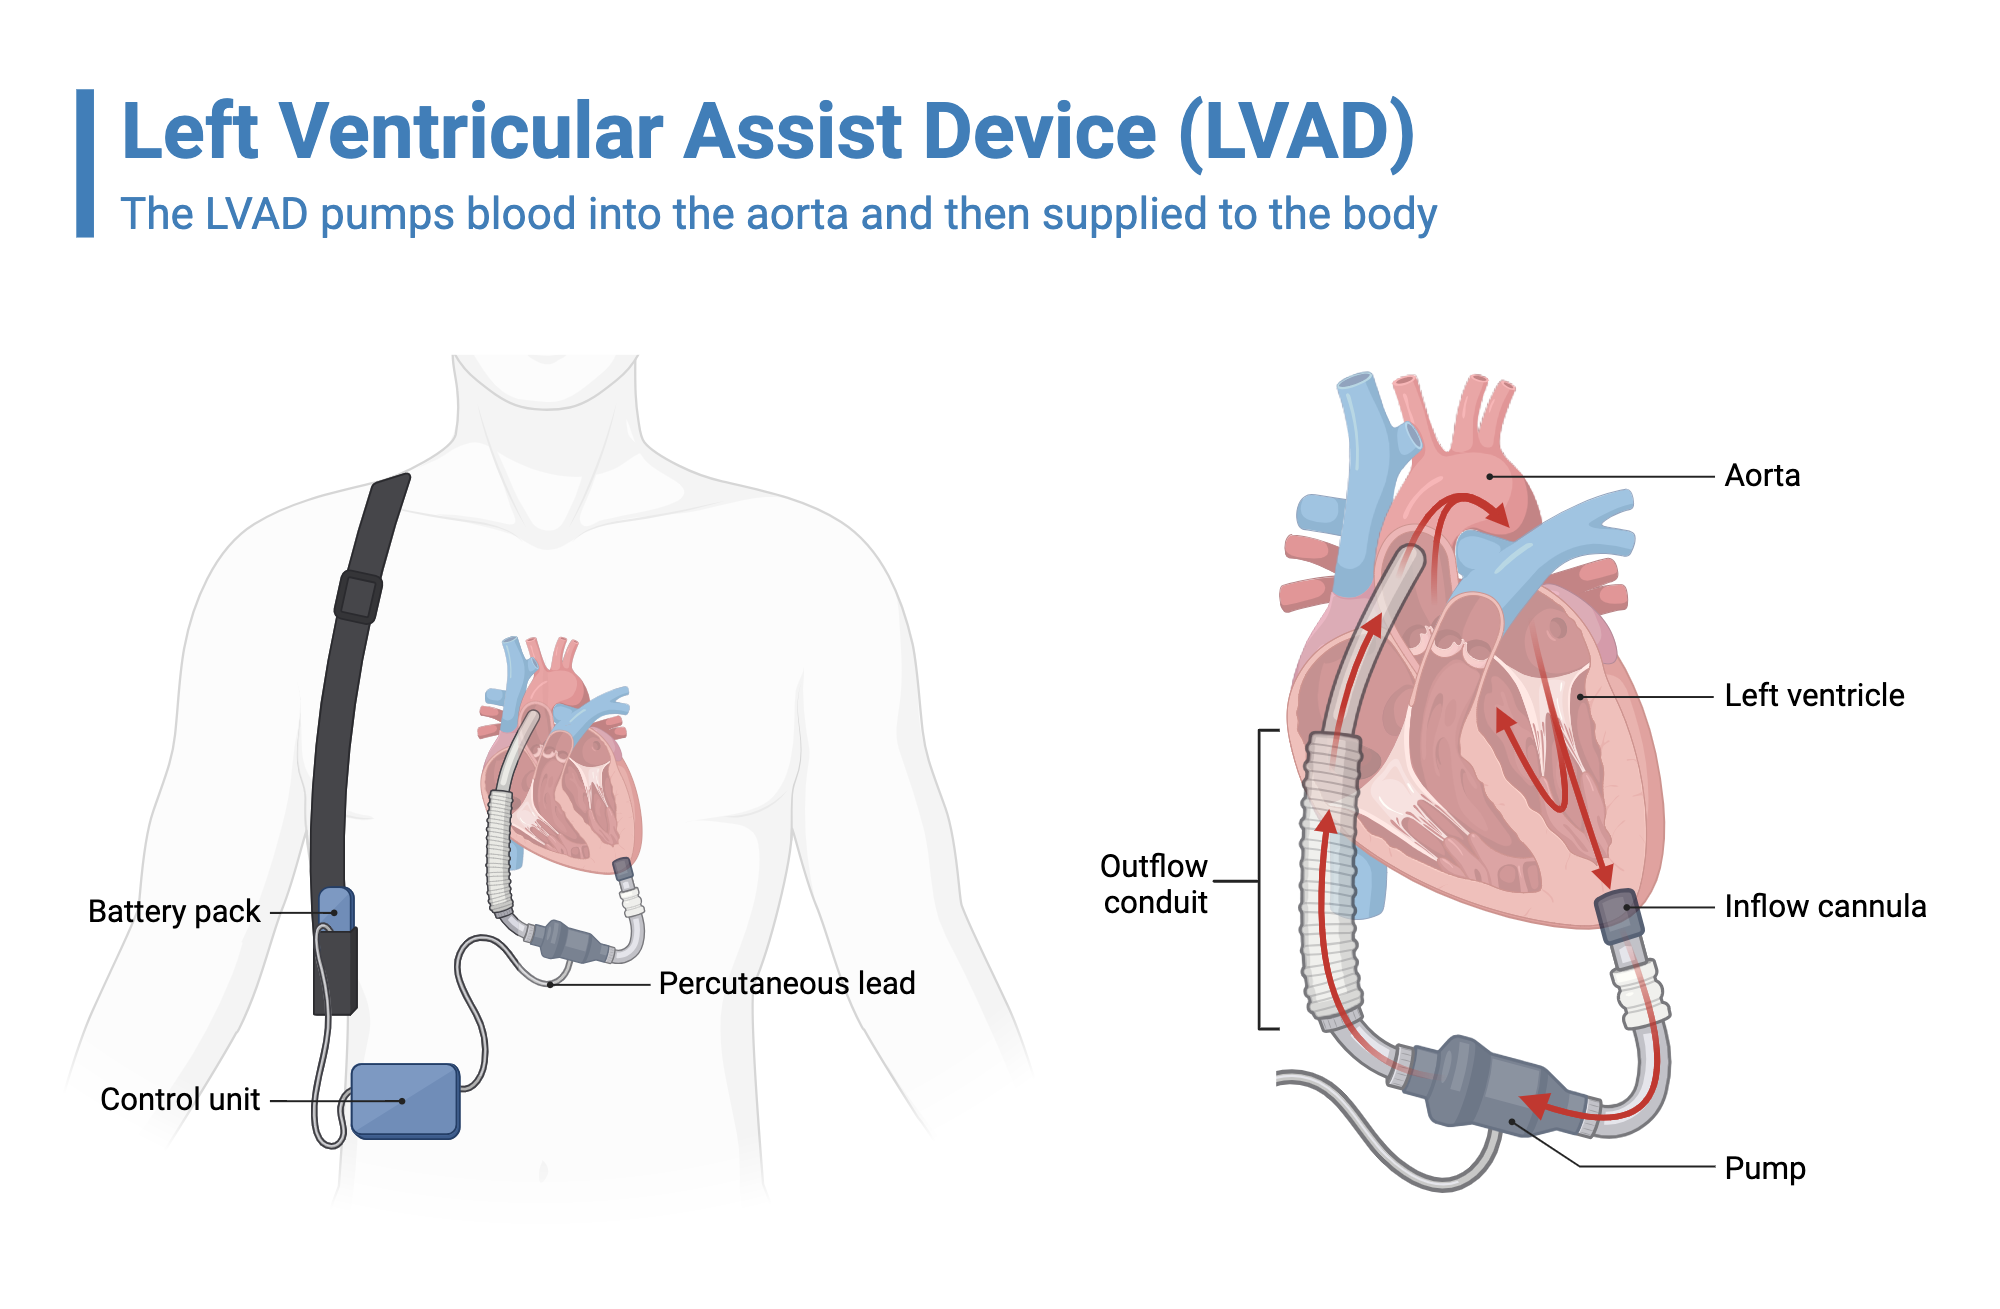
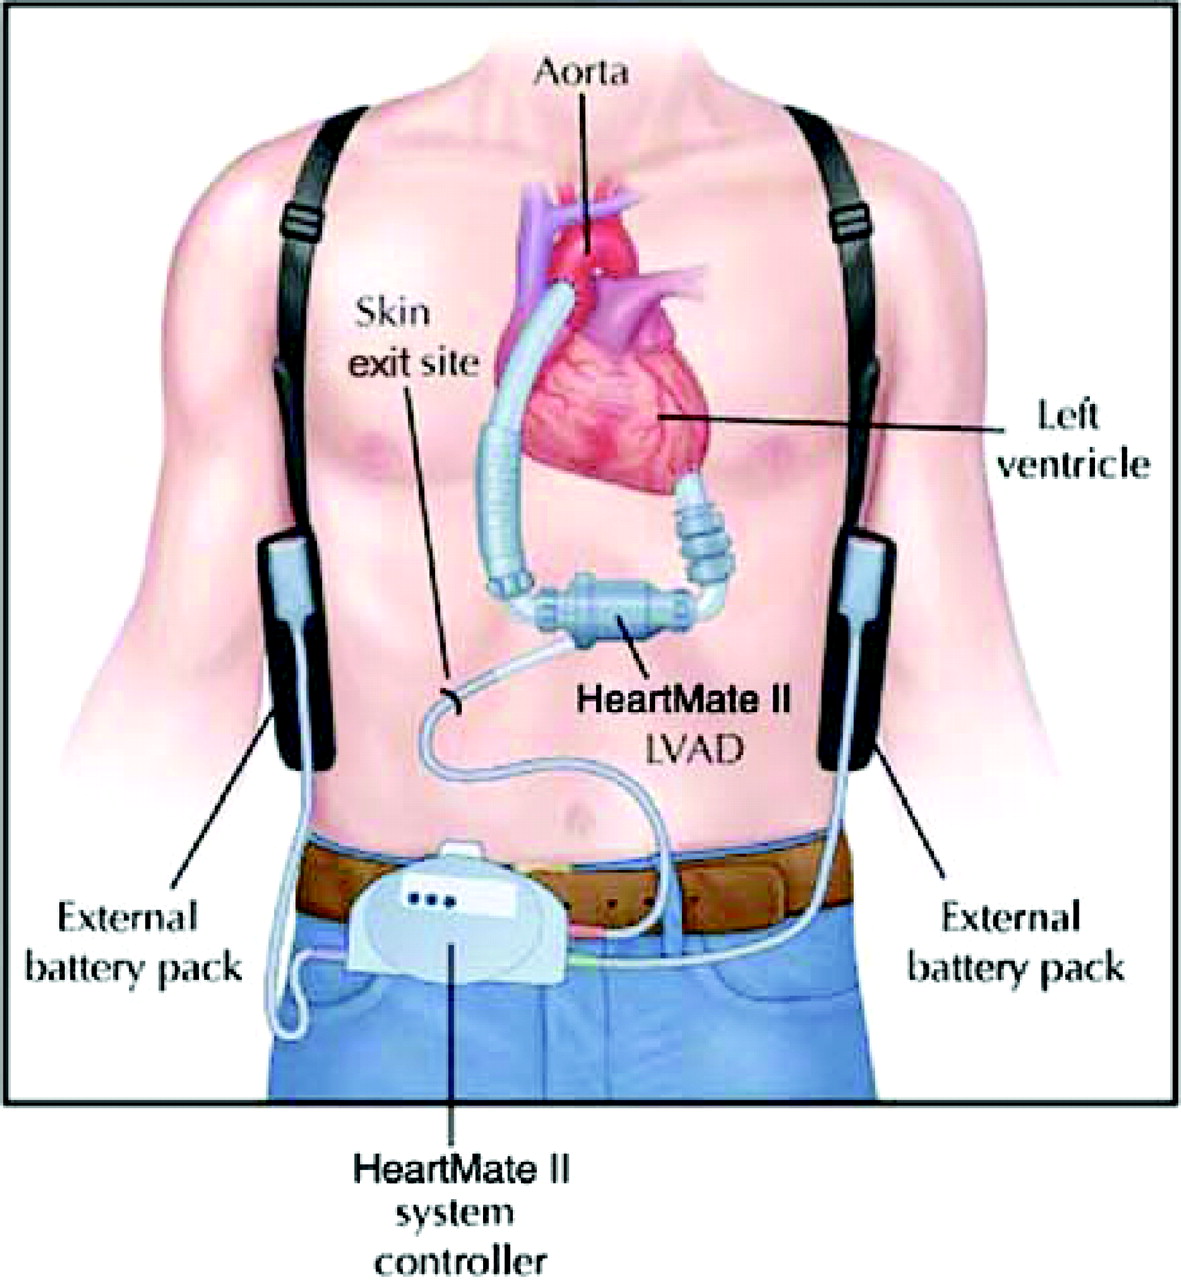
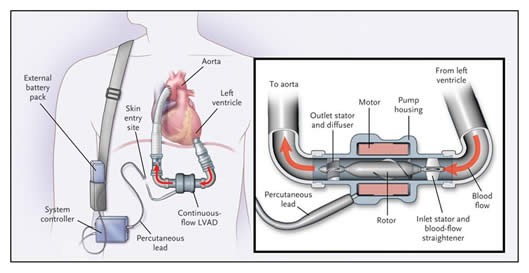
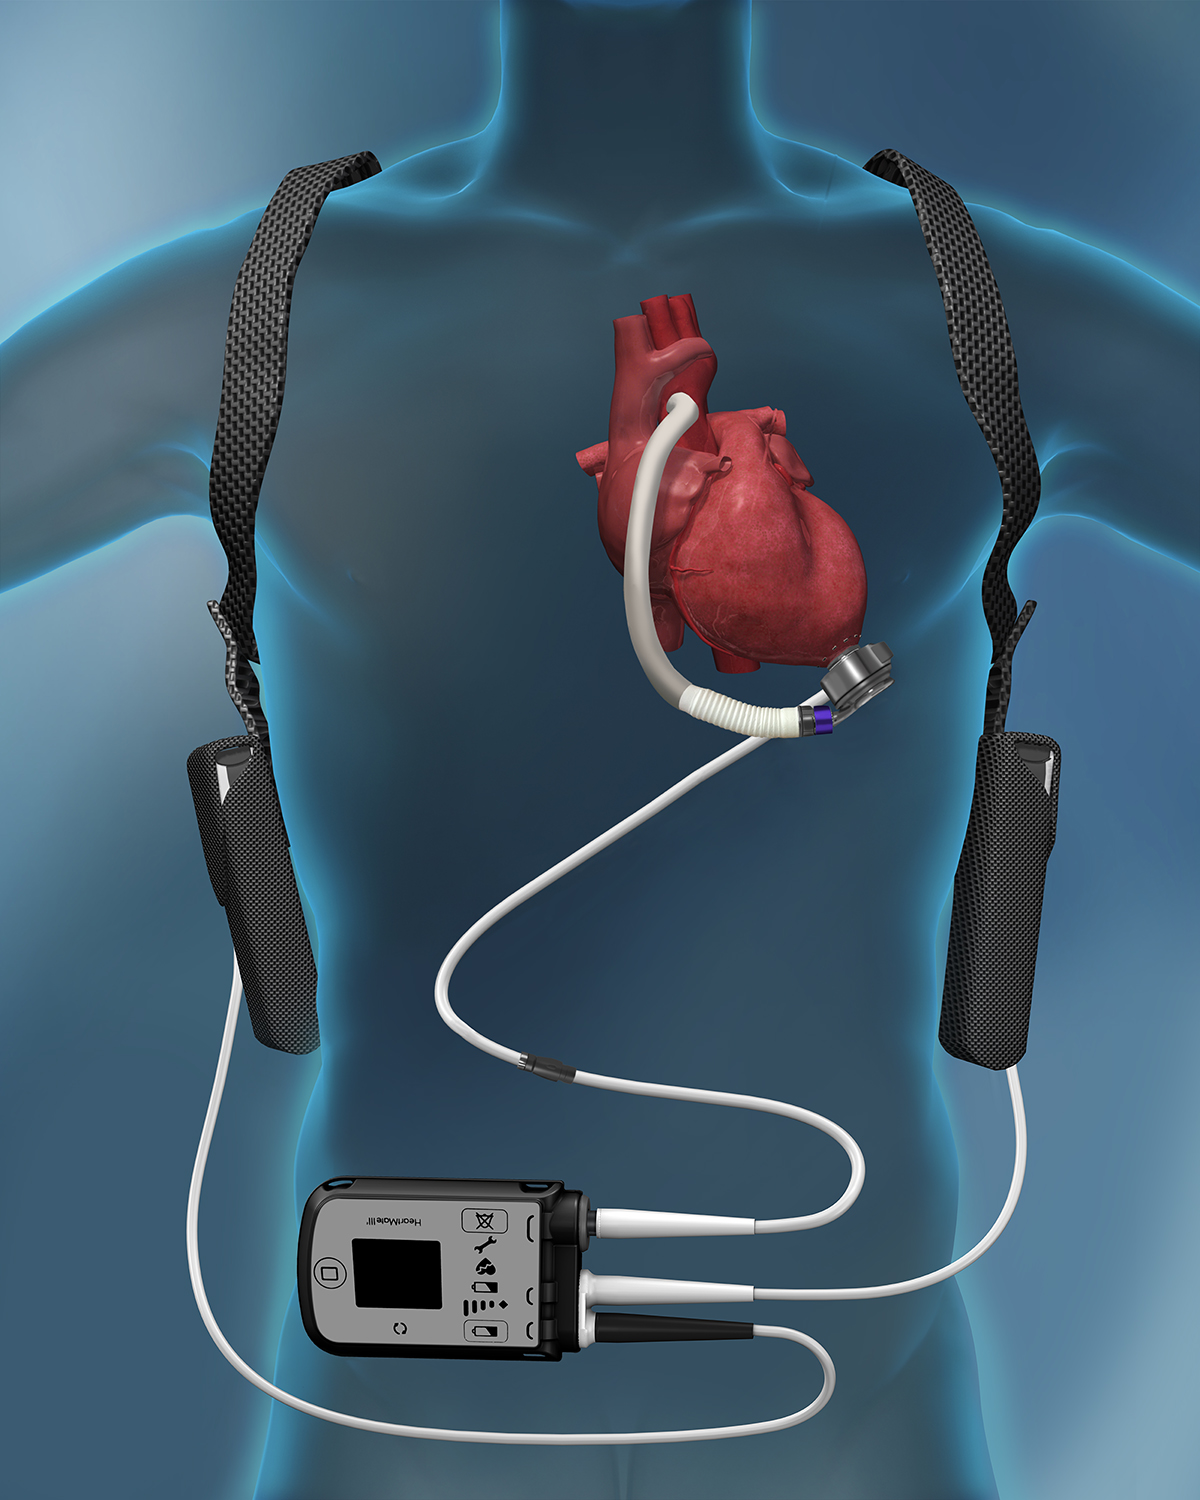
An LVAD is a mechanical pump implanted in patients with advanced heart failure to keep blood moving when the left ventricle can't do the job on its own. It's not a fix. It's a bridge. You either bridge to transplant, bridge to recovery (rare), or just bridge to keeping someone alive longer. Most people get the destination wrong when they first hear about one. The device sits inside the chest. A cannula pulls blood out of the left ventricle and deposits it into the aorta. The pump runs continuously, not in sync with the heartbeat like a real heart does. That continuous flow changes everything about how the body behaves afterward.Lvad Device Types and Clinical Use
There are three generations worth knowing about, though in practice most centers only use the latest two. The HeartMate 3 is the workhorse right now. It uses magnetic levitation for the rotor, which means less thrombosis risk compared to older bearing-based designs. The Micromed DeBakey was popular for a while and is still in some patients' chests, but it's been discontinued and parts support is getting tighter. The HVAD had a nasty track record with stroke and pump thrombosis and was pulled from the market. If you're researching this for a patient or a paper, focus on the HeartMate 3 data. The RESTAGE trial and MOMENTUM 3 gave us the clearest picture of outcomes. One-year survival sits around 85 to 90 percent in contemporary series. Two-year survival drops to roughly 70 to 75 percent. Those numbers are good by old standards and mediocre by anyone's standards if you're comparing to a successful transplant.I spent about six months dealing with a specific problem on a patient who had a HeartMate 3 implanted after a failed transplant workup. The controller kept throwing low power alerts even though the flow numbers looked fine. Turns out the battery cable connector had a hairline fracture at the pin interface. The flow was intact but the electrical contact was marginal under movement. We replaced the driveline and the alerts stopped. If you're seeing intermittent low power alarms with normal flow parameters, check the cable connection before you chase software updates or suspect the pump itself.
How It Actually Works Day to Day
The pump speed is set in RPM and typically runs between 8000 and 12000 depending on the patient's anatomy and cardiac status. The goal is to maintain adequate cardiac output while preventing suction events. Suction happens when the ventricle is too empty and the inflow cannula pulls against the septum or the ventricular wall. Your team will set a baseline speed and then adjust based on echocardiography, hemodynamics, and clinical symptoms. The external setup includes the controller, one or two rechargeable batteries, and a power supply. The patient carries a pouch on their belt or shoulder. They swap between batteries as needed. The controller monitors flow, speed, power, and alarm conditions in real time. Most modern controllers also log event data that your device clinic can pull during follow-up.One thing that trips people up constantly: the flow number on your display is an estimate, not a measurement. It's derived from motor current and speed using a model. It tends to be most accurate at stable, moderate speeds and less reliable during transient changes. Don't treat a flow reading of 4.2 L/min as gospel if the patient just changed position or had a vagal episode. Look at the whole picture.
Key Management Considerations
Anticoagulation is non-negotiable. Warfarin with a target INR of 2.0 to 3.0 is standard, plus low-dose aspirin. Direct oral anticoagulants are generally not recommended because there's insufficient evidence and the device's thrombogenicity is too high to risk it. I've seen complications when patients tried to negotiate DOACs after reading forums. Stick to warfarin unless your center has a specific protocol. Monitoring happens at regular intervals. Echocardiography checks ventricular size, function, and rules out inflow or outflow obstruction. Blood work tracks coagulation parameters and renal function. Device checks pull the event log from the controller. Most patients are seen every one to three months once stabilized.Here's something the brochures don't emphasize enough: right heart failure is the thing that kills you after the left side is sorted. The LVAD unloads the left ventricle beautifully. But if your right ventricle was already marginal, it can't keep up with the increased venous return coming back to it. You'll see elevated central venous pressure, worsening renal function, ascites, and low forward flow despite adequate pump speeds. In those cases, inotropes, pulmonary vasodilators, and sometimes temporary right ventricular support are the reality. Preoperative right heart catheterization isn't optional. Skip it and you're gambling.
Get the Full Details
Known Limitations and Failures
Stroke remains a significant risk. Major stroke rates in the HM3 trials were around 10 to 15 percent over the study period. Some of that is hemorrhagic from over-anticoagulation, some is ischemic from thromboembolism. Gastrointestinal bleeding from arteriovenous malformations is another real problem, especially in patients on dual antithrombotic therapy. It's not rare. It's just well documented because everyone writes about it. Driveline infections happen. The percutaneous exit site is a permanent open pathway from skin to internal hardware. Proper wound care and dressing changes are mandatory. I managed a patient whose driveline site developed a chronic granuloma that never fully resolved despite repeated local treatments. Eventually we revised the exit site trajectory and switched to a subcutaneous tunnel modification. The infection cleared after that. Leaving it alone and hoping was never a valid option.Pump thrombosis is the worst-case scenario. Symptoms include rising power at a given flow rate, hemolysis markers spiking, and clinical deterioration. In severe cases the pump stops and the patient goes into cardiogenic shock within minutes. The HeartMate 3 has reduced thrombosis rates compared to previous generations, but it hasn't eliminated the risk. Patients who develop thrombosis often need surgical exchange or emergency transplantation if they're still eligible.
Where Lvad Therapy Falls Short
LVADs don't restore quality of life to normal for most patients. Fatigue, exercise limitation, dietary restrictions, and the constant awareness of equipment around your body are real. Many patients report depression and anxiety at clinically significant levels. The device saves lives, but it doesn't give back the life someone had before heart failure became fatal. Frail patients with significant multi-organ dysfunction are poor candidates. Pulmonary hypertension that's fixed rather than reactive, severe renal insufficiency, active malignancy, and irreversible liver disease are typical exclusion criteria. Some centers use the ELSO score or INTERMACS profile to help decide. These tools aren't perfect but they're better than a gut feeling.If your center isn't doing high-volume LVAD implantations, find one that is. Outcomes are directly correlated with institutional experience. A low-volume center might have 15 to 20 percent higher mortality rates in the first year. This isn't theoretical. The ISHLT registry data backs it up across multiple device types.
Most patients learn to live with the system within a few weeks. Battery management becomes routine. Controller alarms stop causing panic. Driving, bathing, and light exercise are all possible with proper training. Sexual activity, travel, and returning to work depend on individual recovery and support systems. The device doesn't prevent any of that but it adds constraints that require planning.