Practical Guide To Axillary Lymph Nodes
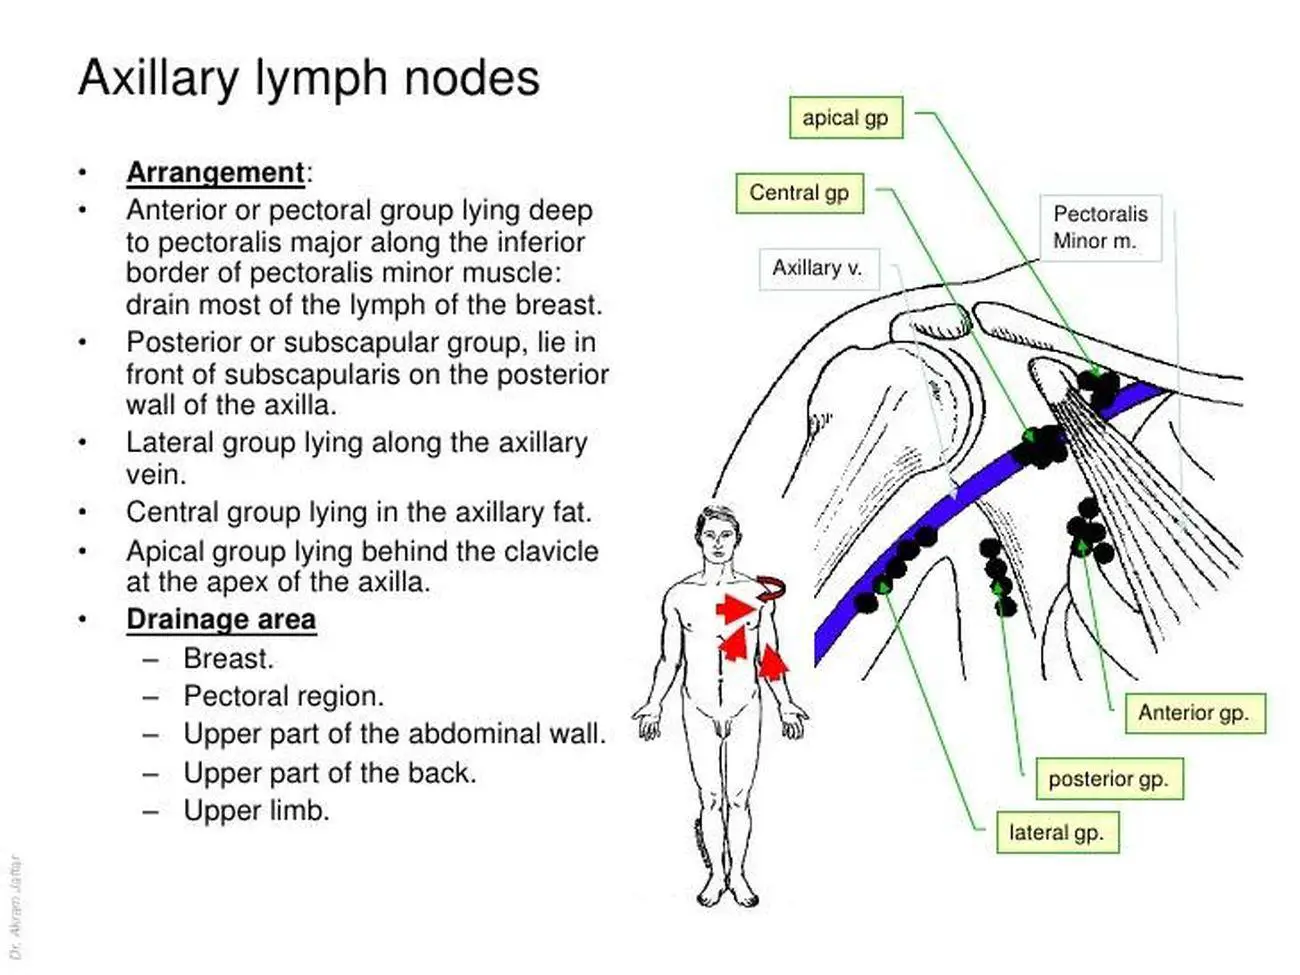
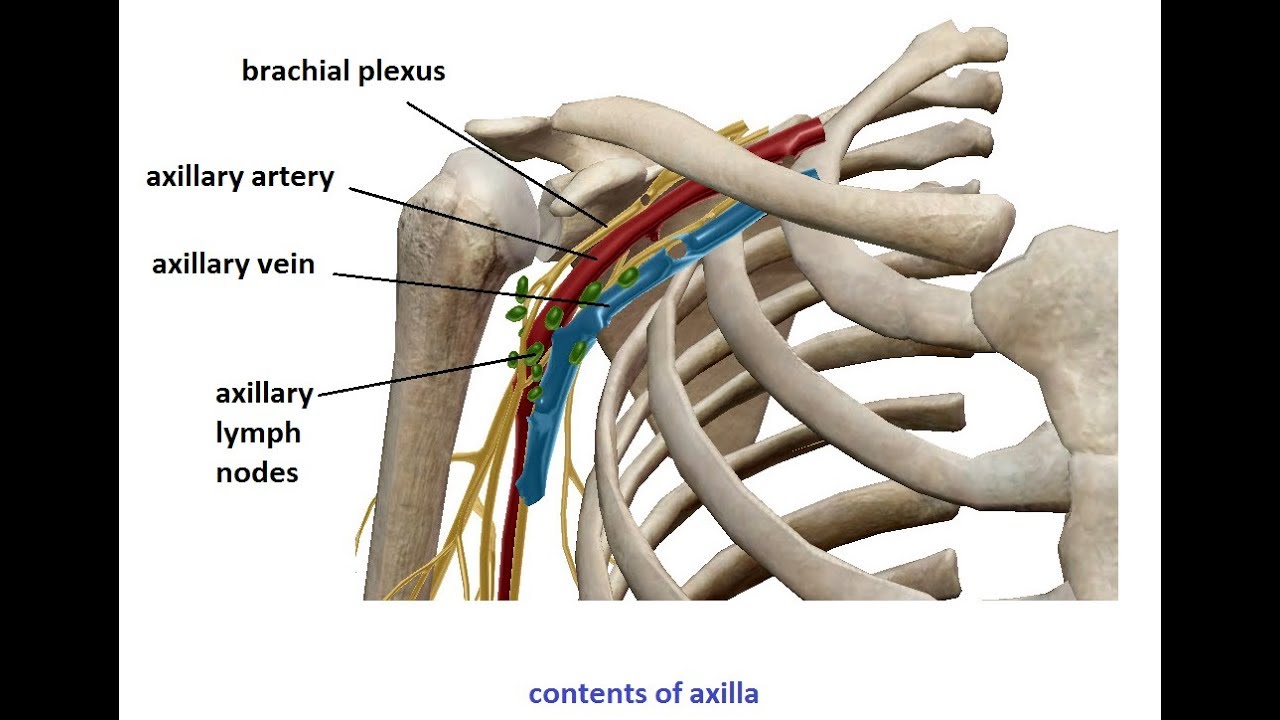
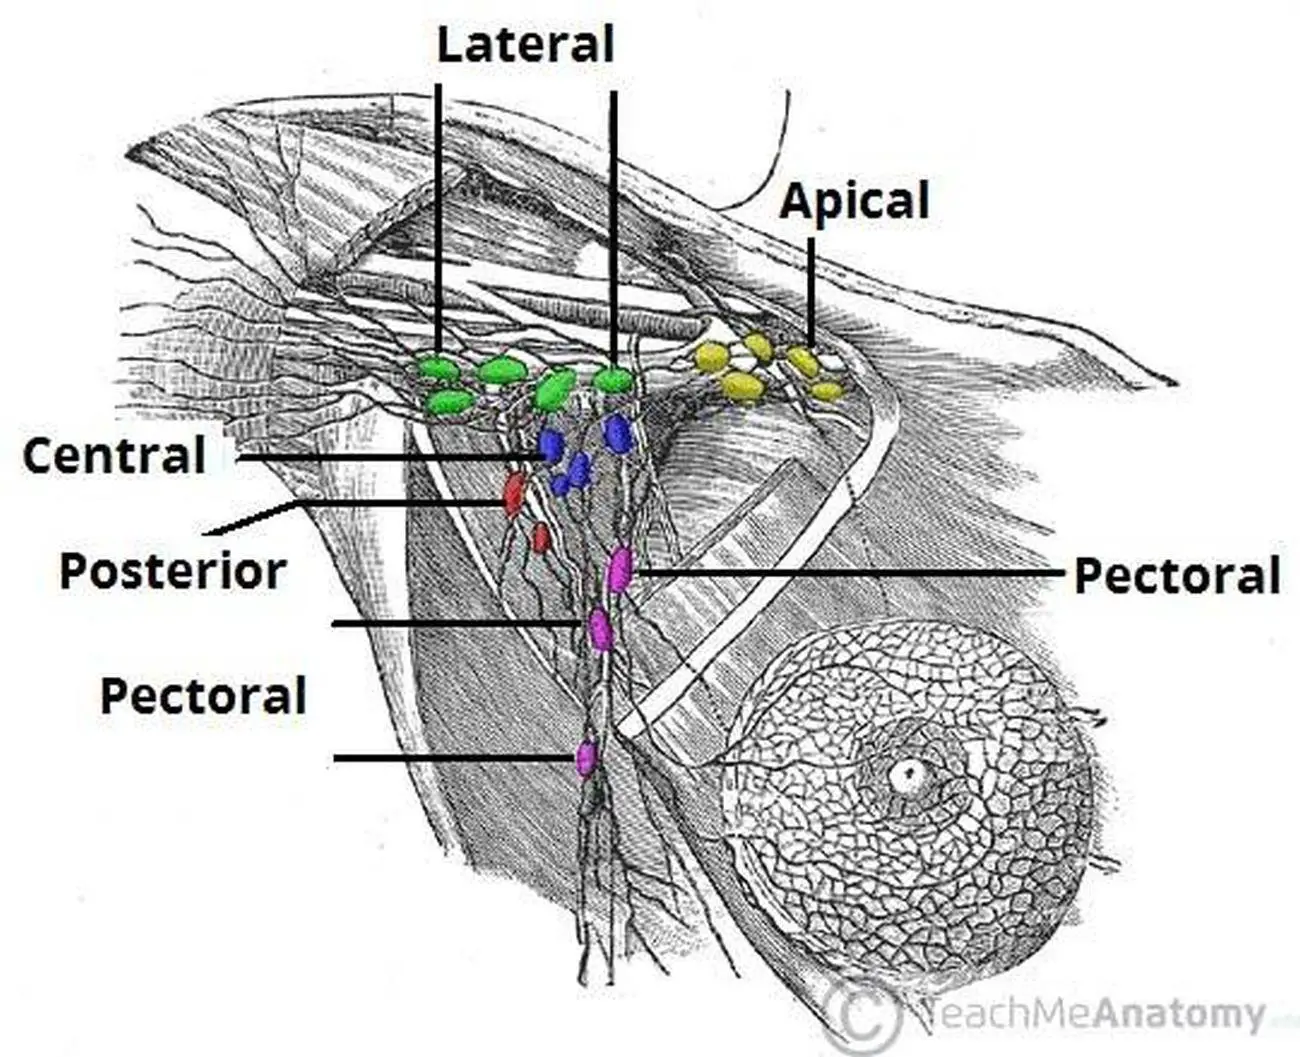
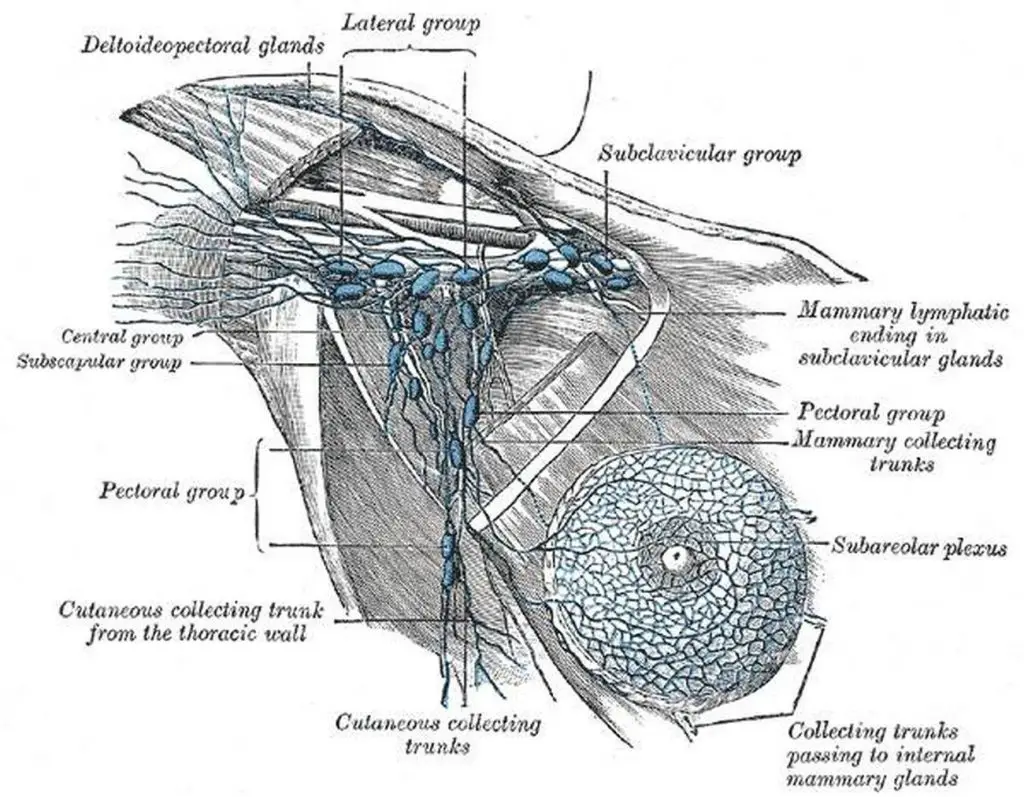
Axillary lymph nodes are grouped into five levels, and most textbooks list them but skip the part about why you'd actually care during a real exam. Level I sits lateral to the pectoralis minor muscle, Level II is deep to it, and Level III is medial. Rotatores nodes, apical nodes, and the central group round out the clinical picture. For breast cancer staging, this architecture matters more than any summary table. I spend more time on axillary dissection than I do on almost anything else clinically. When you palpate the axilla, you are not just checking for lumpiness. You are mapping an entire drainage basin, and missing a node here changes everything downstream. Start lateral to the pectoralis minor, then work medially. Document size, consistency, and whether the node is mobile or fixed. Fixed nodes are already beyond staging discussions. The trap most people fall into is assuming that any palpable node in the axilla is automatically pathological. It is not. Reactive nodes from upper limb infections, shaving nicks, or recent vaccinations are common and often dismissed as noise. The distinguishing factor is duration. A reactive node typically shrinks within two to three weeks. A suspicious one either persists or grows. I once missed a metastatic Level II node in a patient whose primary breast tumor was small but deeply invasive. The ultrasound was read as benign-appearing, and I nearly passed on a biopsy. After repeated palpation with the arm slightly abducted, I identified a firm, non-tender 1.4 cm node that ultrasound had flattened against the pectoralis minor. I biopsied it. It was positive. That saved us from understaging by at least one level.
Palpation Technique That Actually Works
Stand behind the patient with their arm relaxed at their side or slightly abducted. Use the palmar surface of your fingers, not the tips. Glide medially from the lateral chest wall toward the pectoralis minor border, then sweep upward toward the apex of the axilla. The key is slow pressure, not firm pressure. You are feeling for discrete masses beneath the subcutaneous tissue, not pressing through fat. If the axilla is hairy or the patient has prominent subcutaneous fat, ultrasound changes the game entirely. Fine-needle aspiration under ultrasound guidance picks up nodes that physical exam completely misses, especially in Level II where the nodes sit between muscle and vessel structures. Level III nodes are the ones most commonly overlooked because they sit deep near the axillary vein. They are harder to reach without imaging. If you suspect medial spread from an axillary node, do not rely solely on palpation. Request cross-sectional imaging and correlate with surgical findings. Surgical lymph node dissection remains the gold standard for staging when clinical assessment is ambiguous, though sentinel lymph node biopsy has largely replaced full dissection for early-stage disease.
Common Pitfalls In Clinical Assessment
One issue I see repeatedly is clinicians labeling every small, mobile, soft node as normal. Small does not equal benign. In a patient with known breast carcinoma, even a 6 mm node warrants attention if it feels abnormal on. Another problem is relying on a single imaging modality. Ultrasound can miss Level III involvement. MRI helps but is expensive and not universally available. CT provides gross anatomical information but lacks the resolution to distinguish reactive hyperplasia from metastasis reliably. The combination of ultrasound and FNA biopsy gives you the best balance of accuracy and cost for most cases. There is also the issue of axillary web syndrome, which appears after dissection or radiation. Patients develop cords along the lymphatic channels, and they sometimes confuse these with recurrent nodal disease. The difference is palpable tension along the cord versus discrete nodularity. I have seen patients come back panicked after noticing a cord, only to learn it was post-surgical fibrosis rather than recurrence. Documentation matters here, so photograph or sketch findings at baseline and compare later visits.
Get the Full Details
When To Refer For Further Workup
Refer any node that is firm, fixed, larger than 1 cm, or persisting beyond three weeks. For confirmed malignancy, surgical oncology coordinates the next steps, which may include sentinel node biopsy, axillary dissection, or radiation depending on the primary tumor characteristics. The NCCN guidelines update annually, so check the current version before making staging decisions. There is no single perfect algorithm, and clinical judgment still matters more than any checklist. If you need detailed anatomical diagrams or surgical atlases, I recommend the Netter collection or the Gray's Anatomy atlas. Online resources like Radiopaedia provide good ultrasound correlations. Downloadable guides are scattered across medical education sites, but the most reliable reference remains an attending who has actually performed dissections. Practice palpation on healthy volunteers first, then progress to symptomatic patients. The tactile skills you develop there are the ones you rely on when imaging is inconclusive.