Manual Lymphatic Drainage: What Actually Works
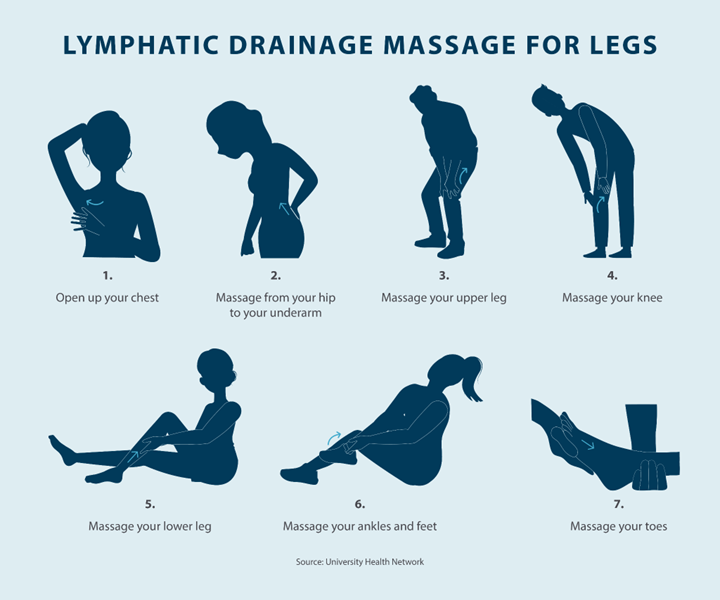
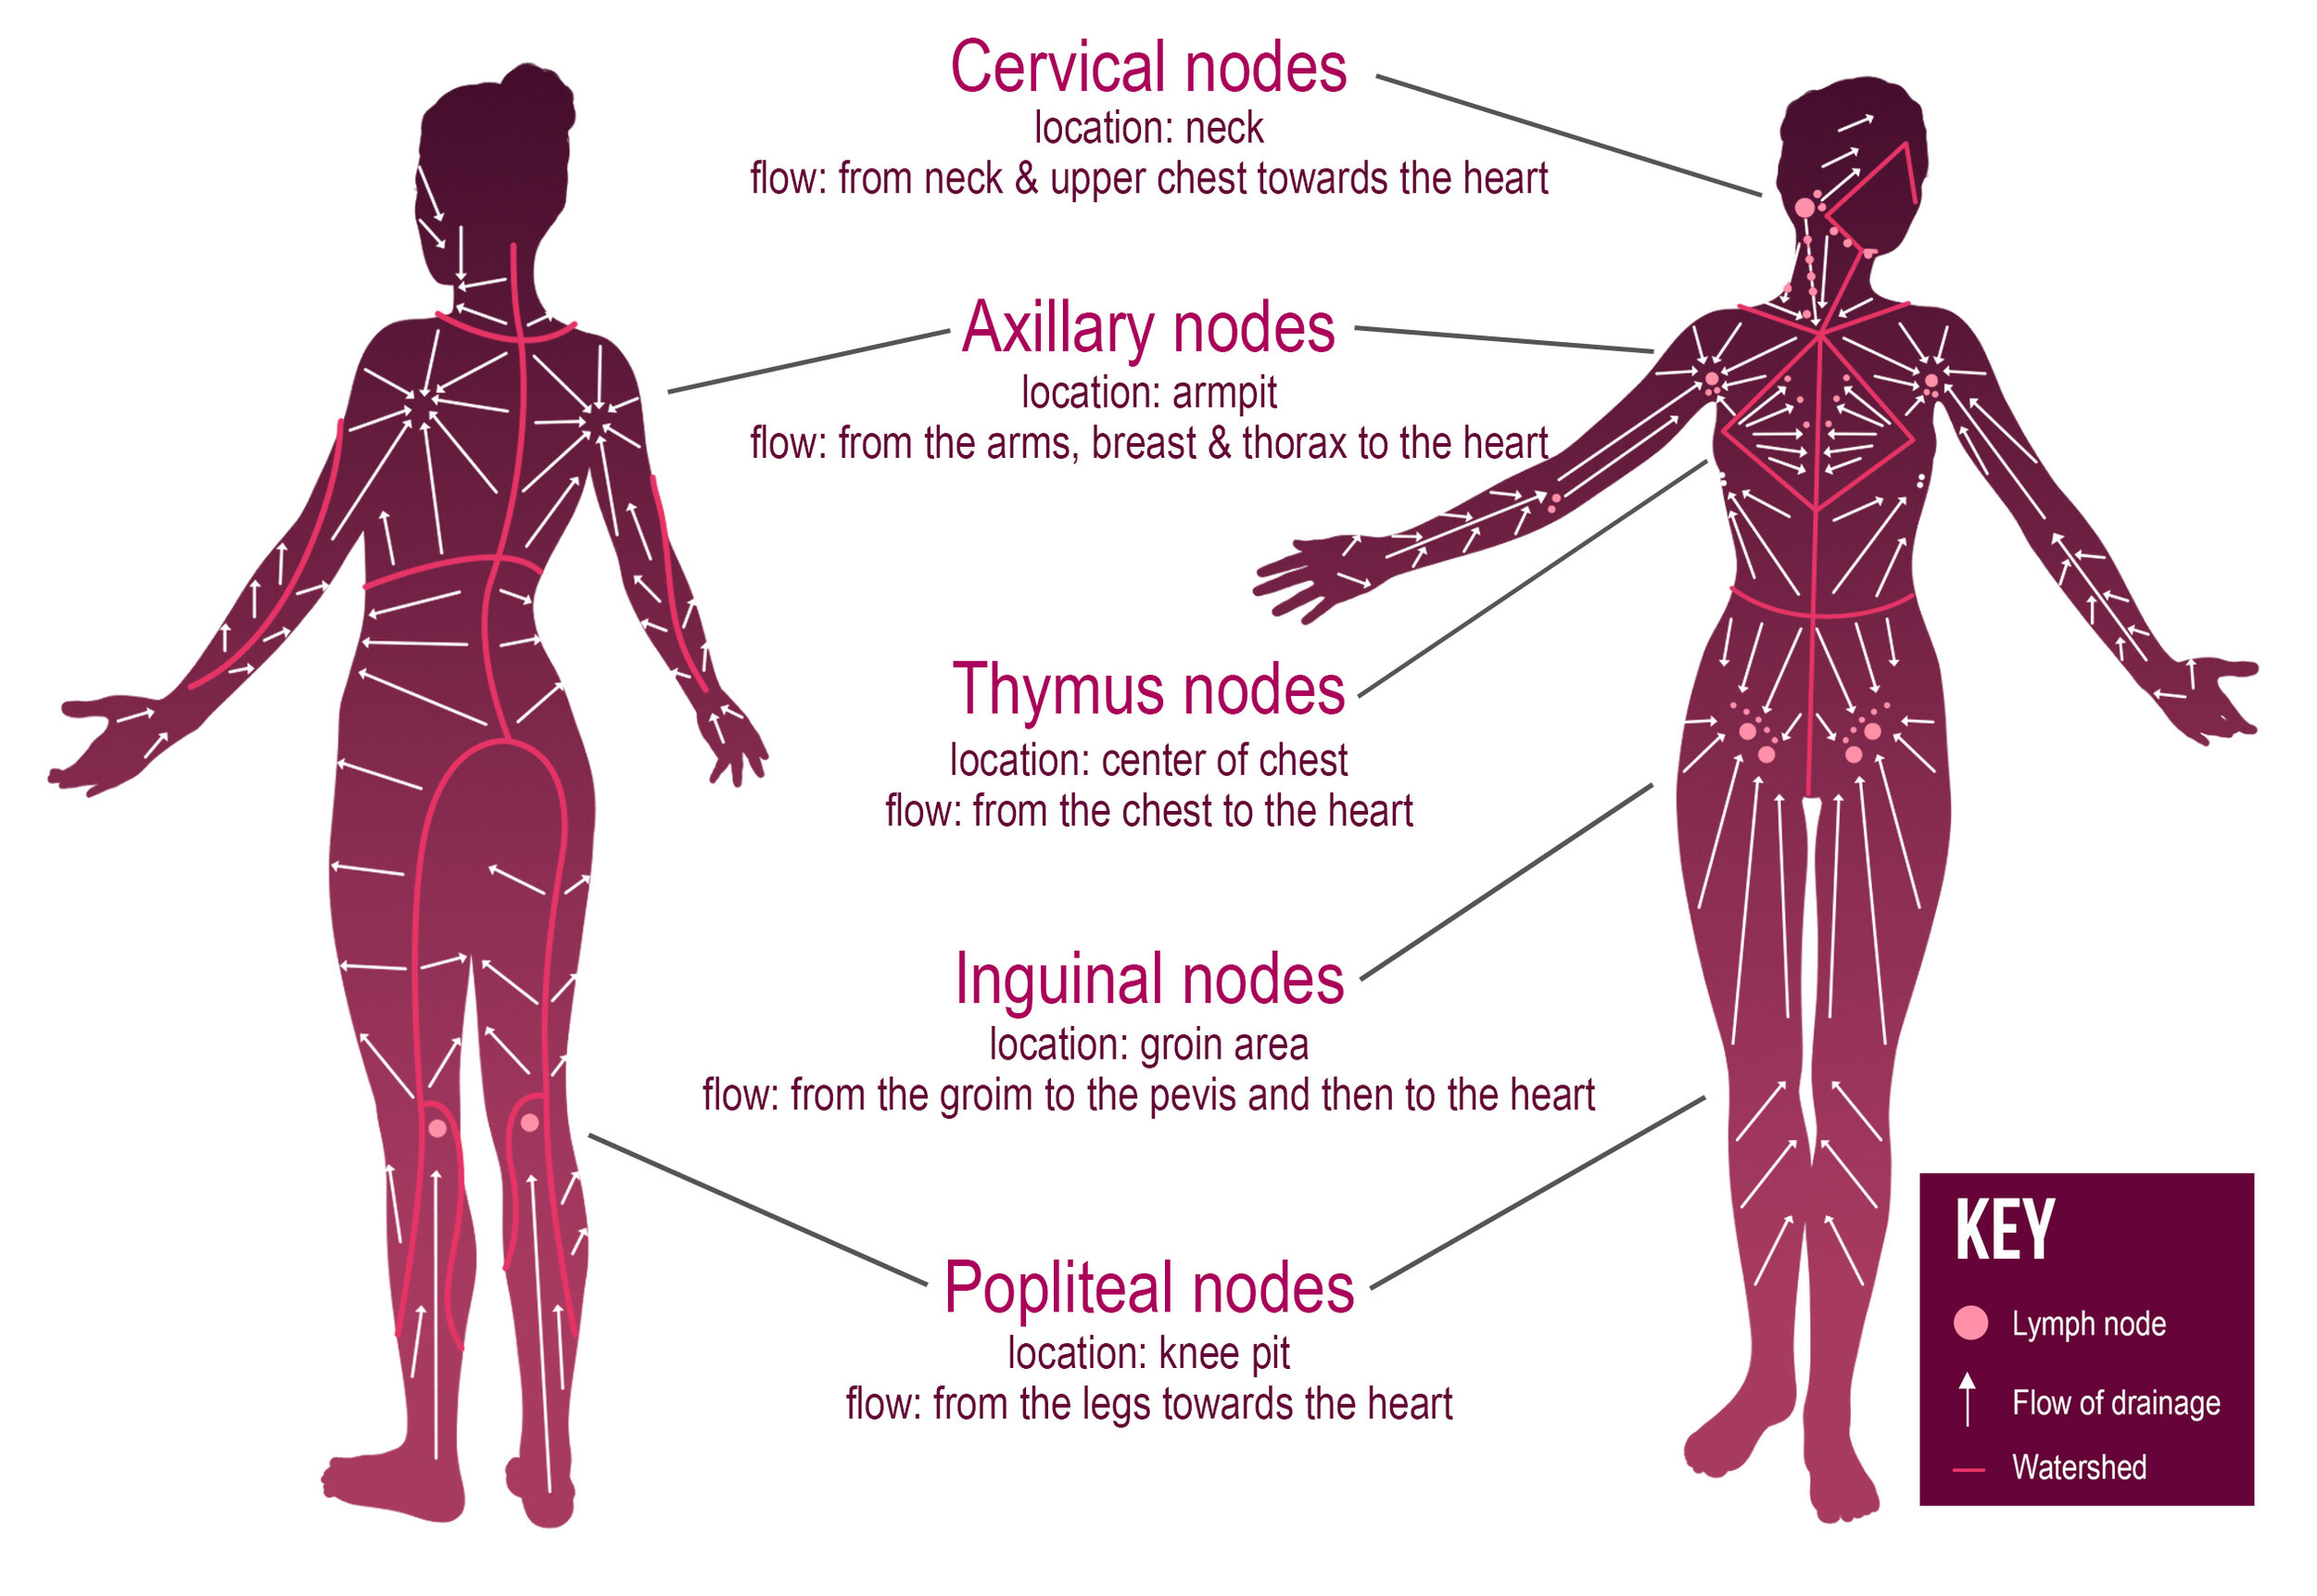
Most people who try lymphatic drainage on themselves or their clients end up pushing too hard. The technique looks simple enough, but it fails because the underlying anatomy doesn't behave the way beginners assume. Lymphatic vessels are extremely superficial, sitting just beneath the skin surface. When you press down with any meaningful force, you collapse them. The fluid doesn't move. It actually backs up. The correct approach uses near-imperceptible pressure, somewhere around 30 to 40 millimeters of mercury, which is roughly the weight of your hand resting on the skin without actually adding weight. This is where most practitioners make mistakes. The lymphatic system drains toward central nodes, so you have to clear those upstream pathways before touching anything downstream. Start with the client supine. Do three to five minutes of gentle sternal and clavicular work to open the thoracic duct and right lymphatic duct. These are your primary drainage routes, and if they are congested, pushing fluid into the arms or legs accomplishes nothing except shifting fluid from one swollen area into another, which is a known clinical pitfall. From there, work proximally to distally. Axillary nodes first, then the arm. Inguinal nodes first, then the leg. Each node group gets about two minutes of slow, rhythmic, circular motion at the same near-zero pressure. Your fingers should move the skin slightly over the underlying tissue, not compress into it. The stroke rate should be about 7 to 10 cycles per minute. This is deliberately slow, and it feels almost absurdly gentle to both practitioner and recipient. The client often asks if you are doing anything at all.
Practical Application of Lymphatic Drainage Massage Techniques
Volume reduction techniques like Vodder and Foldi form the basis of what most practitioners call manual lymphatic drainage. The core movement patterns are stationary circles, pump strokes, and scoop motions applied over each anatomical region. Stationary circles are the most important. You place your fingers on a point, apply that feather-light pressure, and rotate the skin beneath your fingers in small circles without sliding across the surface. This activates the superficial lymphatic plexus directly. A typical full-body session using these Lymphatic Drainage Massage Techniques takes about 45 to 60 minutes because you cannot rush the proximal clearance phase and compress the distal work. The skin displacement should be visible but minimal. If the client's skin is bunching or folding under your hands, you are pressing too hard. If you cannot feel any skin movement at all, you are not engaged enough. The sweet spot is rare and requires actual tactile calibration. I spent months developing the sensitivity by practicing on my own forearms and measuring displacement with a calibrated pressure gauge. The threshold is narrower than most training programs acknowledge.
A Problem That Caught Me Off Guard
About three years ago, I worked with a post-mastectomy client presenting with Stage 1 lymphedema in the left arm. Standard protocol called for immediate distal drainage of the affected limb after proximal clearance. But the client had significant scar tissue and adhesion along the axillary region from her surgery. When I attempted direct strokes through the scarred area, she reported sharp pain and the edema actually worsened slightly in the hand afterward. The scar tissue was acting as a functional blockage, and forcing fluid past it created localized inflammation. The workaround was indirect drainage. Instead of working through the scarred axilla, I performed extensive manual lymphatic drainage on the contralateral (right) axilla and the entire trunk to maximize cross-circulation. I also used gentle circumferential breathing techniques to activate the thoracic duct passively. Over four sessions, the arm volume decreased by approximately 18 percent without ever directly massaging the problematic scar zone. The lesson was straightforward: the textbook sequence does not override individual pathology.
Get the Full Details
Counter-Intuitive Details Beginners Miss
Positioning matters more than most guides admit. A client seated upright drains differently than one supine because gravity alters venous and lymphatic return patterns. For upper extremity edema, I prefer the client supine with the arm supported at a slight elevation, not raised above heart level, which creates a vacuum effect that can actually pool fluid at the shoulder. The arm should rest at approximately 15 degrees of elevation on a firm pillow. Another overlooked detail is breath timing. The thoracic duct opens and closes with respiration. Coordinating your strokes with the client's exhale increases intrathoracic pressure changes that assist lymph propulsion. It adds maybe 10 to 15 percent more efficiency per session if done consistently, but very few practitioners time their movements to the cycle.
What This Technique Cannot Do
Manual lymphatic drainage is not a treatment for cellulite. It will not break down fat deposits or restructure connective tissue. It is a fluid mobilization method, nothing more and nothing less. The evidence base supports its use for lymphedema management, post-surgical swelling reduction, and certain types of edema related to venous insufficiency, but the effects are temporary. A single session may reduce limb volume by 10 to 30 milliliters in measurable cases. Sustained reduction requires a treatment course, typically five to ten sessions over two to three weeks, followed by compression garment use and self-drainage maintenance. There are hard contraindications. Active deep vein thrombosis, untreated cardiac failure, active infection in the treatment area, and active malignancy without oncology clearance are all reasons not to proceed. I once treated a client who had a history of recurrent DVT without proper vascular evaluation. After the second session, she developed calf pain and swelling that turned out to be a new thrombus. The massage did not cause it, but proceeding without vascular screening was reckless. Every client with a history of thromboembolic events needs medical clearance first. The technique also has a practical bottleneck: it is labor-intensive and time-consuming. If your goal is quick circulation stimulation or general relaxation, compressive massage or myofascial work will give you more perceived benefit per minute invested. Manual lymphatic drainage is worth the time only when the clinical indication is genuinely lymphatic fluid accumulation. Applying it as a general wellness treatment wastes both your schedule and the client's money.
Equipment and Resources
You do not need special equipment for basic manual lymphatic drainage. Hands, a flat treatment surface, and appropriate draping are sufficient. Some practitioners use lymphatic pumps or compression devices as adjuncts, but the manual component remains the primary modality. If you want to study the original techniques, the Vodder method is documented in specialized literature from the International Society of Lymphology, and the Foldi approach is available through the Foldi Clinic training materials. There is no single downloadable resource that replaces hands-on training, and any course claiming to certify you in lymphatic drainage after a weekend webinar should be treated with skepticism. The skill develops gradually over 200 to 300 hours of supervised practice before you reach consistency. Most introductory courses cover the theory and basic strokes in 16 hours. That is enough to understand the concept, not enough to execute it reliably on complex presentations. Budget your training time accordingly.