Manual lymphatic work doesn't require fancy equipment, but it does require understanding what you're actually doing
Most people who come into this have no idea how the lymphatic system works. They think lymph is just waste fluid, which is partially true but misses the whole picture. The lymphatic system is a one-way drainage network that runs parallel to your bloodstream, moving interstitial fluid, immune cells, and debris back toward venous circulation. Unlike blood, it has no central pump. Gravity and muscle movement do the work. That matters when you're trying to move fluid manually. I've spent years working with post-surgical patients and people dealing with chronic edema, and the first thing I tell them is that timing matters more than pressure. A lot of beginners crush into tissue immediately and wonder why the client's skin gets irritated or why the fluid doesn't budge. The lymphatic channels are just under the skin surface, roughly one to three millimeters deep. You're not pressing into muscle. You're applying light stretch to the skin. The target pressure is about 30 grams, roughly the weight of a nickel resting on the skin. If you can blanch the skin, you're pushing too hard. Lymph vessels actually collapse under excessive pressure, which blocks rather than promotes flow.
Getting Started with Lymphatic Drainage Techniques
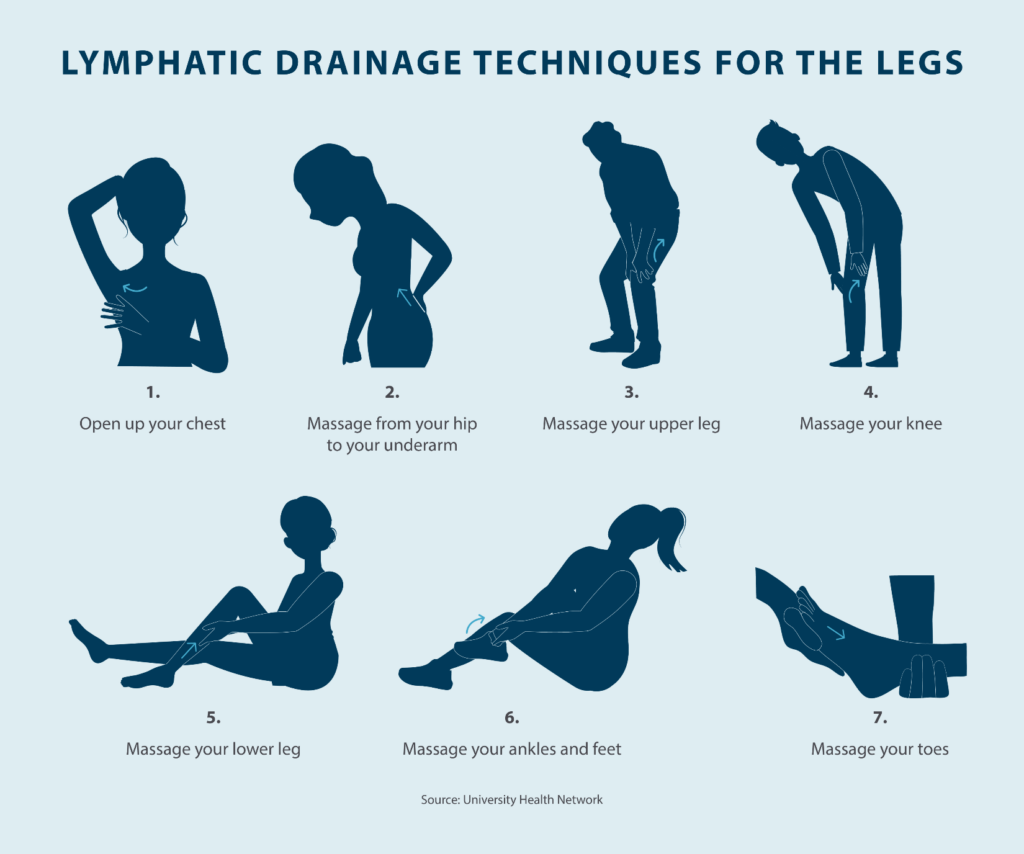
The core method is stationary pumping, also called lymphatic pump or circular pumping. You position your fingers or palm on a region, apply that light touch, hold for three to five seconds while the client breathes in, then release slowly on the exhalation. Each pump draws lymph into the initially blind-ended capillaries. From there, it moves through collecting vessels with one-way valves toward lymph nodes. The rhythm is slow. About 15 to 20 pumps per session area is typical, and each sequence takes roughly 30 to 60 seconds depending on how you count the breath cycles. The direction always follows the anatomical pathway toward the nearest lymph node basin. For the arm, that means toward the axillary nodes. For the leg, toward the inguinal nodes. For the face and scalp, toward the cervical nodes. This isn't optional. Moving fluid away from a node cluster without clearing that node first is like trying to fill a sink with the drain plugged. It backs up. Here's the sequence I use most often. Start at the proximal nodes and clear them first, even if the issue is distal. If someone comes in with a swollen ankle, you don't start at the ankle. You do ten slow pumps over the inguinal region first, then the popliteal, then the lower leg. The proximal clearance creates a pressure gradient that the distal work can actually move into. This is where most tutorials get it wrong and why some people think manual lymphatic drainage doesn't work. They skip the upstream clearing.
I ran into a specific case with a post-mastectomy patient who had significant arm lymphedema. The standard protocol said to drain toward the axilla, but her axillary nodes had been compromised during surgery. The fluid had nowhere productive to go. Pushing more volume in just increased discomfort and sometimes caused a localized inflammatory flare. The workaround was to redirect the drainage path. Instead of aiming solely at the axilla, I used a technique called cross-body or crossover drainage, directing fluid toward the contralateral axilla and then along the lateral thoracic wall toward the deep cervical chain. It's slower and requires more careful assessment upfront, but it actually moves volume instead of just compressing it into a blocked zone. I documented the technique in a brief manual that circulates among lymphedema therapists, and you can find a downloadable version of that protocol document through the Association of Lymphatic Therapists clinical resources section. There are a few more modalities worth knowing about. Pneumatic compression devices exist, and they work for some people, but they have real limitations. The sequential inflation can't match the specificity of manual work, and in cases of active infection, DVT, or decompensated heart failure, they're outright contraindicated. Manual techniques give you tactile feedback that a machine won't. You can feel a firm node, a region of fibrosis, or a area where the tissue simply won't accept more volume. Machines press regardless. Another approach is Bimanual Pumping, where one hand supports the distal tissue while the other performs the pumping motion proximally. This is useful for areas like the lower leg where the tissue can pool between both hands. It's also the go-to for pediatric cases where a single adult hand covers too large an area relative to the child's anatomy.
Get the Full Details

Then there's the Heald-Mansueto concept, which emphasizes very slow stretching of the skin rather than pressing. Some practitioners confuse this with standard massage and end up using gliding strokes that drag tissue instead of lifting it. The difference is critical. A glide stretches skin in the direction of movement. A lymphatic pump lifts and holds in place, then releases. The lifting action creates a slight negative pressure that draws fluid in. Dragging just pushes fluid around unpredictably, sometimes into areas that don't have open pathways.
What actually limits this work in practice
Lymphatic drainage isn't a cure. It's management. In acute injury phases with active infection, increased drainage can theoretically spread pathogens if you're not careful about proximity to inflamed nodes. In congestive heart failure, moving fluid from the extremities increases venous return and can overwhelm a heart that's already struggling. These aren't edge cases. I see them regularly enough that I screen every client for cardiac history and signs of active infection before touching them. A quick conversation and a couple of questions about medication and recent labs usually covers it. Fibrotic tissue is another bottleneck. After years of chronic lymphedema, the subcutaneous tissue becomes fibrotic, meaning it hardens from constant protein-rich fluid accumulation and the body's response to it. Manual techniques can't reverse established fibrosis. At best, they can maintain what's mobile and provide temporary reduction. Compression garments become non-negotiable in those cases, and the clinical approach shifts toward complete decongestive therapy, which combines manual drainage with compression, exercise, and skin care. Skipping any of those four components undermines the whole thing. Self-drainage is possible and useful for maintenance between sessions, but it has a reach problem. You can't reasonably access your own axillary or inguinal regions effectively. The proximal node clearing that I mentioned earlier is nearly impossible to do properly on yourself. Most people who try it either skip it or do it so lightly that it's not effective. A partner or a therapist makes a real difference for the initial clearance sequences. After that, the distal work you can do alone with minimal instruction.
Hydration matters more than people expect. Lymph fluid is mostly water with proteins, lipids, and immune cells. Dehydrated clients have more viscous lymph, which moves slower through the channels. I usually recommend 500 milliliters of water within an hour after a session, not because the fluid disappears instantly but because rehydration supports the kidney's role in overall fluid balance, which affects lymph production rates. It's a small factor but a consistent one. If you're looking to learn this further, the clinical standards are set by the International Society of Lymphology and the associated certification pathways. There are also university-level courses in lymphedema therapy that cover the anatomy and physiology in enough depth to practice safely. A two-day workshop won't make you competent. It will teach you the strokes. Competence comes from supervised hours and repeated assessment of individual anatomy, because two people with the same diagnosis can have very different drainage patterns depending on surgical history, scarring, and prior trauma.