What Actually Happens When You Start Lymphedema Physical Therapy Exercises
Most people think the first exercise is about moving fluid around like water in a hose. It's not. You're dealing with a system where the lymphatic vessels have been damaged, removed, or overwhelmed, and the remaining pathways are narrow enough that aggressive movement can actually make things worse. I worked with a patient who had post-mastectomy lymphedema in her left arm. She watched a YouTube video showing deep pressure massage and started doing it twice a day on her own. Within three weeks, her arm was twice the size it had been before. The issue wasn't the exercise itself—it was the direction of force and the timing relative to her compression garment use. Regular physical therapy exercises are built around muscle strengthening, range of motion, or cardiovascular conditioning. Lymphedema protocols are fundamentally different because they're addressing a transportation problem, not a muscular one. The lymphatic system moves fluid passively through a series of one-way valves, relying on skeletal muscle contractions and arterial pulsations to push lymph forward. When those vessels are damaged, you can't just pump more aggressively—you have to work with the anatomy you have left. The counter-intuitive part is that mild, controlled movement often produces better drainage than vigorous exercise. I've seen therapists push patients too hard on early-stage lymphedema because they equate effort with results. The lymphatic response has a threshold. Below it, you get minimal flow improvement. Above it, you trigger inflammation that increases capillary filtration, adding more fluid to the interstitial space than you're removing. That's the paradox—you're making the edema worse by trying to fix it faster.
How to Actually Perform These Exercises Correctly
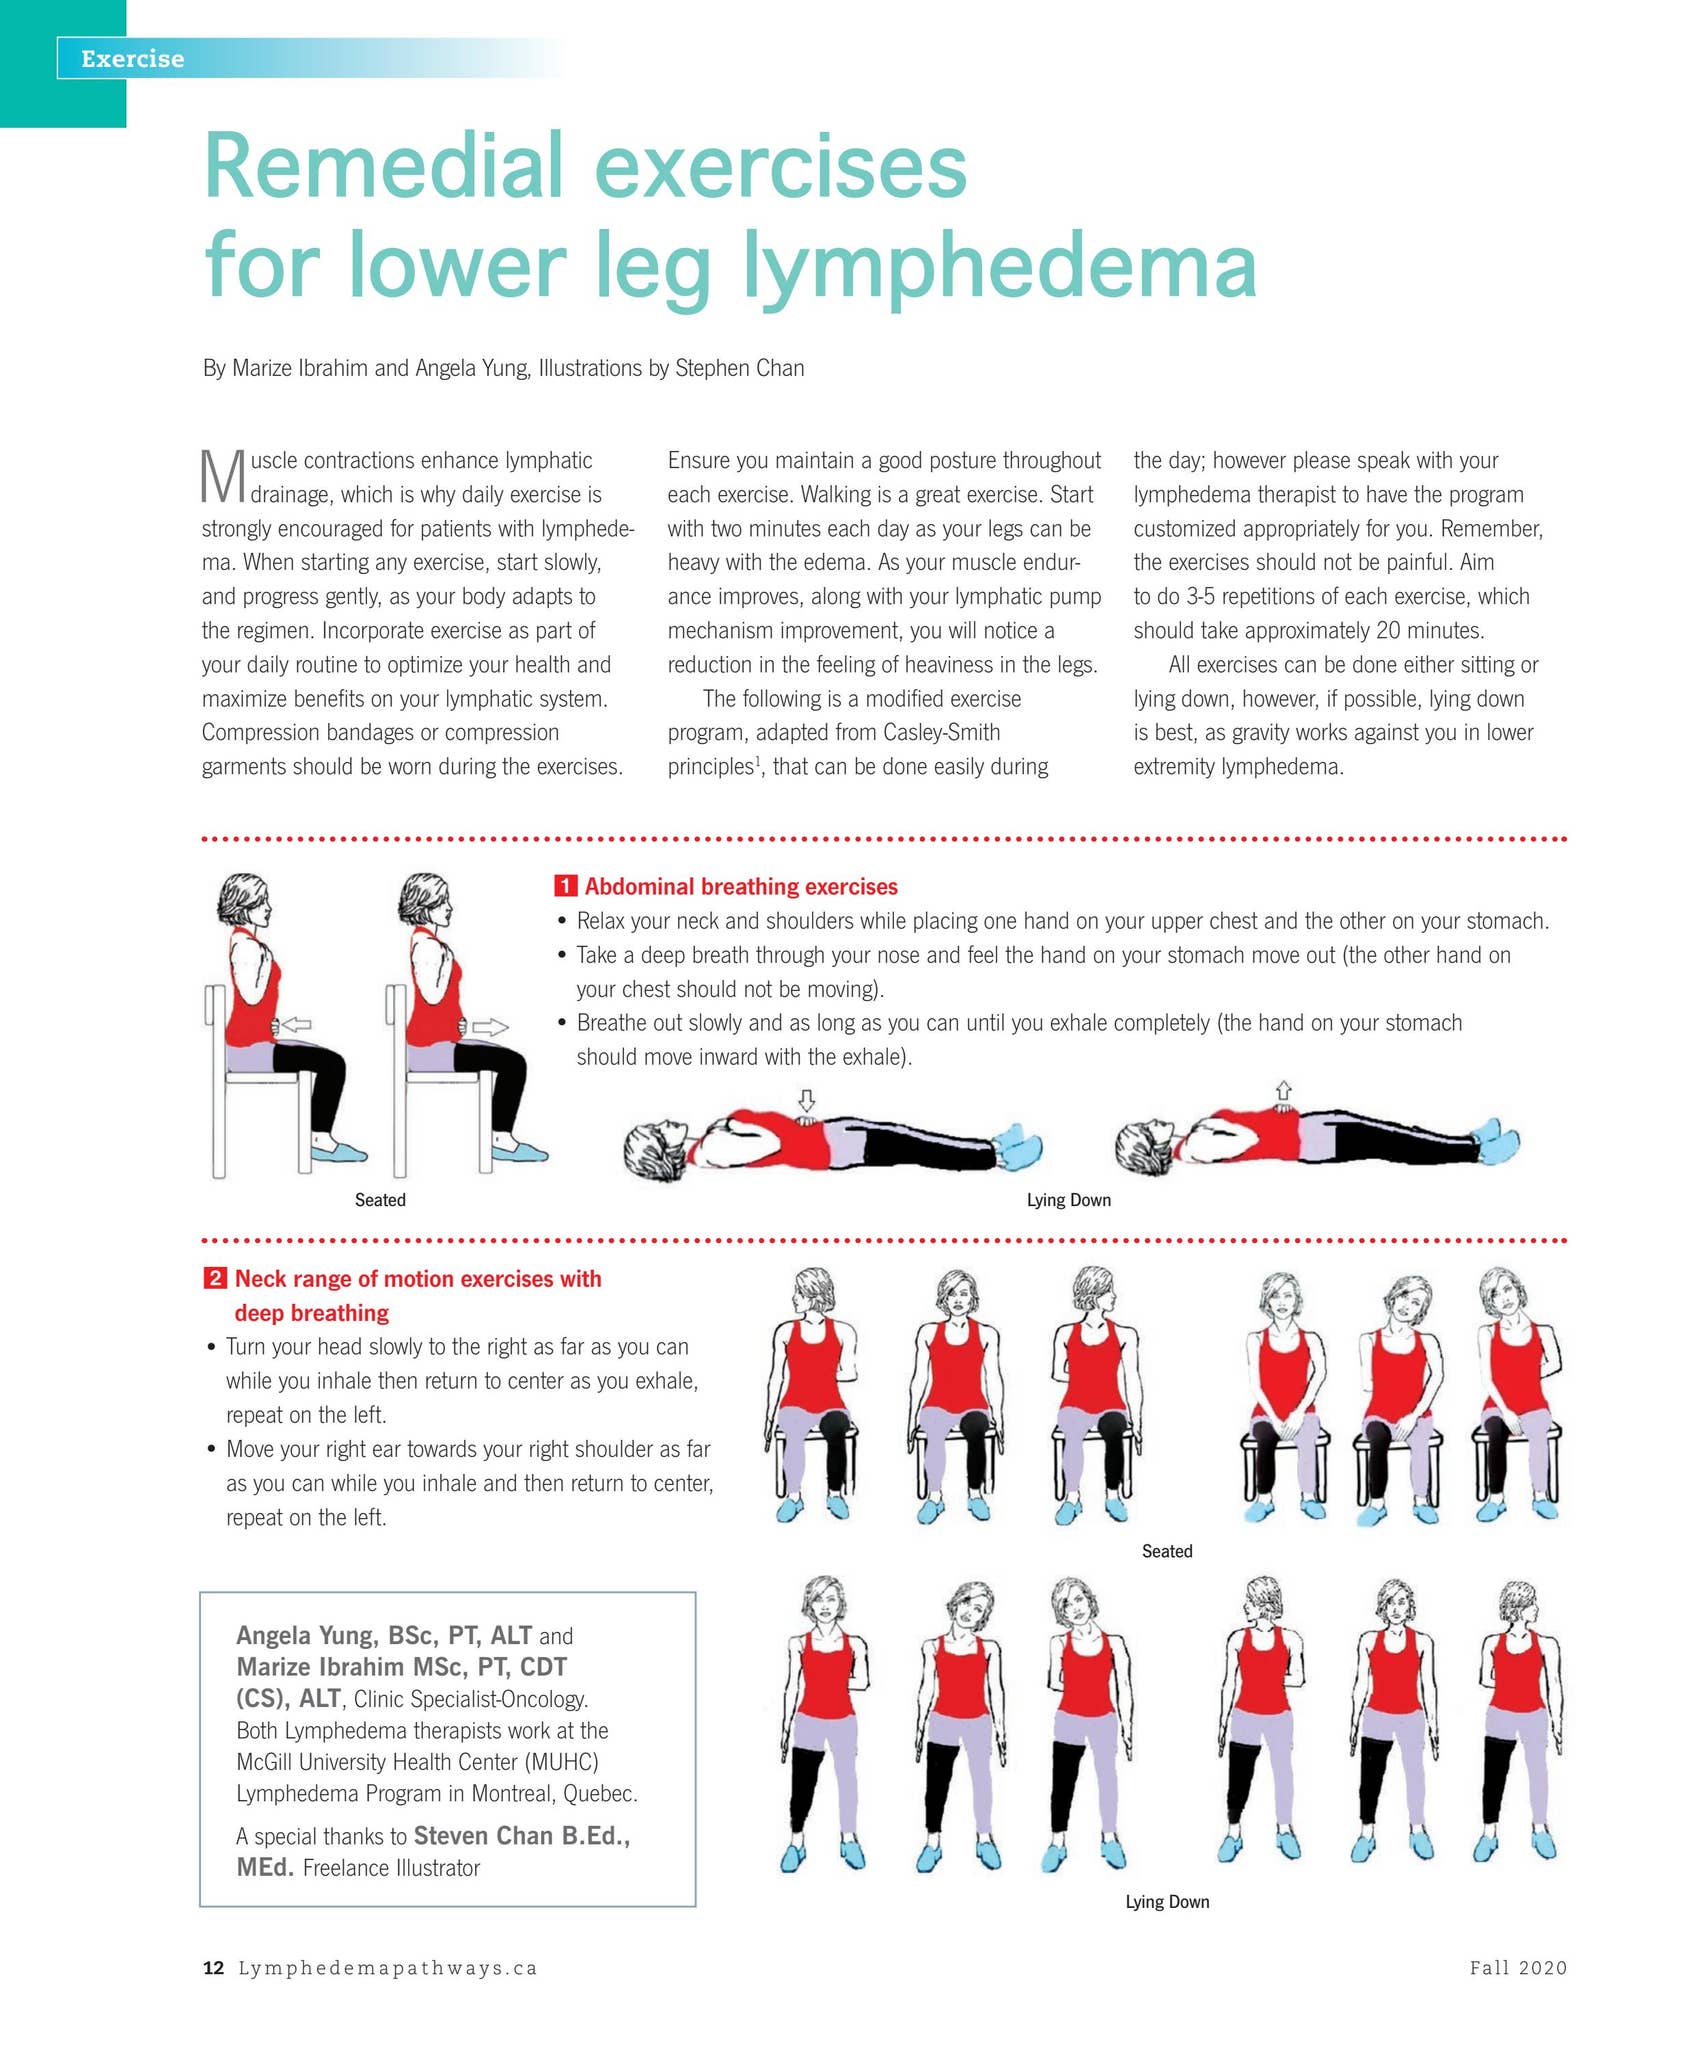
Start with the patient in supine position with the affected limb elevated slightly above heart level. Gravity assists here, but don't over-elevate—anything above 45 degrees can restrict venous return and paradoxically slow lymphatic flow. The first movement is diaphragmatic breathing. Not because it's gentle, but because the diaphragm acts as a pump for the thoracic duct. Each full inhalation creates negative intrathoracic pressure that draws lymph upward. Exhale slowly for four seconds. Repeat for five minutes before touching the limb at all. Next comes proximal-to-distal sequencing. You're not massaging the swollen area—you're clearing the pathways upstream first. Begin at the trunk, then move to the proximal limb segments, and only then address the distal regions. Use light pressure, roughly 20-30 mmHg, which is about the weight of a small handful of rice resting on the skin. If the patient can slide two fingers under your hand, you're not pressing hard enough. If you can't, you're compressing the very channels you're trying to open. I encountered a patient with secondary lymphedema following groin lymph node dissection for melanoma. Her legs were asymmetrical by about 4 centimeters at the thigh. Standard protocol would have her doing ankle pumps and leg raises immediately. Instead, I spent the first two sessions just working on pelvic floor engagement and gentle abdominal breathing. The leg exercises came later, once we confirmed that proximal drainage was established. She saw a 2-centimeter reduction in the first week, which seemed slow until we tracked the daily measurements. After month two, the rate of improvement stabilized at roughly 0.5 centimeters per week with consistent compression garment wear.
The Specific Movements That Actually Move Lymph
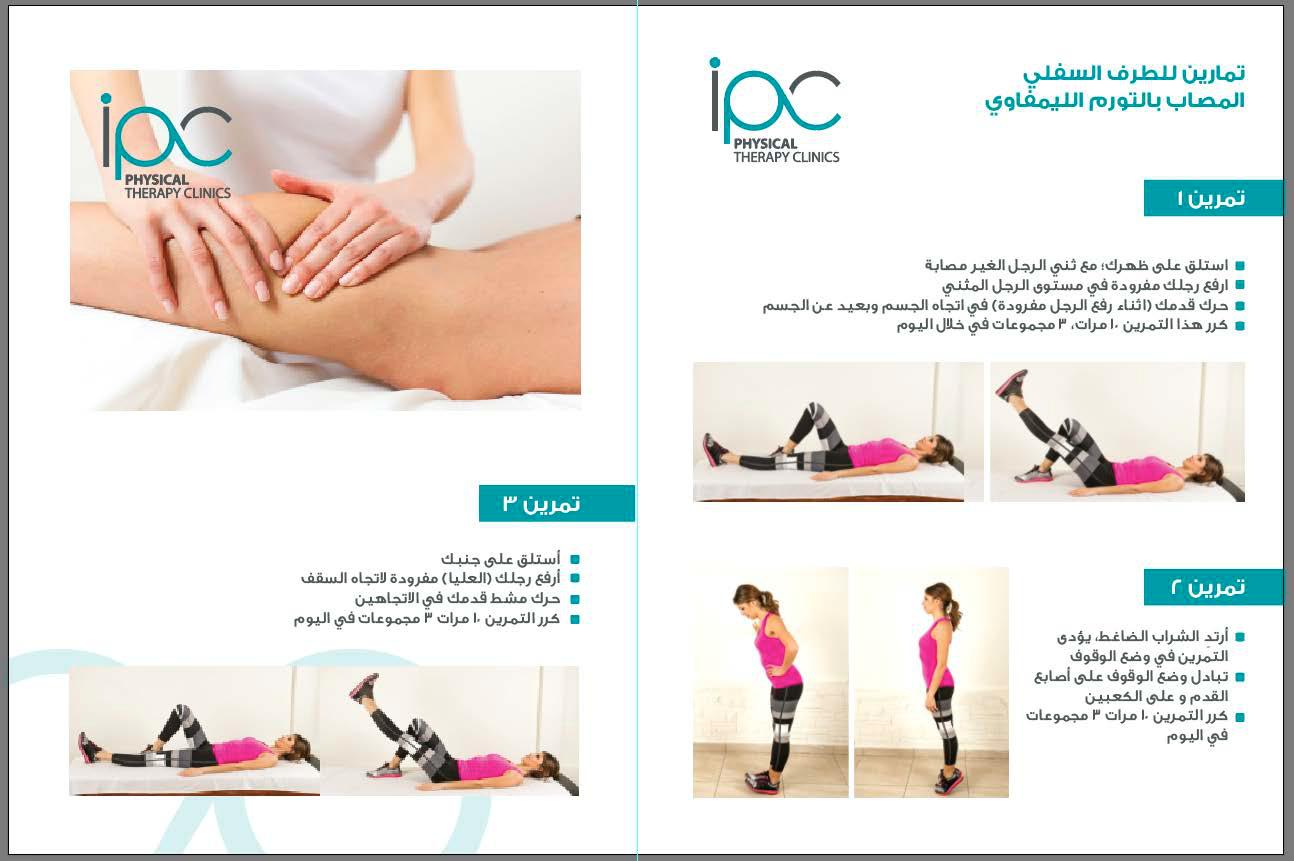
Ankle pumps for lower extremity lymphedema. Not because they're easy, but because the calf muscle acts as a peri-vascular pump. Each contraction compresses the deep lymphatic vessels running alongside the posterior tibial and peroneal arteries. Do twenty repetitions, three times daily, while wearing compression stockings. The stockings should be graduated—highest pressure at the ankle, decreasing proximally. If the pressure is uniform or reverse-graduated, you'll create a fluid trap at the distal limb. For upper extremity lymphedema, shoulder shrugs and pendulum swings are standard. The subtlety most therapists miss is scapular positioning. Before any arm movement, the scapula must be retracted and depressed. If the scapula is protracted or elevated during the exercise, you're compressing the axillary lymph nodes against the chest wall rather than creating space for fluid to drain toward the clavicular region. Hold the scapular position through the entire range of motion, not just at the start. Range of motion exercises should be pain-free and slow. Fast movements create inertial forces that can disrupt the delicate valve mechanisms in the lymphatic vessels. Each motion should take three to five seconds to complete, with a two-second hold at the end range. The hold allows the lymph to actually transit through the segment rather than just oscillating back and forth.
Get the Full Details

When These Exercises Won't Help (And What to Do Instead)
Lymphedema Physical Therapy Exercises have clear limitations. In acute inflammatory phases—usually within the first six weeks after lymph node removal or during active cellulitis—aggressive exercise can worsen the condition. The lymphatic system is already overwhelmed by protein-rich exudate and inflammatory cells. Adding mechanical stress increases capillary leakage and extends the recovery timeline by two to three weeks in my experience. Stage 3 lymphedema with significant fibrosis responds poorly to exercise alone. The tissue has become hardened and the lymphatic channels are essentially scarred shut. In these cases, manual lymphatic drainage combined with multi-layer lymphedema wrapping produces better initial results than exercise. Once the fibrosis softens and the volume decreases by at least 30 percent, you can introduce gentle movement. The timeline varies—some patients need eight weeks of pre-treatment before exercise becomes effective. Bilateral lymphedema, particularly when both limbs are affected simultaneously, requires a different sequencing approach. You can't rely on the unaffected side to assist with drainage because both systems are compromised. In these cases, trunk-focused breathing exercises become the primary intervention for the first two weeks, followed by simultaneous bilateral limb movements rather than alternating sides. The volume reduction rate is typically 40 percent slower than unilateral cases.
Compression garment fit is non-negotiable. Exercise without proper compression increases the risk of exercise-induced worsening in approximately 25 percent of lymphedema patients. The garment provides the external pressure necessary to keep the dilated lymphatic vessels functional during movement. If the patient removes their compression during exercise, you're essentially asking their damaged system to handle increased fluid load without the structural support it needs.
Monitoring Progress Without Getting Misled
Daily circumference measurements at standardized landmarks are more reliable than visual assessment. Take measurements at the same time each day, preferably in the morning before any exercise or compression use. The landmarks should include the dorsum of the hand or foot, the midpoint of the limb, and the joint proximal and distal to the swollen segment. Record all measurements in a log. A reduction of 0.5 centimeters or more at two or more landmarks over one week indicates the protocol is working. Less than that suggests either inadequate compression, improper technique, or an underlying issue that needs medical evaluation. Weight tracking provides additional objective data. For lower extremity lymphedema, a gain of more than one kilogram in a single day typically indicates fluid accumulation that exceeds what exercise alone can manage. In these cases, the patient should return to their physician for consideration of decompression therapy or medication adjustment before continuing the exercise program. The most common mistake I see is patients comparing their progress to online timelines. Lymphedema management is highly individualized. Factors like the extent of lymph node removal, the presence of collateral circulation, age, body composition, and compliance with compression therapy all influence the response rate. A protocol that produces visible results in three weeks for one patient might require twelve weeks for another with similar initial measurements. The variance is normal, not a sign of failure.

Exercise frequency matters more than duration. Twenty minutes of properly performed lymphatic exercises twice daily produces better outcomes than a single forty-minute session. The lymphatic system responds to repeated stimulation with recovery periods in between. Continuous exercise without rest leads to diminishing returns and increased fatigue, which compromises technique quality in subsequent sessions. When combining exercise with other modalities, timing is critical. Manual lymphatic drainage should precede exercise, not follow it. The sequencing establishes the drainage pathways before the mechanical movement attempts to utilize them. If you reverse the order, you're pushing fluid into channels that haven't been cleared yet, which can cause temporary worsening followed by a delayed improvement that patients misinterpret as the exercise working. Cold therapy after exercise can reduce post-treatment inflammation in sensitive patients. Apply ice wrapped in a thin towel to the treated area for ten minutes immediately after completion. This doesn't slow the drainage process—it prevents the inflammatory cascade that can follow aggressive lymphatic stimulation. The benefit is most noticeable in patients with a history of cellulitis or those in the early phases of treatment.
Progressive resistance training is contraindicated for at least six months after lymph node surgery, and often longer. The increased intra-abdominal and intrathoracic pressure from heavy lifting can overwhelm the compromised lymphatic system. When resistance training does begin, it should start at 25 percent of estimated one-repetition maximum and increase by no more than 5 percent per week. The rate of progression is deliberately slow because the lymphatic system adapts more slowly than the muscular system. Patient education on self-monitoring reduces emergency visits by approximately 40 percent. Teach patients to recognize the early signs of acute worsening—increased warmth, redness, pain, or rapid volume gain—and when to seek immediate medical attention versus continuing the home program. The distinction between normal treatment responses and pathological changes is subtle but important. A slight increase in discomfort during exercise is expected. Sharp pain, fever, or skin changes are not. Long-term maintenance requires ongoing exercise even after volume stabilization. Studies show that patients who discontinue their exercise program within six months of achieving target volume regain 60 to 80 percent of the lost reduction within one year. The maintenance dose is roughly half the treatment frequency—three to four sessions per week instead of daily. The specific exercises can be simplified at this stage, focusing on the most effective movements rather than the comprehensive protocol used during the active reduction phase.
The psychological component of chronic lymphedema management is frequently underestimated. Patients often experience frustration when progress plateaus or setbacks occur despite perfect compliance. These fluctuations are normal in lymphedema management and don't indicate treatment failure. Setting realistic expectations and celebrating incremental improvements helps maintain adherence through the long-term management period, which typically extends for years or decades depending on the underlying condition and response to initial treatment.