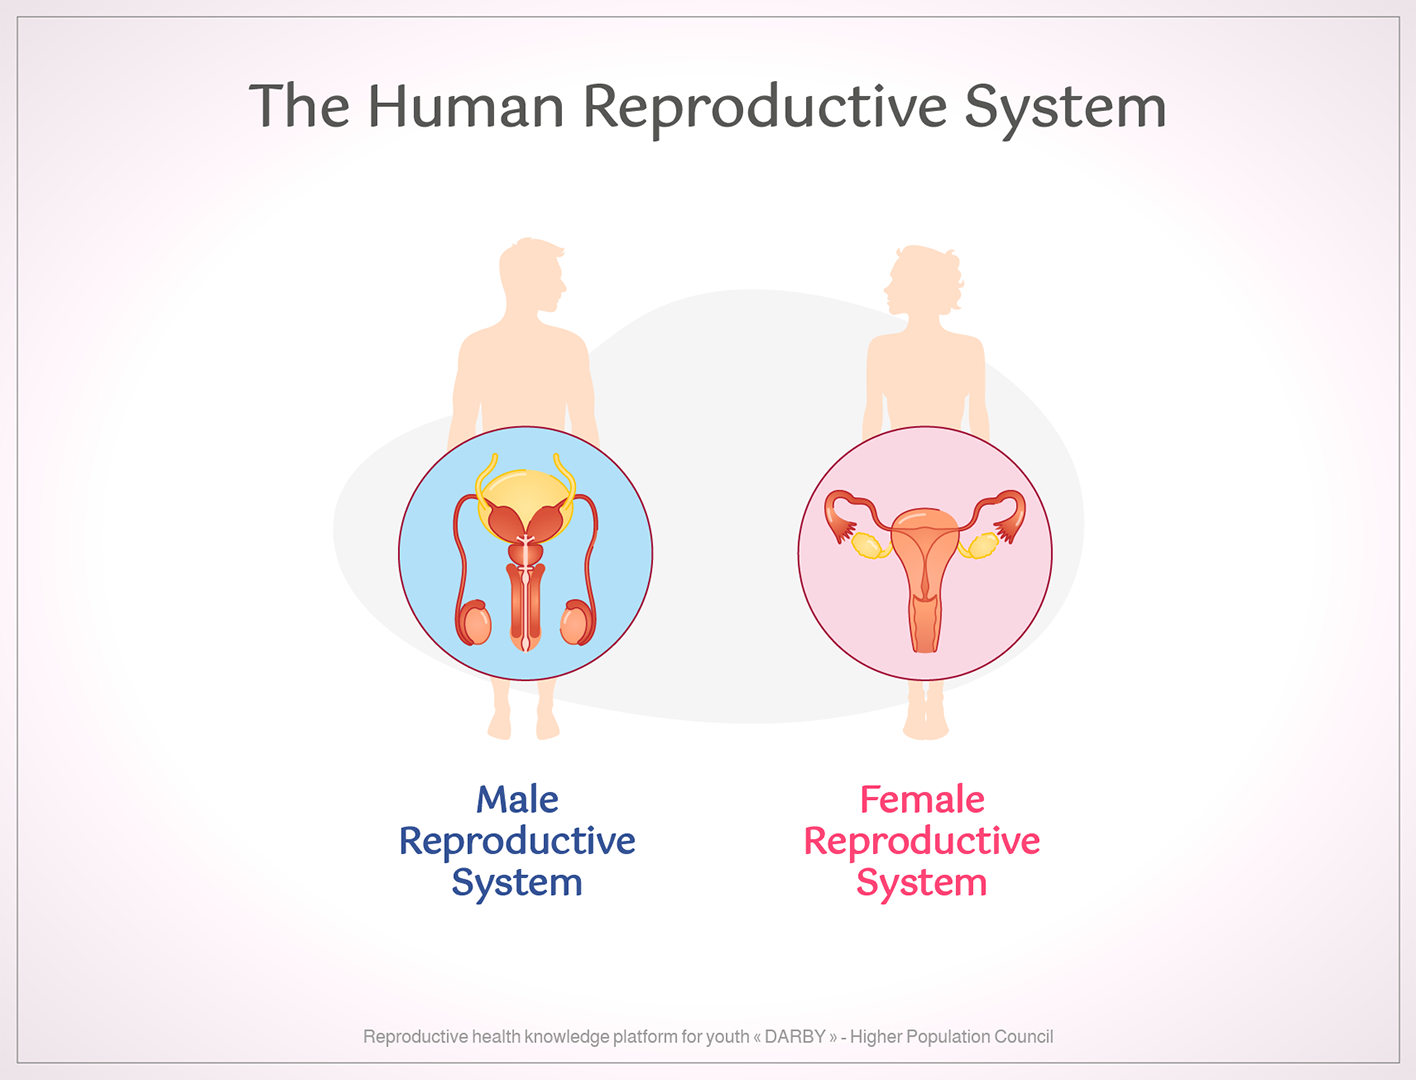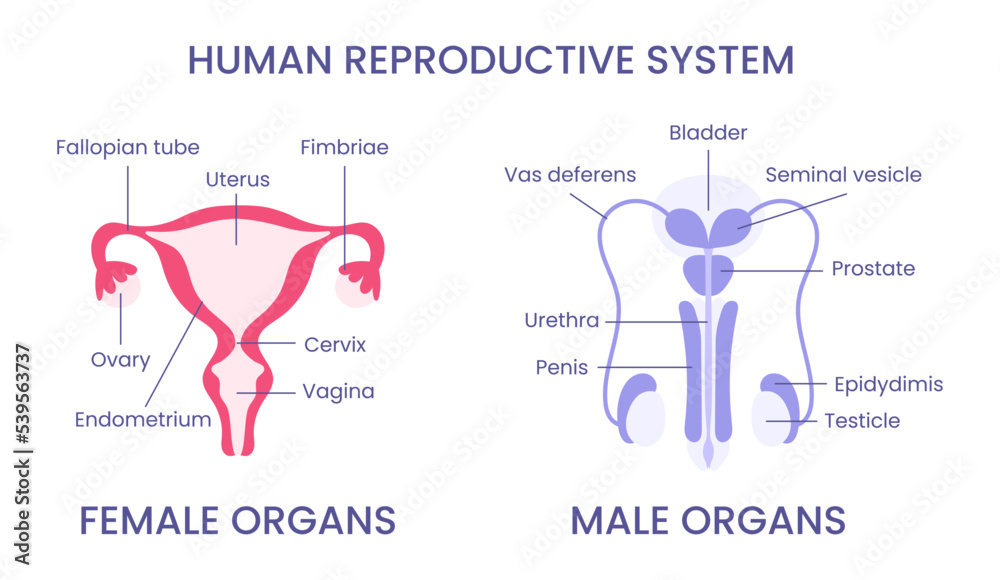
So you need to understand the Male And Female Reproductive Tract and actually use that knowledge, not just regurgitate textbook diagrams.
I spent years working with medical imaging and urology consults before I ever saw a fully functional tract outside of an illustration. The first thing most people miss is that the tract is not two separate systems neatly packaged side by side. It is a continuous series of conduits, glands, and exchange surfaces that do not operate on the same timeline. You have to think in terms of transit time, not just structure. Here is how I approach it when someone asks me to walk through the system from start to finish.
Male And Female Reproductive Tract: Where Most People Get Confused
The male tract moves sperm from the seminiferous tubules through the rete testis, efferent ductules, epididymis, vas deferens, ejaculatory duct, and urethra. That is the standard list. The part nobody remembers is that sperm are not motile enough to travel the vas deferens on their own. They sit in the epididymis in a protein-rich fluid that keeps them quiescent until smooth muscle contraction during ejaculation forces them forward. If you are studying for boards or counseling patients, you need to know that epididymal transit takes roughly 10 to 14 days. Shorten that with inflammation or obstruction and you get oligospermia or complete blockage. I once had a patient who presented with azoospermia and elevated FSH. We ruled out obstruction with a scrotal ultrasound and semen fructose testing. The fructose was present, which meant the seminal vesicles were patent and draining. The problem was testicular failure, not a tract blockage. That distinction saved him from an unnecessary surgical exploration. Most clinicians jump to the vas deferens first because it is easier to image, but the testis itself was the actual issue. Know the diagnostic hierarchy before you order invasive tests. The female tract is semicolon different in both purpose and mechanics. Ova travel from the ovary into the fallopian tube, where fertilization usually occurs in the ampulla. From there the zygote moves into the uterus and implants in the endometrium. The cervix sits at the bottom as a gatekeeper. It is not a passive pipe. Mucus consistency changes across the cycle, becoming more permeable around ovulation and denser the rest of the month. That mucus barrier is why I always tell patients trying to conceive or avoiding pregnancy that cervical mucus observation is far more predictive than calendar tracking alone.
One thing students consistently underestimate is the uterine cavity shape. A normal cavity is roughly triangular in cross section. When I review hysterosalpingograms, the first thing I look for is whether that triangle is intact or distorted. Septate uteri, bicornate configurations, and intrauterine adhesions all present differently on imaging and require completely different management. Treating a septate uterus with blind d & c is a well documented pitfall that leads to recurrent loss. Hysteroscopic resection under direct visualization is the standard now. I saw a case last year where a patient had three first trimester losses before someone finally caught a thin septum on 3D ultrasound. She carried to term after the resection. Both tracts share one functional requirement: they need hormonal signaling that is precisely timed. The hypothalamic-pituitary-gonadal axis drives everything in the male system through pulsatile GnRH, LH, and FSH release. The female system adds cyclical feedback loops that create the ovarian and endometrial cycles. Disrupt the pulse frequency and you disrupt spermatogenesis or ovulation. I have seen men with normal testosterone levels who still had low sperm counts because their FSH was suppressed from exogenous steroid use. The tract looks fine on imaging, but the signaling is broken upstream. When I explain clinical relevance, I focus on three things that actually matter in practice.
Get the Full Details

First, timing. Sperm production takes about 74 days from spermatogonia to mature sperm. If you are evaluating a lifestyle change, a new medication, or a febrile illness, you are not seeing the full effect for over two months. Patients get frustrated because they expect results within weeks. Tell them the 74 day window upfront and it cuts follow up visits in half. Second, the blood-testis barrier. It protects developing sperm from immune attack, but it also limits drug delivery. Many antibiotics and anti-inflammatories do not penetrate well. If you are treating epididymitis, you pick agents with good tissue penetration like fluoroquinolones or doxycycline, not the first thing in the formulary. Third, the female tract is colonized. The vagina has a lactobacillus dominant microbiome in healthy reproductive aged women. Disturb that with douching, broad spectrum antibiotics, or hormonal contraception in some cases and you open the door to bacterial vaginosis and infection. I always ask patients about douching habits before ordering yeast or BV testing. Half the recurrent cases trace back to a habit they never mentioned because they assumed it was irrelevant.
If you want a practical framework for studying this, stop memorizing structures in isolation. Map them by function. Follow one sperm or one ovum from origin to exit and note every checkpoint where pathology can interrupt the journey. That is how I learned it and that is how I teach it now. There is no shortcut that replaces understanding transit, signaling, and barriers. Everything else is just vocabulary.