Identifying Pelvic Sex: What Actually Works
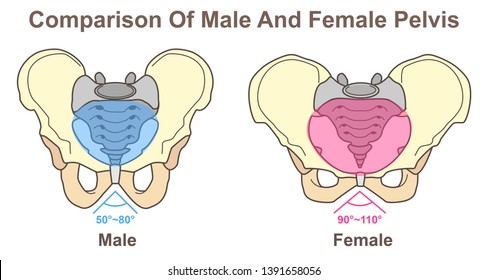
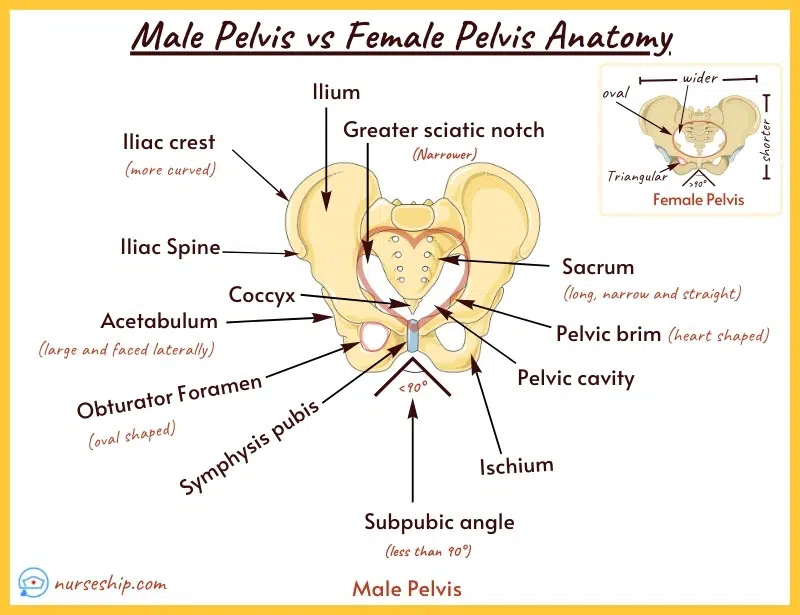
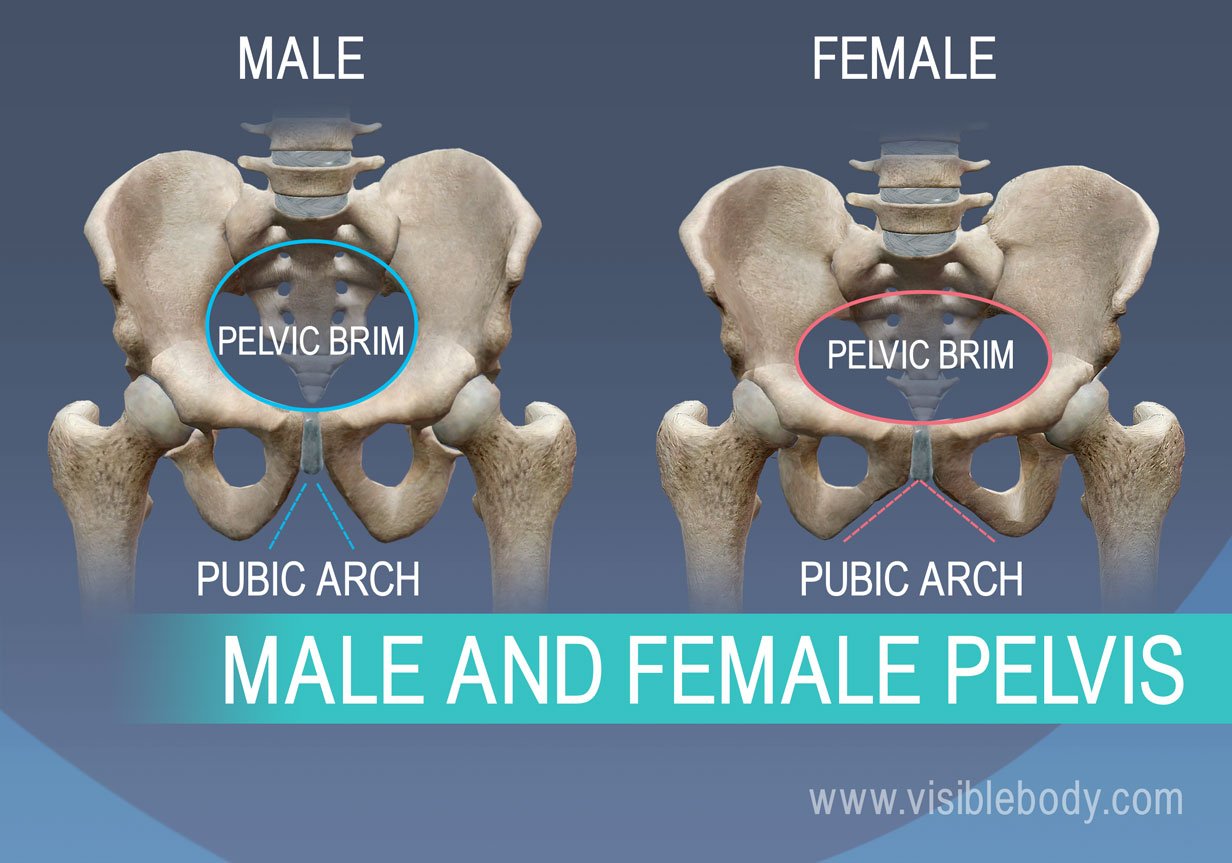
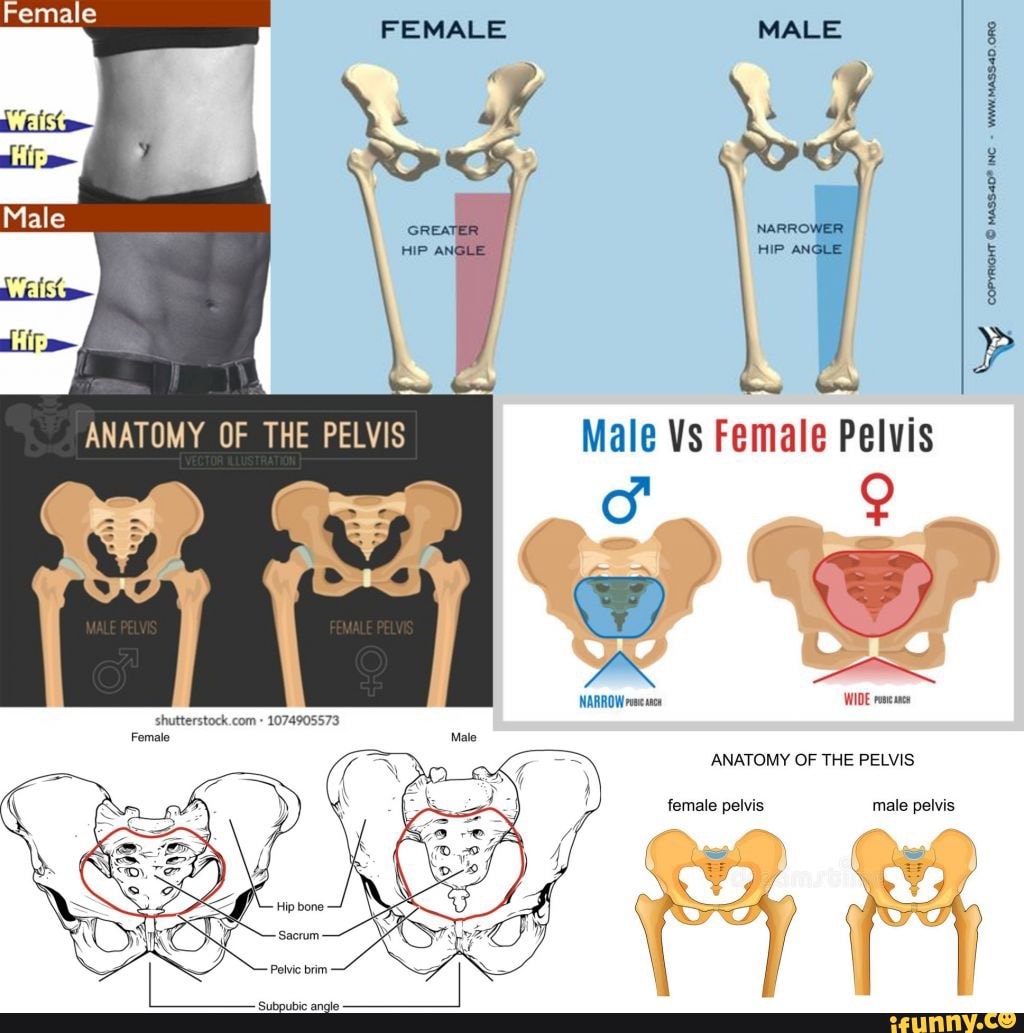
The male versus female pelvis distinction comes up constantly in forensic anthropology, anatomy labs, and yes, even in some medical imaging contexts. People tend to overcomplicate it. It's really just a matter of knowing which features to look at and in what order. I've spent years going through cadavers and CT scans, and the quick-and-dirty version is that female pelves are generally broader and more open, while male pelves are narrower and more robust. But "generally" doesn't pay the bills when you're staring at a fragment and need to make a call. Start with the greater sciatic notch. This is the single most reliable feature, and honestly, if you only remember one thing, make it this one. In females, it's wide and shallow, usually greater than 90 degrees. In males, it's narrow and deep, typically under 70 degrees. There's overlap, sure, but not as much as people think. I was working a case last year where the ilium was fractured and the notch was partially obscured. Had to fall back on the pubic arch angle instead, which runs about 90 to 100 degrees in females and 50 to 60 in males. Next, look at the subpubic concavity. Female pelves have a noticeable curve on the inferior surface of the pubic body. Male pelves are mostly flat or slightly convex there. Then check the preauricular sulcus, a groove just in front of the auricular surface on the ilium. It's far more common in females, though its absence in a female doesn't rule anything out. It's present in maybe 60 to 70 percent of females and 10 to 20 percent of males. Don't rely on it alone.
The iliac flaring is another thing worth noting. Female ilia flare outward more, giving that wider hip appearance. Male ilia are more vertical and closer to the midline. The overall shape tells you something even before you measure anything. A female pelvis looks almost like a wide bowl. A male pelvis looks more like a narrow, steep-walled container. It's crude but effective for quick screening. Move down to the acetabulum. In males, it's larger and more circular. Females tend to have slightly smaller, more oval-shaped acetabula. The ischial spines are another marker. They're pointed and project more in males, while in females they're blunter and flatter, partly because of the demands of childbirth reshaping the canal over time. The pubic bone itself differs too. Males have a rougher, more muscular attachment area because of the higher androgen exposure during development. Females have a smoother surface. One thing nobody emphasizes enough is that size matters less than proportion. A small female pelvis can be larger in absolute dimensions than a large male pelvis, so don't fall into the trap of just measuring everything and picking the biggest number. Look at the relationships between features. That's where the actual diagnostic power lives.
Practical Application and Where Things Go Wrong
I'll walk you through how I actually approach this in practice, because reading about features and using them are two different things. First, I position the pelvis so I'm looking straight down at the pelvic inlet. From that view, the shape difference between male and female becomes immediately obvious. The female inlet is more oval and spacious. The male inlet is heart-shaped and tighter. This is the Gilmartin method, adapted from the work of Gilmartin and others in the field, and it's still the fastest way to get a preliminary answer. After that initial visual pass, I go through a scoring system. The most common one is the Phenice method, which focuses on three features: the ventral arc, the subpubic concavity, and the medial aspect of the ischiopubic ramus. All three point toward female morphology when present. I assign points for each feature and tally them up. Three points strongly suggests female. Zero points strongly suggests male. One or two points is the gray zone where you need to bring in additional markers. Here's where I ran into trouble recently. I had a pelvis that was essentially a Phenice score of two, which should lean female, but the sciatic notch was narrow, the iliac flare was minimal, and the overall robusticity looked male. The person was a tall, lean woman in her late sixties with significant osteoporosis. The bone loss had changed the shape of the pubic rami and made the subpubic angle appear narrower than it actually was. I nearly miscategorized it. What saved me was going back to the sacrum. The female sacrum is shorter, wider, and has less curvature than the male version. Combined with the hip bone morphology and some metric analysis, I confirmed it was female. The lesson here is that age-related changes can blur the sexual dimorphism you're relying on. Always cross-reference.
Get the Full Details

Another common pitfall is assuming that all individuals fit neat categories. Population variation is real. Nordic males tend to have pelves that overlap with Mediterranean females in certain dimensions. Southeast Asian populations show different norms altogether. If you're working with an unknown sample, don't apply a single standard universally. I've seen people use Austin Southwestern standards on Asian remains and get wildly wrong answers. Find population-specific data when you can, or at least acknowledge the limitation. Let me also address the elephant in the room. The male versus female pelvis framework, while useful, has limits. Intersex conditions exist. Hormonal disorders during development can shift pelvic morphology. Athletes, especially those who did heavy weightlifting or dancing from a young age, can develop masculine pelvic features regardless of genetic sex. I once had a case where a genetically female individual had a pelvis that scored firmly male on every trait. The determining factor ended up being the biological sex recorded in the case files, not the bones. Forensic work isn't just about bones, it's about context. If you're doing this for academic purposes, the Walker 2008 study on the preauricular sulcus and the Buikstra and Ubelaker manual from 1994 are the standard references. For a more practical hands-on approach, the Bass textbook "Human Osteology" has clear diagrams and scoring sheets. I keep a printed copy of the Phenice features on my desk because I get tired of flipping through pages during a live dissection or scan review. There are also free scanning software packages like 3D Slicer that let you measure angles directly on CT reconstructions, which is faster than calipers on a dry bone.
There's no shortcut around practice. You need to handle specimens, ideally both male and female, side by side. A week of actual handling will teach you more than a month of reading descriptions. The shapes settle into your memory faster that way. Once you've seen enough examples, you'll start recognizing patterns automatically. That's when it stops being a checklist and starts being instinct.