I spent about three years working with dysphagia protocols at a regional medical center before we restructured the intake process. The Masa Swallow Assessment became our standard tool for initial screening, though not everyone agrees it should be the first step.
The assessment itself is straightforward in theory. You observe how a patient handles different food textures while recording clinical indicators like cough frequency, vocal quality changes after swallowing, and visible residue in the oropharynx. What makes it tricky is that the scoring system depends heavily on the clinician's experience level.
Masa Swallow Assessment uses a seven-level texture scale that corresponds to the International Dysphagia Diet Standardisation Initiative categories, but translating those categories into actual kitchen modifications takes practice. I saw nurses and speech therapists disagree on the same patient's classification more times than I care to count.
The scoring runs from one through seven, with one being thin liquids and seven representing hard, sticky solids. Patients who score below four typically need modified consistencies, but the borderline range around scores four through five is where things get complicated.
I remember a specific case back in 2019 where a patient with early-stage Parkinson's was consistently scoring three on the assessment but actually aspirated on thin liquids during the video fluoroscopy follow-up. The assessment missed it because his compensatory strategies, chin tuck and multiple swallows, were masking the aspiration during the simple bedside portion. We ended up relying on the VFSS results instead of trusting the screening score. That's not a rare occurrence.
Common Misinterpretations During Masa Swallow Assessment
One thing beginners miss is that wetness alone doesn't determine safety. A patient might handle water fine but aspirate pudding because the thicker consistency triggers delayed swallow initiation. The assessment captures that pattern eventually, but not always on the first attempt.
Another pitfall involves fatigue. The Masa Swallow Assessment is designed to take about fifteen to twenty minutes, but by minute twelve, many patients with neurogenic dysphagia show performance decrements that look worse than their baseline. I started repeating the assessment in two shorter sessions rather than pushing through to the full protocol when I noticed that pattern.
The water swallow test portion, sometimes called the water challenge, deserves careful attention. Some protocols use 100 milliliters of room-temperature water as a screening tool, but recent literature suggests 30 milliliters might be sufficient and causes less anxiety for patients who are already hesitant about swallowing.
Setting Up a Practical Assessment Protocol
You need the right tools before starting. Ice cream spoons for thicker consistencies, thinners like hydrocolloid powders for liquid modification, and a timer. Most clinics also keep pulse oximeters nearby even though desaturation during the assessment itself is uncommon in non-ICU populations.
I documented our setup in a laminated checklist that I keep at the nursing station. The most useful section is a troubleshooting matrix for when patients refuse one of the textures, which happens more often than you would expect from a patient population that presumably has a swallowing problem.
Recording methodology matters more than people admit. I switched from narrative notes to structured data entry after noticing that two different clinicians could describe the same patient's performance in ways that looked completely contradictory on paper, even though they agreed in conversation.
The voice recording requirement post-swallow, that harsh breathy quality, has about 85 percent sensitivity for pharyngeal residue when captured correctly, but only if the patient understands what you are asking them to do. Teaching patients to clear their throats or say "ah" on command takes patience but pays off quickly.
When the Masa Swallow Assessment Falls Short
Here is the honest part. The assessment has significant limitations in certain populations. Patients with cognitive impairment, moderate dementia, or severe aphasia often produce unreliable scores regardless of their actual swallowing physiology. I stopped using it as a standalone tool for those groups and moved straight to instrumental assessment when the clinical picture suggested neurological involvement.
Another failure mode involves patients with head and neck cancer who have structural changes from surgery or radiation. The Masa Swallow Assessment assumes relatively normal anatomy with functional compromise, not altered anatomy itself. Using it in that context produces false reassurance about safety.
Compensatory strategies present a particular challenge. A patient might score well on the assessment by using chin tuck, head rotation, or bilateral hand feeding techniques, but those strategies often require cognitive capacity and physical coordination that the patient may not sustain throughout a meal. The assessment captures the behavior in a controlled setting but not the endurance required in real-world eating.
We developed a supplementary tool that tracked strategy use across multiple repetitions and time periods. It added about ten minutes to the evaluation but provided data that the standard assessment alone missed.
Documentation and Communication Requirements
The paperwork component deserves more attention than it typically receives. Insurance reviewers, facility compliance officers, and next-level clinicians all read your assessment notes, and unclear documentation creates liability even when your clinical reasoning was sound.
I learned this the hard way when a malpractice case in 2021 involved a patient who had been scored as eating regular textures based on a Masa Swallow Assessment that morning but choked during lunch service that same day. The assessment had been completed but not re-assessed after the dietary change, and the documentation did not reflect that gap.
Your records should include the specific textures tested, the approximate volume used for each consistency, the patient's response pattern, and any compensatory strategies observed. Note the time of day as well because fatigue significantly affects swallowing performance in progressive conditions.
Communication with the dietary services team requires precise language. "Modified diet" means nothing without specifying which IDDSI framework you are using and what texture levels are approved. I started including a visual reference card in my discharge summaries after receiving repeated requests from home health agencies who could not interpret our written descriptions.
The follow-up timing matters too. A single Masa Swallow Assessment result does not establish a trajectory. I recommend repeating the assessment within 48 hours for acute neurological events and weekly for progressive conditions until a stable baseline is established.
Training Considerations for Clinical Staff
Competency validation should not be a one-time event. I witnessed a speech pathology resident who had been certified on the assessment two years prior miss obvious coughing patterns during a routine evaluation simply because she had not maintained recent practice volume.
We implemented quarterly skill verification sessions where staff were given a simulated patient case and scored on both technique and interpretation accuracy. The results showed a gradual drift in inter-rater reliability over time that we had not been tracking before.
Self-study materials help but do not replace supervised practice. I assigned video libraries of typical and atypical presentations to residents during orientation, but the real learning happened during the second month when they conducted assessments under direct observation and received immediate feedback on their scoring decisions.
The cultural dimension deserves mention as well. Patients from different backgrounds may respond differently to the clinical environment, and that response can affect assessment performance independent of their swallowing physiology. I worked with a Turkish patient whose family considered eye contact with authority figures disrespectful, and he consistently performed below his actual capability during the assessment because of that discomfort. Adjusting the environment produced more accurate results.
Gallery Masa Swallow Assessment
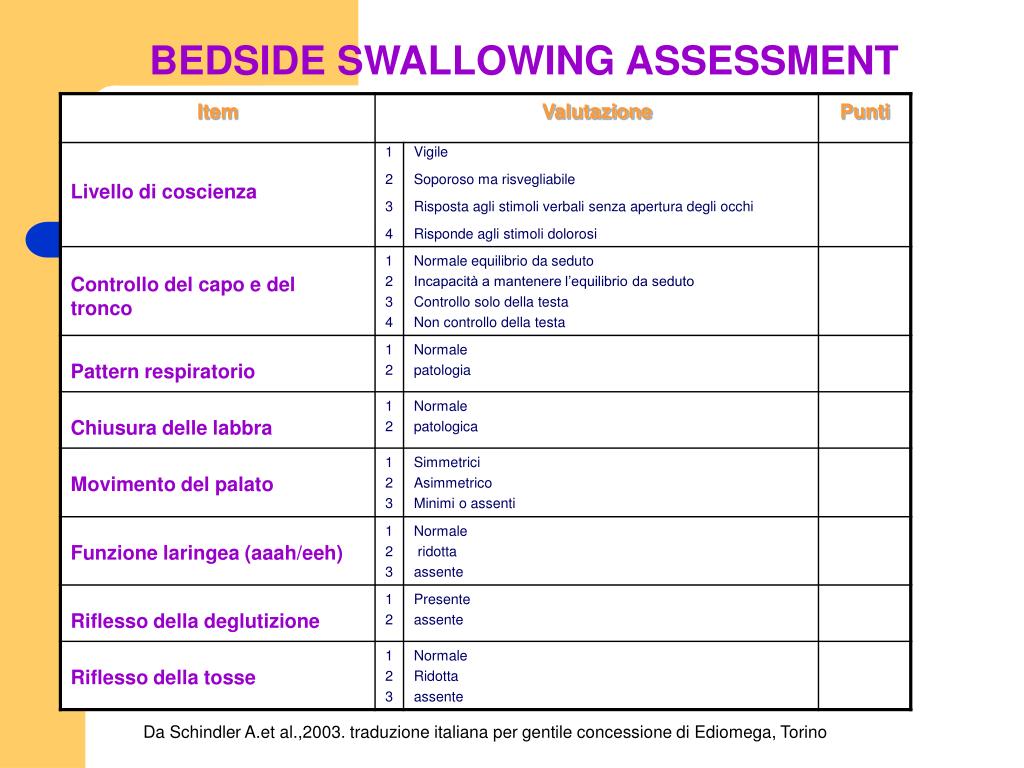
Masa Swallow Pdf , MASA: The Mann Assessment of Swallowing Ability ...
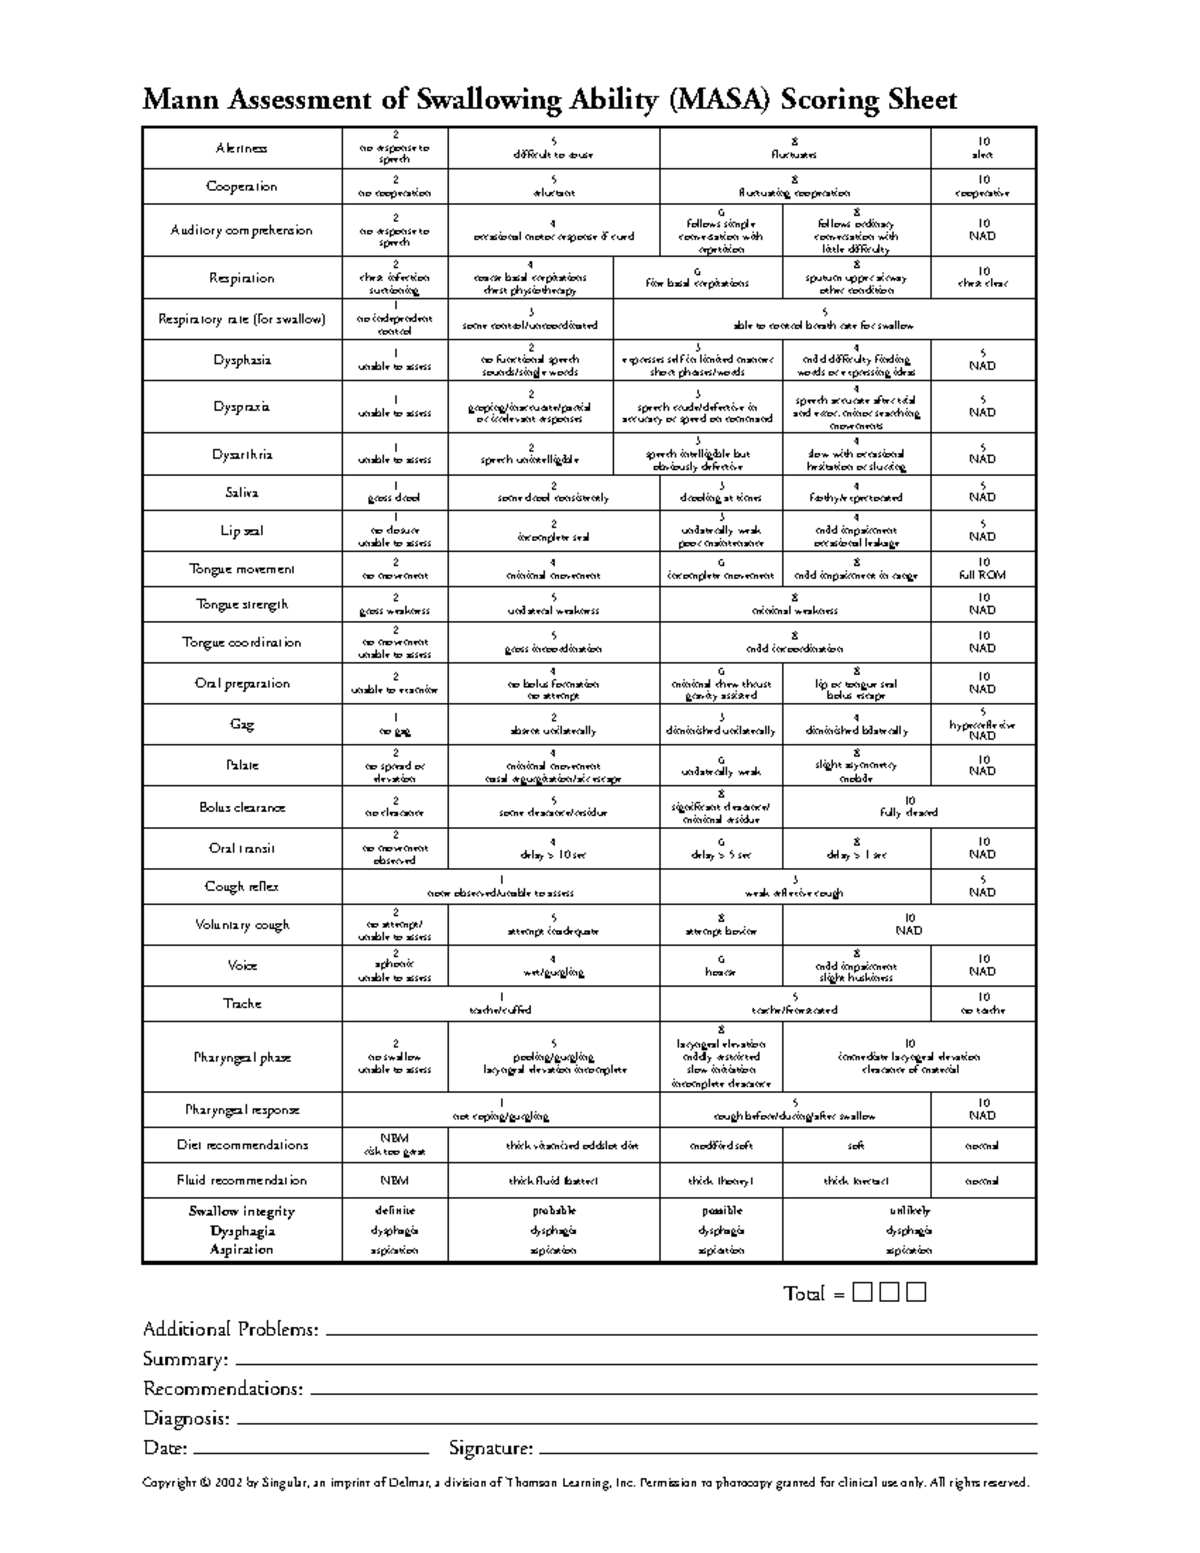
Mann Assessment of Swallowing Ability (MASA) Scoring Sheet Overview ...
Mann Assessment of Swallowing Ability (MASA) Scoring Sheet | Medical ...
Mann Assessment of Swallowing Ability (MASA) Scoring Sheet / mann ...
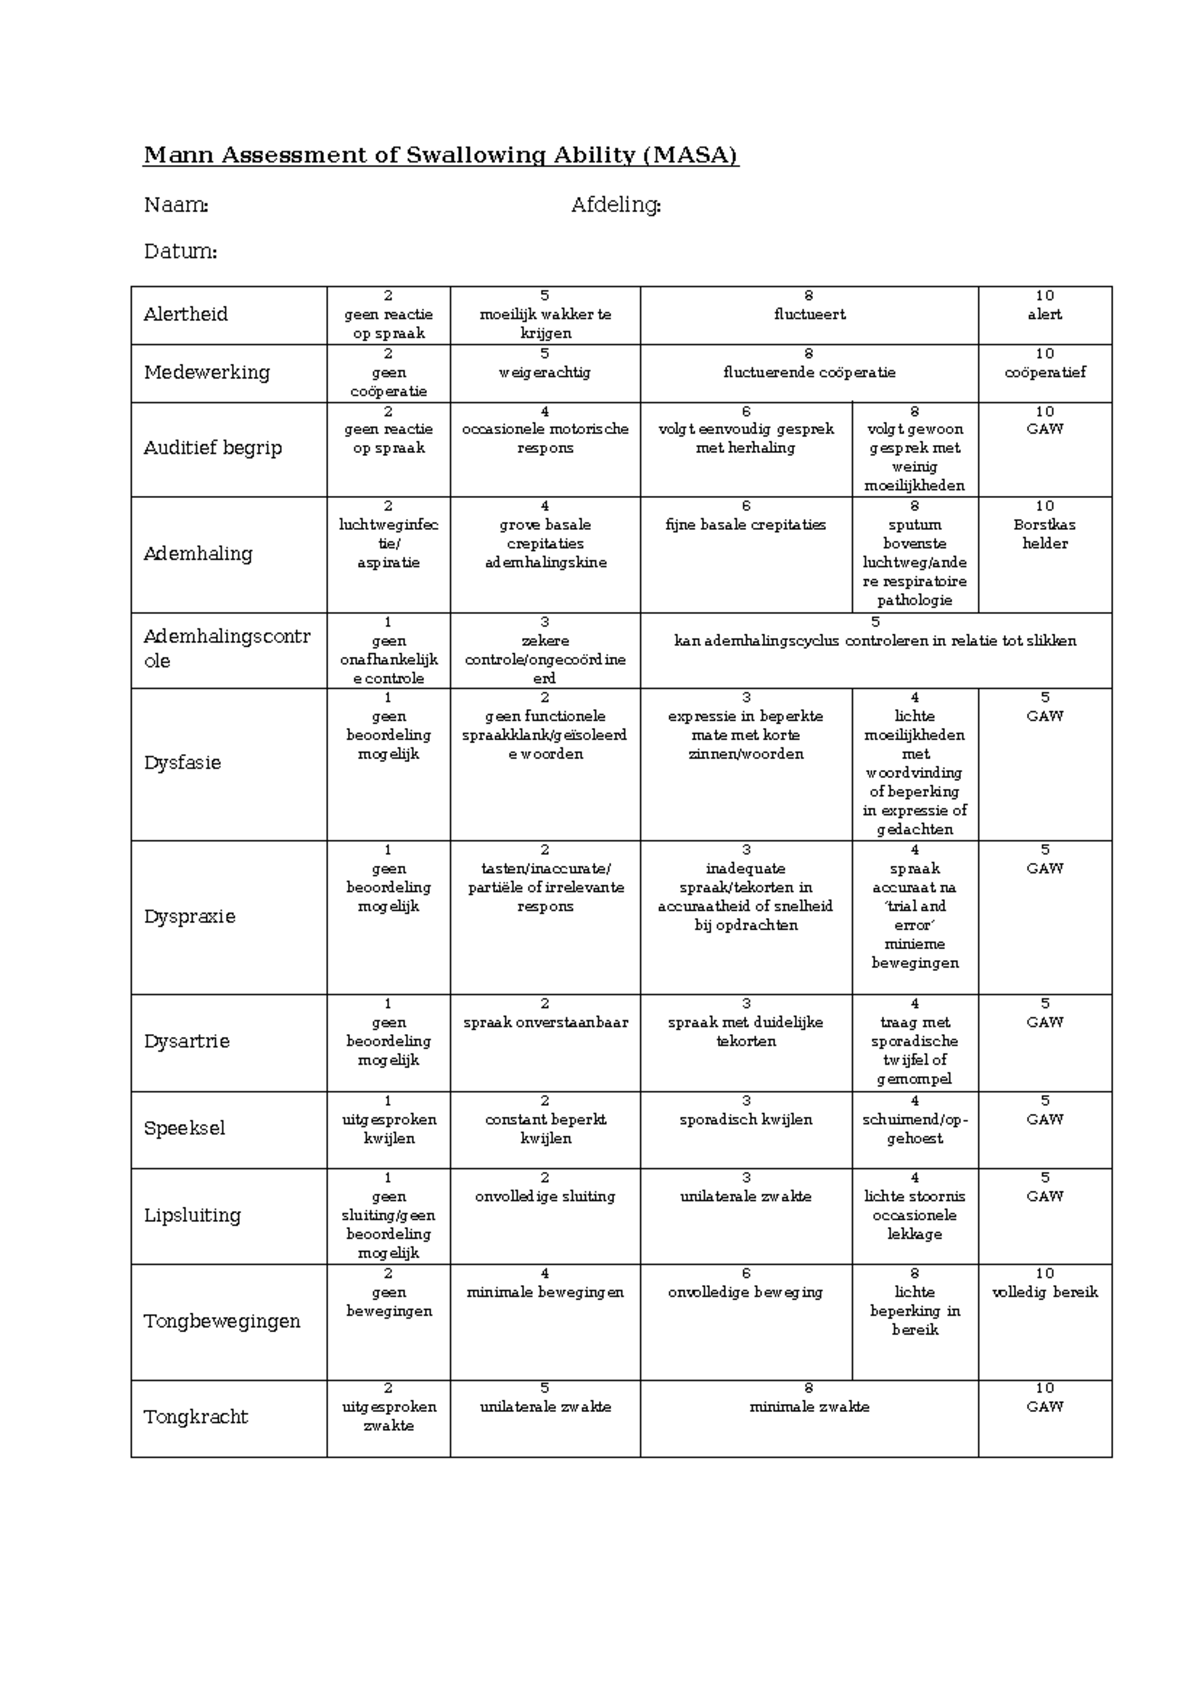
Mann Assessment of Swallowing Ability (MASA) - Detailed Evaluation ...