
What Full Practice Authority Actually Means in Massachusetts
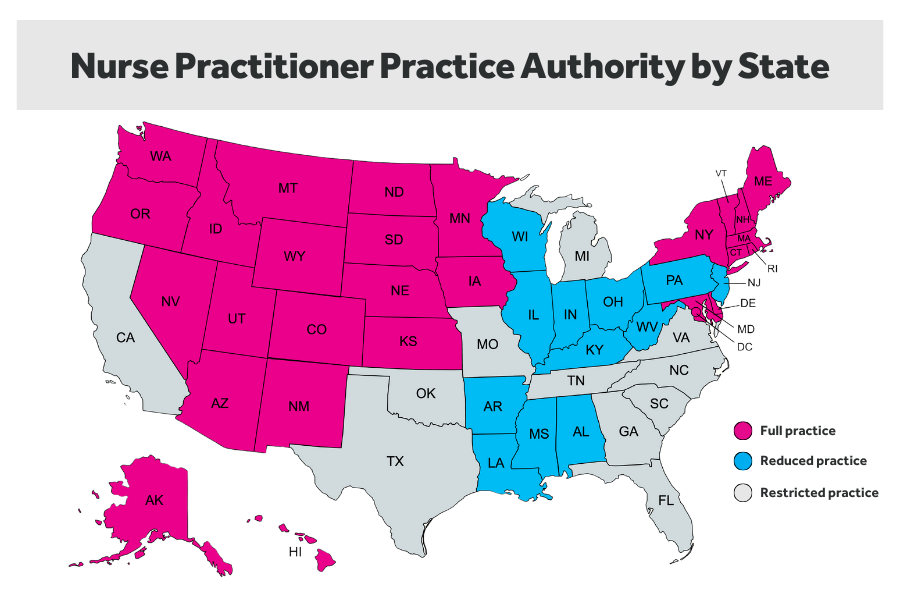
Massachusetts Nurse Practitioner Full Practice Authority is the legal framework that lets you open a clinic, write prescriptions, and make independent clinical decisions without a physician co-signer or collaborative agreement. It sounds straightforward on paper. The reality involves a few bureaucratic layers most people don't tell you about until they run into them. Under M.G.L. c. 112, Section 80G, licensed nurse practitioners in Massachusetts have full authority to evaluate patients, diagnose, order and interpret diagnostics, and prescribe medications including controlled substances. There is no mandated collaboration contract. No physician approval stamp on your charts. You are legally autonomous once you hold your RN license, your graduate NP degree from an accredited program, and your state NP license from the Board of Registration of Nursing. That last point matters more than people realize. You need your state NP license specifically, not just your RN license. The Board issues separate credentials and the paper trail between them can trip up people who assume one covers the other.
For prescribing controlled substances, you need a DEA registration in your NP name. Massachusetts doesn't require a separate state controlled substance certificate anymore, but you do need to register with the Massachusetts CareCTRS system if you're prescribingSchedule II through V medications. That's a separate portal from your nursing license application. I've seen people miss that step and then wonder why their controlled substance prescriber status shows as inactive on the EPCS system three months into practice.
Getting Credentialed Once You Have the Authority
Having full practice authority on paper is one thing. Getting hospitals and insurance networks to actually recognize your autonomy is another. Credentialing committees at many Mass general hospitals still operate under old assumptions. You will encounter them. When I opened my first outpatient practice near Framingham back in 2019, I ran into this exact problem with a local hospital system. Their bylaws required a "collaborating physician" designation for privileging even though state law didn't require it. The privileging packet kept coming back with a checkbox for a collaborative agreement that was left blank, which flagged the whole application for secondary review. That added roughly six weeks to an already slow process. The workaround was relatively simple but not obvious if you haven't dealt with this before. I had the hospital's medical staff office accept a letter from the Massachusetts Board of Registration of Nursing stating the scope of practice granted under 80G, and I attached my graduate program curriculum demonstrating the required direct clinical hours. That satisfied the committee that I wasn't operating outside standard protocols. It cut about four weeks off the pending timeframe. Not everything, but meaningful.
Get the Full Details
Insurance panels are generally easier. Most major PPOs in Massachusetts recognize NP credentials independently. The tricky ones are specialty networks and certain Medicaid managed care organizations that still ask for a collaborating physician signature on their application forms. When that happens, you write "full practice authority per M.G.L. c. 112 s. 80G" in the comments field and attach a copy of your active NP license. They usually process it without pushback after the first submission because they've seen the letter before. The first one always takes longer.
Common Pitfalls That New NPs Miss
There are a couple of things that catch people off guard. First, full practice authority in Massachusetts does not mean unrestricted pharmacy access. Some community pharmacies still hesitate when they see an NP prescribing certain high-dose anticoagulants or specialty biologic agents. They'll call the prescriber to verify. It's not a legal barrier, it's a cultural one. Having a practiced script ready explaining that you have full prescriptive authority under state law helps deflect the unnecessary calls. Second, and this is the one nobody warns you about: hospitalist groups and surgical departments sometimes push back on NP admitting privileges. They'll argue that your full practice authority doesn't extend to inpatient orders in their view. This is a hospital policy issue, not a legal one. Massachusetts law doesn't distinguish between outpatient and inpatient autonomy. But hospitals can set their own bylaws. If you're applying for inpatient admitting rights, expect questions about this. Come prepared with the statute language and be willing to meet with the medical executive committee directly rather than letting it get stuck in credentialing limbo. A third nuance involves prescriptive authority for pregnancy and delivery. While NPs in Massachusetts can prescribe during pregnancy, the Board's stance on conducting deliveries independently is more narrowly defined. If your graduate program included a neonatal or midwifery track with clinical rotation hours in labor and delivery, you'll need to document those separately when seeking hospital delivery privileges. A general family NP license doesn't automatically confer delivery privileges at most Mass hospitals. That's a separate privileging pathway.
Malpractice Insurance and Full Practice Authority
You'll need your own malpractice policy. Since you're practicing autonomously, there's no employer's policy to fall back on unless you work employed by a hospital or large health system. Individual NP malpractice policies in Massachusetts typically run between twelve and twenty-five hundred dollars annually depending on your specialty, claim history, and coverage limits. Several carriers like American Professional Agency and HLM offer NP-specific plans. Don't cheap out on the limits. A $1 million / $1 million policy is the standard expectation for most independent practice setups, and some commercial leases or facility agreements will require it anyway. Even without a collaborative agreement, Massachusetts expects NP charts to meet the same standard as physician charts. That means complete history and physical, assessment and plan, informed consent where applicable, and follow-up documentation. The Board does audit charts periodically. When they do, they're looking for consistency in your clinical decision-making, not whether a physician signed off on anything. Keep your documentation thorough from day one. It saves you from having to reconstruct events during an audit months later. Controlled substance prescriptions require the usual DEA compliance marks: your DEA number, the patient's date of birth, quantity, direction for use, and the date of the prescription. Electronic prescriptions for controlled substances must go through a certified EPCS-compliant platform. Not every EMR handles this cleanly out of the box. I learned that when a vendor update temporarily broke my EPCS routing and I couldn't send oxycodone prescriptions for three days. Verify your EMR's EPCS certification before you need it urgently.

What Full Practice Authority Doesn't Cover
This is worth being blunt about. Full practice authority in Massachusetts does not give you unlimited scope. You cannot perform certain specialized procedures without additional certification. You cannot sign death certificates unless you meet specific state requirements around attending care. You cannot authorize psychiatric holds independently in all circumstances. Some public health orders and disability certifications have their own statutory requirements that go beyond standard NP licensure. If you're considering a career shift into palliative care or addiction medicine, you'll need additional training and possibly separate certifications beyond the base NP license. The full practice authority grant covers general NP practice. It doesn't automatically expand into every subspecialty area. Plan your credentialing roadmap accordingly instead of assuming the license handles everything. The bottom line is that Massachusetts gave NPs real autonomy, and it works if you know how to navigate it. Most of the friction isn't legal, it's institutional inertia. Once you've been through the credentialing cycles a couple of times, the process becomes routine. The first time through, budget extra weeks and keep your documentation clean.



