The Thing About Massaging an Aggrieved Achilles
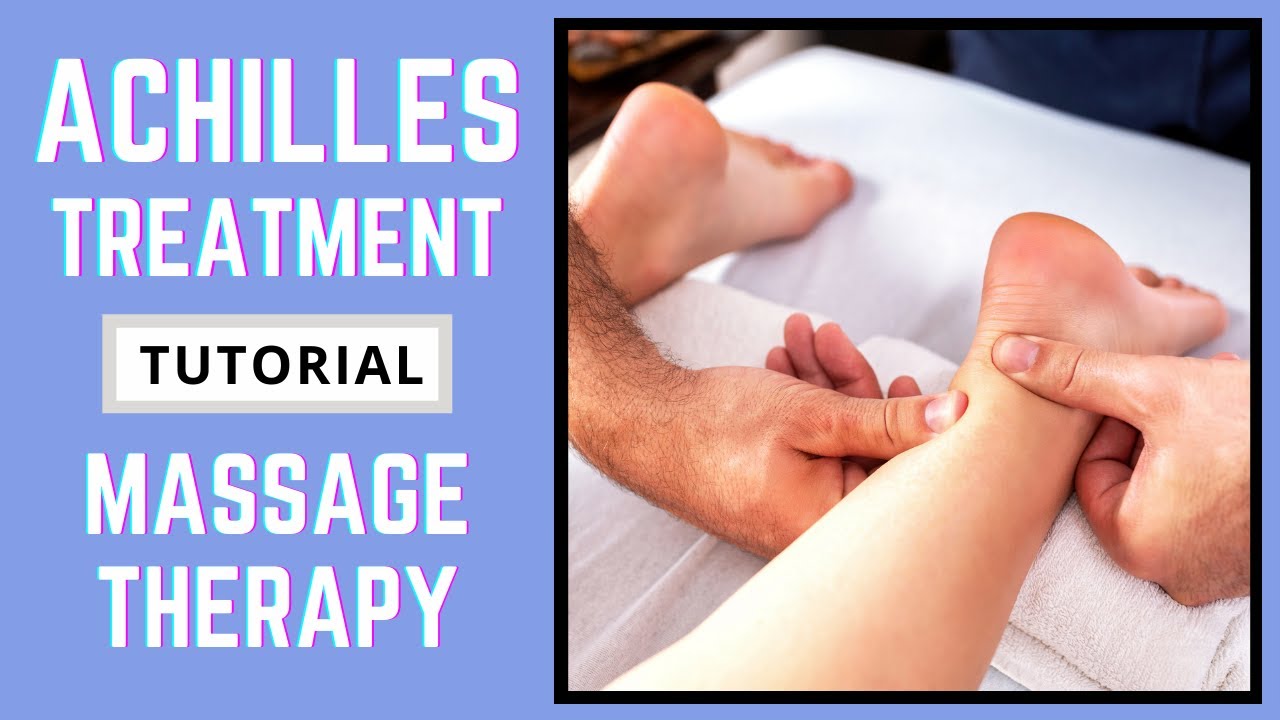
Most people think massage means rubbing the sore area until it feels better. With an Achilles tendon, that approach is usually the problem. The tendon is not muscle. It has poor blood supply, low metabolic activity, and it responds badly to blunt force. You press hard on it and you are mostly just bruising the surrounding fascia while the actual collagen fibers keep getting irritated. The difference between helpful pressure and harmful pressure is measured in millimeters. The protocol I use relies on two movements: longitudinal gliding along the tendon belly and transverse friction across the fibers at the most irritable point. The transverse work is the part that actually does something. It forces a mild, controlled inflammatory response that signals the tendon to remodel. The longitudinal strokes are just for the surrounding tissue, mostly to reduce compression from the triceps surae before you get to the tendon itself. Here is what transverse friction actually feels like when you do it right. You are not trying to create pain. You are trying to create a sensation that sits at about a six out of ten on a pain scale and feels distinctly different from the ache of the tendinopathy itself. If your client winces and tenses up, you are too deep or too focused on the wrong structure. You should be moving the skin and superficial layers across the tendon, not grinding the tendon against the bone. The motion is lateral, side to side, perpendicular to the fiber orientation. About five to seven millimeters of displacement per stroke, roughly one stroke per second, for two to three minutes on the most irritable segment.
I ran into a specific edge case last year with a runner who had mid-portion Achilles tendinopathy that had been bothering him for eleven months. The most irritable spot was not where he expected it. He kept pointing to the thickened section about four centimeters above the calcaneal insertion, which is textbook. But when I did a quiet palpation with my thumb, the real pain generator was a small localized nodule about two centimeters more proximal, near the flexor hallucis longus decussation. I had been treating the wrong segment for weeks because visual swelling is not the same thing as mechanosensitivity. The workaround was simple but easy to miss: I asked him to do slow active plantarflexion against light resistance while I scanned for the point that reproduced his exact complaint. The nodule lit up. Once I shifted the transverse friction there instead, progress accelerated noticeably within three weeks. The deeper you get into this, the more you realize that massage alone is almost never sufficient for established tendinopathy. The literature is pretty clear that loading is the primary driver of collagen realignment. What massage contributes is decreased local tissue tension, improved glide between the paratenon and the tendon proper, and a temporary reduction in pain perception that makes loading work tolerable. If your client cannot walk downstairs without favoring the leg, no amount of transverse friction will fix that. They need isometric holds first. A sustained heel hold at about seventy degrees of knee flexion, thirty seconds, four sets, twice daily, will usually drop the pain score enough that you can actually do anything meaningful with manual therapy. One counter-intuitive detail that beginners consistently miss: the Achilles has a watershed zone around the insertion where blood flow is already marginal. Aggressive deep pressure directly on the distal tendon, especially in clients over forty, can actually worsen symptoms by further compromising an already limited vascular bed. I have seen it happen. A client came in with a two-year history of insertion-level complaints. His previous therapist had been using heavy compressive strokes directly over the enthesis every session. The tendon was not getting thicker because it was healing. It was getting thicker because it was chronically traumatized. We stopped all direct pressure on the insertion entirely and worked only on the proximal gastrocnemius and soleus bellies plus the transverse friction at the most sensitive non-insertional point. The swelling dropped over four weeks.
Another nuance that matters: the line of the Achilles is not perfectly vertical. It runs slightly oblique from the lateral gastrocnemius toward the medial calcaneal tuberosity. If you are doing transverse friction and you are strictly moving medially to laterally, you are not actually crossing the majority of the fibers at the angle they are oriented. You need to angle your stroke to match the obliquity. In practice this means your hand moves across the tendon at roughly a ten to fifteen degree tilt, following the natural pull of the fibers rather than perpendicular to the limb axis. Frequency matters more than intensity. Daily or near-daily transverse friction for two to three minutes produces better outcomes than aggressive sessions twice a week. The tendon remodels on a cycle measured in days, not weeks, when you are talking about the matrix turnover at the fibrocartilaginous interface. Missing consecutive days resets the signal. I usually have clients do about ninety seconds of transverse friction at home with their own thumb, followed by an isometric hold, then ice for three minutes if there is reactive heat. There are scenarios where Massage Therapy For Achilles Tendonitis simply does not work and you need to move on. Insertional tendinopathy with visible calcification does not respond well to friction work and sometimes needs imaging confirmation before any aggressive manual intervention. A client I worked with had undiagnosed Haglund's deformity contributing to his insertion pain. Every time I applied pressure near the retroversorial space, he flared. Once we sent him for an ultrasound and identified the bony prominence, we adjusted the plan entirely. The massage work stopped being directed at the insertion and shifted to the peritendinous soft tissue only, which gave him enough relief to continue with his eccentric loading program.
Get the Full Details

Calcaneal stress fractures are another misdiagnosis trap. The pain location overlaps almost exactly with mid-portion Achilles tendinopathy. Squeeze test on the calcaneus, pain with single-leg heel raises on a hard surface, and a history of sudden load increase are the usual indicators. If manual therapy makes the pain worse rather than better after three to five sessions, stop and recommend imaging. It is not a failure of the technique. It is a failure of the diagnosis. For a practical at-home guide, the sequence is straightforward. Start with ten minutes of gentle longitudinal effleurage along the entire posterior calf, moving from the knee down toward the Achilles, always proximal to distal to encourage fluid movement. Then find the most irritable point on the tendon using the pain scale method, not the visual method. Apply transverse friction for two to three minutes at that point. Finish with an isometric heel hold. Ice only if there is significant reactive heat. Do this daily, not just when it hurts. The equipment side is worth mentioning briefly. A TheraCane or similar trigger point tool can replicate the transverse motion mechanically if you learn the right angle. But the hand gives you sensory feedback that no device can provide. You feel the tissue plane separate and recombine. You feel when you cross from paratenon to tendon to bone. Devices blur that distinction. If you use one, spend time learning the pressure gradient on your own tendon first. It takes about twenty minutes to calibrate.
Ultimately, massage is a modality, not a treatment. It modulates. It changes the local environment so that the actual repair mechanisms can operate more effectively. That is all it does. Anything framed as a cure is selling something. The tendons heal through controlled mechanical loading guided by pain responses. Massage just makes the loading less miserable while that happens.