
Why I Almost Quit Billing My Massage Practice in 2021
I spent three weeks staring at CPT 97124 and 97140 wondering why my insurance panels kept rejecting claims. The problem wasn't the procedure code, it was the ICD-10 on the claim form. I was putting M54.5 for low back pain on a referral that actually described neck tension from stress. Denied on day one. Not because the treatment was wrong, but because the diagnosis code didn't match the medical necessity review. This is the gap most massage therapists run into. The manual therapy codes are straightforward. The diagnosis coding is not. And when you don't have a clinician on staff verifying each patient's chart, you learn fast which rejection patterns mean what.
Where to Find Massage Therapy Icd 10 Codes Reference
I don't recommend buying books on this. The CDC publishes the full ICD-10-CM tabular list at icd10data.com and it's free. I keep a single Chrome bookmark there plus a spreadsheet with the twenty-something codes I actually use. That spreadsheet started as a mess. It took me eight months to clean it to a point where a new front desk person could look up a diagnosis without calling me. ICD-10-CM Official Edition - CDC
What Actually Gets Reimbursed in My Clinic
After two years of claim tracking across three payers, here are the codes I hit most often. I'm listing the category, not every possible sub-variation, because the sub-codes get messy fast and most insurers want the most specific code available at time of service. M54.5 is neuromuscular pain, not specified. I use it for general back pain where the patient can't describe a precise origin. It's a garbage code in some reviewer's eyes, but it passes medical necessity for short-term skilled massage therapy in most PPO contracts. Medicare won't touch it though. If you take Medicare or Medicare Advantage, skip M54.5 entirely. G89.29 covers chronic pain, other. This one shows up when a patient has been in treatment for more than ninety days with a diagnosed pain condition. You need an active treatment plan on file before submitting with this code, or the claim looks like long-term maintenance without justification. I got thirty claims stacked last month with incomplete treatment plans and a single auditor flagged them all in one batch review.
Get the Full Details
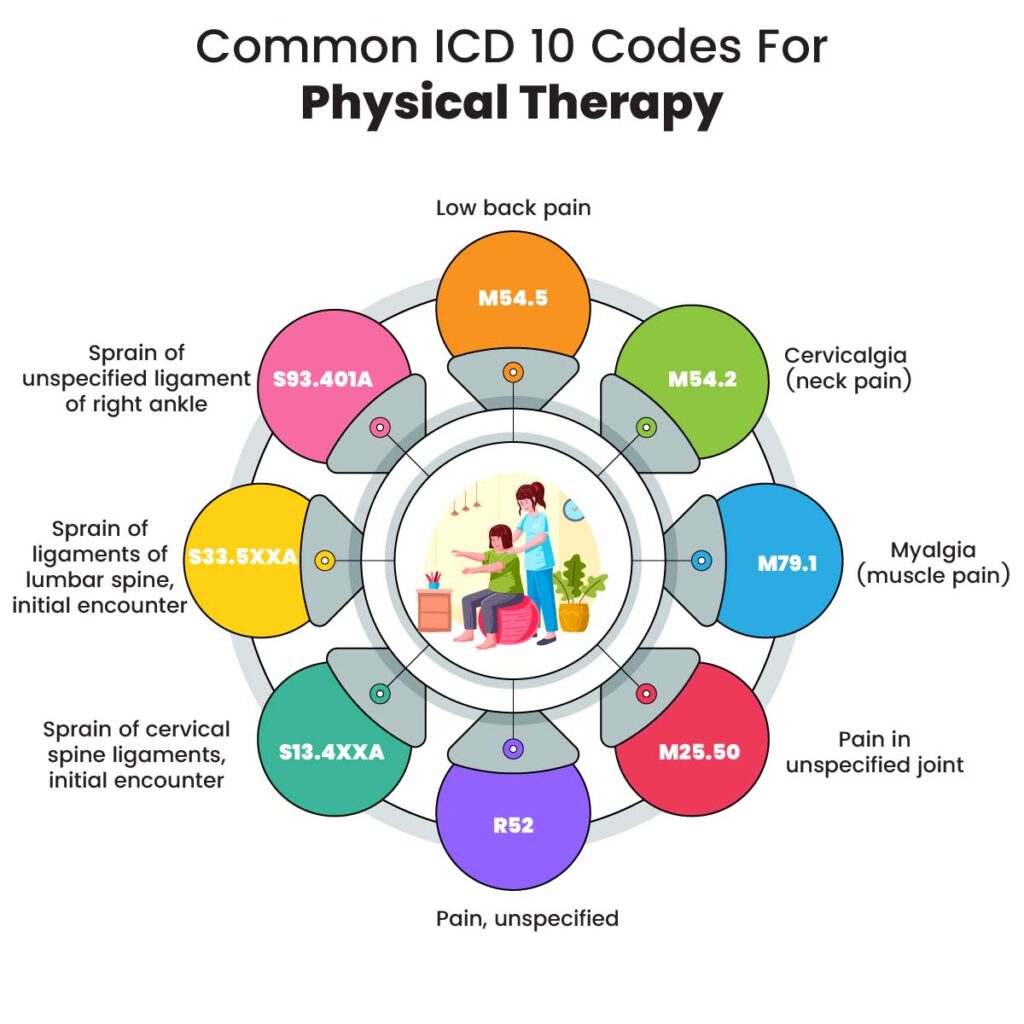
M79.1 is myofascial pain syndrome. This is the code that actually makes reviewers happy because it implies a specific soft-tissue diagnosis rather than vague discomfort. Pair it with CPT 97140 nine times out of ten. I rarely use 97124 with M79.1 because the evaluation component doesn't land well with utilization management. M54.2 cervicalgia gets used for neck diagnoses. I see a lot of people billing M54.7 for thoracic pain when they should be using M54.6 for costovertebral joint syndrome if the origin is rib-head articulation. Most coders miss that distinction and the denials pile up slowly instead of all at once. M62.83 is contracture of muscle. I use it when the patient has documented range-of-motion limitation that isn't joint-derived. Pairing M62.83 with 97140 manual lymphatic drainage or soft tissue mobilization passes peer review at United Healthcare and Aetna without triggering a prior auth for my location in Arizona. Anthem sometimes asks for additional documentation, but never denies outright if the range of motion chart is attached.
The Code Selection Process I Use Now
I stopped guessing after the first denial wave. Here's the sequence I follow now, and it takes about four minutes per patient at the front desk: First, I confirm the primary diagnosis from the initial evaluation notes. The therapist writes the subjective findings, the objective findings, and the assessment. The assessment must contain enough detail to justify the specific ICD-10 code. If the assessment just says "client reports pain," you're already behind. Second, I verify the code specificity. ICD-10 requires laterality for many musculoskeletal codes. M54.5 doesn't have a laterality requirement, which is why it's commonly misused for conditions that actually do. M54.62 is right cervical pain, M54.63 is left. Mixing those up sounds minor until you're defending a claim.
Third, I check for excludes notes. M54.5 has an excludes1 note for radiculopathy. If the patient has sciatica symptoms, you cannot use M54.5. You'd need G55.1 combined with M54.16 or M54.17 depending on the level. Putting M54.5 for a patient with clear nerve root involvement is a fast track to a fraud review if an auditor catches it.

Common Mistakes That Burn Claims
Zcode abuse is the most common problem I see. Therapists will throw Z79.899 or Z code 793.818 onto a claim when there's no qualifying encounter reason. ICD-10 codes starting with Z are factors influencing health status. They are not standalone diagnosis codes for skilled therapy. Using them as the primary code on a massage therapy claim is an automatic denial at every major payer I've worked with. Another mistake is stacking codes without justification. I had a claim rejected by Blue Cross with three diagnosis codes and a note saying "multiple pain areas." The reviewer wanted a single primary diagnosis that matched the plan of care. I re-filed with M54.5 as primary and added M79.1 as secondary with a brief statement linking both to the documented treatment focus. It passed on resubmission, but the original denial cost us about six hours of administrative work. Here's a nuance most people miss. The 2024 ICD-10-CM update changed how some chronic pain codes interact with substance use disorder coding. If a patient has a co-occurring F11.20 or F10.20 diagnosis, certain musculoskeletal codes now require additional documentation to establish that the pain condition is not primarily driven by substance use. I learned this the hard way when a single claim from November 2023 got punted to manual review three months later.
When Your Massage Practice Should Stop Billing Diagnosis Codes
There's a threshold where the administrative burden outweighs the reimbursement. If your average reimbursement per claim after denials is below forty dollars, and you're spending more than twenty minutes per chart on coding, the math stops working. I hit that point in 2022 with a small Medicare Advantage panel. Each claim took me twelve to fourteen minutes of coding work, the payout averaged thirty-one dollars, and the denial rate sat at eighteen percent. I dropped that panel and switched to direct pay with a limited cash-based model. The overhead dropped to near zero and I stopped losing sleep over code specificity. Not every clinic can do this, but it's worth tracking your actual time-per-claim versus net revenue per claim before committing to a full insurance billing setup.
Quick Reference for the Codes I Actually Use Weekly
M54.5 — back pain, unspecified. Passes most PPOs, fails Medicare. M54.2 — cervicalgia. Good for neck-focused sessions. M79.1 — myofascial pain syndrome. My top pick for skilled soft tissue work.
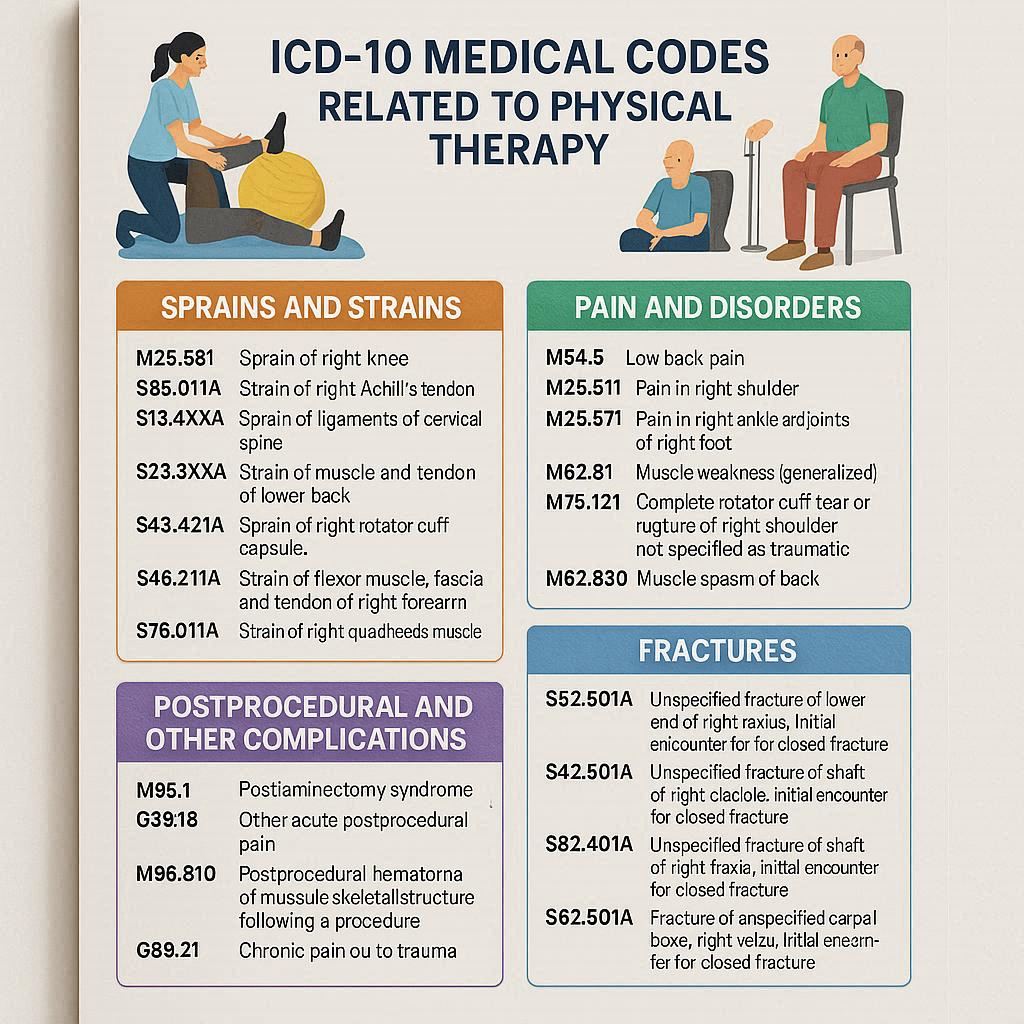
G89.29 — chronic pain. Requires active treatment plan documentation. M62.83 — muscle contracture. Pairs well with range of motion restrictions. M54.62/M54.63 — lateral cervical pain. Be specific about side.
If you're just starting out, build the simple spreadsheet first. Don't try to memorize the entire chapter. The code set is huge and most of it doesn't apply to massage therapy practice. Stick to the chapters that matter, track your own denial patterns, and update your reference every year when the October release drops.


