Getting the Standard Views Right on Mid-Trimester Ultrasound
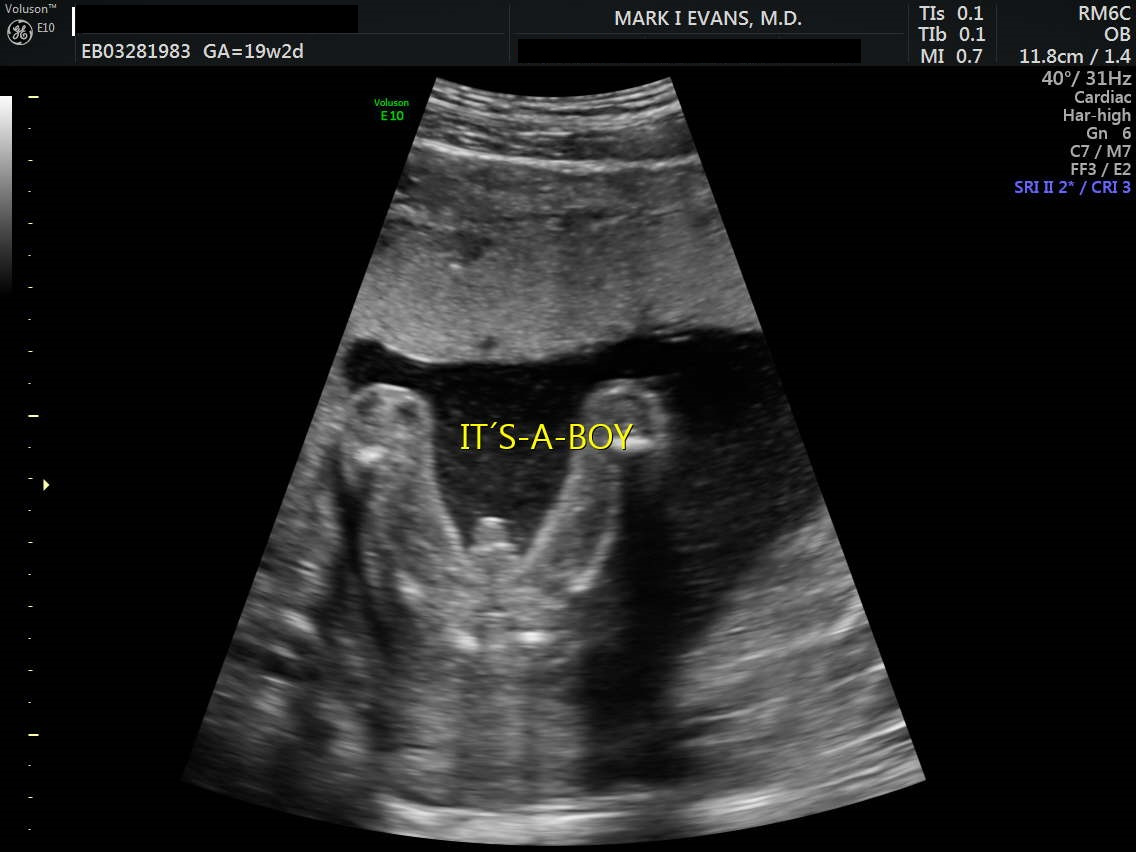
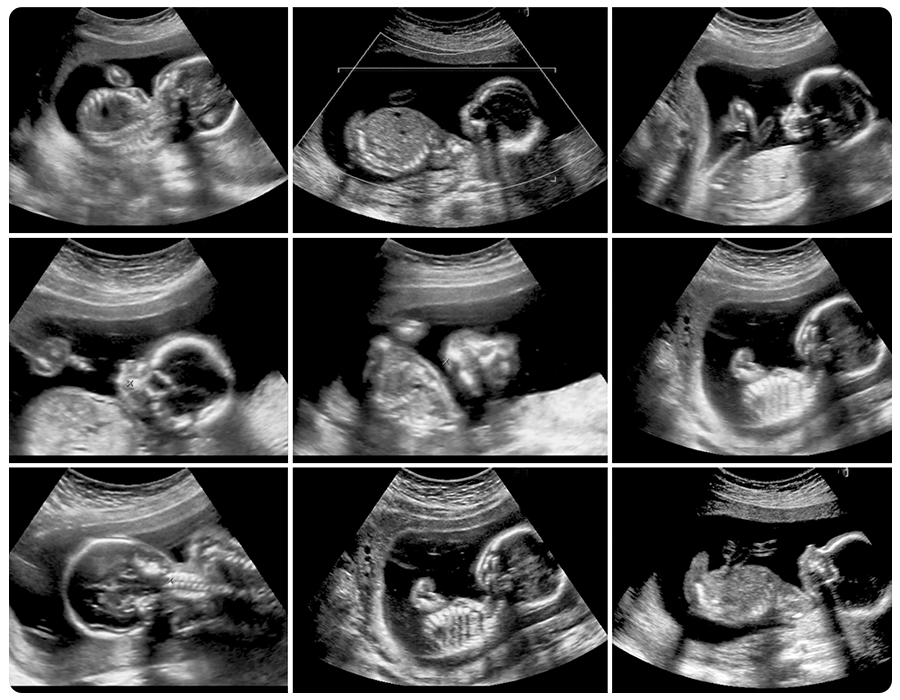
The anatomy scan between 18 and 22 weeks is where most of my weekends went. You show up, the patient is already anxious, and you've got about forty minutes before the next one rolls in. The goal is straightforward on paper: hit every plane the guidelines require and flag anything that doesn't look right. In practice, half the time the baby is facedown with their legs crossed and won't cooperate. I learned early that you don't get perfect views by pushing harder on the transducer. You get them by understanding what actually blocks the image and working around it. The most common problem isn't poor machine settings. It's the assumption that a standard sagittal view of the spine means you've documented the spine. You haven't. You still need the axial view at the level of the lateral ventricles, the transverse view of the heart at the four-chamber plane, and the sagittal profile of the face. Miss any of those and the scan is incomplete, regardless of how clean the rest of it looks.
What a Maternal Fetal Medicine Anatomy Scan Actually Covers
The standard MFM anatomy scan looks at six major systems: the brain, the face, the spine, the heart, the abdomen, and the urinary tract. That's the baseline. Anything beyond that is added based on indication or whatever you catch incidentally. The brain assessment alone takes up a significant chunk of time because you need to confirm the falx is midline, measure the lateral ventricles, visualize the choroid plexus, and check the cisterna magna. All of it from multiple angles. The heart is where people tend to rush. Four-chamber view, outflow tracts, three-vessel view, and the arch itself. Each one requires a different plane and different probe orientation. The left and right ventricular outflow tracts cross each other in a normal heart. If they run parallel instead, that's a red flag for congenital heart disease. You won't catch that unless you actually take the time to rotate the probe and find the crossing point. For measuring tools, you'll want a system that supports calipers, preset measurement templates, and ideally some automated fetal biometry modules. Most modern machines from GE, Philips, and Samsung have these built in. The specific platform matters less than making sure you know which preset corresponds to which measurement before the patient gets on the table.
The Practical Workflow I Actually Use
Start with the uterus and adnexa before you even look at the fetus. Confirm the number of gestational sacs, check placental location, and note any obvious masses. Then move to the fetus. I begin with a sagittal view of the head and face to establish lie and presentation. From there I go to the spine in longitudinal and transverse planes, checking for continuity from the cervical region down to the sacrum. Every vertebra needs to be visible and aligned. The abdominal circumference is measured at the level of the stomach bubble and the intrahepatic portion of the umbilical vein. The probe needs to be tilted slightly to catch that J-shaped curve of the vein as it enters the liver. Get the angle wrong and your measurement is off by several millimeters, which throws off the estimated gestational age and weight calculation. I've seen this happen repeatedly when sonographers measure from a slightly oblique plane and don't realize it until they're reviewing the images afterward. For the kidneys and bladder, you're looking for symmetry, normal echogenicity, and a distended bladder. A solitary kidney or bilateral renal dysplasia changes the entire risk profile. The umbilical cord insertion point matters too. Velamentous insertion and marginal insertion aren't emergencies on their own, but they carry real risks for growth restriction and bleeding during labor. I make it a habit to trace the cord from the placental insertion all the way to the fetal abdomen.
Get the Full Details

A Specific Problem I Ran Into and How I Handled It
Last year I had a patient at 20 weeks where the fetal position was completely uncooperative. Face down, back against the anterior uterine wall, legs flexed. The standard transabdominal approach was giving me nothing but shadowing from the maternal bowel gas. I spent twenty minutes trying to get a four-chamber heart view through various angles and kept hitting the same wall of acoustic interference. The workaround was switching to a transvaginal approach for the cardiac views. Yes, it's less comfortable for the patient, but at 20 weeks the cervix is accessible and the transducer frequency gives you much better resolution for small structures. The four-chamber view came into focus within two minutes. I then used the same approach for the outflow tracts. The whole additional assessment took maybe twelve minutes total. The patient left knowing we'd actually seen what we needed to see instead of scheduling a vague "follow-up in two weeks" appointment that nobody wanted. This is the kind of thing that doesn't get emphasized enough in training. Everyone learns the transabdominal route. Fewer people are comfortable with transvaginal fetal imaging during the anatomy scan, but it's a legitimate tool when the window closes.
Counter-Intuitive Things Most People Miss
The nuchal fold measurement at the posterior fetal neck is one of those things that seems minor but carries significant weight. A nuchal fold thicker than 6mm at 15 to 22 weeks is a soft marker for trisomy 21. The trick is that you have to measure the fold itself, not the skin line. The probe needs to be in a true axial plane at the level of the cerebellum and cisterna magna. Tilt the probe even slightly and you'll either underestimate or overestimate the measurement. I've seen both happen in real clinical practice. Another thing that surprises people: the fetal stomach should be visible on every routine scan, but its absence doesn't automatically mean esophageal atresia. The baby could simply not have swallowed amniotic fluid in the thirty minutes leading up to the scan. I've noted empty stomachs on multiple occasions, followed up with a second look an hour later, and found it filled normally. Patience matters more than you'd expect here. The midline cerebral structures are equally tricky. The cavum septum pellucidum should be visible as a box-shaped structure anterior to the third ventricle. When it's absent, that can indicate holoprosencephaly or septo-optic dysplasia. But the CSP is also dependent on the exact plane of section. Rotate the probe two or three degrees and it disappears from view even in a normal brain. Confirm it's truly absent by checking at least three adjacent planes before you document it as a finding.
Where This Approach Falls Short
The anatomy scan has real limitations that nobody likes to talk about. It cannot rule out all congenital anomalies. Certain conditions like neural tube defects at the most severe end are detectable, but milder forms like spina bifida occulta frequently go unseen. Cardiac rhythm abnormalities are essentially invisible on a standard anatomical survey. Hearing and vision deficits, metabolic disorders, and most genetic syndromes leave no structural trace at this gestational age. Maternal body habitus is another hard limit. In patients with a higher BMI, image quality degrades significantly regardless of operator skill or machine quality. I've had scans where even the fetal heartbeat was borderline difficult to confirm with certainty on the transabdominal approach. The only honest recommendation in those cases is a transvaginal follow-up or referral to a center with higher-frequency probes and more experience in difficult acoustic windows. Operator dependency is the elephant in the room. Two sonographers can perform identical scans on the same patient and produce genuinely different reports. This isn't a flaw in the technology. It's a flaw in human perception and training consistency. The best mitigations are structured reporting checklists, regular competency review, and a willingness to refer borderline cases to an MFM specialist rather than guessing.
What I Recommend for Documentation and Reporting
Write the report while the images are still fresh. Don't wait until the end of the day. The difference between a well-documented scan and a vague one often comes down to whether you captured the actual measurements in the moment or tried to reconstruct them from memory later. I keep a standard template with checkboxes for each required view. It takes about ninety seconds to fill out during the scan and saves me fifteen minutes of charting afterward. If you're looking for reference materials or protocols, the ISUOG guidelines for the performed scan are the closest thing to a standard. They're freely available online and get updated periodically. The AIUM practice parameters are also useful. Neither is perfect, but they're better than winging it. The bottom line is that the Maternal Fetal Medicine Anatomy Scan is a skill built through repetition and pattern recognition. You will miss things. You will have days where the baby won't cooperate and the images look terrible. The goal isn't perfection. It's consistent, thorough documentation of what you can see, clear acknowledgment of what you couldn't, and appropriate referral when something falls outside your comfort zone.