How the Method Actually Works in Practice
The core idea is simpler than most people think. You have a person with mechanical low back pain, and you need to find out which direction their spine prefers to move. You start with extension. Prone on elbows, lying flat on your stomach, propped up on hands. Most people with disc-related issues feel relief. Some feel worse. The ones who feel worse usually have a different problem entirely. I spent years doing this, and the pattern is boringly consistent. About 70 percent of mechanical low back cases respond to repeated extension. The remaining 30 percent? They'll either not respond at all, or they'll centralize pain with flexion instead. There is no magic here. It is mostly observation and patience. The technique breaks down into three phases: assessment, treatment, and self-management. During assessment you perform a series of repeated movements to find a directional preference. Treatment involves loading that direction repeatedly until symptoms change. Self-management means the patient does a maintenance routine at home. That third part is where most people fail. Not because the method is bad, but because compliance drops off after the first week of improvement.
Learning the Mckenzie Method Mckenzie Exercises
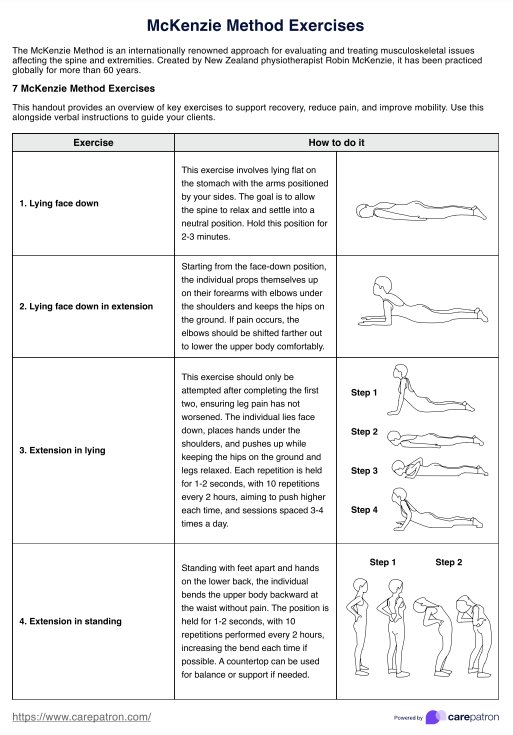
You do not need a certification to try the basic McKenzie exercises on yourself, though I would strongly recommend seeing a trained clinician if you have not been properly assessed. The standard exercise sequence starts with the patient lying prone, then progresses through three stages: Stage 1: Prone on elbows. Lie face down, forearms on the floor, elbows under shoulders. Hold for 2 to 3 minutes. Breathe normally. This applies a gentle load through the lumbar spine in extension. If this reduces or centralizes pain, you have found your directional preference. If it increases pain, stop and move to stage 2 or try a different direction. Stage 2: Prone on hands (press-up). From the prone position, place hands under shoulders and slowly straighten arms to lift the upper body while keeping hips on the floor. Return to starting position. Repeat 10 times. This is the most commonly prescribed movement in the McKenzie system. It loads the lumbar spine more aggressively than stage 1.
Stage 3: Standing extension. Hands on hips, fingers pointing toward the belly button. Lean back slowly, then return to upright. Repeat 10 times. This is useful for patients who cannot tolerate the prone position. Each stage should be held for 2 to 3 minutes per position, or repeated for sets of 10, two to four times daily. The goal is symptom reduction or centralization of pain. Pain moving from the leg toward the lower back is a good sign. Pain moving further down the leg is not. I had a patient once who could not tolerate any lumbar extension past stage 1. She felt sharp lateral pain in her right SI region within 30 seconds. She also had a history of sacroiliac joint dysfunction that had never been formally assessed. The workaround was straightforward: I stopped testing lumbar extension and started testing lumbar side-gliding movements instead. She responded well to left-sided side-glides, which turned out to be the correct directional preference for her particular pattern. The McKenzie system allows for this kind of adjustment, but most people only learn the extension protocol and give up when it does not work for them.
Get the Full Details

Another thing nobody tells you about the McKenzie approach is that the number of repetitions matters less than the quality of the response. Doing 50 press-ups in one session will not help more than doing 10 well-spaced sets throughout the day. The spine responds to repeated, moderate loading, not to a single aggressive bout of exercise. I have seen too many people treat it like a workout and end up worse on day two. The method is not designed for acute inflammatory conditions, fractures, tumors, or cauda equina syndrome. It is not even particularly effective for spinal stenosis, where flexion-based relief is typically needed rather than extension. If your pain is constant, worsening regardless of position, and accompanied by systemic symptoms like fever or unexplained weight loss, this is not the method for you. See a doctor first. For discogenic pain with radiculopathy, the evidence is mixed but leans positive. A 2019 systematic review found moderate-quality evidence supporting MDQ-ME for short-term pain reduction. Long-term outcomes are less clear. That is worth noting before you commit months to a protocol with uncertain durability.
Find a certified practitioner if you can. The MDQ-ME training runs several days and covers assessment patterns, staging progression, and special population considerations. Without that training, you are essentially guessing which direction your spine likes. That guess might be right. It might also send you in the wrong direction for weeks.