How I Actually Use the McKenzie Method in My Clinic
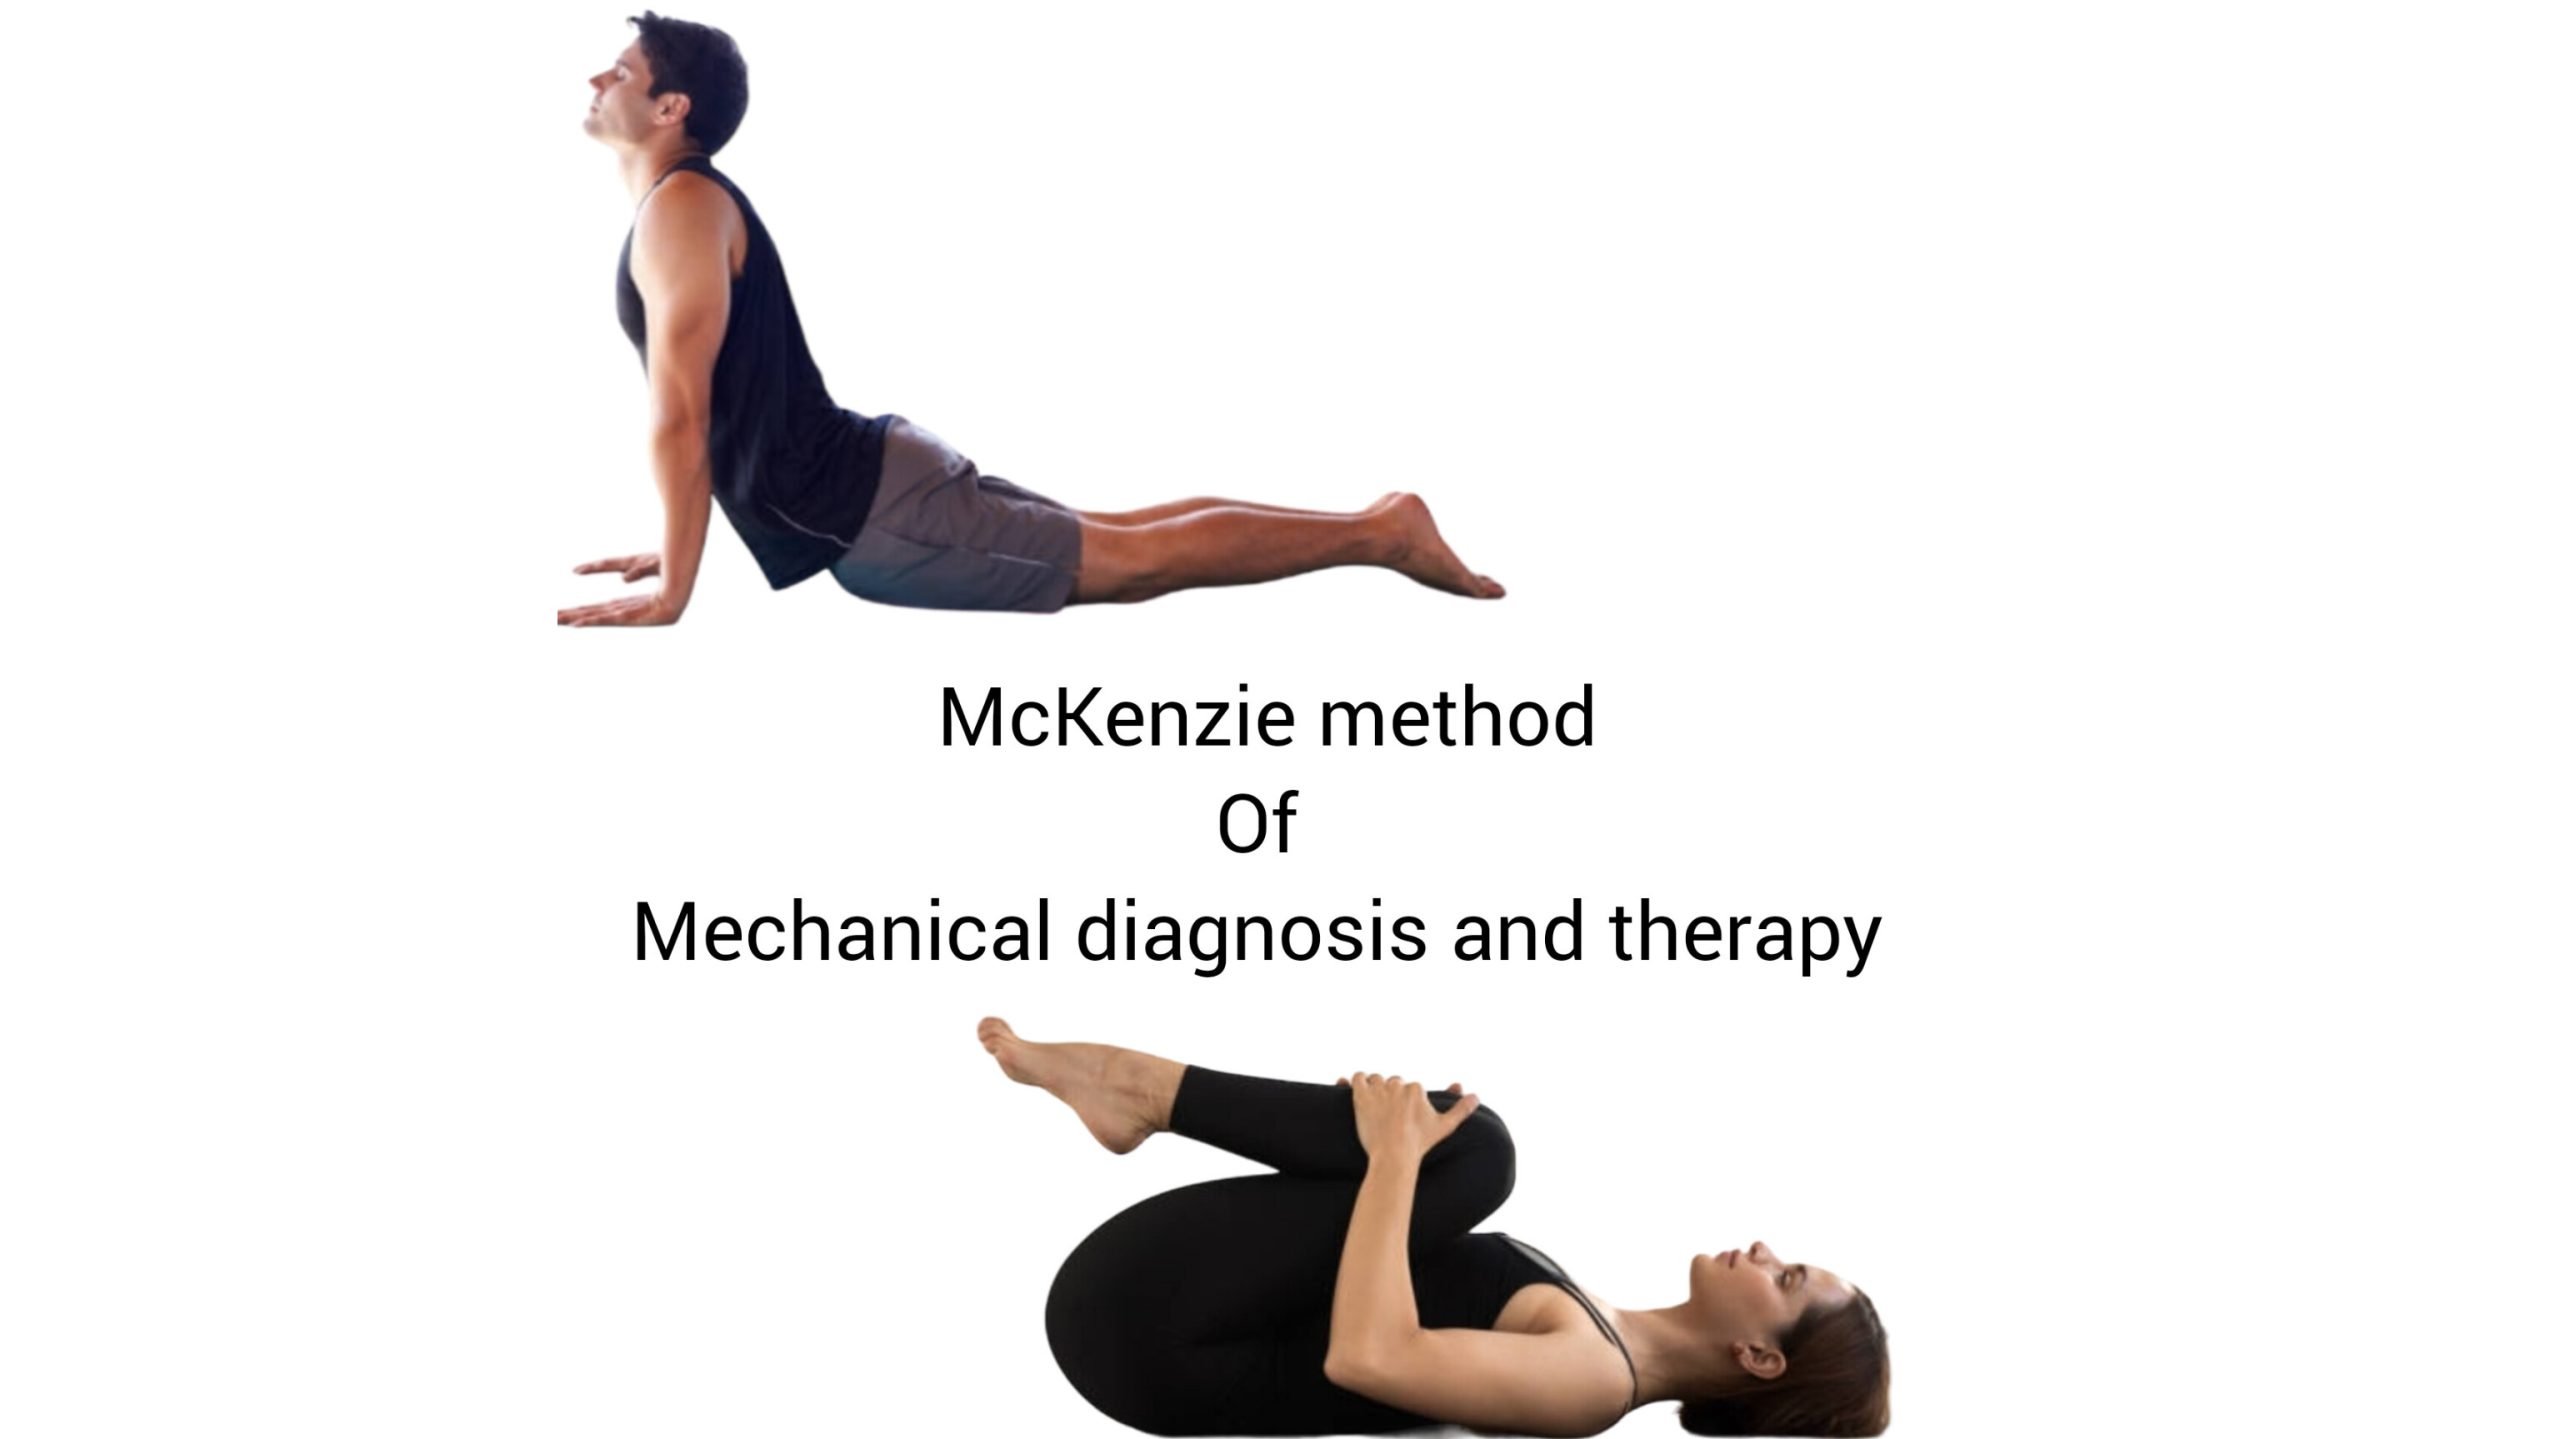
Most people come to me expecting me to wave a wand and fix their back in one session. I tell them upfront that the Mckenzie Method Of Mechanical Diagnosis And Therapy is more like learning to drive than getting a repair. You do the work, I just show you which pedal does what. The McKenzie Method, formally called Mechanical Diagnosis and Therapy or MDT, was developed by Philip McKenzie in New Zealand during the 1950s. He was a chiropodist who noticed something interesting while treating patients with lower limb pain. The patterns of movement that made symptoms worse or better kept showing up in predictable ways. He spent the next forty years turning those observations into a structured assessment and treatment system. At its core, the method is built on three pillars: assessment, classification, and treatment. The assessment phase is where most therapists rush through, and rushing through it is exactly why the method fails for a lot of people. You are not just asking "does this hurt?" You are mapping directionality. Which movements produce centralization? Which produce peripheralization? Which are impossible without symptom change? These questions matter more than the pain score itself.
The classification system divides patients into four main categories: derangement syndrome, dysfunction syndrome, postural syndrome, and variation. Derangement is by far the most common finding. It means the joint or tissue has shifted into a position that creates a mechanical problem, and that problem can often be reduced through specific repeated movements. Dysfunction is a contracture or adaptive shortening that limits range. Postural syndrome is pain produced purely by sustained positions, not by movement itself. Variation is when the patient falls outside the normal diagnostic categories entirely.
How the Assessment Actually Works
I start every new patient with a history interview, but I keep it tight. Three minutes max on the story. Then I move straight to observation and movement testing. The first thing I check is whether symptoms are central or peripheral. Central means the pain is located in the trunk or near the spine. Peripheral means it has traveled into the limbs. This distinction alone tells me more than most imaging studies. Next comes the directional preference test. I ask the patient to perform repeated movements in different directions. Extension, flexion, lateral movements. I watch for two things simultaneously: does the symptom pattern change, and does it change in a predictable way? If extension reduces lumbar pain and pulls it back toward the spine, that is centralization. That is a positive response. If extension makes the pain travel further down the leg, that is peripheralization. That is a negative response and I stop immediately. The key insight that beginners miss is that the number of tests matters less than the quality of each test. I might do twelve tests in twenty minutes, or I might need fifty in an hour. What matters is whether each test produces a clear, interpretable result. Ambiguous results mean I have not found the right position or the right angle yet. I do not force a classification. I go back to basics.
Get the Full Details

A Real Problem I Encountered
Two years ago I had a patient with chronic lumbar radiculopathy. Standard McKenzie assessment showed extension producing centralization. I gave her the standard extension protocol. Three sets of ten, twice daily. She came back three days later saying the pain in her leg had gotten worse, not better. The original assessment had been misleading because I had not checked for sustained positioning. Extension worked in the clinic but failed at home because she was sitting for six hours a day between tests. The workaround was straightforward but not obvious. I added a positioning protocol. She had to avoid flexion beyond sixty degrees for the first forty-eight hours. Then I reintroduced extension in short bursts with positional breaks every twenty minutes. The symptom pattern stabilized after seven days. She completed the full protocol in three weeks instead of the original four-month estimate. The lesson was simple: assessment is not a one-time event. It is a continuous process that includes real-world positioning.
Common Pitfalls That Beginners Fall Into
The biggest mistake I see is treating the McKenzie Method as a treatment protocol rather than a diagnostic framework. You diagnose first, then you treat. Skipping diagnosis means you are guessing. Guessing is expensive in terms of time and patient trust. Another pitfall is over-relying on the initial assessment. I have seen therapists do one comprehensive test session and then never revisit the classification. Symptoms change. Positions shift. What worked on day one may not work on day ten. I reassess every session. The reassessment takes five minutes. Five minutes is nothing compared to the alternative.
What the Method Cannot Do
I need to be blunt about the limitations. The McKenzie Method fails completely for patients with structural pathology. Fractures, tumors, infections, cauda equina syndrome. These are not McKenzie cases. These are referral cases. If a patient has red flag symptoms, you do not test directional preference. You refer immediately. The method also struggles with patients who have generalized pain syndromes. Fibromyalgia, chronic widespread pain, central sensitization. These patients do not respond to mechanical classification because the pain is not mechanical. The McKenzie Method is designed for mechanical problems. Using it for non-mechanical problems is like using a screwdriver to hammer a nail. It might work once or twice. It will not work consistently. For patients with postural syndrome, the method is less effective because the pain is position-dependent, not movement-dependent. Sitting for twenty minutes causes pain. Standing for twenty minutes does not. The solution is positioning advice, not exercise. Exercise is unnecessary and sometimes counterproductive in these cases.

Advanced Nuances
Here is something most textbooks do not mention: the concept of "unloading" is more important than "loading." Most therapists focus on the movement that reduces symptoms. They should focus on the position that prevents symptom recurrence. Unloading means removing the mechanical stress. Loading means applying the corrective stress. Both matter, but unloading usually comes first. Another nuance is the difference between "centralization" and "resolution." Centralization means the symptom moves toward the spine. Resolution means the symptom disappears entirely. Most patients achieve centralization before resolution. Some never achieve resolution. That does not mean the treatment has failed. It means the patient has achieved the maximum mechanical improvement possible. Further improvement requires addressing other factors: positioning, activity modification, psychological factors.
When to Use an Alternative
If the McKenzie Method is not producing results after three sessions, I switch approaches. I do not persist with a failing protocol. Persisting is not dedication. It is waste. For patients with dysfunction syndrome, I combine McKenzie with stretching and strengthening. The directional preference test still matters, but the treatment is more comprehensive. For patients with postural syndrome, I focus on ergonomics and positioning. Exercise is secondary. For patients with variation, I refer to a specialist. The McKenzie Method is not a universal solution. It is a tool for a specific type of problem. The method works best for acute derangement syndrome. Most patients respond within one to three sessions. The average treatment duration is two weeks. Some patients need four weeks. Some need eight. I do not promise a timeline. I provide an estimate based on the classification. Estimates are useful. Promises are not.
The Practical Workflow
I start with a ten-minute history interview. I ask about the onset, the pattern, the aggravating factors, the relieving factors. I listen for two things: does the story match the mechanics? Does the patient understand their own body? If the story does not match the mechanics, I go back to the assessment. I do not force a fit. Then I do the movement testing. Ten to fifteen minutes. I check directionality, I check positionality, I check repeatability. I look for centralization and peripheralization. I record the results. The results are not just data. They are a map. The map guides the treatment. Next comes the treatment. Fifty to seventy percent of patients with derangement syndrome respond to extension-based exercises. Twenty percent respond to flexion-based exercises. Ten percent respond to lateral exercises. Ten percent do not respond to any directional preference. For the last ten percent, I reassess. I do not assume the initial classification was correct. I go back to the basics.
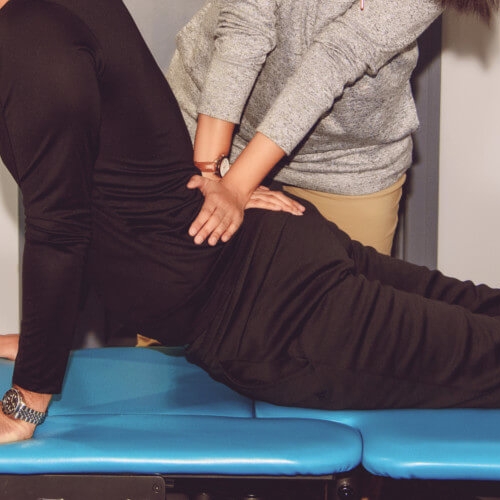
The patient education component is critical. Most therapists spend five minutes explaining the exercise. They should spend twenty minutes. The patient needs to understand why they are doing the exercise, not just how. Understanding leads to compliance. Compliance leads to outcomes. Outcomes lead to trust.
What I Wish Beginners Knew
First, the McKenzie Method is not a brand. It is a framework. You can use it without buying the certification. You can misuse it with the certification. The framework matters more than the credential. Credential is paper. Framework is practice. Second, the method requires patience. Most patients want a quick fix. Quick fixes are rare. Most patients need three to six sessions to achieve centralization. Some need twelve. Some need twenty-four. I do not rush. Rushing produces errors. Errors produce failures. Failures produce distrust. Third, the method is not standalone. I combine it with other approaches when appropriate. Stretching, strengthening, education, positioning. The McKenzie Method is a tool, not a religion. Tools are used. Religions are followed. I use tools.
The McKenzie Method of Mechanical Diagnosis and Therapy is a practical, evidence-based approach to assessing and treating mechanical pain syndromes. It works best for derangement syndrome. It fails for structural pathology. It struggles with postural and generalized pain. The key is knowing when to use it, when to modify it, and when to move on. The method is a starting point, not an ending point. Starting points matter. Ending points matter more.