Getting the MDS Assessment Process to Actually Work for You
Most people look at the MDS Assessment Cheat Sheet expecting it to be some magic shortcut that turns a 40-hour process into five minutes. That is not how it works. A cheat sheet is useful when you already understand the underlying mechanics and just need a reference when you are juggling multiple assessment windows across a busy floor. I have spent years watching nurses and coordinators struggle with MDS timing, so I built something practical for people who just need to get it right without re-reading the entire RAI manual every single time.
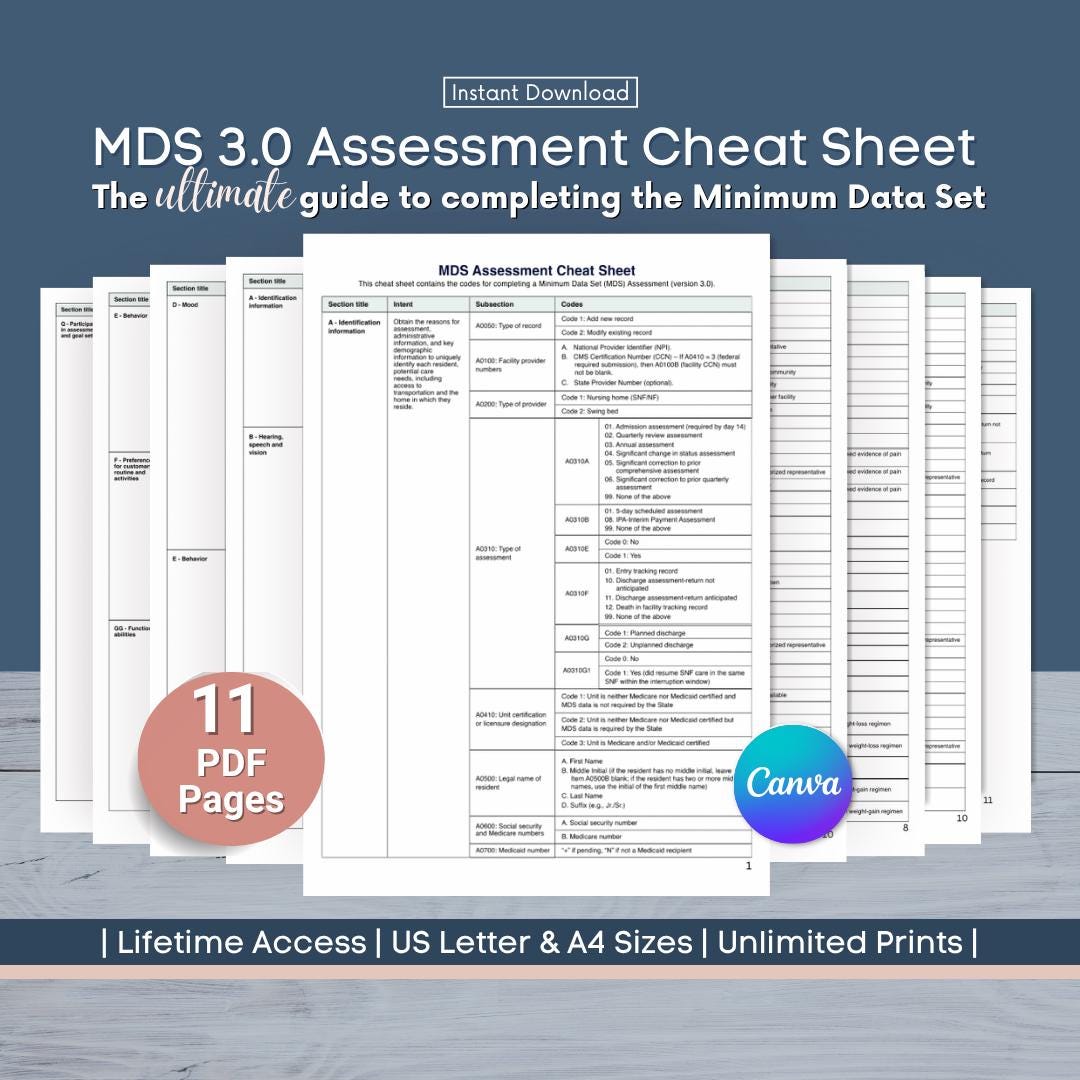
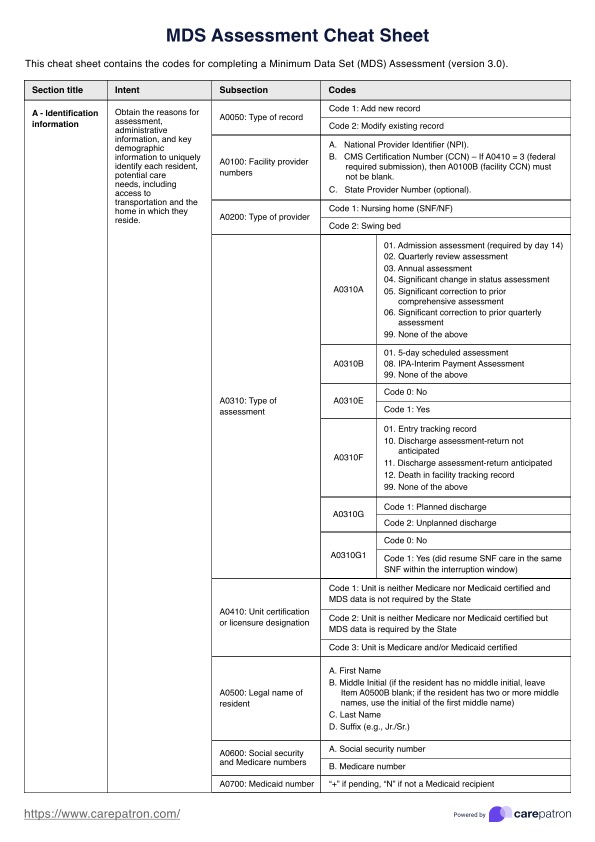
What the Mds Assessment Cheat Sheet Actually Covers
This is not a full curriculum. It is a focused quick reference that pulls out the decision points people consistently mess up. The main sections break down by assessment type, the trigger criteria for each, and the typical window windows. You will find it most valuable for the admission window, the 7-day comprehensive, the monthly assessment, and the major change assessment. The most common mistake I see people make is confusing the trigger event dates. A resident falls on the 14th, they start calculating the assessment window from the 15th, but the trigger actually resets the clock differently depending on whether it is a voluntary discharge or a clinical change. Getting that wrong pushes your whole timeline and can result in a down-coded or missed assessment.
How to Use This Without Making It Worse
Print the section for your current focus area rather than keeping the full sheet at your desk. When you are doing 20 assessments in a week, having all of it open at once actually slows you down because your eye jumps to the wrong reference point. I keep three separate prints, color coded by assessment type, sitting in different work areas. Here is a specific problem I ran into recently that most guides do not mention. A resident was admitted on a Wednesday with a diagnosis of pneumonia and was on oxygen. The admission assessment window opened, but the resident was also scheduled for a discharge to acute care on Friday. The question became whether this qualified as a short stay and what the scoring implications were. The cheat sheet had the general rule, but the actual workaround required checking the SNF benefit days against the length of stay calculation and confirming whether the resident had already exceeded their benefit. I resolved it by cross referencing the admission date with the projected discharge and running a quick benefit day check before locking in the M3 goals. Took about twenty minutes instead of two hours of back and forth with the billing team.
Get the Full Details

Common Pitfalls That the Cheat Sheet Does Not Fully Address
Even with a solid reference tool, there are blind spots. The first one is the assumption that every assessment follows the same 60 day cycle. Some facilities use a rolling window approach while others anchor to the calendar month. If your facility does not have a clear policy documented, you will end up with duplicate or overlapping assessments, which triggers a review flag during state surveys. Another issue is the interdisciplinary team coordination. The MDS requires input from nursing, therapy, medical, and sometimes dietary. The cheat sheet gives you the forms, but it does not solve the workflow problem of getting all those signatures before the window closes. I solved this by implementing a two day soft close policy where preliminary data collection happens forty eight hours before the official window end. It adds a small administrative step but prevents the desperate scramble that causes errors. If you need the resource itself, the Mds Assessment Cheat Sheet is available through the standard healthcare documentation portals. It updates with each CMS revision cycle, so make sure you are pulling the version that matches your current assessment period. Using an outdated sheet will cost you more time than it saves, especially after the 2024 updates to the cognitive and functional domains.
When This Approach Fails Completely
There are situations where a cheat sheet simply does not help. Complex cases involving multiple comorbidities, psychiatric residents, or those with advanced directives that conflict with standard assessment protocols require manual review against the full RAI manual. The cheat sheet is a decision support tool, not a replacement for reading the actual guidance when the case does not fit a standard pattern. For those edge cases, the better approach is to consult directly with your clinical consultant or the state survey agency when the documentation is unclear. I have seen facilities waste weeks trying to force a non standard resident into a standard assessment template, and the result is always an audit finding. Sometimes the right answer is to request a variance or document the clinical rationale separately rather than trying to fit it into the default fields. The cheat sheet works best when you use it alongside your facility\'s specific policies and the most current CMS guidance. Treat it as a starting point, not the final word on any complex assessment decision.