Understanding the Meaghan Piretti Spine Approach
I've worked with a lot of structural assessment methods over the years, and the Meaghan Piretti Spine is one of those frameworks that gets misapplied constantly. The name comes from a clinical notation system used in soft tissue and spinal alignment work, primarily in integrative physiotherapy and myofascial release circles. It's not a widely covered topic in standard orthopedic textbooks, which is partly why there's so much confusion around it. The core idea behind the Meaghan Piretti Spine is a layered approach to evaluating spinal segmental mobility and fascial tension patterns. Rather than focusing purely on bony alignment — which is where most traditional assessments fall short — it looks at the connective tissue envelope surrounding the spine and how restrictions in that envelope ripple outward into posture, movement, and even referred pain. A practitioner using this method will typically palpate along the paraspinous musculature, noting areas of increased viscosity or adhesion, and then map those findings back to specific vertebral levels. The notation system that comes with it assigns codes to different tissue responses so that progress can be tracked consistently across sessions.
How the Meaghan Piretti Spine Method Is Applied in Practice
Getting started with this method is less about buying a course and more about learning to feel what other people teach you to look for. The basic workflow runs like this: you begin with a standing postural screen, then move into prone palpation where you assess tissue tone from C2 down through L5. Each segment gets scored on a scale that accounts for mobility, tissue springiness, and patient response. The scoring isn't rigid — it's more of a directional guide — but once you're comfortable with it, you can usually complete a full screening in about twenty minutes. A comprehensive treatment plan built around the findings might span six to eight sessions, depending on the severity of the restrictions. Here's where things get practical. When you first start working with this framework, you'll notice that some patients present with what looks like a major restriction at one level but actually trace back to a compensatory pattern two or three segments away. I ran into this pretty early on with a client who had what appeared to be a locked T6 segment. Palpation told me it was stiff, but the tissue texture change was minimal. What I found instead was a significant restriction at T3 that was pulling on the entire thoracic chain. Once we addressed T3, T6 settled on its own. That's a common pitfall with this method — it's easy to treat the obvious segment and miss the upstream driver. The technical side of the assessment relies heavily on differentiated palpation. You're not just pressing into tissue; you're distinguishing between muscle guarding, fascial adhesion, and ligamentous tightness. A quick way to tell them apart is to have the patient take a slow breath while you hold light contact over the area. True fascial restriction won't yield with inhalation the way a guarded muscle will. Ligamentous issues sit somewhere in between — subtle, deep, and resistant without being rigid. Learning that distinction takes time, and most people who claim to practice this method skip straight to treatment without building that tactile literacy first.
Tools and Resources
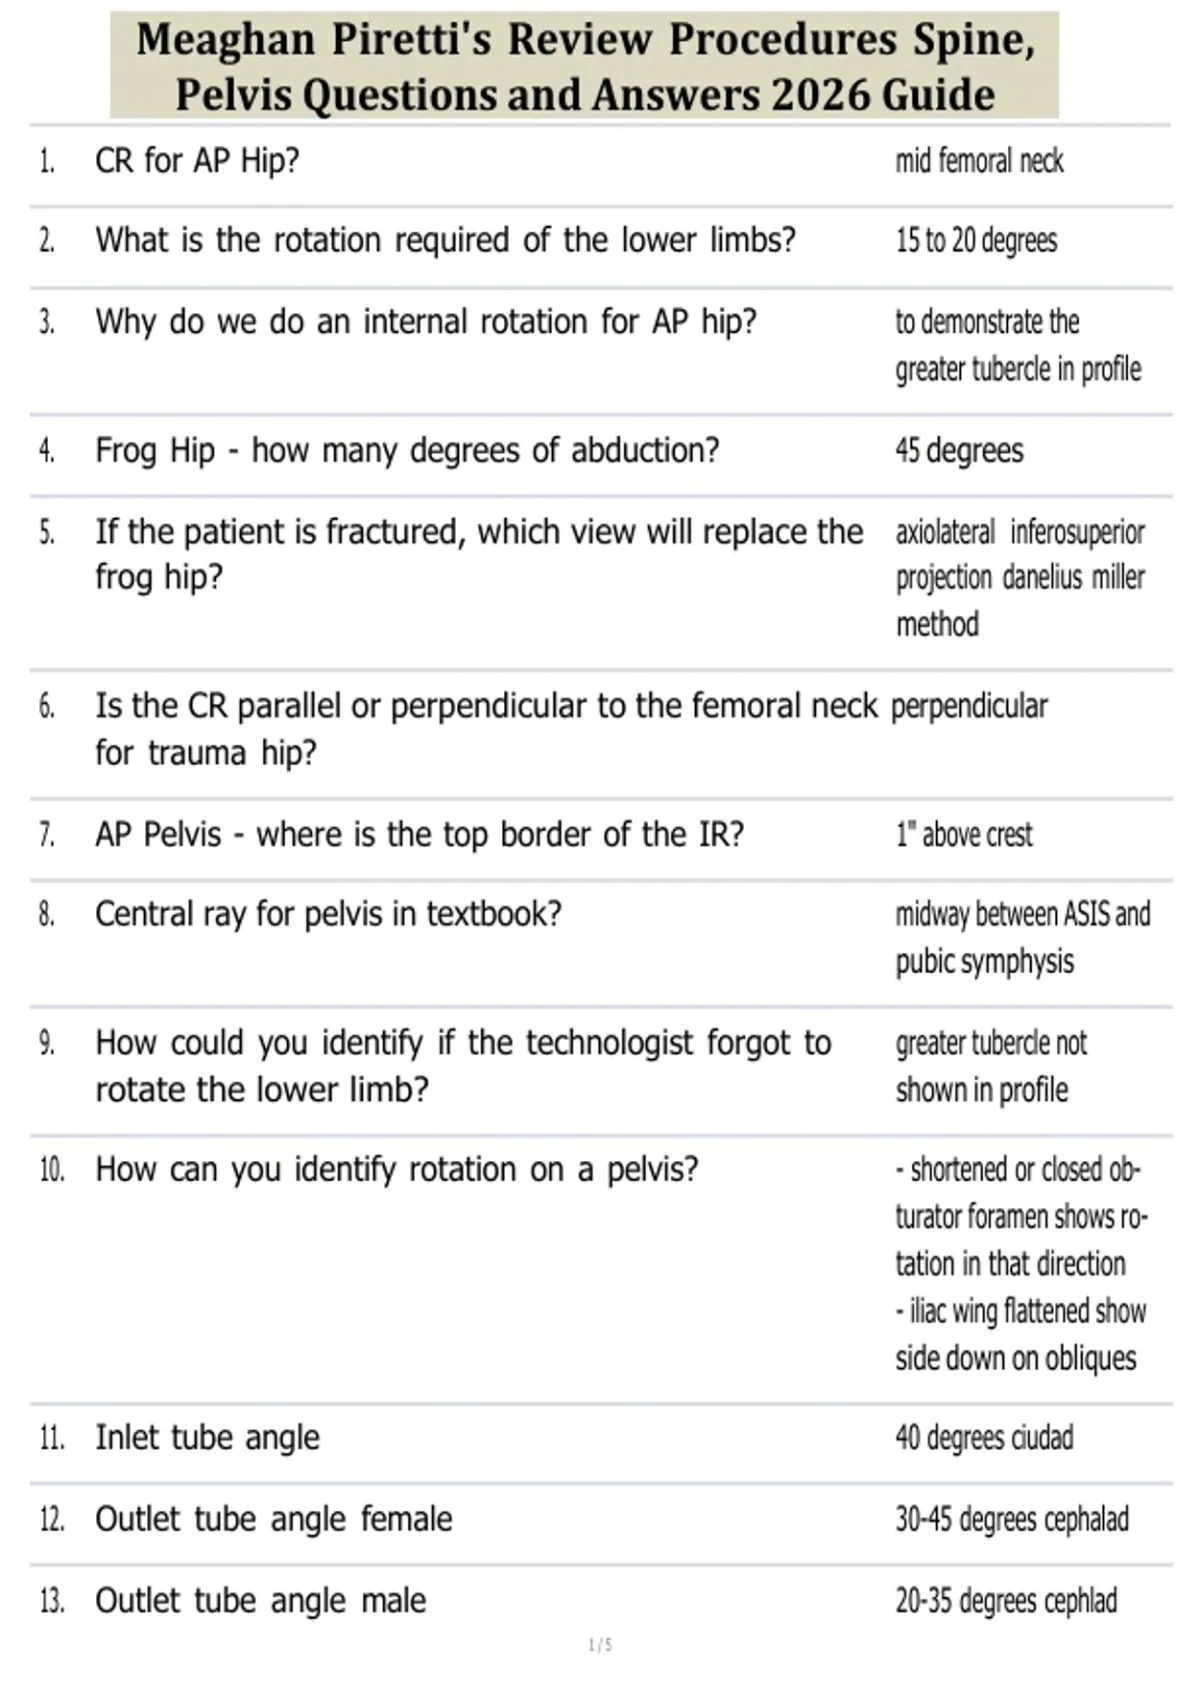
There isn't an official Meaghan Piretti Spine download or a single canonical textbook. The method circulates primarily through clinical workshops, private practitioner networks, and a small number of instructional PDFs that circulate in niche communities. If you're looking for the notation guide itself, the most complete version I've seen is a privately distributed reference sheet that outlines the segmental scoring system and treatment sequencing. It's not something you'll find on a mainstream medical education site, and honestly, that's partly by design — the originators have kept it outside academic channels to preserve the hands-on component. What you will find online are summaries and derivative guides, some of which are accurate and some of which are oversimplified to the point of being misleading. For self-study, the most useful starting point is pairing whatever written material you can find with regular supervised practice. The notation system makes sense on paper but translates poorly into clinical judgment without someone who already knows what they're feeling showing you the difference. I'd recommend spending at least ten to twelve hours of direct mentorship before relying on the method independently.
Get the Full Details

Where This Method Falls Short
I want to be clear about the limitations because nobody talking about this method usually does. The Meaghan Piretti Spine is not a diagnostic tool for structural pathology. If a patient has a herniated disc, spondylolisthesis, or any condition that requires imaging and medical intervention, this framework is irrelevant and could actually delay proper care if someone treats it as a replacement for standard orthopedic assessment. It's designed for functional movement restrictions and myofascial patterns, nothing more. Another honest drawback is the variability in practitioner skill. Because the method depends so heavily on palpation proficiency, two practitioners working with the same patient can come away with very different readings. There's no objective instrument that validates the scores. That means choosing who teaches or practices this matters enormously — and most people don't vet their sources carefully enough before investing time and money into it. If your goal is a more structured, evidence-based approach to spinal assessment, you might be better served looking into methods like SFMA (Selective Functional Movement Assessment) or DNS (Dynamic Neuromuscular Stabilization), both of which have broader research backing and more standardized training pathways. The Meaghan Piretti Spine has its place, particularly for practitioners who already work in soft tissue medicine and want a more systematic way to document and track fascial findings. But it's a specialized tool, not a universal solution.



