Central tendency isn't a concept you figure out once in school. You figure it out again every time you open a dataset.
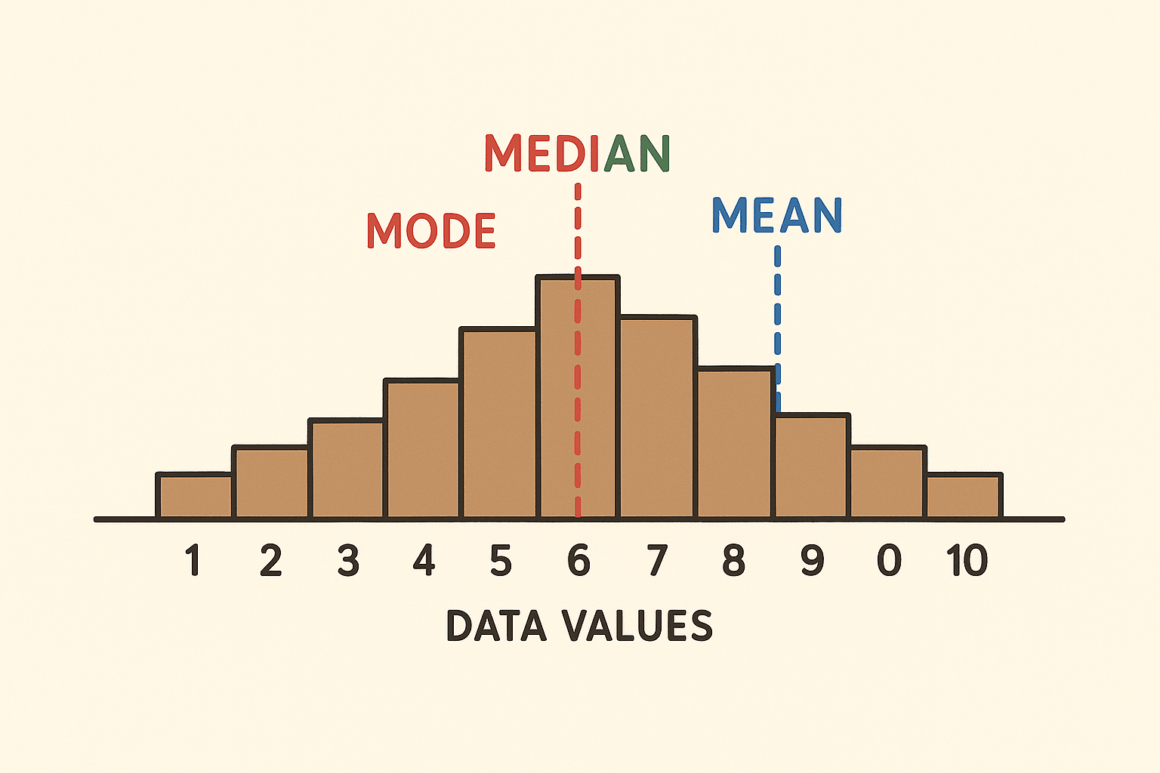
I still remember pulling a survival dataset for a Phase II oncology trial. The mean overall survival came out to 14.2 months. The median was 8.7 months. Two patients had lived over three years and were still alive at the time of analysis, and they dragged that mean so far right it barely represented anyone in the study. I spent two solid days explaining to the clinical team why median was the number that actually mattered here. Mean gave a nicer press release number, sure, but it was lying by omission. This is what Mean Median Mode Biostatistics actually is. Not a memorized definition for an exam. It's knowing which measure describes your data and which one is actively misleading you. The mode, the mean, and the median each answer different questions. You pick the wrong one and your entire analysis shifts.
Mean Median Mode Biostatistics: What each one actually does
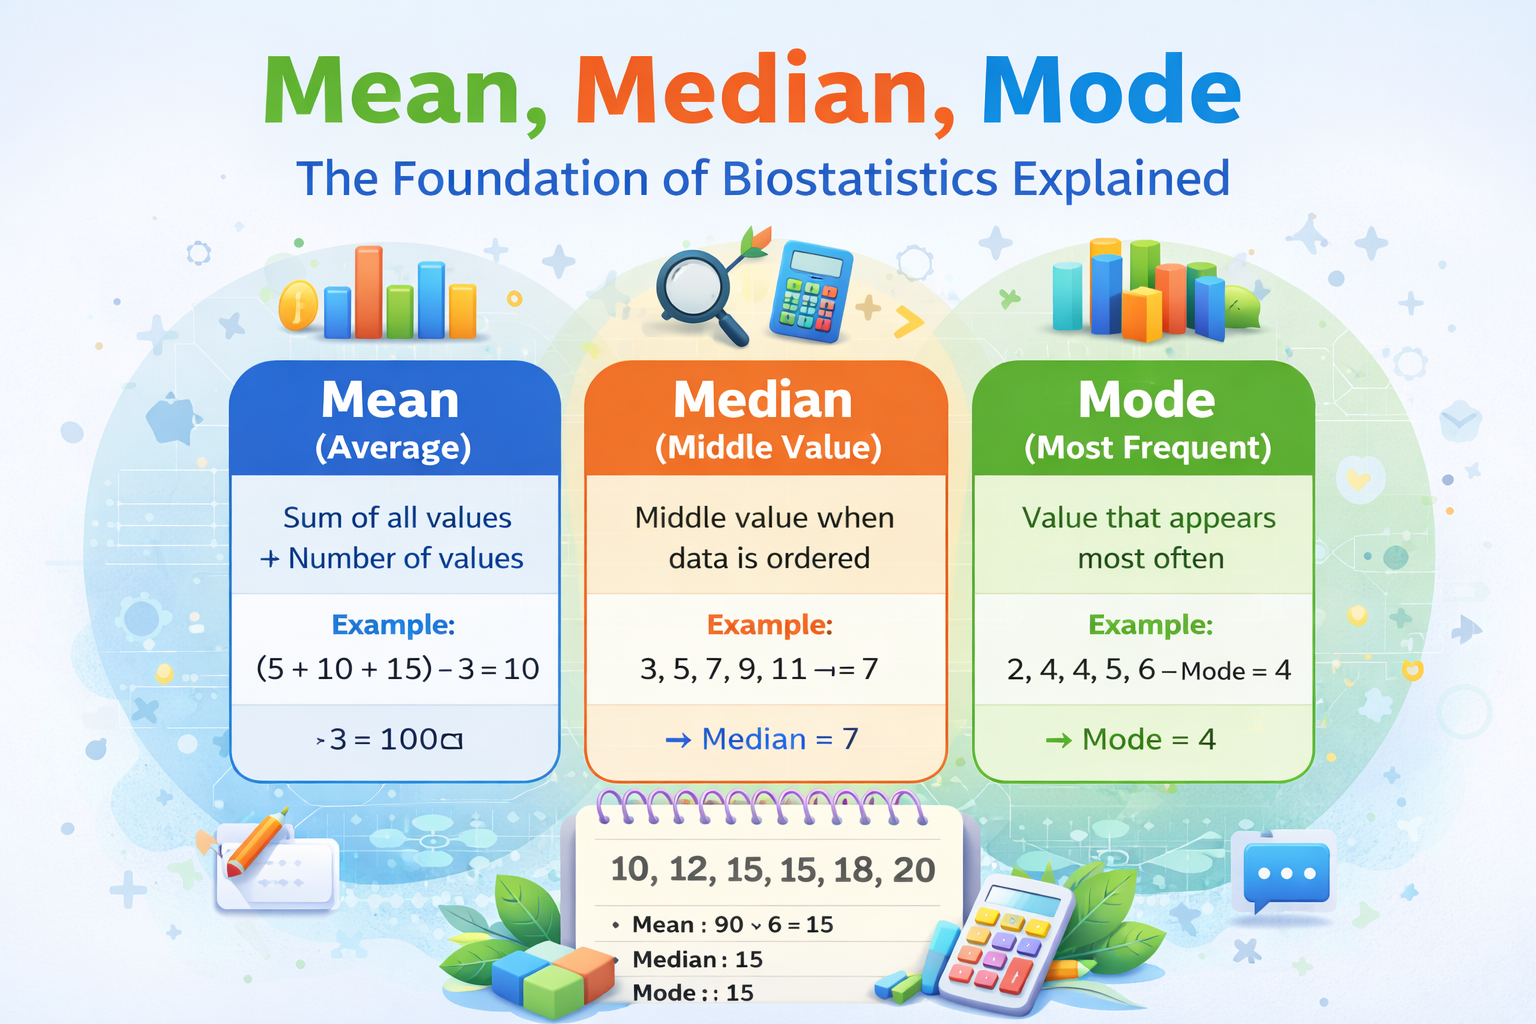
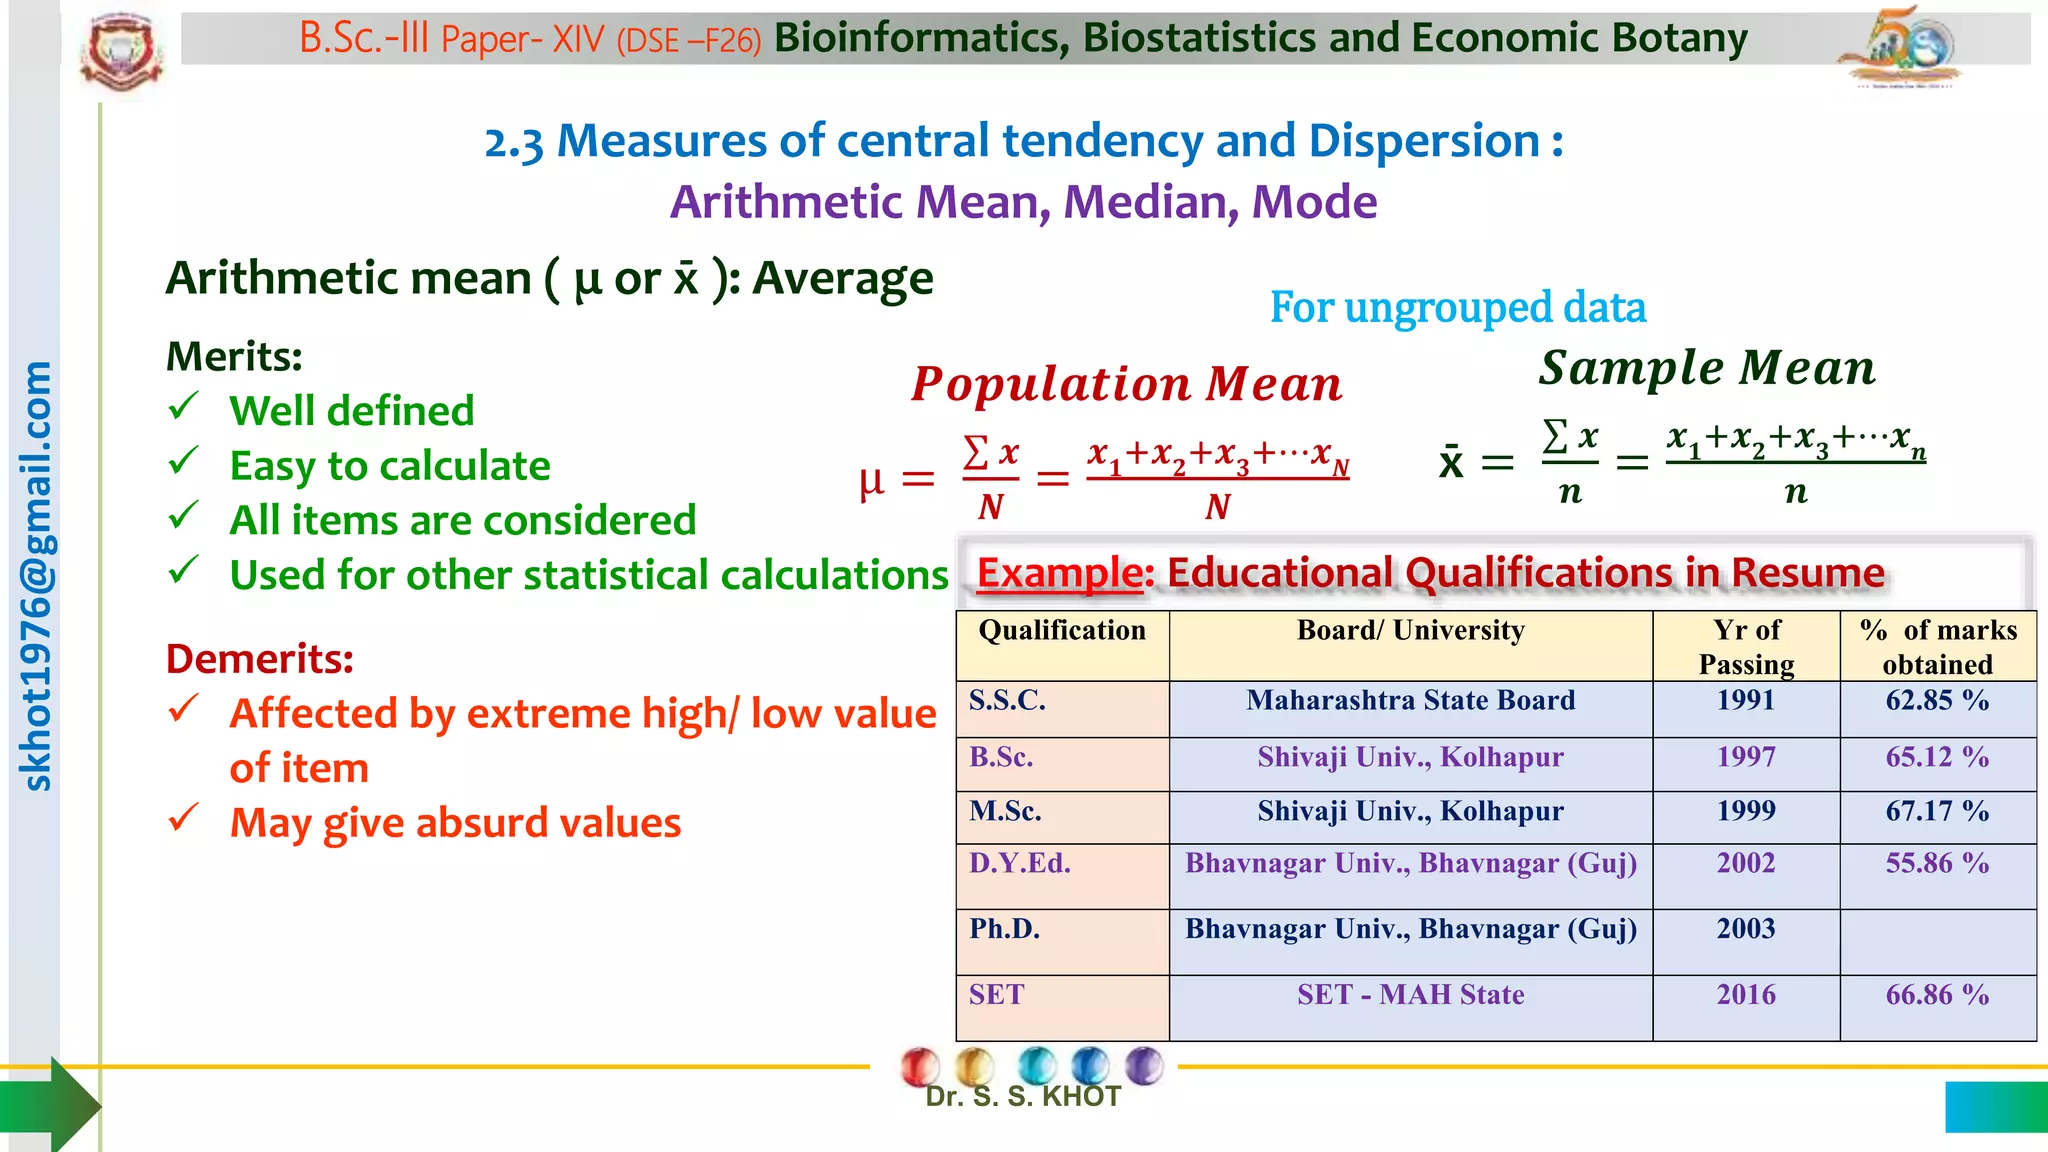
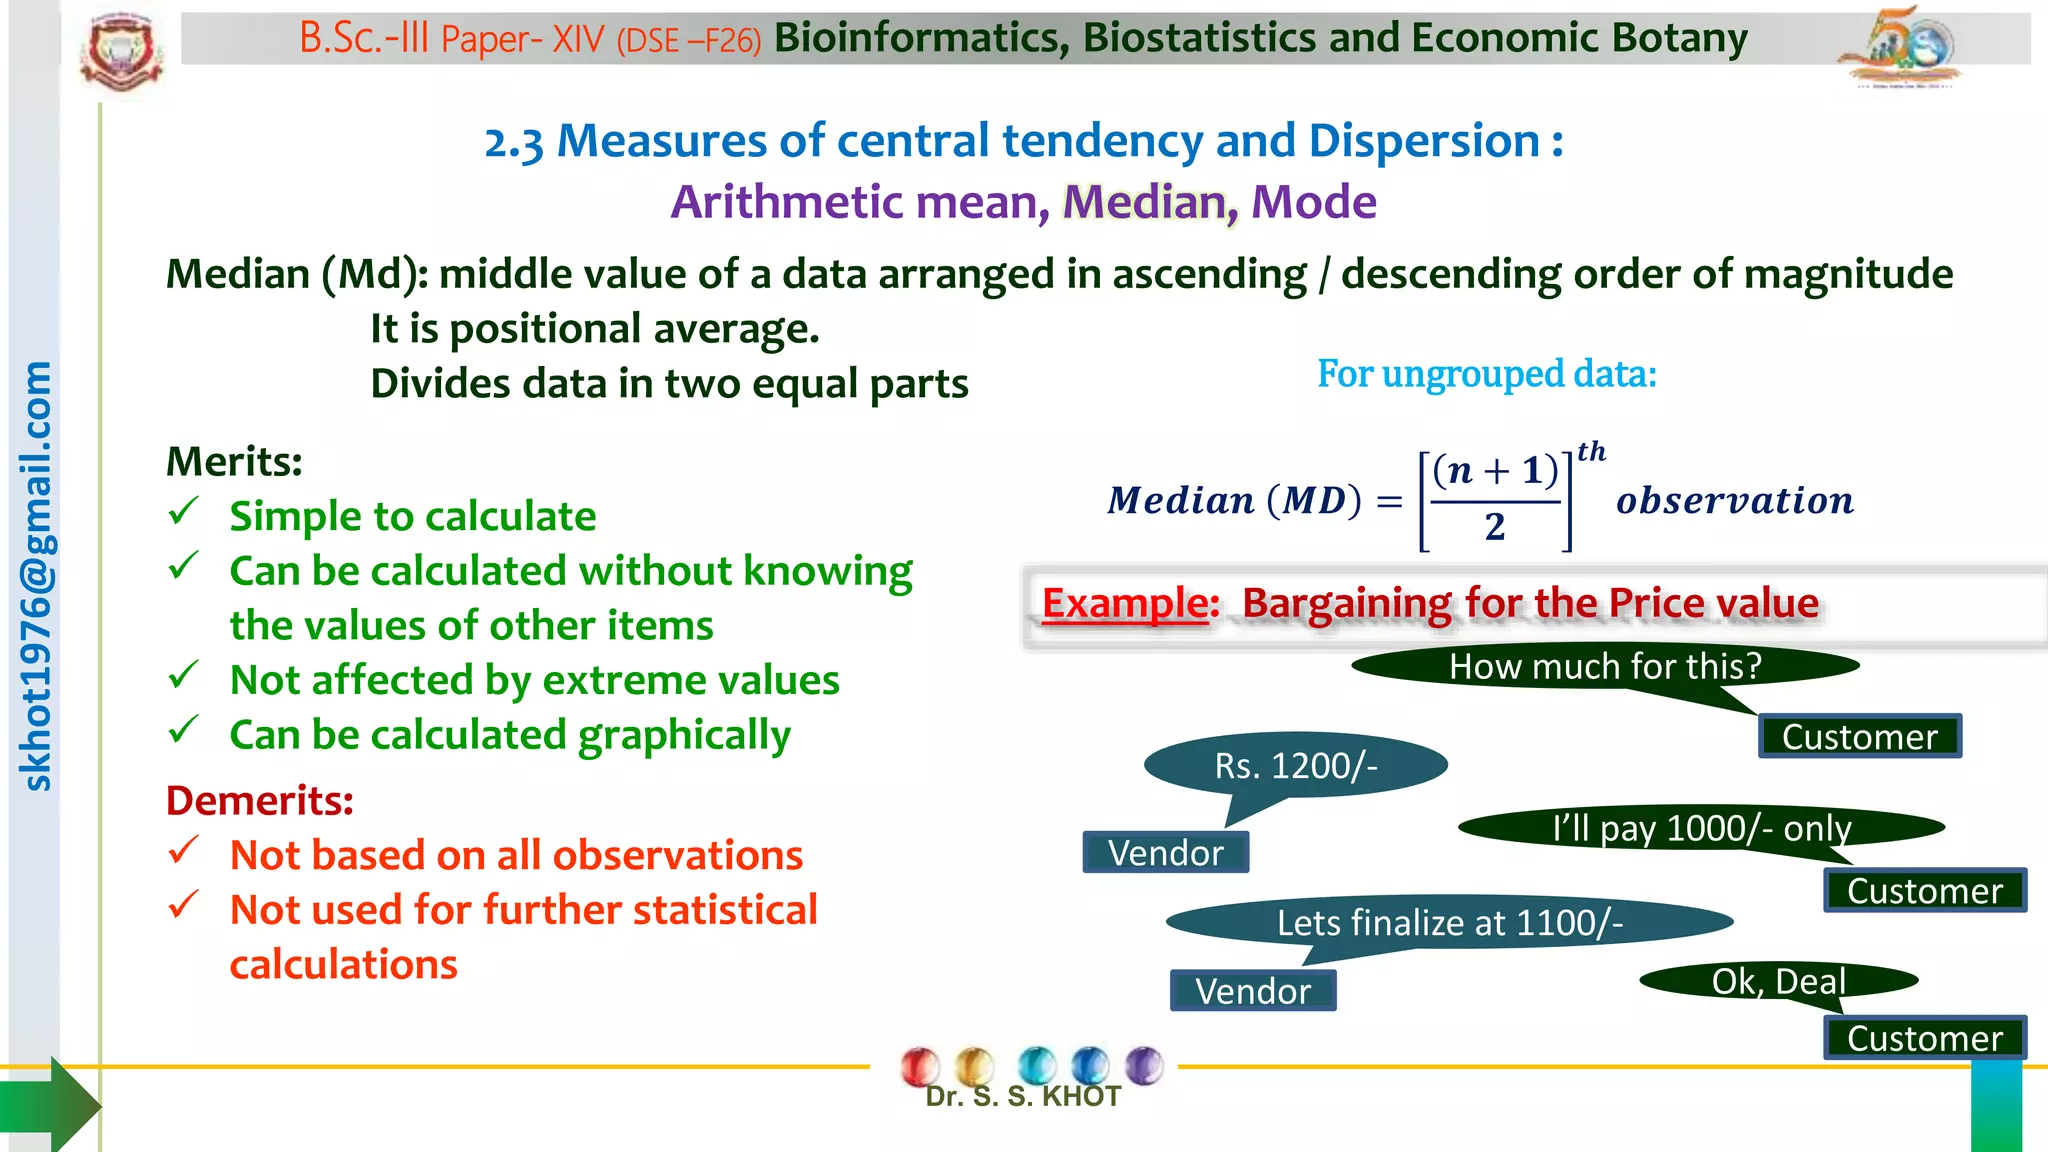
The mean is the arithmetic average. Sum everything, divide by the count. It's sensitive to every single value in the dataset, including outliers. A single extreme value can shift it dramatically, which is both its strength and its fundamental weakness. The median is the middle value when your data is ordered. Half the observations fall below it, half above. It ignores the magnitude of extremes entirely. In survival analysis, lab values with a long right tail, or income distributions, the median is often the number people actually need even though they rarely admit it. The mode is the most frequently occurring value. It sounds trivial until you're dealing with discrete clinical measurements like blood pressure categories, Likert scale survey responses, or genotypic data where certain alleles repeat with predictable frequency. The mode is the only measure of central tendency that works for nominal data. You cannot calculate a mean or median for a categorical variable like blood type.
I found this out the hard way during a health services utilization study. We were categorizing patient visit frequency and someone suggested running a mean on a variable that was heavily zero-inflated with a long tail of repeat visitors. The mean suggested an average of 3.4 visits per patient per year. The median was 1. The mode was also 1. The mean made it look like utilization was than it actually was because a small cluster of high-utilizer patients was pulling the number up. We ended up reporting median with interquartile range and adding a separate breakdown for the high-utilizer group. The original mean-based summary would have cost us credibility with the department chairs.
Get the Full Details
When the standard approach fails you
Beginners are taught that mean, median, and mode are just three numbers to calculate and report. That's incomplete. The real question is which one your data distribution actually supports and what assumptions you're making when you pick it. One counter-intuitive point that comes up constantly: the mean is not always worse than the median just because your data has outliers. If you're working with normally distributed data and the outliers are genuine observations rather than data entry errors, the mean is actually the more efficient estimator. It has lower variance across repeated samples. The median becomes preferable only when your distribution is meaningfully asymmetric or when extreme values are artifacts of measurement error or a different underlying population your sample. Another thing people miss is that the mode is not uniquely defined. A dataset can be multimodal, and reporting a single mode gives you nothing useful. I encountered a bimodal distribution in a lab quality control dataset where one peak represented normal results and the other represented samples affected by a reagent lot issue. Reporting the mode as a single number would have been actively harmful. We had to identify the two subpopulations first and analyze them separately before any central tendency measure made sense.
How I actually compute and validate these in practice
Here's the workflow I use when I pull a new dataset. I don't calculate anything until I've visualized the distribution. Histogram, box plot, kernel density estimate. I need to see the shape before I decide whether the mean or median is appropriate. This usually takes about five to ten minutes in R or Python and prevents at least an hour of downstream correction work. For the mean, I compute it with the standard arithmetic formula but I immediately check the coefficient of variation and the skewness. If skewness exceeds 0.5 in absolute value, I flag the mean as potentially misleading and report the median alongside it. For the median, I sort the data and find the middle position. With even sample sizes, it's the average of the two central values. For the mode, I use a frequency table and identify the highest count. In continuous data, I bin the values first or use a density estimation approach rather than looking for exact duplicate values, which almost never exist in real clinical data. When I hit missing data, which is nearly every dataset, I do not simply delete rows. Listwise deletion can introduce bias if the missingness is not completely random. I check the missingness mechanism first. If it's missing at random, I use multiple imputation. If it's missing not at random, I flag it and report sensitivity analyses showing how the central tendency measures shift under different assumptions. In one dialysis adherence study, the mean adherence appeared acceptable at 82 percent until I ran a sensitivity analysis assuming the missing patients were nonadherent. The adjusted mean dropped to 61 percent. That changed the entire clinical recommendation.
Software shortcuts that save time
I use R primarily now. The base function summary() gives you mean, median, and min/max in one call. The psych package's describe() function adds standard deviation, skewness, and kurtosis. For quick mode calculation on categorical variables, table() followed by which.max() works fine. In Python, numpy and pandas handle mean and median efficiently, but mode requires scipy.stats.mode or pandas.value_counts(), and scipy's implementation has been historically problematic with multimodal data. I recommend using the pingouin package or rolling your own mode finder with value_counts() when dealing with complex distributions. If you're working in Excel, be aware that the AVERAGE function includes hidden rows and filtered data depending on your version, which can produce misleading results in large datasets. Use SUBTOTAL with function number 1 for mean and 2 for median when your data is filtered. It saves you from manually recalculating whenever you adjust a pivot table.
What these measures cannot tell you
The mean, median, and mode describe central tendency only. They tell you nothing about spread, shape, or the presence of subpopulations. A dataset with mean 50 and standard deviation 5 looks very different from one with mean 50 and standard deviation 25, even though the central value is identical. Always report variability alongside central tendency. Interquartile range with the median is the standard pairing for skewed data. Standard deviation with the mean works for approximately symmetric distributions. These measures also fail when your sample size is very small. With fewer than 20 observations, all three statistics become highly unstable. A single new data point can flip the median or create a spurious mode. In those cases, I report the raw data sorted numerically and let readers draw their own conclusions rather than giving a single summary number that implies precision we don't have. I've also seen analysts apply mean-based parametric tests to heavily skewed data and then wonder why their confidence intervals look wrong. The mean exists, but the sampling distribution of the mean may not be approximately normal with small n and high skew. In those situations, nonparametric methods or bootstrap confidence intervals are more appropriate. The central tendency measure itself is still valid, but the inferential framework around it needs adjustment.
A practical example from a recent project
Last quarter I analyzed readmission rates across three hospital units. The raw readmission percentages were heavily right-skewed because a few high-volume units had disproportionately many readmissions. The mean readmission rate across units was 18.3 percent. The median was 12.1 percent. The mode was 9 percent, which was also the most common rate among the majority of units. I reported all three values with a note explaining the skew, and I used the median for between-unit comparisons. The mean was included only for context because administrators outside the statistics team were more familiar with it. This approach took about twenty minutes once the data was cleaned and prevented the kind of miscommunication that happens when a single misleading average gets quoted in a board meeting. The practical takeaway is that Mean Median Mode Biostatistics is less about calculation and more about diagnosis. You look at your data, you understand its structure, and then you pick the measure that matches. The calculation itself is trivial. Knowing which measure to trust and which to discard is what takes experience.