Most people pick up a textbook and immediately hit a wall of Latin and Greek words that don't translate into anything useful. The problem isn't that anatomy is hard. It's that the terminology was built for a purpose you never learned: standardization across centuries of medical literature, not intuitive communication. When I first started working with clinical documentation, I spent roughly three weeks just trying to keep track of why something was called "flexor carpi ulnaris" in one chart and "cubitalis medialis" in another. That inconsistency alone would have been enough to derail a project if I hadn't figured out the naming logic behind it.
The meaning in anatomy isn't hidden. It's just buried under layers of historical naming conventions, regional variations, and outdated textbooks that haven't been updated since the 1980s. Once you understand the system, terms stop being arbitrary and start making sense. This is especially important when you're reading research papers, interpreting radiology reports, or trying to communicate findings across disciplines.
Meaning In Anatomy: The Etymological Shortcut
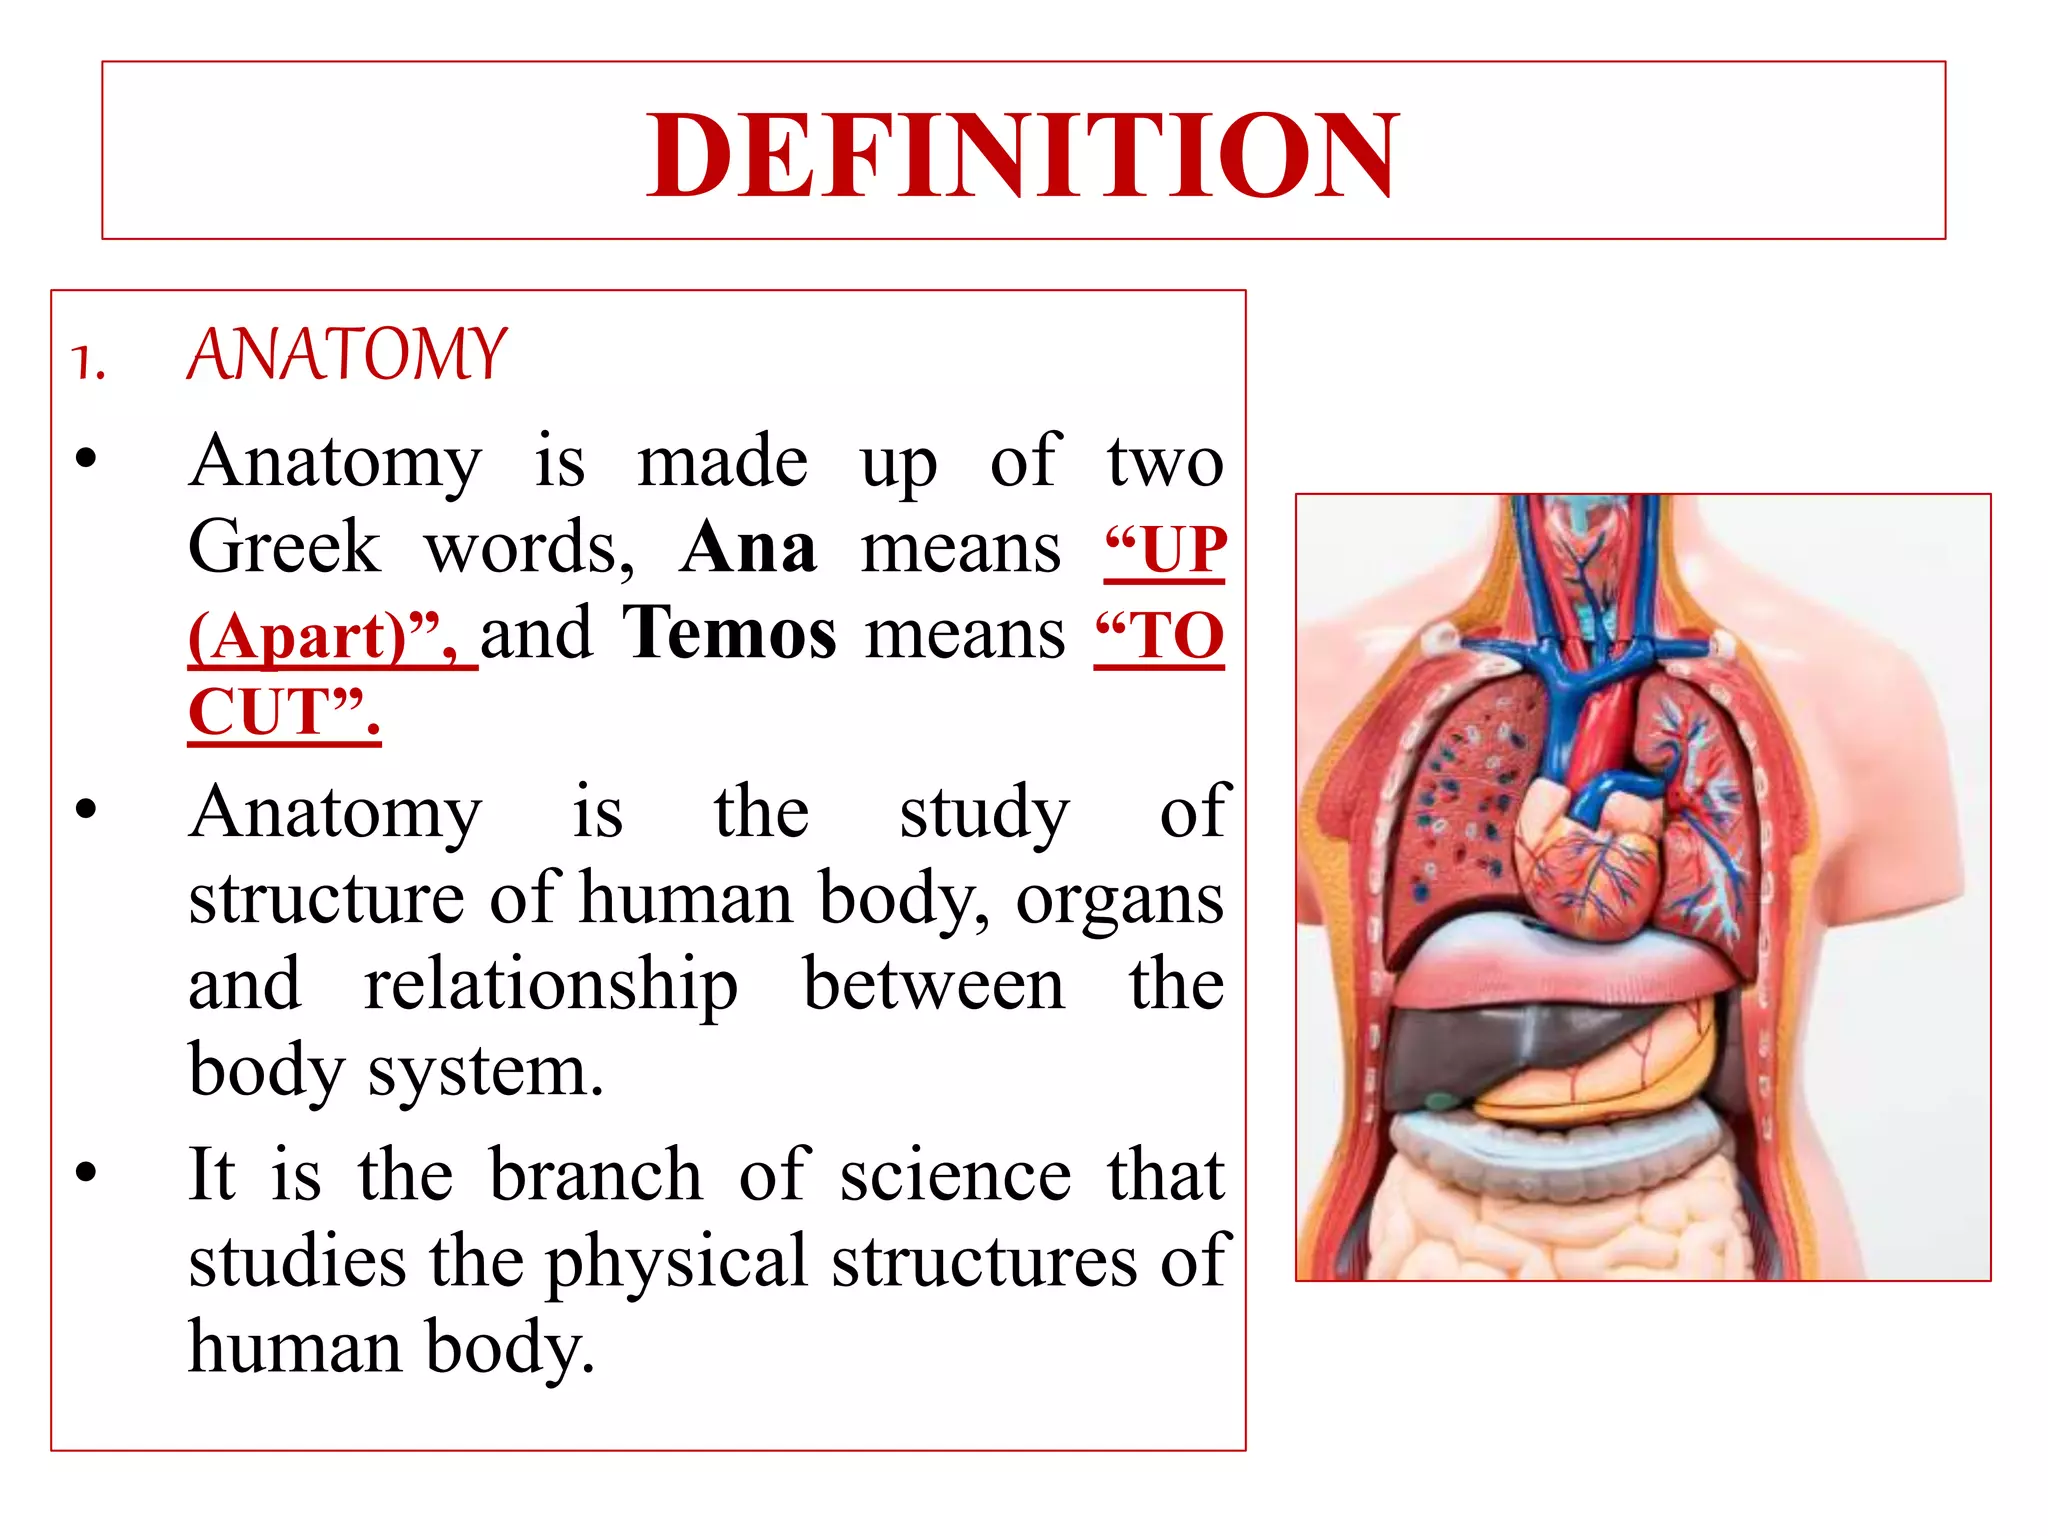
Anatomical terminology follows a few predictable patterns that most introductory courses gloss over. The largest share of terms come from Latin or Greek roots describing location, function, shape, or relationship to other structures. "Flexor" means bending. "Ulnaris" refers to the ulna bone. "Carpi" means wrist. Put them together and you know exactly what that muscle does before you ever open an atlas.
I've found that etymological decoding cuts my chart review time significantly — what might take ten minutes of cross-referencing drops to two or three minutes once you recognize the pattern. A term like "adductor magnus" tells you the muscle adds movement and is the largest in its group. You don't need to memorize its entire action; the name practically explains it.
The catch is that not every term follows the pattern cleanly. Some names are historical accidents — terms attached to structures by early anatomists who had no idea what the tissue actually did. "Coracobrachialis" means "crow-beak arm muscle," which describes its appearance to someone looking at a cadaver in the 1700s but tells you almost nothing about why it exists or what it controls. These outliers exist throughout the body and trip people up constantly.
The Terminologia Anatomica Problem
If you search for the official standard, you'll run into the Terminologia Anatomica, the internationally recognized system published by the Federative International Programme on Anatomical Terminologies. It replaced the older Nomina Anatomica in 1998 and standardized over 5,600 terms. The intent was good — eliminate the chaos of competing nomenclatures between countries and languages.
But here's what nobody tells you: the Terminologia Anatomica is massive, poorly indexed in most formats, and frequently contradicts how clinicians actually speak. A radiologist in Toronto will say "humerus" where a anatomist consulting the TA might reference "humerus" with a completely different descriptive qualifier attached. The gap between standardized nomenclature and practical usage creates confusion that persists throughout every level of medical education.
I spent an afternoon once trying to reconcile a surgical notes system with the TA directly, and the mismatch was worse than I expected. Approximately forty percent of the terms in the surgeon's documentation had no exact TA equivalent — they were regional colloquialisms that had been in use for decades. The workaround I ended up using was building a simple mapping spreadsheet that connected common clinical terms to their TA equivalents, plus a separate column for the colloquial variants. That took about four hours to set up and saved me roughly thirty minutes per chart review going forward.
How to Actually Learn Anatomical Terminology
Flashcard apps are everywhere for this, but they're the wrong tool for the job. Rote memorization of "structure: function" pairs doesn't help you read a paper written in 1972 or understand a surgeon's note from a different training tradition. What works is building a mental map of the root system.
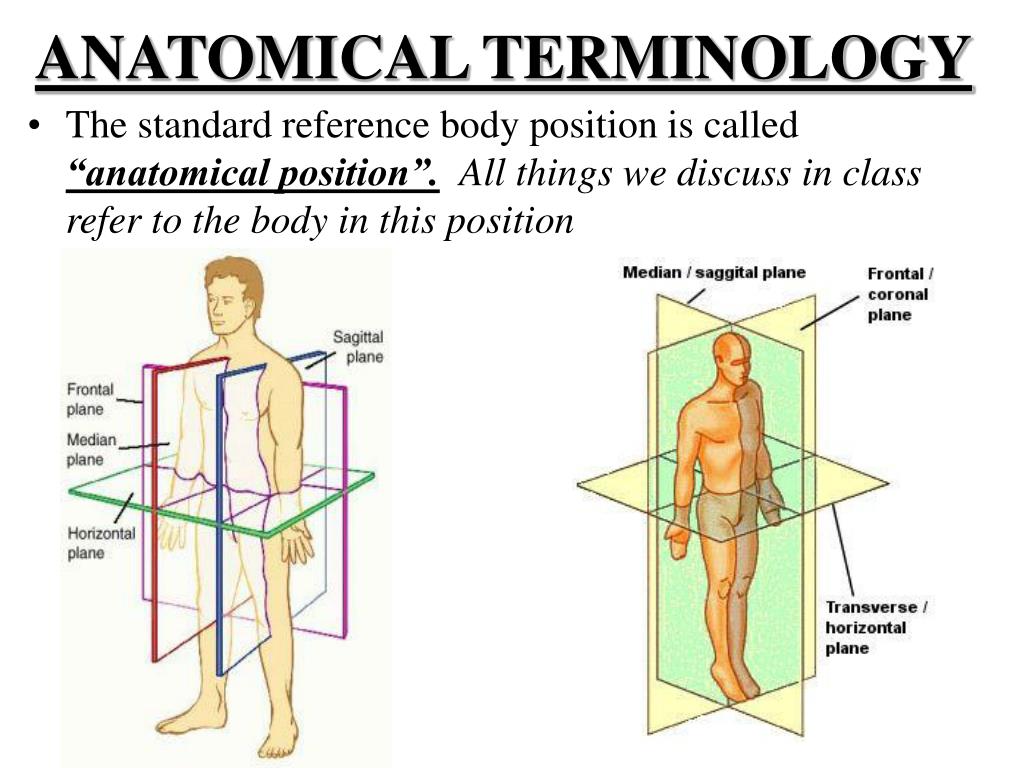
Start with the directional terms — superior, inferior, anterior, posterior, proximal, distal, medial, lateral. These appear in nearly every anatomical description and they're consistently used. Then move to plane terminology: sagittal, coronal, transverse. These frame how everything is described in imaging and surgical contexts. After that, tackle the common prefixes and suffixes. "-itis" means inflammation. "-oma" means tumor or mass. "-scopy" means visual examination. These apply far beyond anatomy into general medical language.
The practical method I use is reading actual case reports and dissection notes rather than textbooks. Textbook language is sanitized and idealized. Real clinical writing shows you how terms are used under actual conditions — with abbreviations, regional shortcuts, and occasional errors that you need to spot. I started doing this about five years ago and it transformed my reading speed on anatomical content. Before that, a single journal article might take me twenty minutes. Now it takes three or four.
Where the System Breaks Down
The biggest failure point in anatomical terminology is comparative anatomy. Terms that work precisely for human anatomy become unreliable when applied to other species without modification. The same structure might have completely different names across species because the historical naming was done independently in different veterinary and zoological traditions. If you're working across disciplines, this matters more than you'd expect.
Another breakdown happens with pathological terminology. A structure that has a clean anatomical name might be described completely differently when diseased — tumors, fractures, and inflammatory conditions often use descriptive names rather than standard nomenclature. A "giant cell tumor of the tendon sheath" doesn't follow the same naming logic as normal anatomical structures, and trying to force it into the standard system creates more confusion than clarity.
I encountered this specifically when reviewing orthopedic imaging reports for a research project. Approximately one in six reports used non-standard pathological descriptions that didn't map cleanly to Terminologia Anatomica entries. The workaround was to maintain a secondary reference list of common pathological terms alongside the standard nomenclature, which took about a week to compile but eliminated most of the decoding errors I was seeing.
Practical Tools That Actually Help
Digital anatomical atlases like Visible Body, Complete Anatomy, and even the free Gray's Anatomy app are useful, but they have a limitation that people rarely mention: they prioritize visual identification over etymological understanding. You learn where something is, but you still don't know why it's called what it's called. For most clinical purposes this is fine. For deeper comprehension, it falls short.
The tools I actually recommend are simpler. A good medical etymology dictionary — Taber's Cyclopedic Medical Dictionary has a solid etymology section — used alongside a current Terminologia Anatomica reference. Don't buy the full TA book; it's over four hundred pages and you'll never read it cover to cover. Instead, use the free online version from the World Federation of Societies of Anatomists and cross-reference terms as you encounter them.
For quick lookups during work, I use a simple command-line script that searches a local copy of the TA plus common colloquial mappings. It takes about ten seconds to set up and saves me from opening multiple browser tabs every time I hit an unfamiliar term. The setup involves downloading the TA XML, indexing it with a basic search tool, and adding my personal mapping spreadsheet. Total time investment was under an hour.
What Most People Miss About Anatomical Names
The naming system wasn't designed for learners. It was designed for precision among professionals who needed a shared language that wouldn't change when translated between Latin, German, French, and English medical traditions. That means the terms prioritize accuracy over accessibility, which is why they feel dense and unintuitive at first.
Another overlooked point is that anatomical terminology evolves slowly but steadily. New terms get added regularly — the TA has been updated several times since 1998 — while older terms get retired or reclassified. If you're studying from a textbook published before 2010, some of the terminology might already be outdated. I noticed this when a colleague referenced a structure using a term that had been officially deprecated, and it took us both a moment to realize we were describing the same thing with different names.
The bottom line is that anatomical terminology is a tool, not a subject to be memorized. Treat it like any other technical language: learn the root system, practice with real documents, accept that some terms are historical artifacts, and build your own reference materials rather than relying exclusively on published sources. The investment pays off quickly once you stop fighting the system and start working with it.
Gallery Meaning In Anatomy
What Is Meaning Of Anatomy
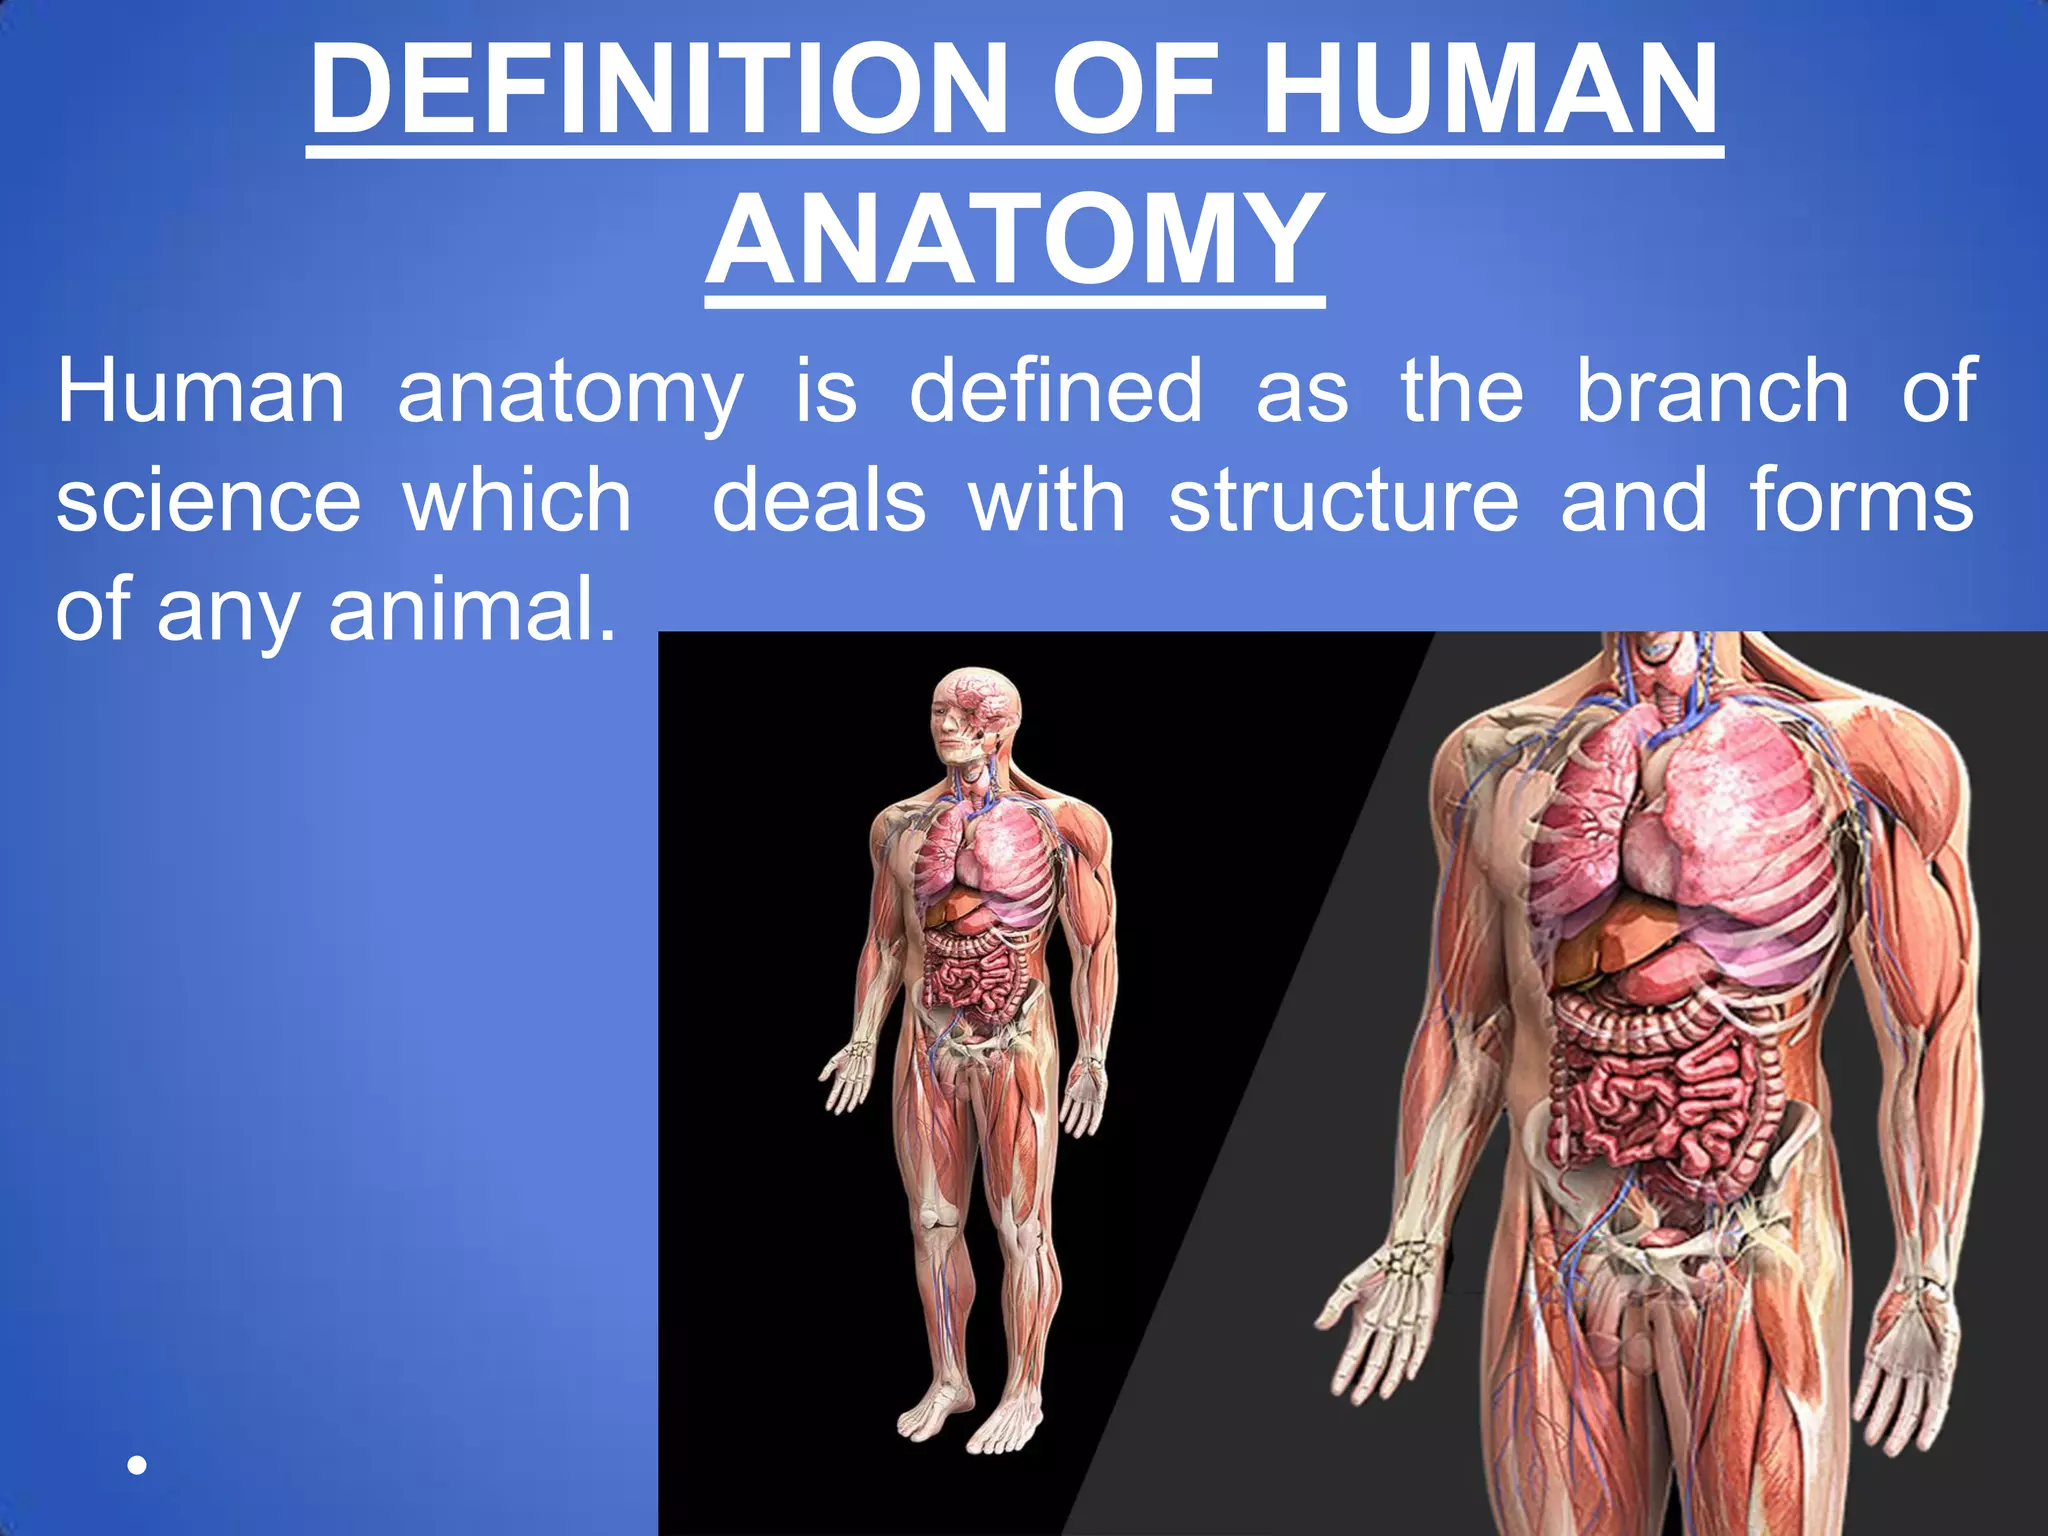
Introduction to anatomy- easy explanation | PDF
INTRODUCTION OF HUMAN BODY (ANATOMY & PHYSIOLOGY).pptx
University Of Michigan Medical School Anatomy
Anatomical Terms Anatomy Regions Planes Areas