Rotational Decompression for Mechanical Low Back Pain: The Porterfield Method Explained
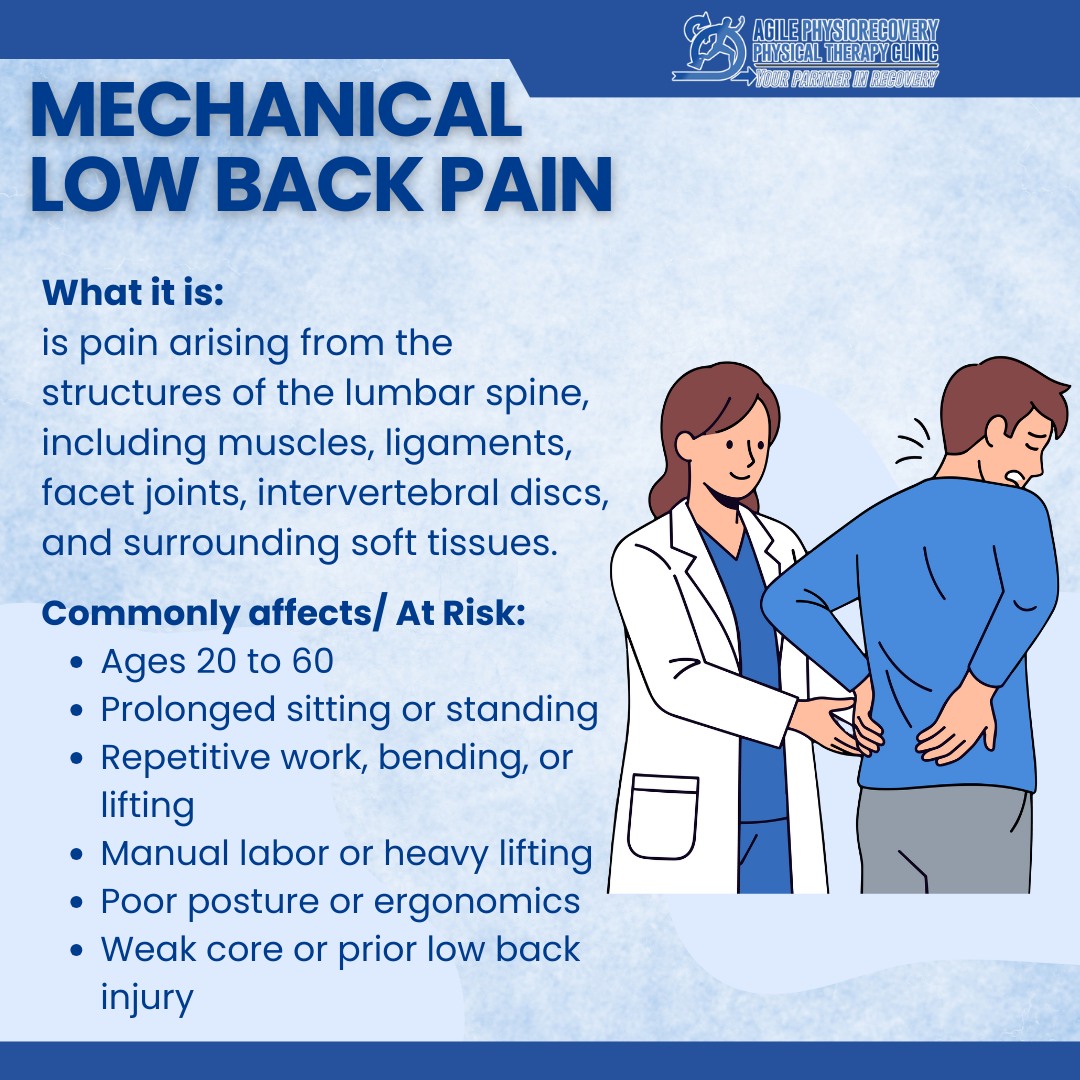
Most people walking into a physical therapy clinic with low back pain fall into one of two buckets: they have a disc issue or they don't. Dr. James A Porterfield's approach to Mechanical Low Back Pain James A Porterfield built on the reality that a significant number of patients sit squarely in between, and the standard treatment protocols were missing them entirely. He developed rotational decompression therapy as a response to that gap, and it remains one of the more clinically useful but under-discussed interventions for mechanical back pain outside of specialized circles. The lumbar spine experiences shear forces constantly. When you rotate your trunk, even slightly, the facet joints and surrounding ligaments take load. Most mechanical low back pain originates from a combination of disc dysfunction and facet joint irritation that creates a cycle where certain positions or movements trigger pain, and the body responds by guarding — which then increases stiffness and further limits safe range of motion. Porterfield's key insight, published in his work through the 1980s and 1990s, was that rotational decompression could address both components simultaneously by reducing pressure on the disc while also mobilizing the facet joints in a controlled way. The technique involves a specific directional rotation combined with axial traction, and it's not a general stretch. The angle matters, the speed matters, and the direction relative to the patient's pain pattern matters more than anything else.
How the Technique Is Applied
The patient lies prone on a treatment table. The therapist rotates the patient's pelvis and lower thoracic region in a specific direction — either left or right — while applying a sustained, gentle longitudinal traction force. The rotation is typically held for about 30 seconds to a minute per set, with three to five sets per direction depending on tolerance. The goal is not to push into pain but to create a separation at the affected level that reduces mechanical compression. The directional preference is critical. If a patient's pain centralizes with rotation in one direction and peripheralizes in the other, you treat toward centralization. This follows the same logic as the McKenzie method, but the decompression component adds the traction element that changes the mechanical environment of the disc and facets differently than repeated movement alone would. In practice, I've found that the most common mistake therapists make is applying too much force early on. The decompression effect is produced by sustained, low-load positioning, not by aggressive rotation. I had a patient once who had been receiving aggressive spinal manipulation for six weeks without meaningful improvement. We switched to rotational decompression at approximately 15 percent of their maximum rotational capacity, held for 45 seconds, and they reported a noticeable reduction in radicular symptoms within the first session. It wasn't magic — it was a different mechanical stimulus applied at the right magnitude.
What the Evidence Actually Shows
The literature around rotational decompression is modest but consistent. Studies published by Porterfield and colleagues demonstrated significant improvements in patients with acute and subacute mechanical low back pain, particularly those with discogenic components. A commonly cited figure from his research is that roughly 70 to 80 percent of appropriately selected patients experience meaningful relief, though selection criteria are tighter than most clinicians apply them in practice. The counter-intuitive point that most beginners miss is that this technique can actually worsen symptoms if applied to the wrong patient. Patients with spondylolisthesis, significant facet arthropathy, or instability patterns may experience increased pain because the decompression and rotation combine to increase stress on already compromised structures. A quick screening test involves having the patient perform repeated extension movements first — if those centralize symptoms, the patient is likely a good candidate. If extension makes things worse, you need to reassess before proceeding. Another thing that doesn't get enough attention is the timing component. Rotational decompression works best when applied early in the treatment course, ideally within the first two to three sessions. Once a patient has developed chronic guarding patterns and adaptive shortening of the para spinal musculature, the same technique requires more iterations and a longer overall treatment timeline. I've seen cases where switching from aggressive mobilization to rotational decompression cut total treatment time from eight weeks down to approximately four, but that only applied to patients who were still in the acute to subacute phase.
Get the Full Details

Setting Up a Protocol
If you're considering incorporating this into practice, the practical steps are straightforward. You need a standard treatment table, preferably one that allows the therapist to stand at the patient's side with clear access to the pelvis and lower rib cage. The technique itself requires minimal equipment — no tables with drop pieces or mechanical traction devices are necessary, which is one reason it persists in clinic settings despite not being widely taught. The typical protocol runs two to three times per week for three to four weeks, with reassessment at the two-week mark. Patients who show less than 20 percent improvement in pain-free range of motion or functional metrics by then usually need a different approach. That's not a failure of the technique — it's a signal that the underlying pathology falls outside the mechanical decompression model.
Limitations and When It Fails Completely
Rotational decompression does not address systemic inflammatory conditions, neoplastic processes, or referred pain from visceral sources. It is specifically a mechanical intervention for mechanically derived symptoms, and applying it to non-mechanical low back pain is a waste of time and potentially harmful. Patients with cauda equina symptoms, progressive neurological deficits, or unexplained weight loss should not be treated with this method regardless of how mechanical the presentation appears on the surface. There's also a practical limitation that most sources don't mention: the technique requires the therapist to develop a specific feel for end-feel and tissue response. It's not something you pick up from a video or a brief workshop. The difference between effective decompression and simply rotating a patient's spine is measured in millimeters of joint separation and seconds of sustained hold time. Most therapists who attempt it without proper mentorship end up producing either no decompression effect or excessive torque that irritates the tissues rather than relieving them. If rotational decompression isn't available or appropriate, the closest alternative is standard mechanical traction combined with directional preference-based exercise, though the combined shear and decompression effect of the Porterfield technique doesn't have a direct equivalent in most general orthopedic physical therapy toolkits. Some clinicians use prone propping with rotation as a self-management substitute, but the sustained decompression component is significantly reduced compared to manual application.
The core reference material remains Porterfield's own publications, particularly A Mechanical Approach to Low Back Pain, which details the clinical reasoning behind patient selection and technique modification. Secondary sources tend to oversimplify the directional component and miss the nuance around force modulation, so the original work is worth reading even if some of the formatting and organization feel dated.