How Albuterol Actually Works In Your Lungs
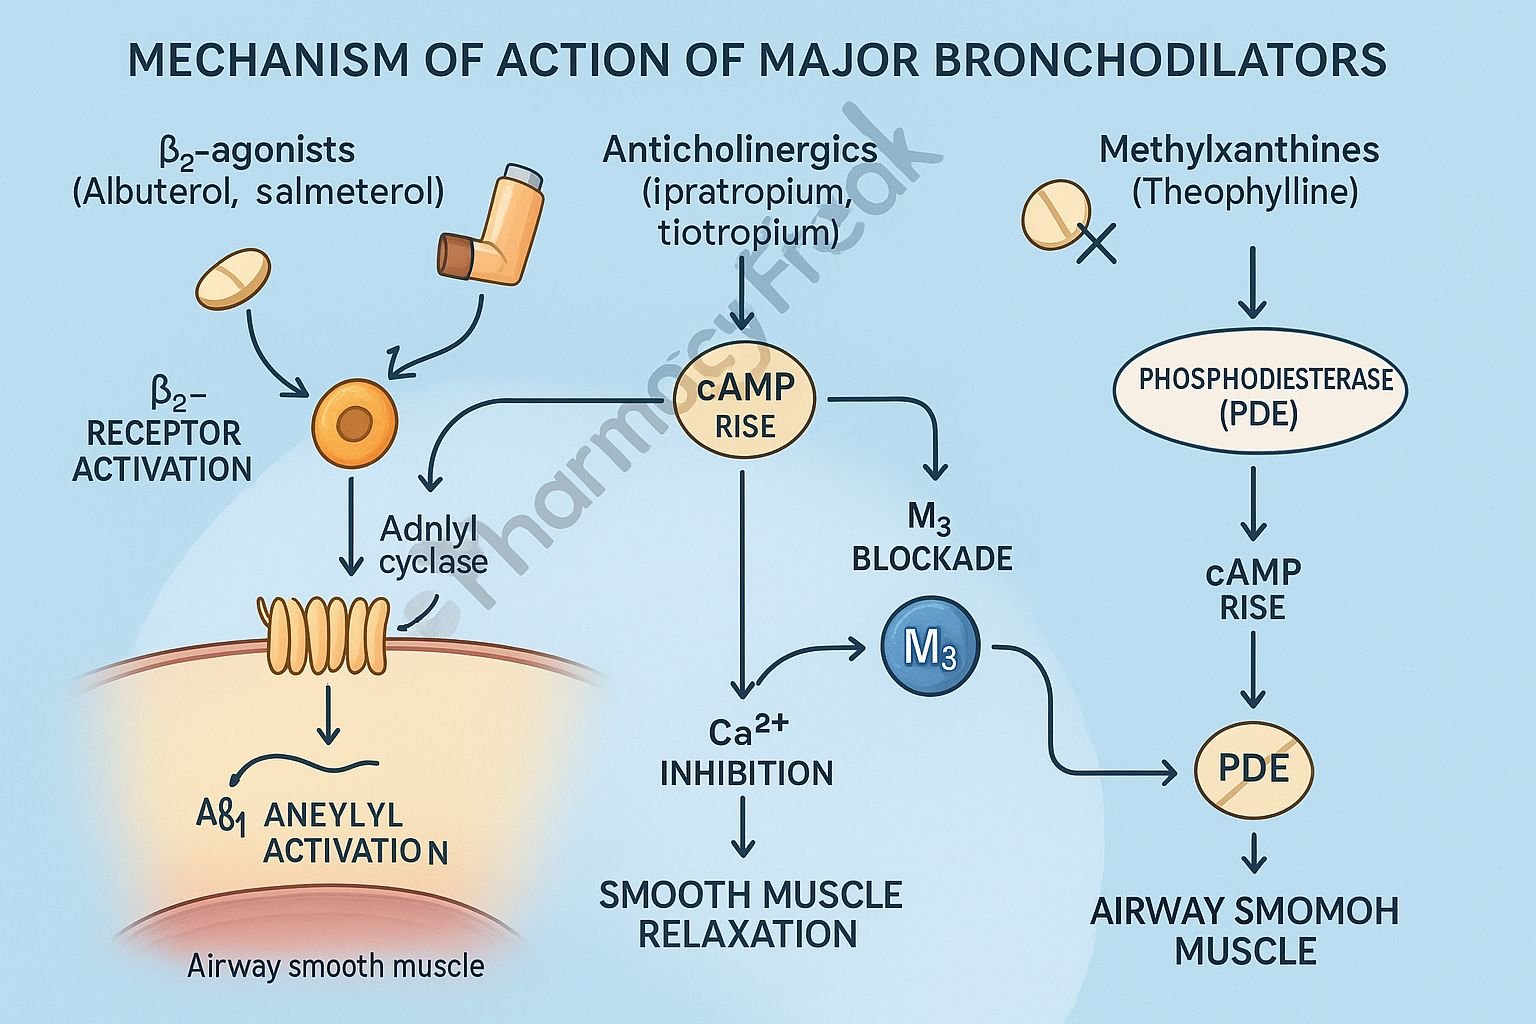
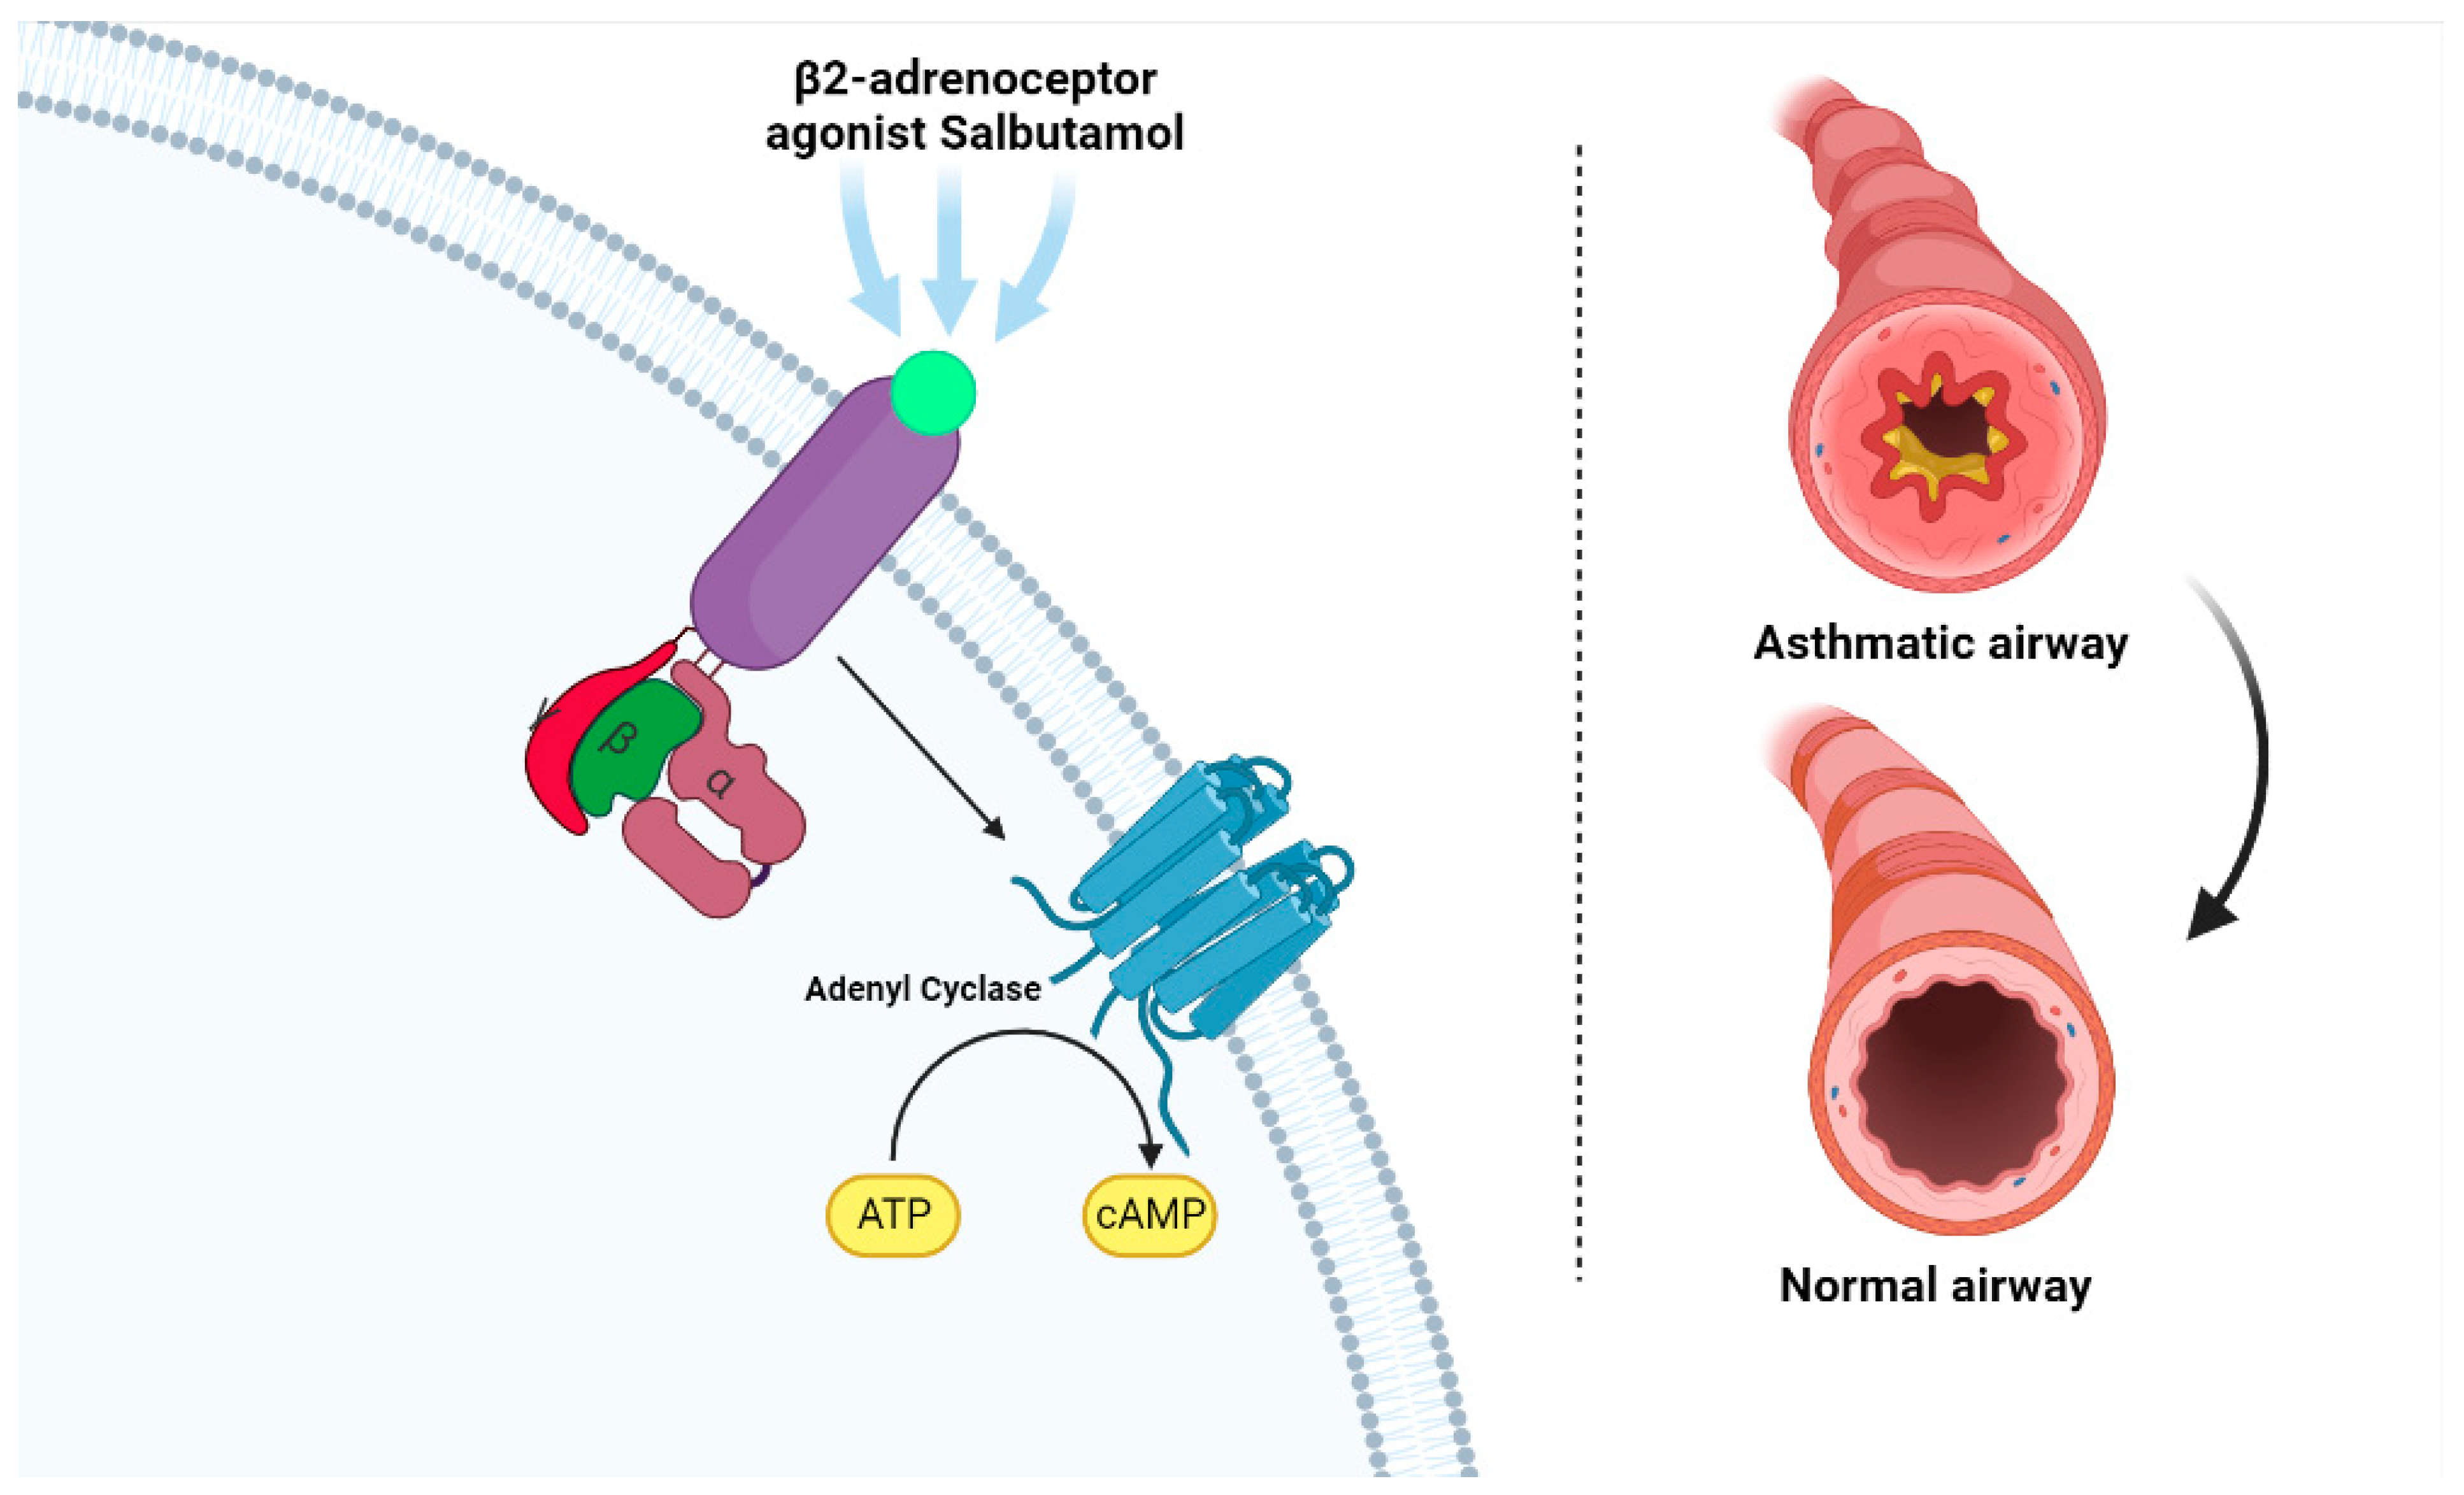
Albuterol is a short-acting beta-2 adrenergic agonist. That means it targets beta-2 receptors primarily located in the smooth muscle of your airways. When those receptors get activated, a cascade happens inside the cell that relaxes the muscle. The bronchioles open up. Breathing gets easier. It's fast—usually within minutes of inhaling it. The pathway itself isn't complicated. The drug binds to the beta-2 receptor on the surface of airway smooth muscle cells. That receptor is coupled to a Gs protein, which activates adenylate cyclase. Adenylate cyclase converts ATP to cyclic AMP. Cyclic AMP activates protein kinase A. PKA phosphorylates several targets that ultimately lower intracellular calcium levels. Less calcium means the smooth muscle can't contract. It relaxes. The airway widens.
Mechanism Of Action Albuterol
That's the textbook version. What nobody tells you is how unevenly it actually works in practice. I spent years managing asthma patients, and one thing kept coming up: two people can use the exact same dose, same inhaler, same technique, and get completely different results. The mechanism doesn't lie, but the delivery does. The real bottleneck is particle size and deposition. An MDI without a spacer shoots particles that are too large. A lot of the drug hits the back of the throat and gets swallowed instead of reaching the lower airways. Swallowed albuterol gets first-pass metabolism in the liver and does basically nothing for breathing. That's why I started pushing spacers on basically everyone who couldn't demonstrate perfect MDI technique. It took maybe two minutes to set up and cut systemic side effects significantly while improving lung deposition. Another thing that comes up less often than it should: tolerance. With frequent overuse, the beta-2 receptors downregulate. I had a patient who was hitting his rescue inhaler six or seven times a day because his underlying inflammation wasn't being treated. He came in one day and the albuterol wasn't working like it used to. Not because the drug changed. Because his receptors were tired. We got him on a daily inhaled corticosteroid and his rescue use dropped to maybe once a week. The albuterol worked fine again after that. The lesson is obvious in retrospect but easy to miss when you're just treating the acute symptom.
There's also the issue of paradoxical bronchospasm. It's rare but it happens. Some patients actually get tighter after using albuterol, usually because of a reaction to the propellant or preservative in the inhaler. If someone comes in wheezing worse after their puff, don't assume the disease is progressing. Try a dry powder inhaler instead. Different formulation, different excipients. I've seen it resolve the issue completely. Side effects are worth mentioning because they're not subtle. Tachycardia, tremor, jitteriness. These come from the drug hitting beta-1 receptors in the heart a little bit too. Albuterol isn't perfectly selective, especially at higher doses. If a patient is already running fast or has an arrhythmia, that extra stimulation can be problematic. I've seen sinus tachycardia in people who weren't even in respiratory distress just because they'd used too much albuterol. The fix is usually straightforward: treat the underlying obstruction properly so they need less rescue medication, and don't stack doses closer than four hours apart. One more practical note about nebulized versus inhaled. Nebulizers sound more aggressive and some patients feel better with them, but for mild to moderate attacks, a well-administered MDI with a spacer is at least as effective and gets the patient home faster. I saw a study once where the outcomes were identical between the two for moderate exacerbations, but the nebulizer group spent significantly longer in the ER. Time matters.
Get the Full Details

If you're studying this for an exam, memorize the Gs-cAMP-PKA-calcium pathway. If you're actually using it clinically, pay more attention to how the patient is delivering it and whether their receptor responsiveness is holding up over time. The mechanism is solid. The execution is where things fall apart.