What Actually Happens When You Take a Med Admin Practice Test
The difference between passing a medication administration exam and failing it usually comes down to one thing: you know the pharmacology facts but you don't know how the question writers trap you. I spent years working clinical floors and then reviewing exam questions for a nursing program, and I can tell you the pattern without much effort. Most practice tests you'll find online are garbage. They regurgitate definitions and throw in made-up dosage math that never appears in real life. The ones that actually prepare you for the NCLEX or your hospital competency exam share a few specific traits, and they're not what most study guides tell you to look for.
How to Use a Med Administration Practice Test Without Wasting Your Time
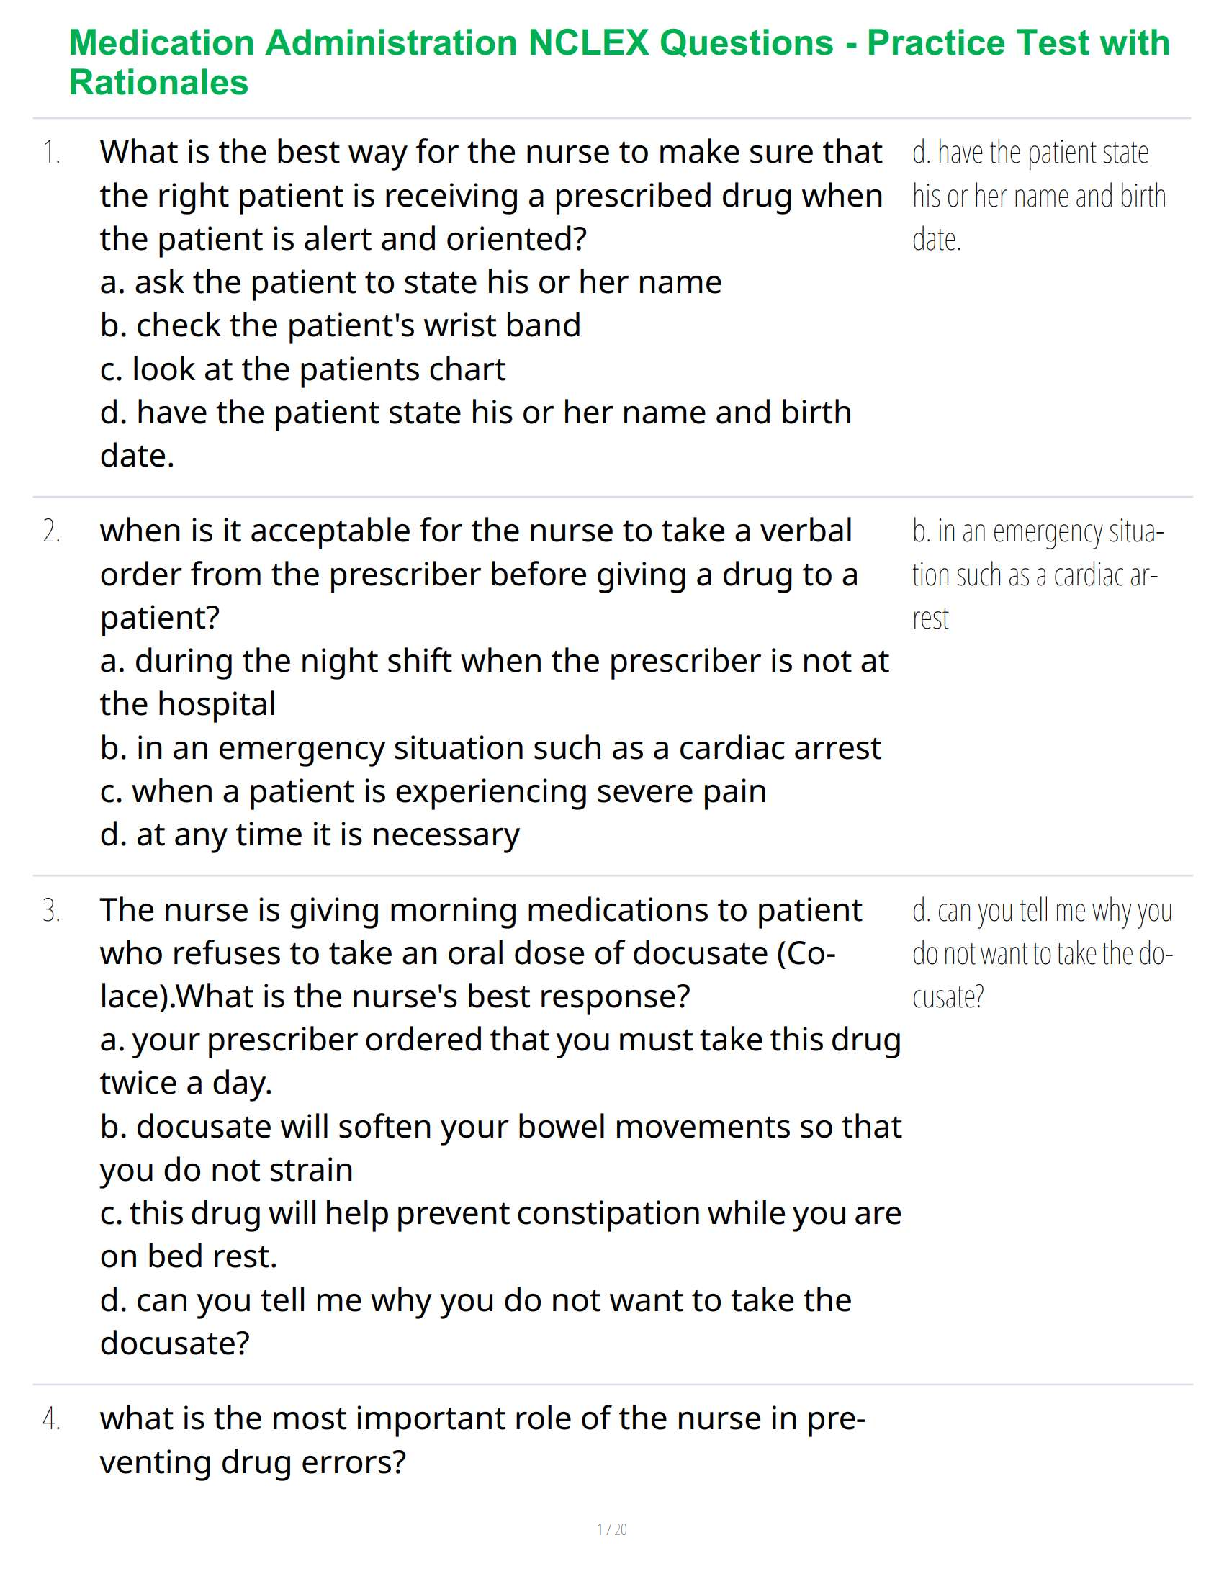
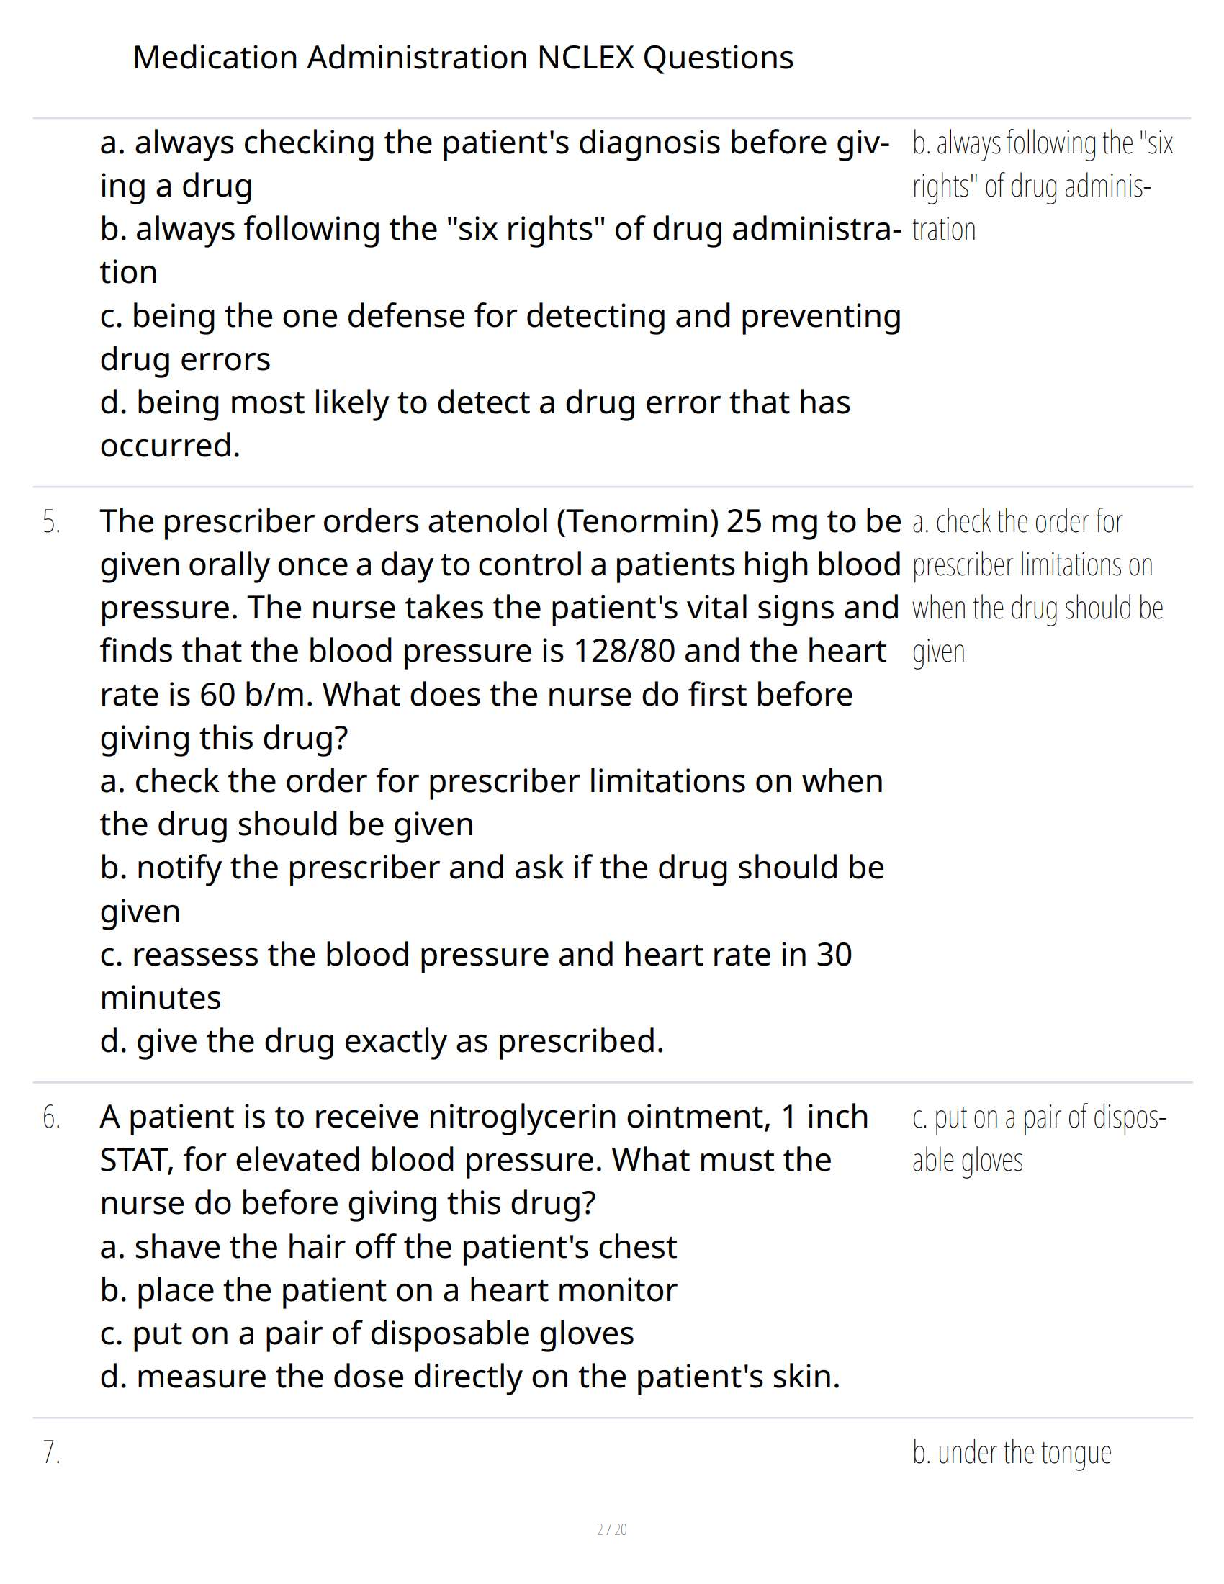
Start by answering every question without looking at the answer key. Write down your reasoning on paper for each one, even if you think you know the right answer. This forces you to engage the decision-making process rather than just matching keywords to answers. When you check your work, don't just note whether you were right or wrong. Read the explanation for every single question, especially the ones you got correct. You'll often find your reasoning was flawed even though your answer happened to be right. Here is something most prep materials won't tell you: questions about the "five rights" of medication administration — right patient, right drug, right dose, right route, right time — are rarely the hardest questions on the exam. The ones that actually sink people are the situational judgment questions where two of the five rights create a conflict. For example, a prescribed dose falls outside the recommended range per package insert but the physician insists on it. The test wants you to identify the nurse's next action, and the wrong answer choices are designed to look morally reasonable while being legally dangerous. I ran into this exact scenario during my own competency review. The practice question described a pediatric patient where the ordered dose was borderline high but still within an accepted off-label range documented in the hospital formulary. The answer choices included calling the pharmacist, administering as ordered, and contacting the provider. The trap was that calling the pharmacist first seems proactive but actually delays clarifying the order when the order itself may already be legitimate. The correct action was to verify the order directly with the prescribing provider before involving other parties. I got that wrong on my first practice run because I had memorized a protocol that worked in one hospital but not in the testing scenario.
Common Pitfalls That Have Nothing to Do With Pharmacy Knowledge
Time pressure is the biggest factor most people underestimate. A real medication administration exam often gives you 90 to 120 questions in two hours. That is roughly one minute per question. When you are doing dosage calculations under that kind of pressure, rounding errors compound fast. I have seen competent nurses fail these exams because they spent four minutes on a complex IV drip calculation and then rushed through ten pharmacology questions at the end, missing straightforward drug class identifications they already knew cold. Another pitfall is overthinking anti-emetics and drug interactions. Exam writers love to put a second medication in the question stem that is clinically relevant but distractor-level important. If a patient is on warfarin and the question asks about administering a new antibiotic, the interaction matters, but only if the question specifically asks about the antibiotic's effect on INR. If the question is simply asking about administration technique, circling back to the drug interaction is a waste of mental energy and time. The practical workaround I developed was to read the actual question sentence first, before the clinical vignette. Most people read the paragraph describing the patient and then the question at the bottom. By reading the question first, you know exactly what information you need to extract from the vignette instead of processing everything passively. This cut my question completion time from about ninety seconds to roughly forty-five seconds per item after a couple weeks of practice.
Get the Full Details

Finding a Med Administration Practice Test That Isn't Useless
The resources worth using are those published by the major nursing exam prep companies or state board of nursing organizations. Free practice tests from random websites often have outdated content, incorrect answers, or questions written by people who have never taken the actual exam. The fee-based versions from established publishers are worth the cost because the questions undergo psychometric review and have verified answer keys with explanations tied to current guidelines. Most commercial prep platforms have a free trial or a sample question bank. Use that sample set to evaluate the quality before committing any money. Check three things: are the explanations detailed enough to teach you something, do the questions match the format and difficulty of your target exam, and are the dosage calculations realistic rather than clean round numbers that never occur in practice. One resource I found useful was the practice test section available through the National Council of State Boards of Nursing website. It is not free, but the questions reflect the actual testing philosophy better than anything I found elsewhere. The HESI and Saunders question banks are also industry standards for a reason. They are expensive, and you do not need both, but picking one and doing every question twice beats buying three cheap test banks and finishing none of them.
The Honest Limitations
No practice test, regardless of quality, can replicate the pressure of an actual clinical medication pass. The cognitive load of walking into a room, verifying an identity wristband, scanning a barcode, preparing the med, documenting it, and monitoring for reactions in real time is fundamentally different from answering multiple-choice questions in a quiet room. If your program or employer requires a hands-on competency, practicing with written tests alone will leave gaps. You need to combine the written practice with actual skill check-offs on IV pumps, insulin syringes, and medication preparation trays. Practice tests also cannot account for institutional policy variations. What your textbook says about double-checking controlled substances may differ from your hospital's actual policy. During my own review, I learned that the testing standard and my workplace standard for opioid verification were subtly different, and that difference showed up in a handful of questions. If you are preparing for a specific facility's competency exam, ask a coworker who recently passed what their particular policy deviations are and adjust your study approach accordingly. The most reliable approach combines a reputable question bank, timed practice sessions that simulate exam conditions, and a review of your institution's specific medication administration policy handbook. That combination covers the test format, the time management skills, and the real-world procedural details that separate a passing score from a retake.