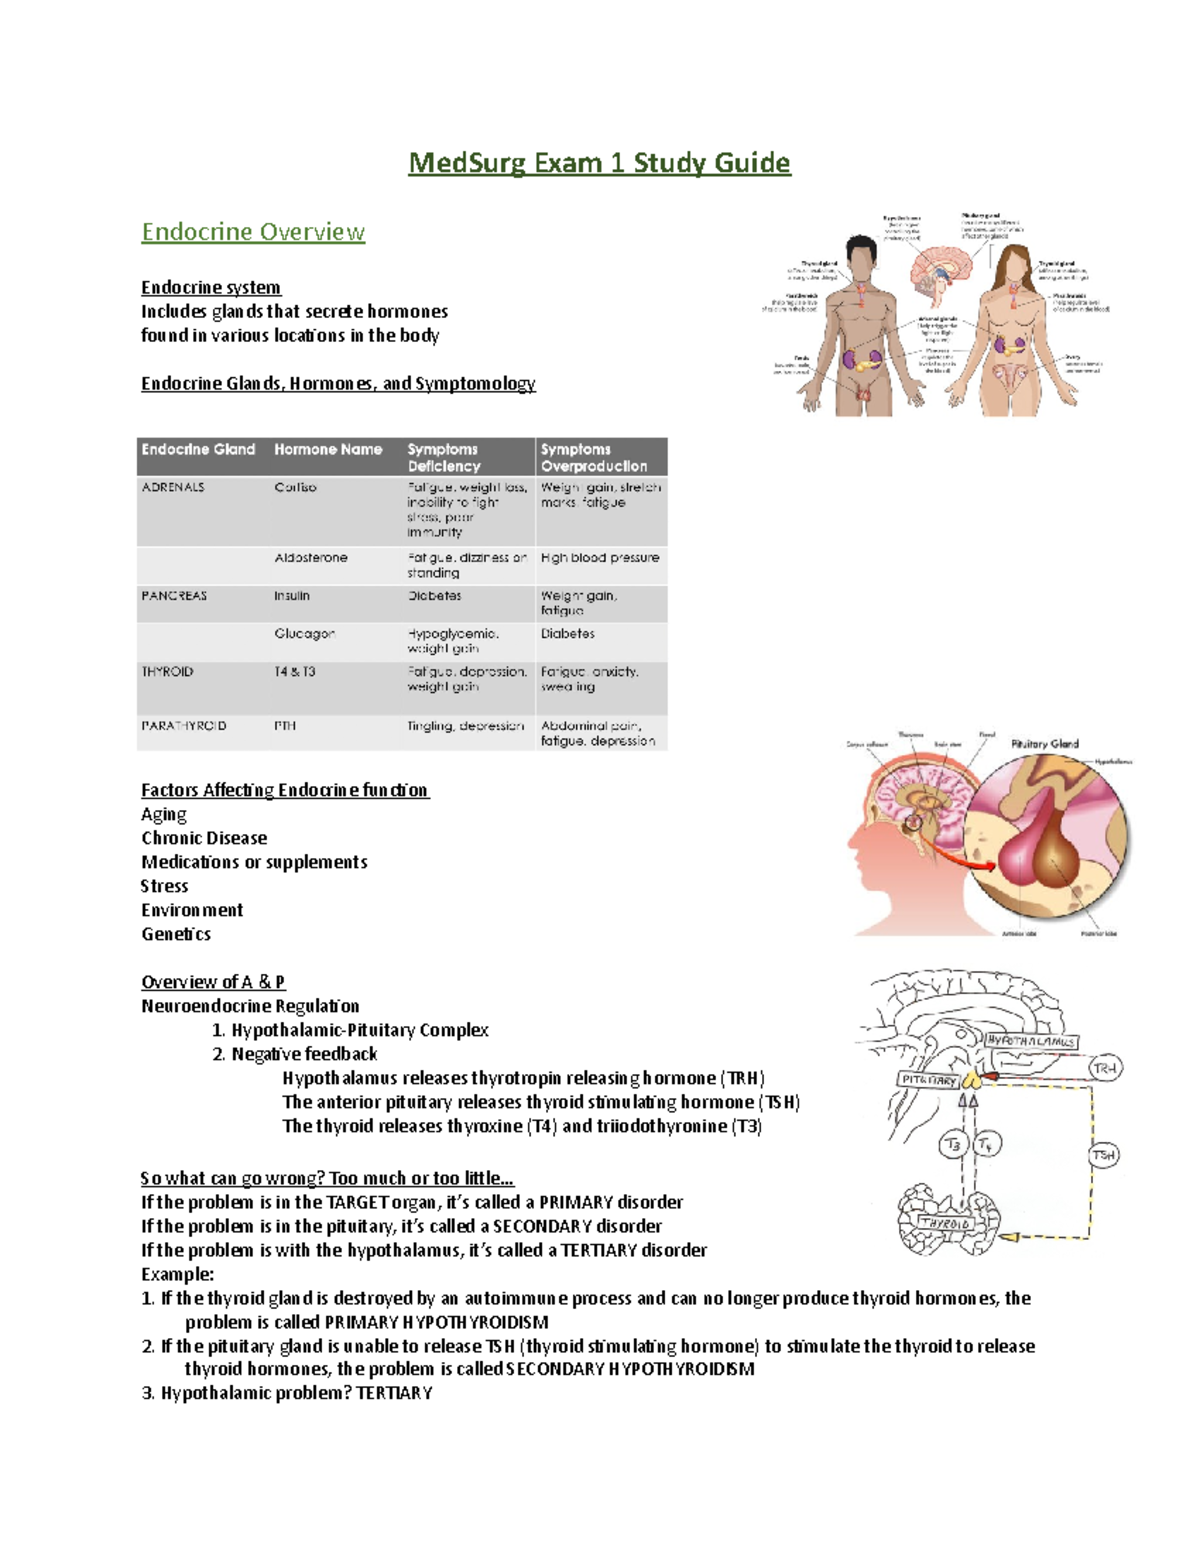
Why Med Surg 1 Study Guide Materials Matter More Than You Think
Most nursing students treat Med Surg as this massive wall of information they need to cram before every exam. That approach works okay for a few topics, but it falls apart when you hit the integrated cases that show up on final exams. A proper Med Surg 1 Study Guide helps you organize the content so you are actually recalling it under pressure instead of recognizing it passively. I built mine during my first semester by combining three things: lecture notes condensed to one page per system, NCLEX-style question banks filtered by topic, and a self-made flowchart for common disease processes. The result was a document about 40 pages that covered everything I needed without the noise.
How to Build a Med Surg 1 Study Guide That Actually Works
Start by listing every disease process your professor covered. Not every one, just the high-yield ones. Things like heart failure, COPD exacerbation, DKA and HHS, post-op complications, stroke, MI, and sepsis. These show up constantly across questions and clinicals. If your syllabus had them, they belong in the guide. For each condition, I use a consistent format. Pathophysiology in three sentences. Key lab values and what they mean. Three to five medications with their mechanism and nursing considerations. Expected assessment findings. And one red-flag symptom that means call the provider now. This keeps everything in one place instead of jumping between textbook chapters. Here is something people miss. Medications are where most students lose points. Not because they do not know the drug names, but because they confuse the priority nursing interventions. For example, with furosemide you need to check potassium and monitor for ototoxicity. With enalapril you monitor blood pressure and watch for that first-dose hypotension. Writing these separately under each disease process helps you connect the pathophysiology to the treatment.
Common Pitfalls in Med Surg 1 Study Guide Creation
The biggest mistake I see is turning the study guide into a textbook summary. Copying entire sections from your nursing drug handbook or pathophysiology text creates a document you will never read again. Every line in your guide should be something you wrote yourself in your own words. If you can explain it without looking at the source material, it belongs there. If you cannot, you need to figure it out before adding it. Another issue is not practicing with questions alongside the content. A Med Surg 1 Study Guide that is only reference material is incomplete. You need to pair it with active recall. After you finish a section, close the guide and answer ten practice questions on that topic. Then open the guide and check what you got wrong. That gap is where the actual learning happens. I ran into a specific problem during my second semester when I was trying to integrate electrolyte imbalances into my study guide. Potassium and magnesium abnormalities appear in almost every case study, but they were scattered across different sections of my notes. I ended up making a separate two-page insert that mapped each electrolyte to its normal range, ECG changes, symptoms, and replacement protocols. That insert became the most referenced part of my entire guide. I wish I had built that integration from the start instead of retrofitting it later.
Get the Full Details

What to Include for Maximum Retention
Your study guide should cover assessment frameworks, medication priorities, lab value interpretation, and common clinical scenarios. Use tables for lab values. Use bullet points for medications. Use short paragraphs for pathophysiology. Do not write essays inside a study guide. The goal is quick retrieval under test conditions, not comprehensive reading. Include a section on prioritization frameworks. Nassu order, ABCs, acute versus chronic. These come up in almost every exam question and they are easy to lose track of when you are tired. Having them written out in plain language takes about thirty seconds to review and can save you three minutes per question during a timed exam. For the Med Surg 1 Study Guide you build, I recommend keeping it to no more than fifty pages. Anything longer and you will not use it consistently. The compression process itself is where the learning happens. You are forcing yourself to decide what matters and what does not. That decision-making is the skill that gets you through the exam and into clinical.
Limitations You Should Know About
A study guide is not a substitute for understanding the underlying physiology. If you memorize without comprehending, you will struggle when a question presents a variation you have not seen before. The guide is a tool for organization and rapid review, not a crutch for avoidance of deep learning. Also, study guides become outdated if your program changes its focus. Some courses emphasize community health more, others lean harder into acute care. Adjust your guide to match what your specific program and instructor test on. Do not assume a guide you find online or receive from a previous student will align with your current curriculum. If you want a downloadable template to start with, search for the Med Surg 1 Study Guide template from your nursing program's resource page or the academic support center at your school. Those tend to match your course objectives better than generic versions found online.
Final Thoughts on Using This Material
The guide I described above saved me roughly two weeks of study time over the semester. Not because it contained more information than my textbook, but because it contained only the information I needed and it was organized for quick access. That is the real advantage. Speed of retrieval on exam day comes from structure, not from volume of content reviewed. Build it early. Revise it after each exam based on what you missed. Keep it updated through the end of the term. And use it actively, not passively. That is the difference between passing Med Surg 1 and doing well in it.




