Medical And Dental Space Planning in Practice
Most medical and dental offices I've looked at have been designed backward. Someone picks furniture, then figures out where the walls should go, then argues with code enforcement about it later. The whole thing takes two to three months longer than it should, and the final layout still has a chair in the middle of a walkway. It's not dramatic, it's just how it usually happens when someone treats space planning as an afterthought rather than the foundation. Space planning for medical and dental facilities is the process of determining where every wall, door, piece of equipment, and workflow path goes before any construction starts. You map patient flow, clinical zones, support areas, and regulatory requirements into a coherent floor plan. That's the definition. Here's what it actually involves.
The Core Components of Medical And Dental Space Planning
You need to account for four main categories. Clinical spaces are your operatory rooms, treatment chairs, imaging areas, sterilization, and any procedure rooms. Support spaces include storage, staff break rooms, medical supply closets, and waste handling. Patient circulation covers the front desk, waiting area, corridors, and accessibility routes. Then there's the infrastructure zone where mechanical rooms, HVAC units, electrical panels, and data racks live. Everyone focuses on the clinical spaces because that's what matters to the operator. The support and infrastructure zones are where projects lose time and money. For a typical general dental practice, you're looking at roughly 1,200 to 2,500 square feet per operatory depending on the region and whether you're doing sedation work. A standard single-operator dental room runs about 150 to 200 square feet minimum to clear ADA and OSHA requirements. That includes the chair footprint, operator stool arc, equipment carts, and the clear floor space needed for a wheelchair to turn around. People who skip the turn radius requirement come back to reconfigure things six months in, which costs more than getting it right the first time. Medical offices follow a different density curve. A general practitioner exam room needs about 80 to 100 square feet minimum, and that's before you add the adjacent procedure space, storage, and handwashing station. Specialty practices like cardiology or orthopedics scale up significantly because they need procedure rooms with imaging equipment, recovery space, and higher patient turnover corridors.
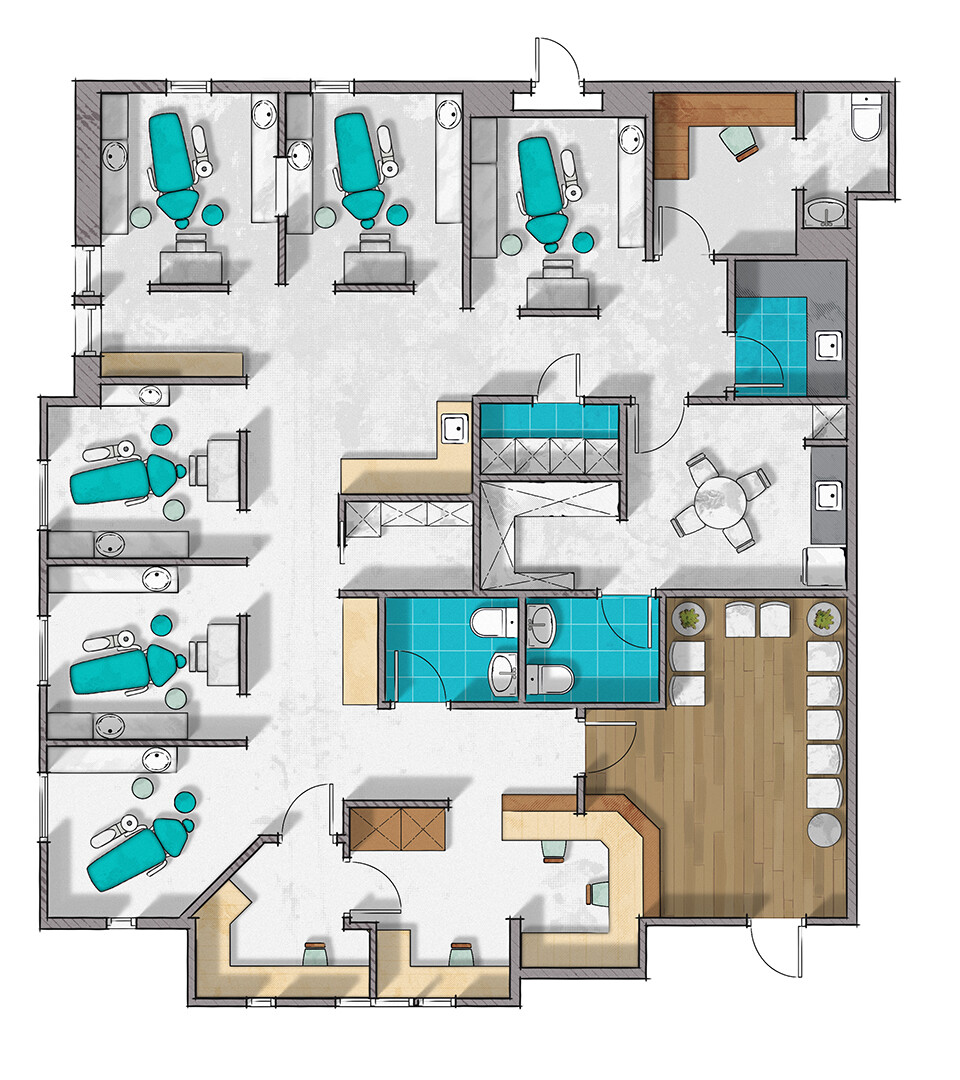
The workflow sequence matters more than most people realize. Patient arrives at reception, checks in, moves through the waiting area, gets called back through the corridor, passes the nurse station, enters the exam or operatory, then exits the same way in reverse. Every one of those transitions is a point where bottlenecks form. I've seen clinics redesign their patient flow to cut average wait times by forty percent just by moving the check-in desk and repositioning the corridor junction. No new square footage, just rearranging existing space to eliminate a U-turn in the path.
Get the Full Details

How I Actually Do a Space Plan
Start with the program. Before any drawing happens, I write out exactly what rooms and equipment are required. Not what sounds good. What is functionally necessary based on the anticipated case mix and patient volume. A periodontist who does a lot of surgical procedures needs a different sterilization and instrument turnaround area than one doing mostly non-surgical maintenance. A pediatric dental office needs wider corridors for strollers and parents. A general practitioner doing moderate sedation needs recovery space adjacent to the operatory. Get the program wrong and the rest of the process is decoration. After the program, I pull local code requirements. This varies by jurisdiction but typically involves IBC, ADA, OSHA, and state dental or medical board regulations. Fire egress, hallway width, door swing directions, barrier-free access, and ventilation requirements for certain procedures. I don't memorize this stuff. I pull it from the current codes and cite the specific sections. This saves the project from a costly change order later when the inspector flags something. Then comes the bubble diagram phase. You sketch rough overlapping circles for each functional zone and draw arrows showing how they connect. Patient flow, staff flow, supply flow, waste flow. These don't need to be precise. They need to reveal conflicts early. If the dirty utility room needs to be next to the sterilization area but the bubble diagram puts it across the clinic, you catch that now instead of during construction. I usually spend two to four hours on bubble diagrams for a standard office and four to eight hours for larger multi-provider practices.
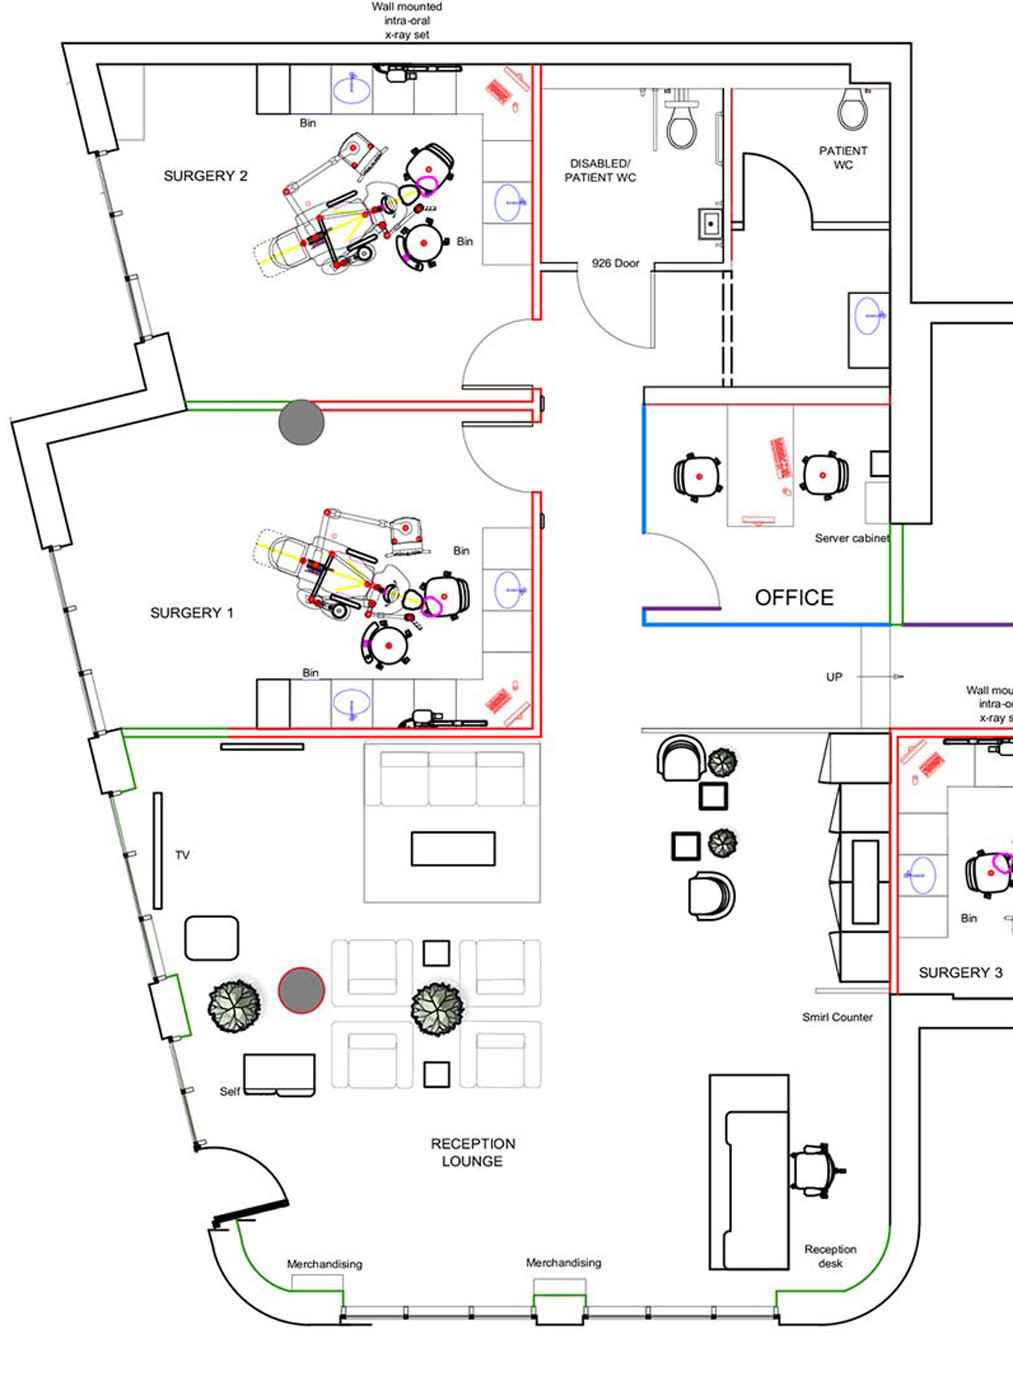
From there, I move to a scaled floor plan using CAD or a dedicated space planning tool. Revit is common for larger projects. For smaller dental offices, Vectorworks or even SketchUp works fine if you know how to set up the dimensioning correctly. The key is testing each room against the minimum square footage and equipment clearance requirements before locking anything down. I place every piece of equipment at full scale, including the chair in its most extended position, the mobile X-ray unit, the light, the computer cart, and the operator's stool with full range of motion. Then I verify clearances. This step usually catches two or three issues per project that would have been expensive fixes otherwise. One specific problem I ran into recently involved a dental office in a converted retail space. The existing structure had a load-bearing wall running through the middle of what should have been the operatory cluster. The architect wanted to knock it out. Local structural requirements made that impractical without a steel beam that would have dropped the ceiling twelve inches, violating the minimum headroom for an operatory with overhead equipment. So we rearranged the entire floor plan to work around the wall instead of fighting it. The operatories ended up on either side of the wall with a shared corridor running through the gap, which actually created a better workflow because it separated the surgical side from the prophylaxis side. It took an extra two days of design work but saved about ten thousand dollars in structural modifications and kept the project on schedule.
Common Mistakes That Cost Time and Money
The biggest mistake is designing for today's equipment instead of tomorrow's. A dental chair from twenty years ago is smaller than a modern unit. People building new offices often measure for the old chair and then realize the new equipment doesn't fit the doorways, the cabinetry, or the power and data outlets aren't positioned correctly. I always specify minimum clearances based on current major manufacturer specifications and leave a twenty percent buffer for future equipment upgrades. Another mistake is neglecting the acoustic relationship between spaces. A operatory next to a reception waiting area with thin partition walls is a complaint machine. Dental drills and patient conversations carry through standard gypsum board partitions. Use sound-rated assemblies where noise transfer matters. It adds maybe five to eight dollars per square foot to the partition cost but eliminates a category of post-opening complaints that tends to compound over time. People also underbuild the sterilization area. The CDC and state boards have specific requirements for sterile instrument flow that can't be compromised. Separation of clean and dirty pathways, adequate sink placement, proper surface materials, and ventilation rates. A poorly planned sterilization area causes staff to take shortcuts that create compliance risks. I've seen clinics reconfigure their central sterile processing twice because the first layout didn't meet inspection standards. That's three months of downtime and tens of thousands in rework.

ADA compliance is non-negotiable and it's where most small office plans stumble. Door widths, turning radiuses, counter heights, restroom accessibility, signage, and parking proximity. The 2010 ADA Standards are the baseline for most jurisdictions. An accessibility consultant reviewing your plans before construction typically costs two to four thousand dollars and prevents far more expensive corrections afterward. Skip it and you're gambling with a violation that could affect your ability to open.
When Space Planning Works and When It Doesn't
This approach works well for greenfield construction, full renovations, and tenant improvements up to about ten thousand square feet. For those project sizes, thorough space planning typically takes two to six weeks depending on complexity and client response time. The design phase alone usually runs four to eight weeks once the program is locked. It breaks down in situations where the building shell is extremely constrained and the required program can't physically fit. If you need six operatories and the available footprint only accommodates four with code-compliant clearances, no amount of planning will solve that. The solution is either expanding the footprint through annex construction, relocating to a larger space, or reducing the program scope. I've had clients insist the math would work out, and it never does. The numbers are the numbers. Another scenario where this method hits limits is multi-tenanted buildings where you don't control the structural grid, column placement, or mechanical risers. You can design around those constraints, but the flexibility is reduced. In those cases, I recommend getting a preliminary site assessment from a contractor who's familiar with the building before investing heavily in detailed design. That assessment usually runs one to two days and costs a few thousand dollars, but it can save you from designing a floor plan that turns out to be impossible to execute.
Software tools have improved significantly. Dedicated medical office planning software like ArchiCAD with healthcare libraries, or platform-specific solutions from companies like PlanGrid and Procore, can automate some of the code-checking process. But the software doesn't replace the judgment call about workflow and practical usability. A perfectly code-compliant plan that makes no operational sense is worse than a slightly non-standard plan that works well in practice. The best space plans I've produced were the ones where I spent equal time thinking about how the staff would move through the space as I did about meeting the dimensional requirements. The outcome of good space planning is measurable. Office layouts that get this right typically see thirty to fifty percent faster patient turnover compared to poorly planned counterparts, because staff spend less time walking and more time working. Construction change orders drop by roughly sixty percent when the space plan is thoroughly vetted before breaking ground. And staff satisfaction scores improve because the physical environment reduces friction in daily tasks. These aren't theoretical improvements. They show up in practice management reports and occupancy studies I've reviewed across multiple projects. Get the program right, respect the codes, test the plan at full scale before it goes to construction, and budget for an accessibility review. Everything else is refinement.