How to Actually Train for EMT Medical Assessments
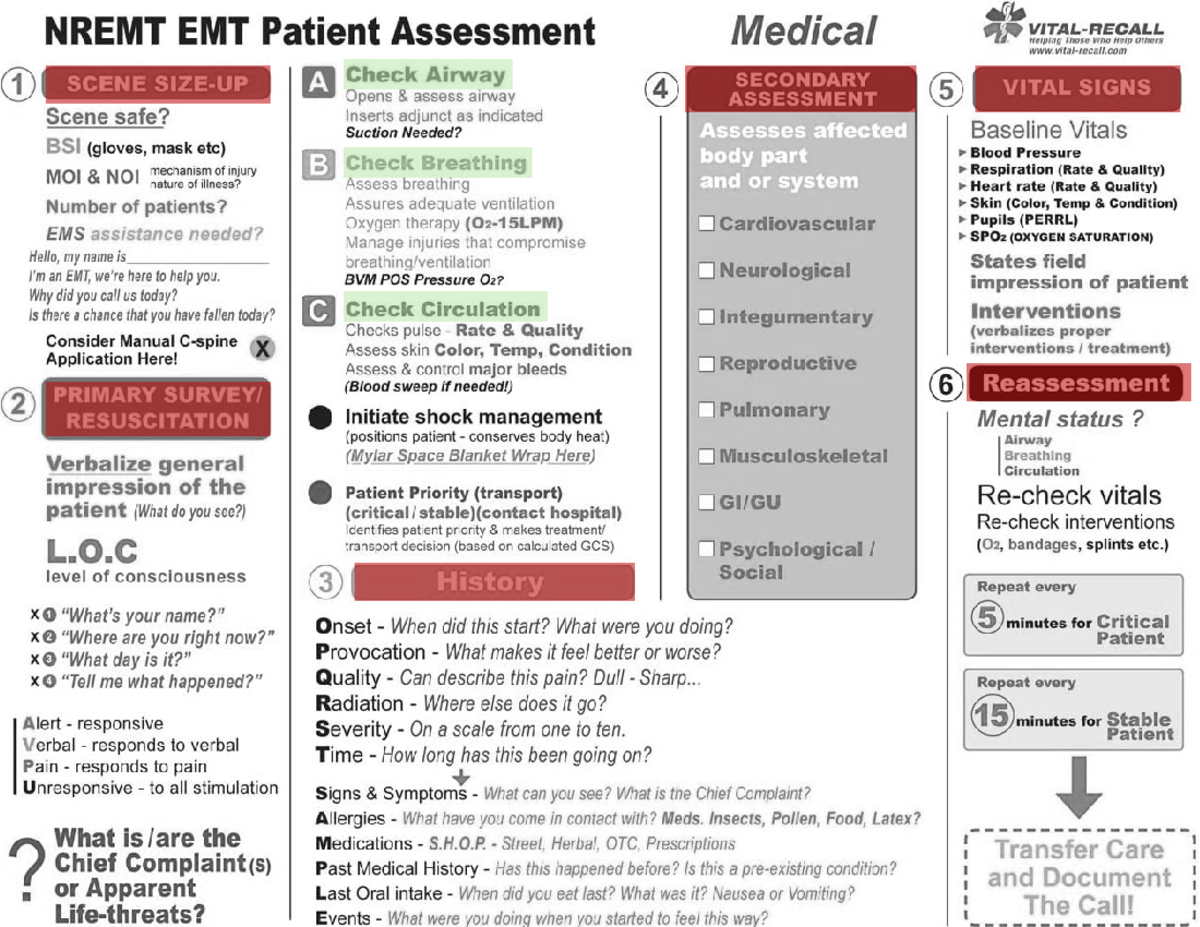
Most EMT programs spend about forty hours covering the fundamentals of patient assessment. The skill sits somewhere between structured textbook knowledge and raw instinct. You learn the steps until they become automatic, then you realize how much depends on doing them without thinking when someone is actively crashing in front of you. I have been through this cycle more times than I care to count. The core medical assessment follows a fixed path. You start with scene size-up, move through primary assessment, gather a sample history, perform a focused secondary exam, and finish with reassessment. On paper this looks clean. In practice the timeline collapses when the patient deteriorates and you find yourself jumping back and forth between steps. I once ran into a problem during a high-fidelity simulation where the patient had simultaneous chest pain and sudden neurological decline. The scenario was designed to test prioritization, but my training kicked in too rigidly. I kept trying to finish the cardiac assessment before moving to the neuro check, and the scenario facilitator kept pressing the urgency clock. What actually worked was calling out my concern over the radio mid-assessment and telling the receiving hospital I was changing my priority to stroke protocol while I was still in the room. That moved the whole chain faster than any textbook decision tree would have.
That moment taught me something most programs do not emphasize enough. Medical Assessment Scenarios Emt students encounter are not really about completing boxes in order. They are about knowing which box you can skip or compress when the patient is unstable, and communicating that change before the instructor asks for it.
How to Structure Your Own Practice Sessions
You do not need a full simulation lab to build competence. A partner, a blood pressure cuff, a pulse oximeter, and a glucometer are enough for most routine scenarios. Set up a basic patient presentation, run through your primary survey, and then complicate it by having the partner introduce a new symptom every three minutes. The goal is to train yourself to update your mental model without abandoning the original assessment. I usually set a timer for twenty minutes per scenario and rotate through four types: medical complaints like chest pain and shortness of breath, altered mental status, abdominal emergencies, and mixed presentations. Each session takes about two hours including feedback. Over a semester this adds up to roughly twenty realistic patients per student, which is close to what many program simulations provide.
Get the Full Details

Common Mistakes That Show Up in Every Scenario
Beginners tend to treat the secondary assessment as a complete head-to-toe exam even when the primary complaint is obvious. This wastes time and distracts from what matters. If a patient presents with severe abdominal pain, you still do a quick secondary, but you spend most of your focused exam on the abdomen, vital signs trend, and relevant history. A full dermatological and musculoskeletal sweep is unnecessary unless something in the primary suggests a broader problem. Another frequent error is anchoring on the first impression and ignoring contradictory data. I had a student once diagnose a severe asthma attack based on wheezing alone, only to miss that the patient was developing silent chest, which is a sign of impending respiratory failure. The scenario did not even punish him for it at first. The facilitator just kept asking about oxygen saturation trends, and he finally caught it after losing three minutes of treatment time. Anchor bias is one of those cognitive traps that shows up repeatedly in EMS evaluations, and it is better to practice catching it on yourself than to learn it on a real call.
Using Checklists Without Becoming a Robot
Checklists exist because human memory fails under stress. The National Registry and most state protocols rely on structured assessment tools precisely for this reason. You should use them, but you should also understand when deviating from the list is the right call. A normal primary assessment checklist will have you checking airway, breathing, circulation, disability, and exposure in sequence. In a trauma scenario with obvious catastrophic hemorrhage, you address the bleeding before you finish checking pupils. The checklist is a memory aid, not a command structure. I keep a laminated one-page reference card for rapid medical assessments. It covers the key history elements, common differentials by chief complaint, and the critical action thresholds for calling for additional resources. It takes me about five seconds to glance at it during a scenario, and it prevents me from forgetting to ask about anticoagulant use or insulin dependence when those details change the entire management plan.
What to Do When the Scenario Goes Completely Off the Rails
Sometimes the patient code, sometimes the equipment fails, and sometimes the scenario giver introduces a complication that makes no logical sense given the initial presentation. The worst thing you can do is freeze and wait for instructions. The best response is to declare your changed assessment to the imaginary receiving facility, document what you observed, and proceed with the next most appropriate intervention based on current data. One time during a practice scenario the simulated patient went into ventricular fibrillation with no warning. I had spent three minutes working a cardiac arrest algorithm and then realized the shock was not being delivered because I had forgotten to attach the pads during the primary assessment. The mistake was mine, not the scenario's. I restarted the rhythm management, called for the AED explicitly this time, and delivered the shock. The feedback I got afterwards was useful because it was specific: pad placement during primary survey is non-negotiable even when the patient seems stable at first.

Download and Self-Study Resources
There are several free resources available online for EMT assessment practice. The American Red Cross publishes sample scenario sheets that cover common medical presentations. State EMS offices often post protocol references that include assessment algorithms. I recommend downloading a few and printing them out rather than studying from a screen, because you will likely be using paper references during actual exams and real calls. Some programs also share scenario banks through their LMS platforms. If yours does, download those files immediately and practice with them before the skill station exams. The questions tend to repeat in structure even when the specific presentation changes, so familiarity with the format itself reduces anxiety more than memorizing individual answers ever could.
Preparing for the Skill Portion of the NREMT
The practical exam tests your ability to perform a coherent assessment under time pressure, not your ability to recite every detail perfectly. Examiners are watching whether you establish patient contact, obtain consent, perform a primary survey, identify the chief complaint, and act on your findings in a logical sequence. Gaps in communication matter more than missing a single vital sign number. I practiced the cardiac arrest scenario at least twelve times before my NREMT skill test. The repetition was tedious, but it made the sequence feel automatic during the actual exam. When the examiner told me the patient was unresponsive and not breathing normally, I moved through the steps without hesitation. That level of automaticity only comes from deliberate, repeated practice, not from reading about the procedure once or twice.
Final Thoughts on Building Real Competence
Medical Assessment Scenarios Emt training works best when you treat each scenario as a problem-solving exercise rather than a performance. The patient in front of you does not care whether you followed every step of the textbook, and neither should your examiner. What matters is whether you recognized the problem, prioritized the right interventions, and communicated clearly. Focus on those outcomes and the details will follow.