Why Medical Assistant Performance Reviews Usually Feel Like a Chore
Most clinics handle medical assistant evaluations the same way they handle inventory counts—once a year, in a rush, with a paper form that nobody actually reads afterward. The result is a document that looks thorough on the surface but tells you almost nothing about whether the person standing next to you in the exam room is actually competent. A well-constructed Medical Assistant Performance Review Competency Checklist changes that dynamic, but only if you build it around how the job actually works instead of how it looks on an org chart. I spent years watching clinic managers hand out printed competency checklists on a clipboard and ask MAs to self-score before the review meeting. It produced tidy paperwork and zero useful data. The breakthrough came when we stopped treating the checklist as a grading tool and started treating it as an observation protocol. That shift changed everything about how reviews played out.
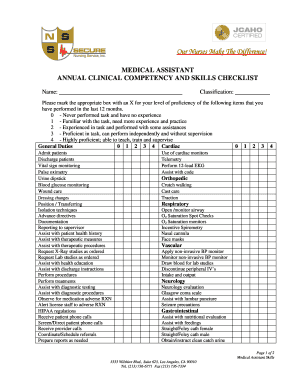
Medical Assistant Performance Review Competency Checklist: What Actually Goes on It
The checklist itself breaks into three domains: clinical skills, interpersonal and communication competence, and administrative reliability. Each domain contains sub-items that map directly to daily responsibilities, not textbook descriptions. Here is how I structured mine after a couple of false starts. Vital signs acquisition, phlebotomy, EKG setup and operation, speciman labeling, injection administration, immunizations, point-of-care testing, wound care, medication reconciliation support, and infection control protocols. Each item requires a direct observation, not a signature from whoever happened to be around that day. Patient intake rapport, explaining procedures in plain language, de-escalating anxious patients, communicating critical lab values to providers promptly, respecting HIPAA boundaries in shared workspaces, and documenting encounters accurately and in real time. These are the skills that separate an MA who keeps patients coming back from one who processes them efficiently but leaves them feeling handled rather than cared for.
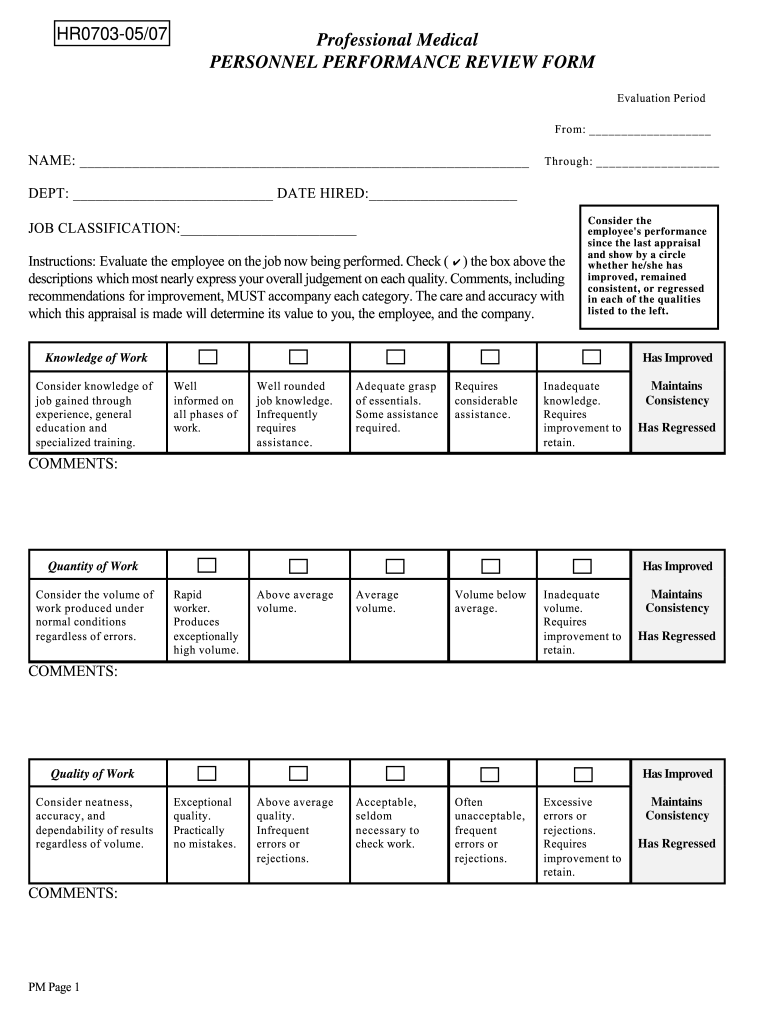
Appointment scheduling accuracy, prior authorization follow-through, EHR charting timeliness, supply restocking cycles, equipment maintenance logs, and coverage reliability. The administrative side rarely makes it onto performance reviews, but it is where most workflow breakdowns originate. The evaluation happens in three phases spread across the review period. Phase one is pre-review self-assessment where the MA identifies areas of confidence and concern. Phase two is direct observation during normal shifts. I usually schedule two to three observation sessions, each lasting twenty to forty minutes depending on the procedure being assessed. Phase three is the summary meeting where findings are discussed and development goals are set together rather than handed down. Scoring uses a four-point scale. One means no observed competence. Two means observed with prompting or assistance. Three means independently competent. Four means consistently exemplary and able to train others. Anything below three triggers a documented improvement plan with a sixty-day re-evaluation timeline.
Get the Full Details
Here is the part most people get wrong. You do not walk into an observation session and grade everything you see. You pick two or three focused competencies per session. Trying to assess twelve items in one shift produces shallow notes and exhausted evaluators. A focused observation takes about fifteen minutes of note-taking and produces more reliable data than a thirty-minute scan of everything.
A Real Problem I Ran Into and How I Fixed It
Years ago I reviewed an MA who scored perfect on the phlebotomy section. Draw after draw, clean sticks, proper labeling, efficient turnover. Then a parent brought in a screaming child who needed a CBC and the MA froze. Not incompetence, exactly. The checklist had no item for pediatric behavioral management during invasive procedures. The skill existed but sat outside the documented framework. My workaround was simple. I added a pediatric and anxious patient management sub-item under the clinical competencies, and I also created an observation scenario for high-stress encounters. Within a month the same MA who failed that scenario was coaching a newer hire on how to position a pediatric patient and talk the parent through the process. The checklist had finally captured something the job actually required.
Counter-Intuitive Things Beginners Miss
First, ranking MAs by overall score is usually worse than ranking them by individual competency. A strong phlebotomist who struggles with prior authorizations will look average on an aggregate score and get overlooked for targeted training that could fix the real problem. Competency-level analysis prevents that. Second, the most dangerous rating pattern is the three-cluster effect. Reviewers avoid ones and fours, so scores bunch around the middle. This masks both truly deficient performance and genuinely exceptional performance. If your data shows sixty percent of your MAs scoring a three, your rating system is broken, not your staff. Third, patient comments during the review period matter more than checklist scores in several cases. I once had an MA who checked every box flawlessly but had a consistent thread in patient feedback about appearing rushed and dismissive. The checklist alone would have recommended a promotion. The qualitative data prevented that mistake.
Limitations and When This Tool Fails
A competency checklist cannot assess judgment. An MA might draw blood perfectly and document everything correctly but still miss a subtle sign that the patient is about to pass out because protocol does not require that assessment. Checklists measure observable behaviors, not clinical intuition. Pair this tool with periodic case-based discussions to cover the gap. The checklist also breaks down in high-turnover environments. If half your MAs are new hires every quarter, the annual review cycle becomes irrelevant because the person you are evaluating six months later is not the person you evaluated at the start. In those settings, quarterly micro-assessments replace the annual event entirely. Some smaller clinics attempt to use this checklist without dedicated evaluation time, expecting supervisors to complete it between patient contacts. That approach produces fake data and corrodes trust. If you cannot spare sixty to ninety minutes per review session, the checklist is not the problem—your scheduling is.
An alternative worth considering alongside this checklist is a 360-degree input model where nurses, front desk staff, and patients contribute brief structured feedback during the same review period. The checklist still anchors the clinical assessment, but the added perspectives reveal blind spots that a single evaluator routinely misses.
Putting It Together
The value of a Medical Assistant Performance Review Competency Checklist depends entirely on the discipline behind its use. Filled out hastily, it is administrative theater. Used as a structured observation framework with focused sessions, direct evidence, and follow-up plans, it becomes the single most reliable tool you have for raising clinic performance. Start small, observe deliberately, and track changes over time instead of chasing a single rating.