What You Actually Need on a Medical Billing Cheat Sheet
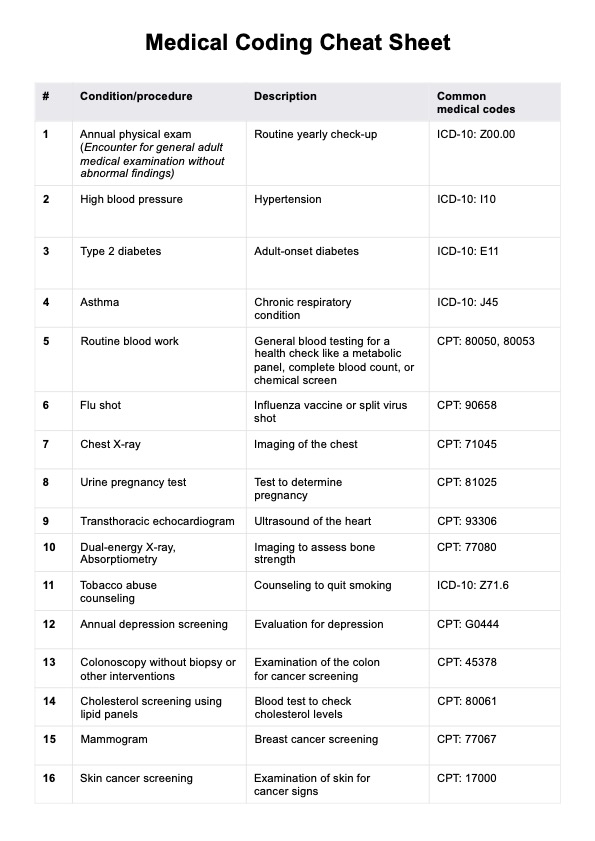
A medical billing cheat sheet is just a condensed reference that lets you look up codes, payer rules, and common pitfalls without opening three different tabs and searching through outdated PDFs. The ones I see floating around online are usually generated by AI or copied from someone else's Google Drive folder, and they miss stuff that actually matters in day-to-day work. A good one saves you time when you're in the middle of a claim and need to remember whether a certain modifier goes before or after the revenue code for your specific payer. Here's what I keep pinned to my monitor at all times. It's not fancy, but it covers the stuff I look up every single shift. ICD-10-CM sections you need to know cold: Category-level codes (the three-character ones like K21) are where most denials start because billers submit them without enough specificity. The fourth, fifth, and sixth characters matter. For GERD, you don't submit K21.0 when the documentation doesn't clearly state esophagitis. K21.9 is the default and it gets rejected by a lot of commercial payers who have specific medical necessity requirements. Always verify the documentation supports the level of detail you're coding to.
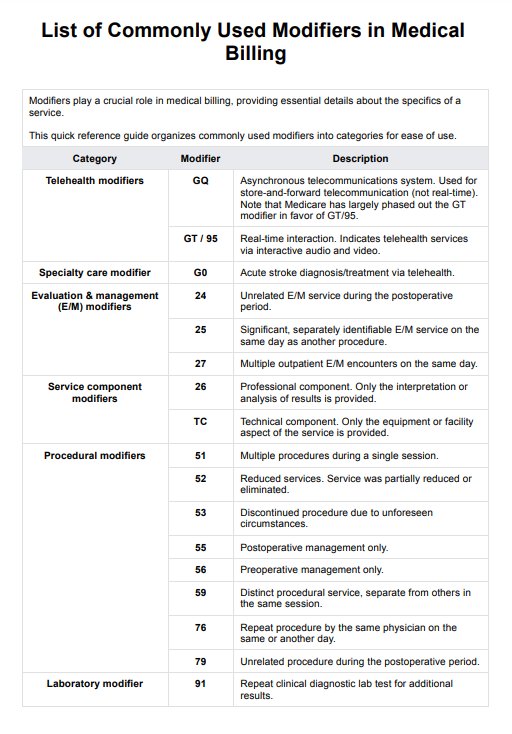
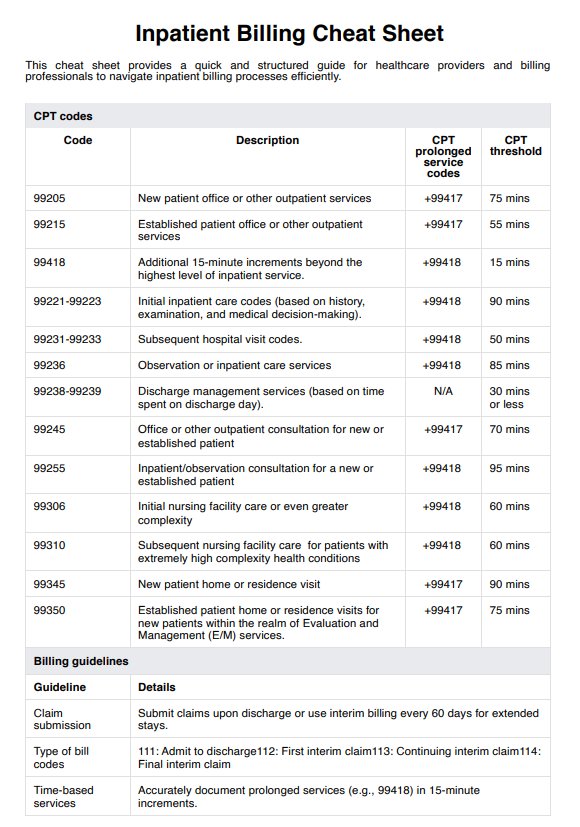
CPT modifier pairs that trigger edits: Modifier 25 with E/M codes on the same day as a procedure is the most audited combination in outpatient billing. Payers want to see that the E/M was separate and significant, not just a routine pre-op or post-op visit bundled into the global period. Modifier 59 is getting used less and less. NCCI edits catch it constantly. Use XE, XS, XP, or XO instead, and make sure the documentation explicitly states which anatomical site or distinct service justifies the separate procedure. Just writing "separate lesion" on a claim form is not enough anymore. Payer-specific prior authorization windows: This varies so much by plan that no single cheat sheet can cover it, but the ones I rely on note down the big ones: UnitedHealthcare typically requires 14 days advance notice for imaging like MRIs, Medicare Advantage plans vary wildly by county so I keep a separate tracker for those, and Blue Cross plans in my state often require authorization at the point of scheduling rather than at the time of service. Missing these by a day is the fastest way to get a clean denial that takes 60 to 90 days to reverse. Revenue code quick reference for inpatient and facility billing: Room and board is where a lot of beginners fumble. Revenue code 0200 is private room, 0210 is semi-private, 0220 is dormitory. These seem straightforward until you're billing for a patient who was upgraded mid-stay due to bed shortages. You need to bill both periods with the correct revenue codes and document the reason for the change. One hospital I worked with had a policy that the nursing staff had to fill out a room change form within 24 hours, but they rarely did. Claims would go out with the wrong revenue code for the entire stay and the adjustments ate into revenue every month.
I ran into a specific issue last year that nearly cost us a significant write-off. A patient came in for a colonoscopy with polyp removal, and the physician documented the polyps as sessile but didn't specify the size in millimeters. The standard cheat sheet approach would be to use the code for polyps under 10mm, but the internal audit found that the endoscopy report actually had the measurements in a different section that the billing team had overlooked. We submitted the claim with the lower-value code, got denied by the payer for missing documentation, and then spent three weeks chasing the physician's notes. The workaround was simple but nobody had implemented it: I created a mandatory cross-reference step where the coder had to confirm that the procedural findings matched the ICD-10 diagnosis code level of detail before the claim was queued. It added about 90 seconds per claim but eliminated that whole category of denial going forward.
Get the Full Details
How to Build One That Actually Works
Most people build cheat sheets by dumping everything they've ever seen into a spreadsheet. That approach creates a document so long that nobody references it under pressure. Start by listing the top 10 problems that cause denials in your specific practice type. For a small internal medicine clinic, those problems are usually modifier stacking, missing linking diagnoses, and expired patient insurance. For a surgery center, it's global period conflicts and incorrect place of service codes. Use a tool like Airtable or a well-structured Excel file with separate tabs for each category. Keep each entry to three lines maximum: the rule, the exception, and the source. If you can't fit it in three lines, it's too detailed for a cheat sheet and belongs in a full policy manual instead. I organize mine with hyperlinks to the official CMS guidelines, payer websites, and our internal charge description master. When a denial comes in, I search by keyword rather than scrolling. A good search function cuts lookup time from several minutes to about 30 seconds.
What Your Cheat Sheet Should Not Include
Don't include code descriptions that change annually. CPT and ICD-10 updates happen every October and January respectively. If your cheat sheet has 2023 code definitions in it, it's already wrong. Only include the structural rules and payer behavior patterns that stay consistent across code sets. Don't include payer phone numbers. Those change regularly and create a false sense of security. Instead, include the payer's URL for provider services and their preferred electronic denial resolution portal. Calling a number is slower than filing an appeal through the online system anyway. Don't include every possible modifier. Stick to the ones your specific billing environment uses. Adding modifier 76, 77, and 91 to a pediatric clinic's cheat sheet is noise. Those rarely apply. Focus on modifiers 25, 59 and its siblings, 50, 52, 53, 76, and GT for telehealth. That covers roughly 95 percent of what any non-surgical specialty needs on a daily basis.
Common Mistakes That Invalidate a Cheat Sheet
The biggest problem I see is that people treat a cheat sheet as a substitute for training. It isn't. It's a reference tool for edge cases and things you forget under stress. If your team hasn't been trained on baseline coding guidelines, a cheat sheet won't prevent downstream errors. It'll just make it faster to find the wrong answer. Another mistake is not versioning your documents. I've worked with practices that had three different versions of a cheat sheet floating around in three different departments, and each one had slightly different information about the same payer policy. That creates inconsistency in billing that auditors notice immediately. Put a version number and a revision date on every page. Review it quarterly at minimum, and do a full audit after any major payer policy change or software update. The cheat sheet approach also breaks down in highly specialized surgical practices. If you're billing complex transplant or oncology cases, the volume of exceptions exceeds what a single document can reasonably capture. In those environments, a decision tree or integrated clinical editing software does more heavy lifting than any spreadsheet ever will. A cheat sheet can supplement that, but it shouldn't be the primary tool.

Where to Get a Reliable Starting Point
There's no legitimate free download that I'd recommend as a complete solution. The CMS website offers free coding guidelines that are accurate but not formatted as a cheat sheet. Most third-party sites selling or giving away "medical billing cheat sheets" are either affiliate marketing plays or selling outdated content. The most practical approach is to start with the CMS Physician Fee Schedule lookup tool and the NCCI Policy Manual, extract the sections relevant to your practice, and build from there over time. If you want a structured starting template, the AAPC and AHIMA both offer member resources that include billing reference materials, though those require membership. For non-members, the Medicare Carrier Specific Manuals by region are freely available and surprisingly thorough for the payer-specific rules that tend to cause the most friction. The best cheat sheet is the one you actually use. If it sits unused on a shared drive, it's not helping anyone. Test it during your next denial review cycle. Note every time you wish you had the information handy, add it, and remove anything you never reference. The document should shrink over time, not grow.