The Actual Differences Between Outsourcing Medical Billing and Keeping It In-House
Most people coming into this ask the wrong question. They want to know which option is cheaper. The answer depends entirely on your patient volume and claim rejection rates. I spent seven years running billing for a mid-size orthopedic group before switching to a facility model, then brought it back in-house two years later. Here is what actually happens with each approach. A medical billing facility is a third-party company that handles your coding, claim submission, follow-up, and denial management for a monthly fee or percentage of collections. A private practice does it internally, meaning you have employees or contractors handling it directly. The structural difference seems simple but the operational impact is where things get complicated. With a facility, your claims leave your office and go through their clearinghouse connections and follow-up queues. With a private practice model, everything stays under your roof and your staff deals with payer portals directly. I found that facilities typically process claims faster because they submit 200 to 500 per day across multiple clients, giving their systems economies of scale. Your private practice might be submitting twelve claims a day. Different world entirely when it comes to catching denial patterns early.
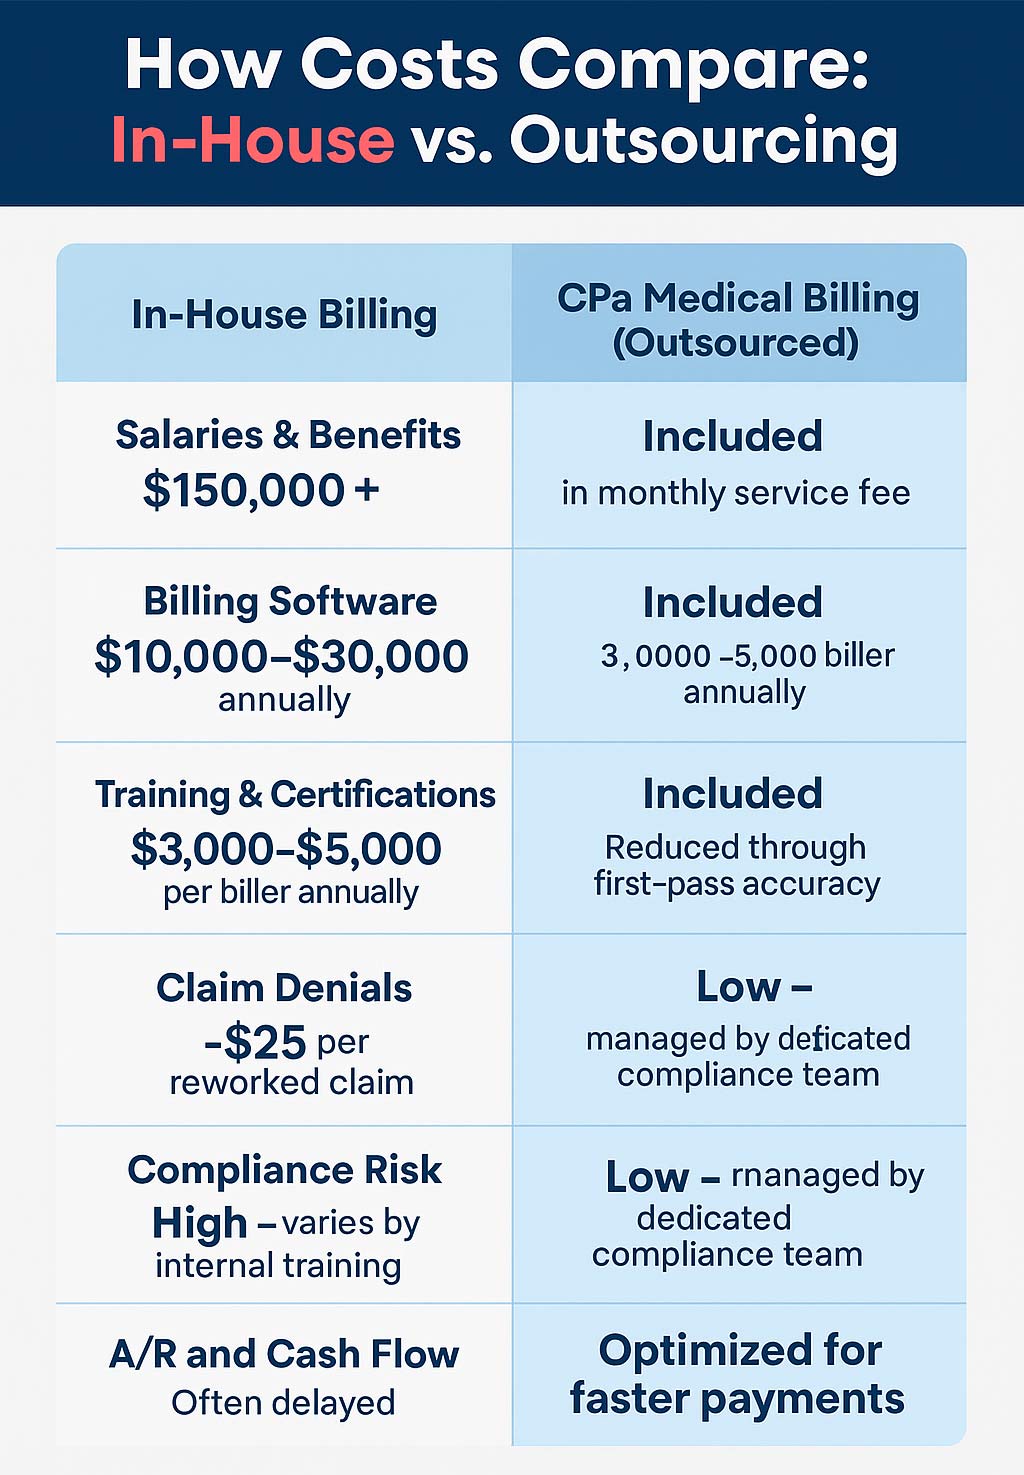
Here is the part nobody mentions upfront. Facilities usually charge between two and five percent of gross collections or a flat per-claim fee around four to eight dollars. For a small practice pulling in sixty thousand a month, that is one thousand two hundred to three thousand going out. Your private practice biller salary in the current market runs fifty to seventy thousand a year plus benefits, which adds up fast if you only have one person covering it. Two billers and the number jumps. I ran into a specific issue with a facility client last year that cost us three weeks of lost revenue. They were using outdated CCR data mapping for a regional Medicare Advantage plan that had recently changed their modifier requirements for physical therapy evaluations. The facility's system kept rejecting the modifier 25 on E/M codes with a minor procedure on the same day. They did not catch it because their workflow assumed the payer rules were static. Meanwhile, our internal team at the previous practice would have flagged this within forty-eight hours through our own chart audits. We switched billing back in-house and the denial rate dropped from eight point three percent to four point one percent over the next quarter. The workaround eventually involved rebuilding their payer file mapping for that specific MA plan, but it took a manual override and a direct conversation with their senior account manager. Facilities are not inherently bad at this. They just move too fast across too many clients to notice when a niche payer changes their rules without sending a formal notice. Payer portals update constantly and the facilities often rely on automated feeds that lag by a billing cycle or two.
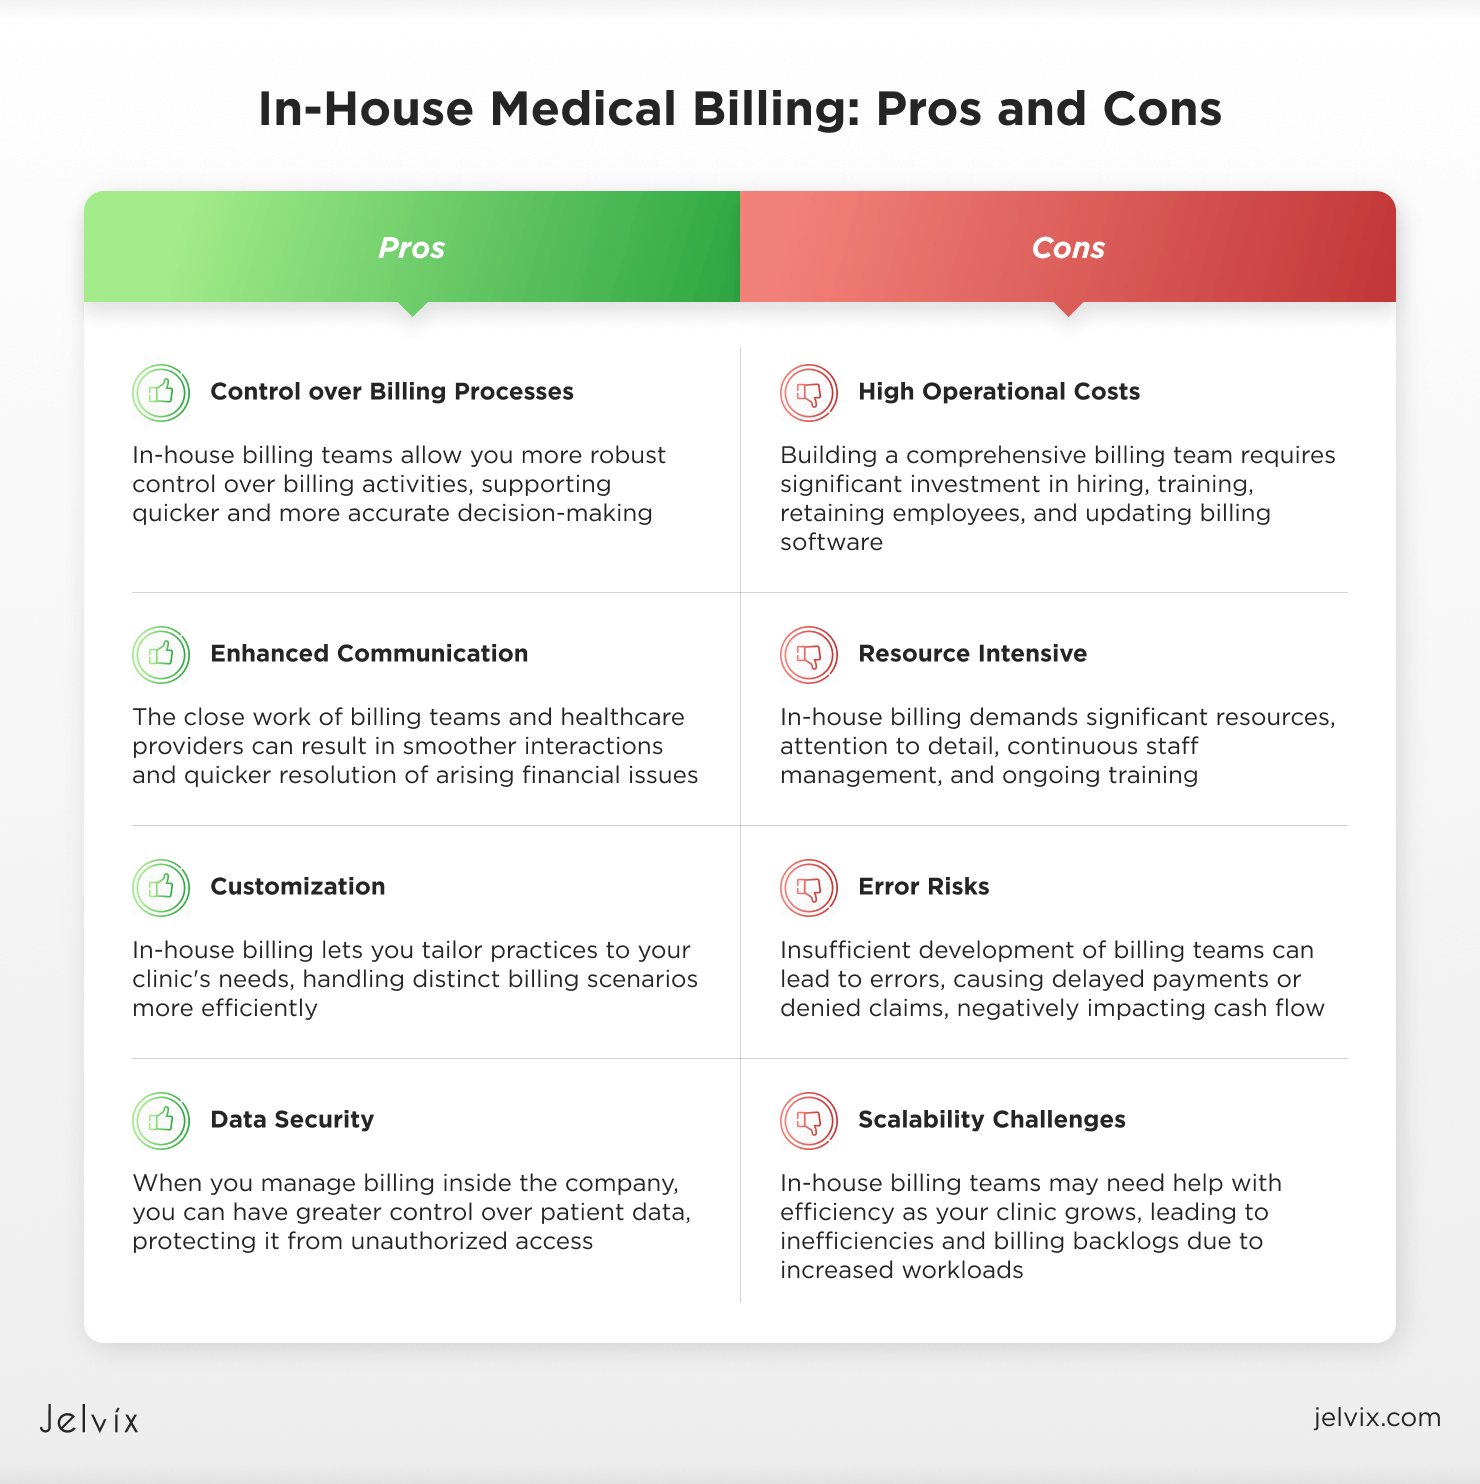
Private practice billing has its own failure mode that people gloss over. Staff turnover. When your sole biller quits, you are scrambling to hire and train someone who knows your specific payer mix and your clinicians' preferences. I watched a group lose six weeks of revenue because the biller left and the new hire did not understand how their specific surgeon documented complex procedures. Claims went out with incomplete documentation and got denied en masse. A facility never has that problem because the knowledge is institutional, spread across a team. Your private biller is a single point of failure. There is also the issue of communication speed. When you bill internally, the front desk calls the biller and gets an answer in thirty seconds. With a facility, you submit a ticket and wait four to six hours for a response, sometimes longer on Fridays. That delay matters when a patient calls about an explanation of benefits they do not understand and your staff cannot look it up in real time. If you are considering either route, here is what I would look at first. Your claim denial rate over the last ninety days. If it is above ten percent, outsourcing to a facility might actually improve it because they have more specialized denial management teams. If it is below five percent, you probably do not need the middleman and the margin you are paying them is pure profit leakage. Then check your average days in accounts receivable. Anything over forty-five days suggests your current setup needs help whether you outsource or not, and you should audit your coding practices before blaming the billing model itself.
Get the Full Details

Facilities tend to underperform with specialty practices that have unusual coding requirements, like pain management or behavioral health. These specialties have complex payer rules and frequent prior authorization needs that generalist billing companies struggle with. If you are in one of those areas, you need a facility that specifically serves your specialty or you stay private and find a specialist biller. Generalist facilities will flatten your nuanced claims into generic submissions and you will see your reimbursement drop even if your volume stays the same. There is a middle ground some groups do not know about. You can keep billing in-house but contract out only the denial follow-up and accounts receivable management. That splits the workload so your team handles front-end coding and submission while an outside company chases the stubborn claims past thirty days. It cuts the facility cost without losing the internal control over your daily operations. I recommended this to a practice last month after they told me they were paying four percent to a facility and still having communication delays with their own surgeons. The hybrid model saved them roughly fifteen hundred a month and cut their AR days from fifty-two to thirty-eight. The biggest mistake I see is owners picking a billing model based on what their neighbor does. If Dr. Patel across town outsources and is happy, that does not mean it is right for you. Your payer mix, your volume, and your internal capabilities determine the answer. Look at the numbers for your own practice first. Run the math on per-claim costs versus salaries. Calculate what an extra five percent in denials costs you over a year. The decision writes itself once you actually have the data in front of you.