
The actual day-to-day work most people don't tell you about
Medical coding isn't sitting at a desk matching diseases to numbers all day. It's reading opaque physician notes, fighting with ambiguous documentation, and spending twenty minutes on a single encounter because the doctor wrote "sepsis" without specifying whether it was due to acute respiratory failure or acute renal failure. The pay is decent if you put in the time. The career ceiling is lower than you'd hope unless you move into auditing or compliance. I've been doing this since before the ICD-10 transition in 2015, and honestly the job has only gotten harder. Documentation standards tightened, payer requirements multiplied, and the automation tools promised to replace coders mostly just shifted the bottleneck elsewhere. You still need a human to make judgment calls on incomplete records. That's the real value proposition now.
Getting Started With Medical Coding As A Career
There are two legitimate entry points. The first is through a certification program from AAPC or AHIMA. AAPC's CPC exam is the industry standard for outpatient coding, while AHIMA's RHIA and RHIT credentials lean more toward inpatient and hospital settings. Neither one is easy. The CPC pass rate hovers around 60 to 65 percent on first attempt. You should budget at least three to four months of serious study if you're working full-time while preparing. The second path is less formal but increasingly common: hiring into an entry-level coding position at a large health system that offers on-the-job training. This route depends heavily on finding the right employer. Most mid-size clinics won't train you from scratch. They want someone who can hit the ground running, which defeats the purpose if you have zero experience. Large hospital networks like Kaiser or Mayo Clinic have structured training programs that last six to twelve months. That's your best bet if you're pivoting from another field. I recommend getting the certification first even if you take the training route. Having the CPC or CCA on your resume gets you past automated screening tools. Without it, you're invisible to most hiring systems. The certification costs roughly $450 to $650 depending on whether you're an AAPC member, plus you'll need a study course which runs another $500 to $1,500. Total upfront investment sits somewhere between $1,000 and $2,000 if you shop around.
What the work actually involves
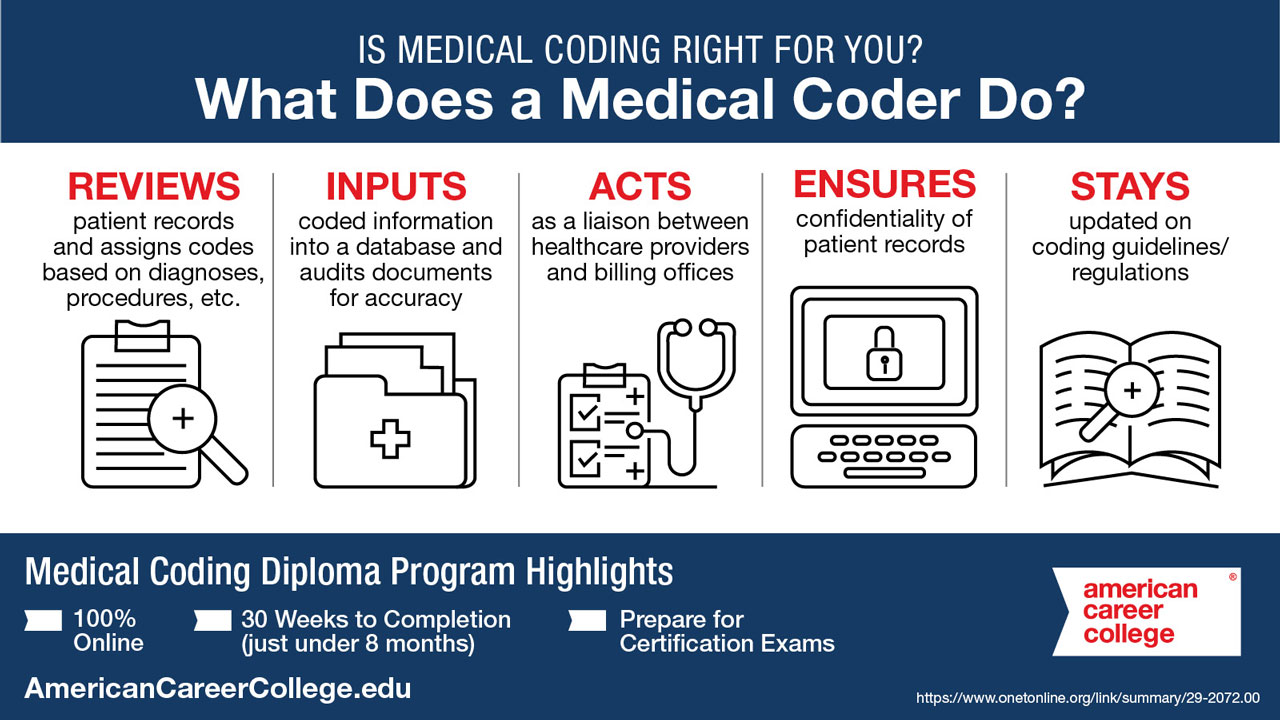
You'll be pulling patient records and assigning codes from three major code sets: ICD-10-CM for diagnoses, CPT for procedures, and HCPCS Level II for supplies and durable medical equipment. Most of your time will be spent in ICD-10-CM. That's the diagnosis code set that changed everything when it replaced ICD-9 in October 2015. The transition knocked out a lot of experienced coders because the specificity requirements are dramatically higher. "Pneumonia" used to be one code. Now it's roughly forty-seven different codes depending on organism, laterality, severity, and whether the patient has underlying conditions. Here's a specific example from my own work that nobody warns you about. I was coding a discharge summary for a patient admitted with acute-on-chronic kidney disease who also had a history of hypertension. The attending physician documented "acute renal failure secondary to hypertensive crisis" but didn't specify whether the hypertension was chronic or uncontrolled. Under the ICD-10-CM guidelines, I had to code both the acute kidney injury and the hypertension, but I couldn't assume the hypertension was uncontrolled just because they mentioned a crisis. I spent an afternoon researching this and ended up querying the physician through our EHR's formal query process. The response came back fourteen hours later confirming chronic hypertension, stage 3. That's two days on one encounter because of sloppy documentation. This happens constantly. The workaround is building a relationship with your physicians early on and sending them structured queries when documentation is ambiguous. Don't guess. The audits will catch you. The tools you'll use daily are an encoder like 3M or TruCode, the ICD-10-CM official guidelines, CPT professional edition, and your facility's specific coding policies. Most employers provide these. If they don't, you're in a place that doesn't know what it's doing. Encoder subscriptions alone run $300 to $800 per year if you buy them independently.
Get the Full Details
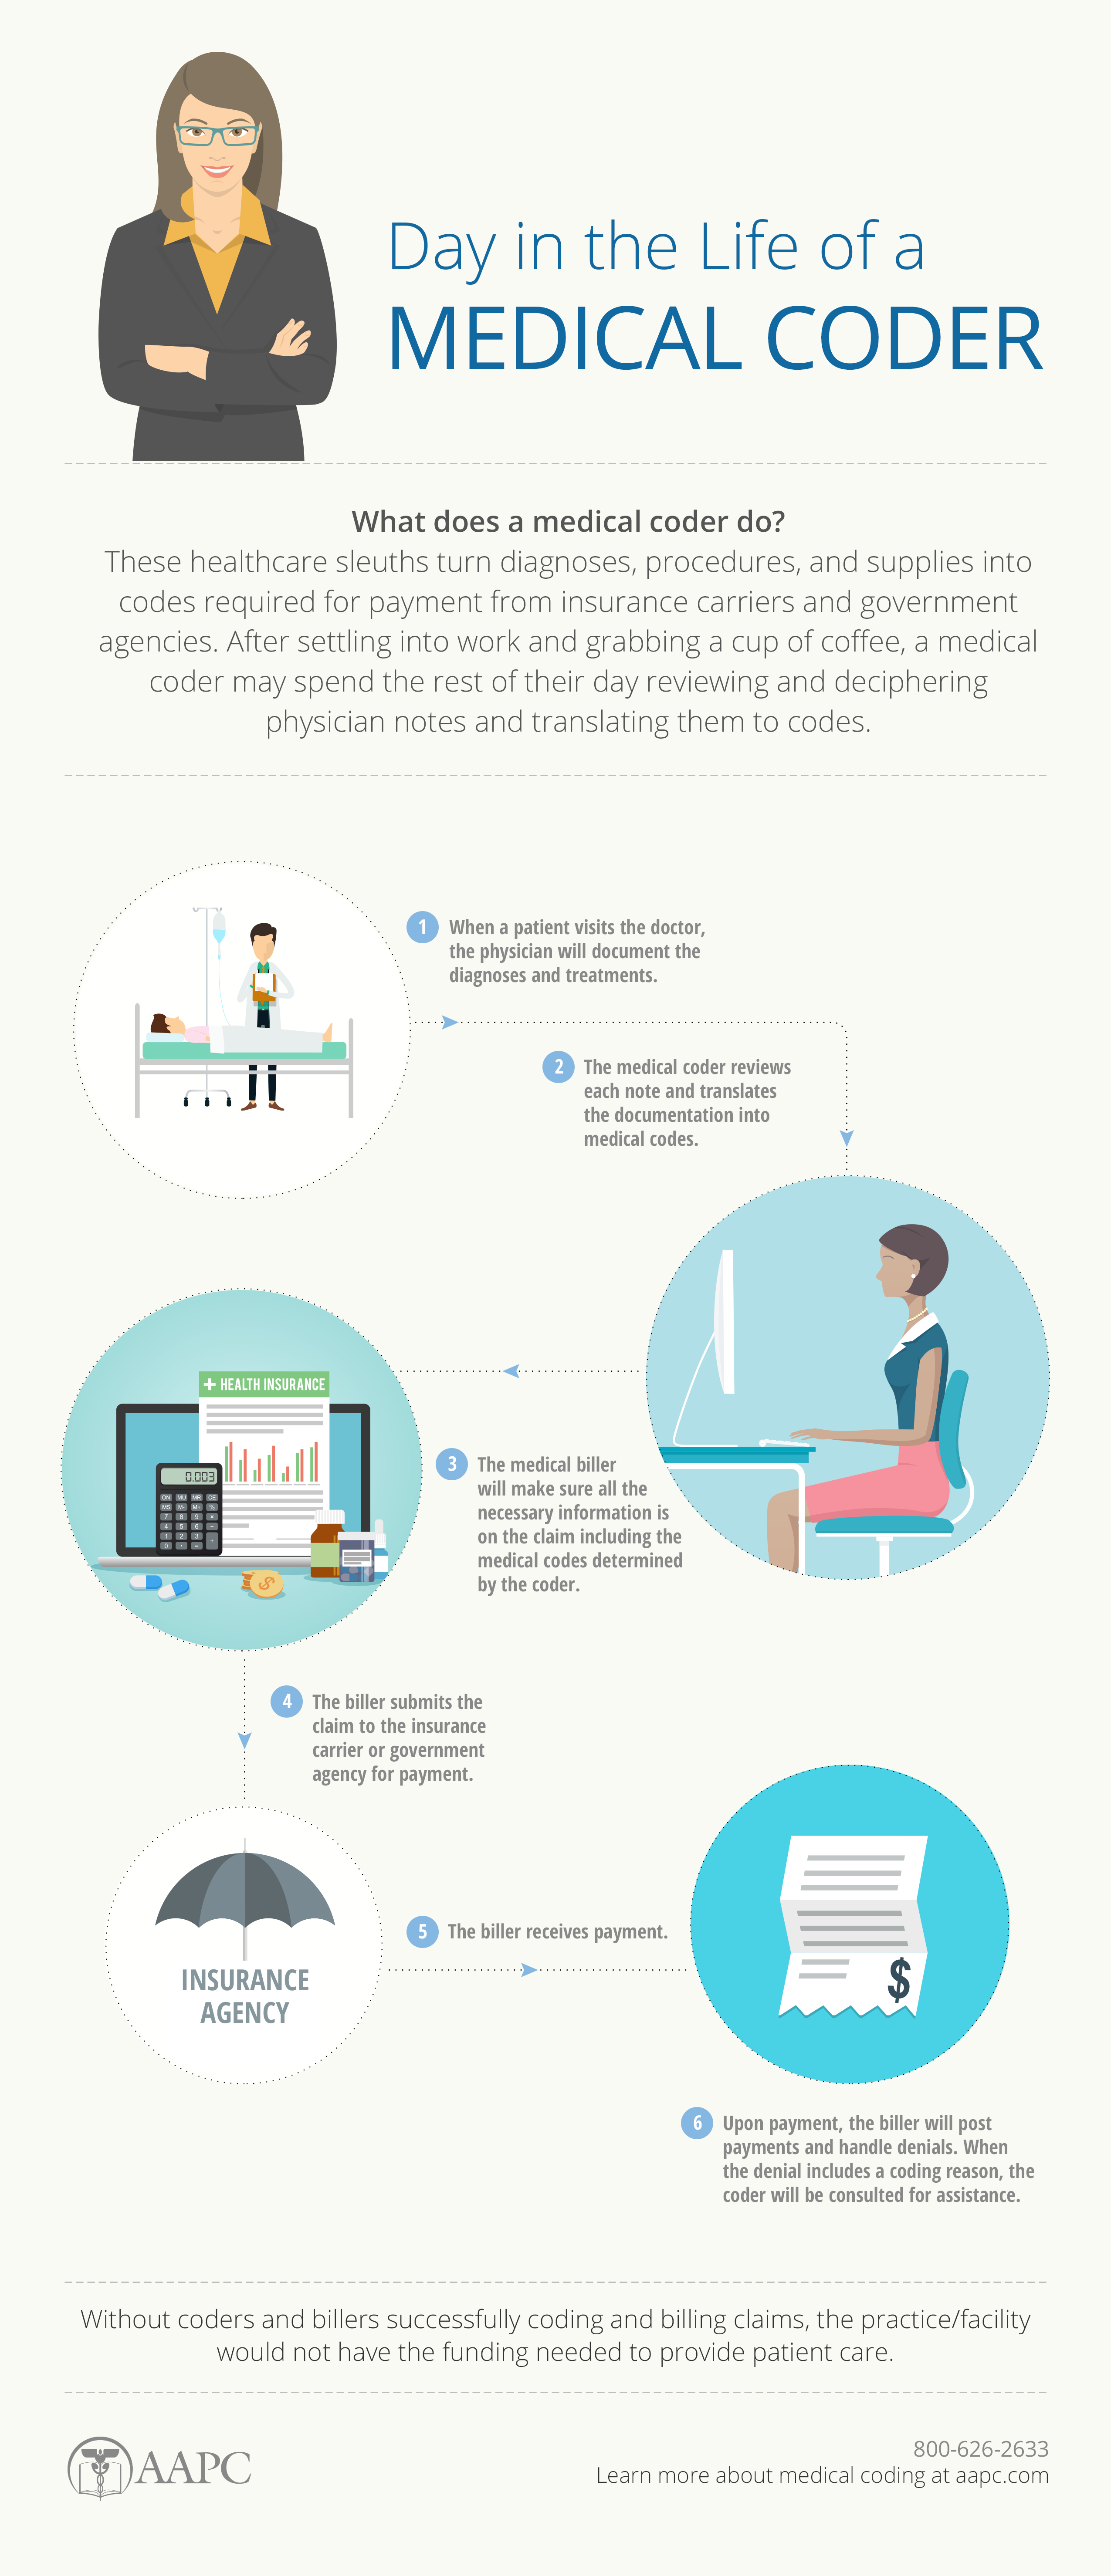
Coding volume varies wildly by setting. In outpatient physician offices, a productive coder might handle 40 to 60 encounters per day depending on complexity. In inpatient settings, you're looking at 8 to 15 discharge summaries per day. DRG coding takes longer because you're dealing with comorbidities, complications, and the sequencing rules that determine whether a case goes to a higher or lower reimbursement tier. A single missed secondary diagnosis can shift a DRG by thousands of dollars in reimbursement.
The part nobody discusses: burnout and stagnation
Medical coding has real attrition problems. The work is repetitive, visually demanding, and increasingly pressured by productivity metrics that don't account for case complexity. A typical coder might be expected to meet 90 to 110 percent of a daily quota measured in relative work units. New grad quotas are usually lower, around 70 to 80 percent, but expectations creep up quickly. After about eighteen months, you're expected to hit the same numbers as the veterans. This is where most people quit or burn out. Eye strain and repetitive stress injuries are genuine occupational hazards. I've seen coders develop carpal tunnel and severe cervical disc issues from years of staring at screens in poor ergonomic setups. Companies that don't invest in ergonomic equipment are cutting corners on liability. Stand desks, vertical mice, and proper monitor height aren't nice-to-haves. They're necessary. Career progression outside of senior coding roles is limited unless you intentionally diversify. The natural next steps are coding audit, compliance work, or clinical documentation improvement. CDI specialists typically earn 15 to 25 percent more than staff coders. Audit and compliance roles pay similarly but come with more variability in work patterns. Remote work became standard after 2020, which helps with quality of life but blurs the line between work and personal time. You're always "on" when your office is in another timezone.
The numbers that matter
Entry-level medical coders in the United States typically earn between $42,000 and $55,000 annually depending on geography and setting. Certified coders with two to five years of experience range from $55,000 to $75,000. Senior coders and lead positions push into the $75,000 to $95,000 range. CDI specialists and coding managers can exceed $100,000, though those roles are competitive and usually require additional credentials beyond the CPC. Geographic variation is significant. A coder in rural Mississippi makes substantially less than one in San Francisco, but the cost of living adjustment often neutralizes the difference. The real outlier is remote work. Companies based in high-cost areas sometimes offer national salary bands, which can be advantageous if you live somewhere affordable. Conversely, some companies peg salary to your ZIP code, which penalizes you for not living near their headquarters. The Bureau of Labor Statistics projects employment for medical records specialists to grow about 8 percent from 2022 to 2032, which is faster than average. This is driven by aging population demand and continued digitization of health records. However, the same report notes that automation is displacing some routine coding tasks. The net effect is that entry-level positions are becoming harder to land while experienced coders remain in demand. The middle is getting squeezed.
Things you should know before committing
Continuing education is mandatory and unpaid. AAPC requires 36 credits every two years for CPC holders. AHIMA requires 30 credits every two years for RHIA/RHIT holders. Most employers don't compensate for this time. You'll spend evenings and weekends attending webinars, taking courses, and tracking your credits. If you neglect this, your credential gets suspended. I've seen people lose their CPC after missing CE requirements because they assumed their employer would remind them. Nobody reminds you. It's your problem. The job market is segmented by specialty. Outpatient coding, inpatient coding, and radiology coding each have different knowledge requirements and different employer pools. Generalist coders exist but are increasingly rare. Most positions require you to specialize within the first year or two. This is by design, not accident. Complex specialties like oncology, cardiology, and orthopedics command higher rates because fewer people can code them accurately. One counter-intuitive insight that most beginners miss: knowing the codes cold is less important than understanding the documentation flow. I've hired coders who could recite the entire ICD-10-CM index but couldn't trace a physician's clinical reasoning through a poorly structured operative report. The ability to read like a clinician matters more than memorization. You'll learn this quickly enough once you start coding real cases, but don't walk into this expecting that flashcard-style studying will prepare you adequately.
Another thing that trips people up: compliance audits are aggressive and they target coders directly. In 2023, the OIG issued a compliance program guidance update specifically calling out improper coding as a top recovery audit risk. When auditors come knocking, they don't differentiate between intentional fraud and unintentional errors caused by ambiguous documentation. Your documentation and your query trail are your only protection. If you guessed on a code without querying, that's on you. I've watched colleagues get flagged in audits for exactly this reason. Don't be that person. Medical coding as a career is viable but narrow. It's stable, it pays reasonably, and remote work is common. It's not glamorous and the advancement ceiling is real. If you're detail-oriented, comfortable working independently, and willing to commit to ongoing education without complaint, it's a solid choice. If you're looking for creative problem-solving or rapid career growth, you'll be disappointed. The work rewards consistency, not ambition.


