
What actually happens when you try to learn this trade
Most people look at Medical Equipment Repair Technician Training and picture someone in a clean lab coat replacing parts on hospital machines. The reality is heavier. You spend most of your time dealing with old firmware that hasn't been updated since 2014, manufacturer lockouts that require passwords nobody at the community college can give you, and bills you need to fix today while the paperwork says you should wait two weeks. I went through a formal program at a technical college in Ohio back in 2008. The classes covered biomedical fundamentals, electronics theory, and basic safety protocols. It gave me enough foundation to not electrocute myself. What the program did not cover is how to deal with a GE 9LT ultrasound that refuses to pair with its transducer because the board firmware version conflicts with the probe serialization. That problem kept me up until 2am on a Thursday night in my first real job at a small hospital in rural Kentucky. The workaround was flashing a custom firmware build from a decommissioned same-model unit we had sitting in the equipment graveyard out back. I stripped the board, pulled the chip, used a TL866 programmer, and reinstalled it. Machine started working the next morning. Nobody at the training program would have known what to do with that situation.
Medical Equipment Repair Technician Training
The formal side of things involves structured coursework in analog and digital electronics, patient safety standards like NFPA 99 and IEC 60601, preventive maintenance workflows, and hands-on labs with the equipment you will actually encounter. Typical programs run between six months and two years depending on whether you are going for a certificate or an associate degree. Community colleges and technical schools are the main providers. Some hospital systems also run their own in-house programs for new hires. Here is what they will not tell you during orientation: the curriculum assumes you have access to working equipment for every module. Most schools do not. The budget for replacing broken trainers runs about eight thousand dollars per unit, and every program I have spoken to is somewhere between three and seven units short. This means you will spend real time troubleshooting machines that may never actually start. You learn more from watching someone else do it correctly than from turning the wrong potentiometer on a dead ventilator for the fourth time trying to force a reading.
The skills that actually matter
There is a gap between what textbooks teach and what you need to know on a Tuesday shift. The gap mostly exists in three areas: electrical safety testing, schematic reading, and documentation discipline. Electrical safety testers are the Anritsu MT-8822B or the Fluke ES4. You learn the procedure in class, which takes about forty-five minutes. In practice you will spend roughly twenty minutes per piece of equipment running leakage current, ground bond, and insulation tests on a typical defibrillator or infusion pump. A full battery of tests on a critical care ventilator with all its auxiliary modules usually takes about fifty minutes to an hour and fifteen minutes, give or take depending on cable management and how annoying the access panels are. Schematic reading is where most trainees stall. You do not need to design circuits from scratch. You need to follow a signal path from input to output, identify the power rails, and locate the section that is misbehaving. Start by pulling the service manual from the manufacturer. Not every vendor publishes these freely. GE Healthcare still requires you to submit a request and agree to a non-disclosure acknowledgment before they release anything beyond the basic operator manual. Philips offers theirs on their support portal if you register the equipment serial number. Siemens requires you to go through a dealer login in most cases. Expect to spend extra time tracking down documentation that should be publicly available but is not.
Get the Full Details

Documentation discipline is something I wish someone had forced into my head earlier. If you do not write down what you found, what you replaced, and what test results you got after the repair, you will rebuild the same work order twice. I lost track of a recurring ground fault on a Stryker operating table because I logged the symptom but not the troubleshooting steps. Three months later the same table came back with the same issue and I spent another two hours reproducing the diagnosis before realizing I had written the solution in a previous work order and forgot to flag it as resolved.
What to expect from the certification path
The main credential people talk about is the CBET through the AAMI Certification Board. It requires a combination of education and work experience. You can sit for the exam with an associate degree plus two years of relevant experience, or a bachelor's degree plus one year. The exam covers biomedical equipment fundamentals, clinical engineering management, and compliance standards. Passing rates hover around seventy percent on first attempt according to AAMI published data. The study guide alone does not cover enough real-world edge cases. Most people who pass do additional reading on IEC 62353, the FDA's guidance documents on medical device reprocessing, and state-specific regulations for medical equipment inspection. There is also the CMTE credential, which focuses more on the technical repair side than the management side. It requires a high school diploma plus four years of documented experience, or an associate degree plus two years. The exam is heavily focused on troubleshooting methodology and repair procedures. If your goal is to stay on the bench fixing equipment, CMTE is the more directly useful certification. CBET opens doors into clinical engineering leadership roles.
Common pitfalls that slow people down
The first mistake I see repeatedly is treating every machine the same way. A patient monitor and an anesthesia delivery system share components, but their failure modes and safety implications are completely different. A loose ground on a monitor might just cause noise in the ECG tracing. A ground fault on an anesthesia machine during active use is a direct patient risk. Your troubleshooting approach should scale with the clinical consequence of failure. Start simple on low-risk devices. Go methodical and document everything on life-support equipment. The second mistake is ignoring calibration fixtures. You can repair a blood pressure analyzer without calibration equipment and get it to display a number. That number will be wrong. A proper calibration setup for a BP analyzer costs between four hundred and twelve hundred dollars depending on the range and accuracy requirements. Budget-conscious shops often skip this. The equipment still works. The readings are unreliable. When the audit comes around, you will know why. The third mistake is assuming software updates solve hardware problems. They do not. I worked with a vendor representative who insisted that a recurring communication error on a series of IV pumps was a firmware bug. He pushed an update that changed nothing. The root cause was a cracked trace on the motherboard near the RS-232 connector from repeated cable stress during routine transport. Micro-soldering the trace fixed it permanently. Firmware updates are useful for feature additions and known vulnerabilities. They will not fix a broken board.
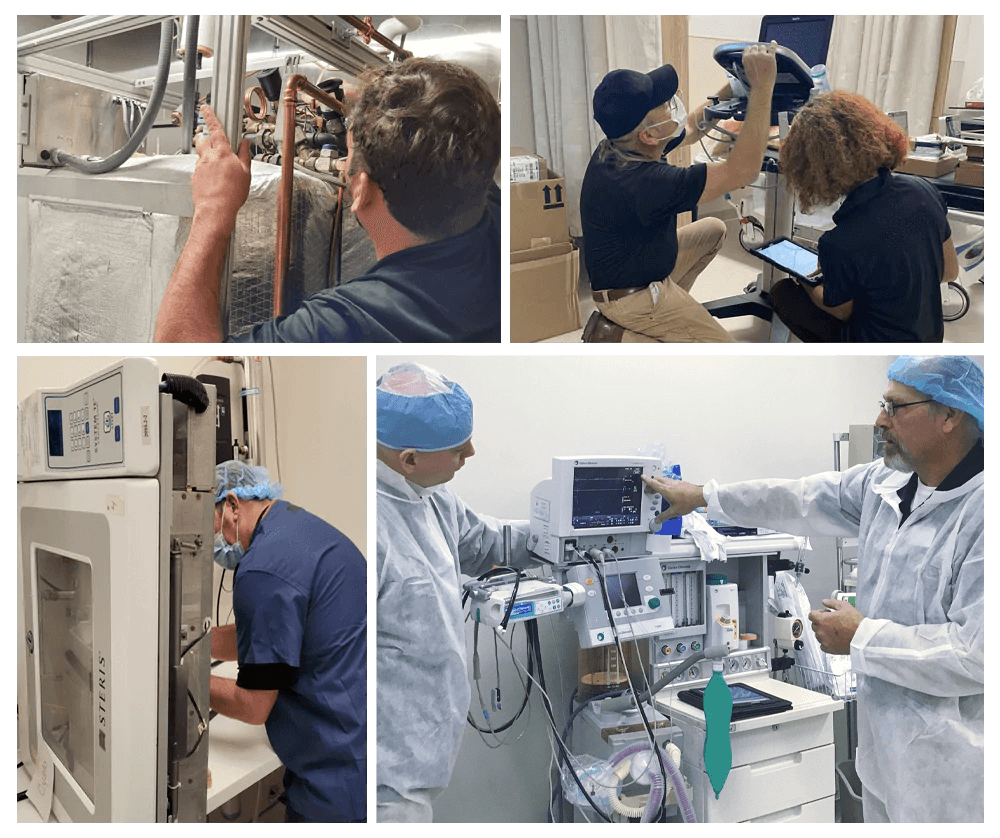
What the training does not prepare you for
One thing the programs miss entirely is vendor hostility. You will call a manufacturer help line to get a diagnostic code explained. The person on the other end will read from a script that explicitly directs you to replace the entire assembly. This is called part-banding, and it is built into the business model. Some manufacturers make it harder by requiring dealer authorization codes just to pull error logs. You will learn to work around these restrictions over time. The workaround is usually a combination of knowledge, patience, and occasionally a favor from someone who has been doing this longer than you. Another gap is understanding the financial pressure behind your work. Every hour a machine sits in your shop is an hour the clinical team cannot use it. Sometimes the right call is to perform a temporary repair that gets the equipment back to the floor while you order the proper part. A field replacement of a cracked housing with epoxy and a donor connector can buy you three to four weeks while the OEM part ships. It is not ideal. It keeps the patient care moving. The alternative is filing a risk report and waiting for administration to approve a replacement device, which can take sixty to ninety days depending on the purchasing cycle.
Where to start if you are serious about this
If you want to enter this field, find a program that includes hands-on lab time with actual hospital equipment, not just trainers and simulators. Ask the program director how much of the curriculum is spent on equipment you will encounter in a typical clinical engineering department. The answer should include ventilators, patient monitors, defibrillators, infusion pumps, and surgical lights. If the program only covers low-acuity devices like scale models and teaching mannequins, you will need supplemental training before you are ready for a hospital floor. Pair formal training with volunteer or entry-level work as soon as possible. Even thirty hours a week in a biomedical department while you finish your classes gives you exposure to the workflow, the paperwork, and the kinds of problems that do not show up in a textbook. I spent two years doing part-time work at a clinic while attending night classes. That experience was worth more than the certificate at the end of the program. The work is not glamorous. The equipment is heavy. The parts can be expensive and slow to arrive. The pay is moderate compared to other technical fields. But the people who stick with it tend to stay because they enjoy solving problems that other people cannot figure out, and because the work has a direct impact on patient safety that most technical jobs do not provide.



