What Actually Goes in an Exam Room
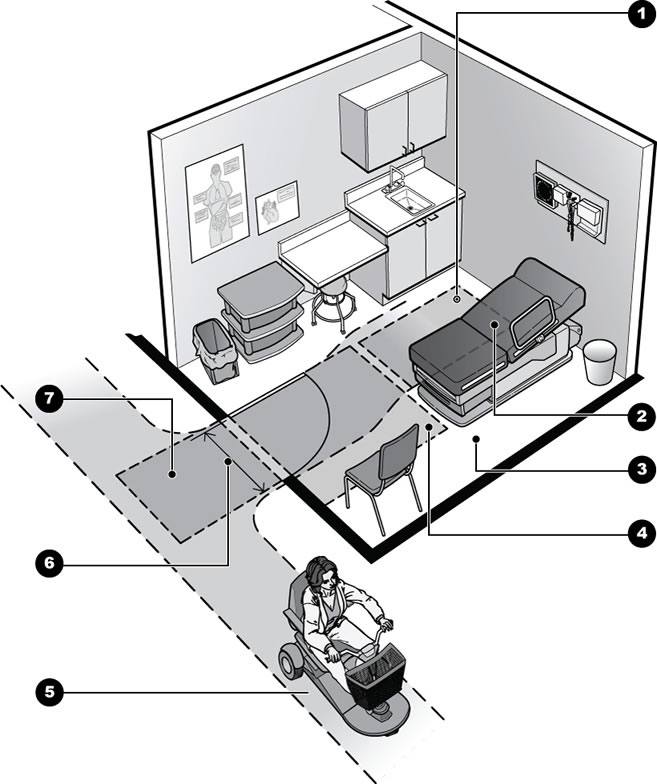
The people who sign off on exam rooms don't care about your aesthetic vision. They care about measurable things: surface materials, sink placement, lighting lux levels, and whether a wheelchair can actually turn around in the space. Most clinics fail on the first pass because they draw up a floor plan from a template they found online rather than walking through the actual inspection criteria with their local health department or accrediting body. I went through this for a clinic build-out in Tennessee. We had our initial survey knocked back because the inspection room door swing was six inches short of what a standard wheelchair needed to navigate from the entrance to the exam table without hitting the wall. That cost us three weeks and $4,200 in re-plan fees alone. The inspector wasn't being difficult. The Americans with Disabilities Act specifies a 60-inch turning diameter for wheelchairs in patient care areas, and our original layout just didn't provide it. Here is what actually matters, stripped of whatever brochure language your contractor fed you:
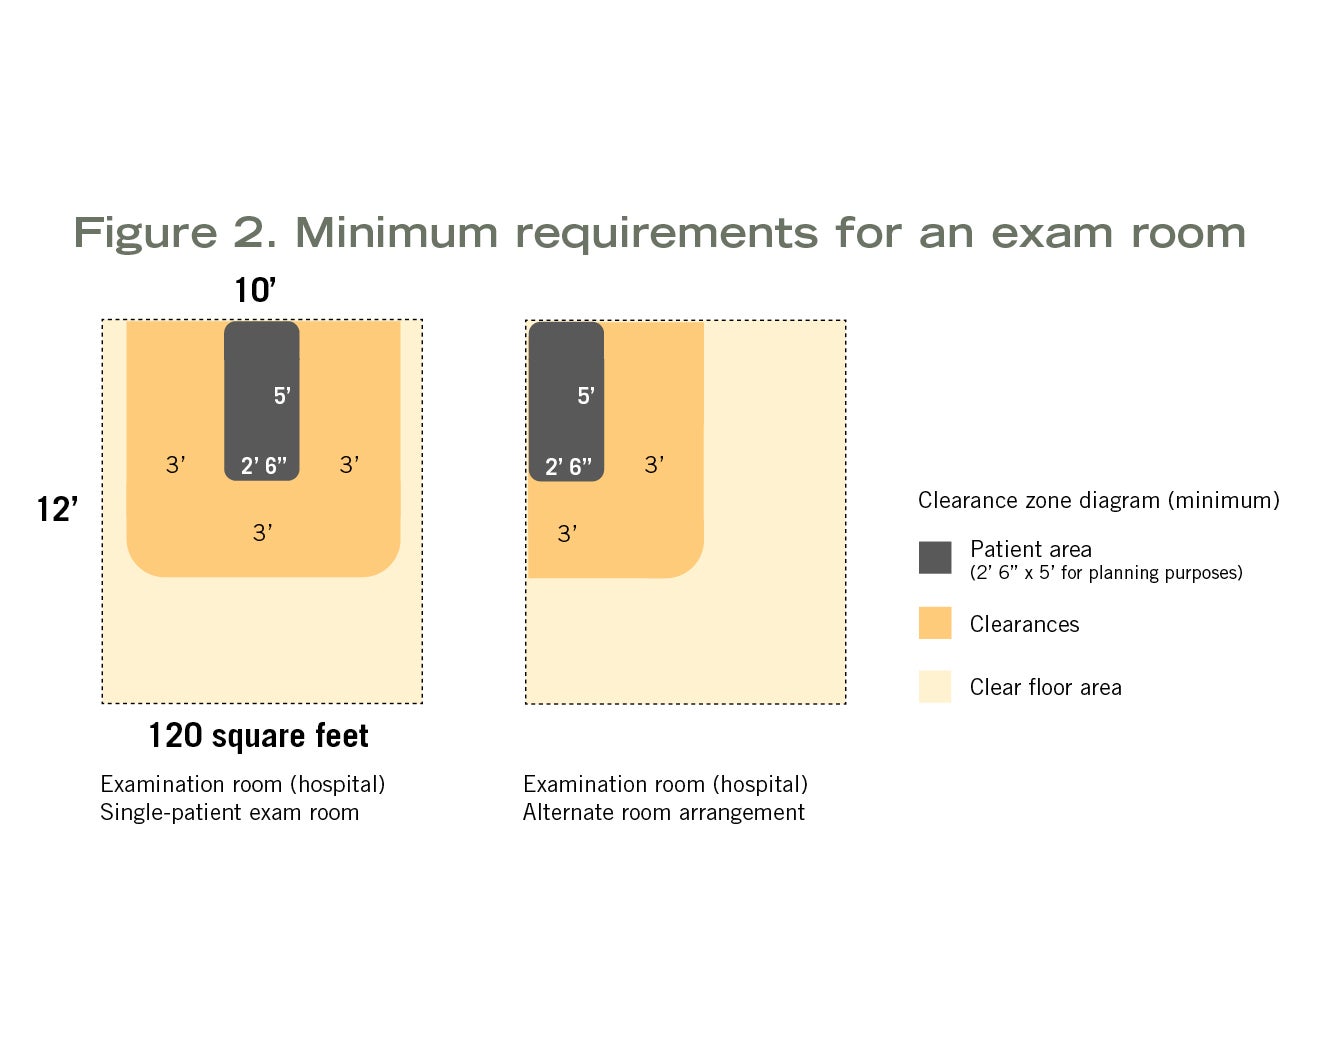
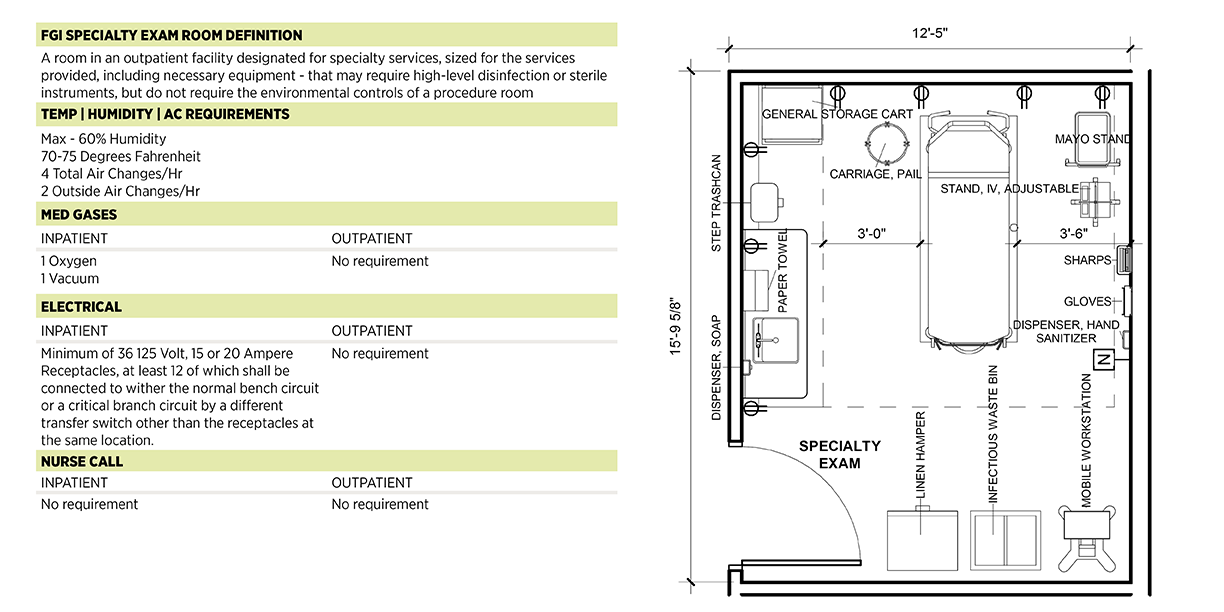
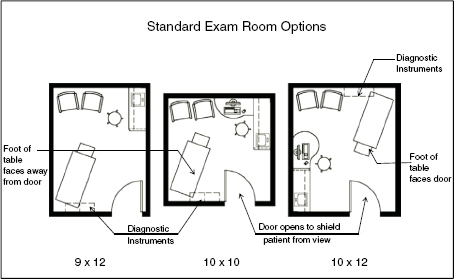
Room dimensions. Minimum clear floor space varies by jurisdiction but a functional exam room generally needs at least 80 to 100 square feet of unobstructed area. The CDC and OSHA don't set a hard minimum, but Medicare Conditions of Participation and state licensing boards typically reference the International Building Code, which means you need that wheelchair turning radius. Most people end up going 10-by-12 or 10-by-14 to be safe. Sink placement. This is the most commonly botched element. The sink needs to be within arm's reach of the exam table and the physician workspace but not so close that someone washing their hands bumps into the patient chair or blocks the doorway. FDA guidelines for hand hygiene in healthcare settings require a sink in or near every patient care room. The sink must be hands-free or knee-operated—foot pedals, sensor faucets, or C-shaped handles. I've seen inspectors reject rooms with elbow-touch faucets because the patient chair interfered with the operating lever. Put the sink on the wall opposite the door, ideally between the exam table and the supply storage area. Surfaces. Walls need to be smooth, washable, and non-porous below the wainscoting line. Most states follow The Joint Commission environmental standards here, which means painted drywall with a semi-gloss or gloss finish works fine, but fabric-covered panels and exposed brick are out. Floors must be hard, seamless, and cove-edged where they meet the walls. Vinyl sheet flooring with welded seams is the standard. Carpet is a one-way ticket to a failed inspection unless it's in a staff-only area.
Lighting. General ambient lighting needs to hit at least 30 foot-candles across the exam area. Procedure lighting should be a separate adjustable fixture, preferably LED with a color rendering index above 90, mounted on a articulating arm. The old fluorescent tubes you see in a lot of older clinics sit around 70 to 80 CRI and make it nearly impossible to accurately assess skin tone and wound appearance. I switched one of my rooms to high-CRI LED and the dermatology referrals dropped because we caught lesions earlier. That is a side benefit, not a requirement, but it matters. Examination table. Standard weight rating is 400 to 600 pounds for a manual table, 600 to 800 for a powered bariatric-capable unit. The table must have stirrups if the room is designated for gynecological or urological exams. Fire codes in several states now require the table to have a minimum of three safety locks engaged when in the raised position. Cheap tables from off-brand medical supply companies often have flimsy lock mechanisms that fail under lateral stress. Spend the extra money on a brand that offers third-party testing certification, usually labeled as meeting ANSI/CGA standards or equivalent. Medical equipment storage. You need closed cabinetry for controlled substances and lockable storage for any Schedule II through V medications. OSHA's Bloodborne Pathogens Standard requires sharps containers and biohazard waste bins to be accessible but not in open sight. Fluorescent light strips should be housed in shatter-resistant covers or switched to LED panels, because a broken bulb over an open wound is a real infection control issue.
Get the Full Details
Electrical and data. At least two grounded receptacles per wall, spaced no more than four feet apart along walls longer than six feet. One of those should be a dedicated circuit for the exam table motor and any imaging equipment. Network drops are essential if you're using an electronic health record system. I've run into cases where a clinic was told to pull new Cat6 cabling through finished walls because the original installer only ran power and left the data ports unplugged. That runs $1,500 to $3,000 depending on your building structure. Patient privacy. HIPAA doesn't dictate room dimensions, but it does require that reasonable safeguards be in place. This means doors that close and latch, window coverings if the room has exterior windows, and sound-dampening measures so conversations in the next room aren't audible. The Joint Commission checks for this during surveys. Frosted glass in door windows is a common workaround that satisfies both privacy and safety inspectors who want to confirm a patient is conscious in the room. There is a persistent myth that every exam room needs an anteroom or cleaning space. It does not, unless you are doing procedural work like minor surgery or wound debridement. A standard wellness or follow-up visit room operates fine with a single space. The anteroom requirement comes from procedural suites, which have their own separate checklist involving scrub sinks, instrument sterilization storage, and stricter air exchange rates.
Another thing people get wrong is the HVAC requirements. You do not need hospital-grade negative pressure in a standard exam room. That is for airborne infection isolation rooms, which are only required if you are treating tuberculosis or other airborne pathogens. For a general practice, you need six to eight air changes per hour with a MERV 13 filter minimum, according to ASHRAE Standard 170. Some local jurisdictions bump that to ten changes. Check your state health department code, not the national model code, because the local amendment always carries more weight. The process of getting an exam room approved usually goes like this: you submit plans to your local building department, then to your state medical board or health department, then to CMS if you bill Medicare, then to your insurance panel auditors if you want credentialing. These are not sequential steps. They often run in parallel, and each one has different checklists. I learned that the hard way when a state license review caught a violation that the building department had already signed off on. The state requires an emergency power outlet near the exam table for situations where the building loses power and a patient is on the table. The building inspector was looking at occupancy and egress. Different priorities. Both matter.
What Most People Skip That Costs Them Later
Fixture selection is where budgets quietly blow up. A $200 exam table sounds fine until you realize the upholstery is PVC vinyl and tears after eight months of daily use, and the replacement cushion runs $180 and has a six-week lead time. Budget $800 to $1,500 for a table that will actually last. Same with the patient chair. The cheap ones wobble and the cushions flatten. A functional chair costs $300 to $600 and holds up for years. Hand sanitizer dispensers are not a substitute for a sink. OSHA and the CDC are clear on this. A wall-mounted automatic dispenser is fine as a supplementary measure, but you still need the plumbed sink with soap. Some clinics try to save plumbing costs by removing the sink and relying on sanitizer stations. That is a guaranteed fail during any real inspection. The sharps container placement is another quiet failure point. The container needs to be at the point of use, within immediate reach of the clinician, and never more than six feet from where injections or phlebotomy occur. I once had a clinic that mounted the sharps container on the wall behind the instrument tray, which looked organized but forced the provider to turn away from the patient to dispose of a needle. The inspector flagged it as a contamination risk because the provider's gloved hand traveled past the patient's face on the return stroke. They moved it to the side of the instrument tray and passed on the re-inspection.
Documenting everything helps when you need to justify costs or defend your setup during an audit. Keep receipts, model numbers, and installation records. If a surveyor asks why you chose a specific sink faucet or a particular floor material, having the spec sheet on file shows you made an informed decision rather than picking the cheapest option and hoping nobody notices.
The Bottom Line
Meeting Medical Exam Room Requirements is less about any single rule and more about making sure every piece fits together without creating a hazard. The inspection will find what you didn't think to check. Plan for the worst case, budget for the upgrades you initially dismissed, and walk through your own room the way an inspector would: door to sink to table to waste bin to exit, noting every obstruction, every unreachable fixture, and every surface that cannot be cleaned in a single pass.