Why Your Front Desk Onboarding Keeps Failing
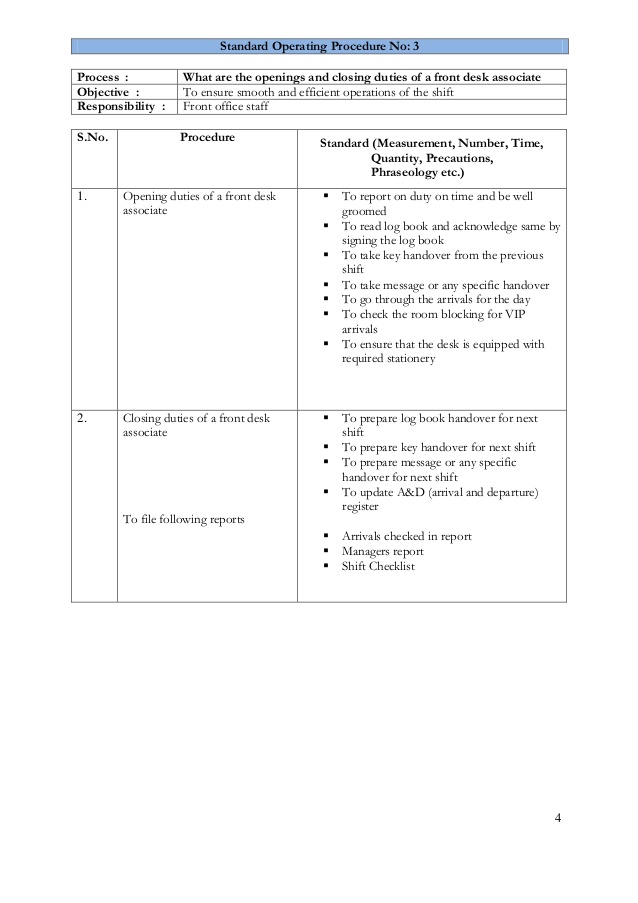
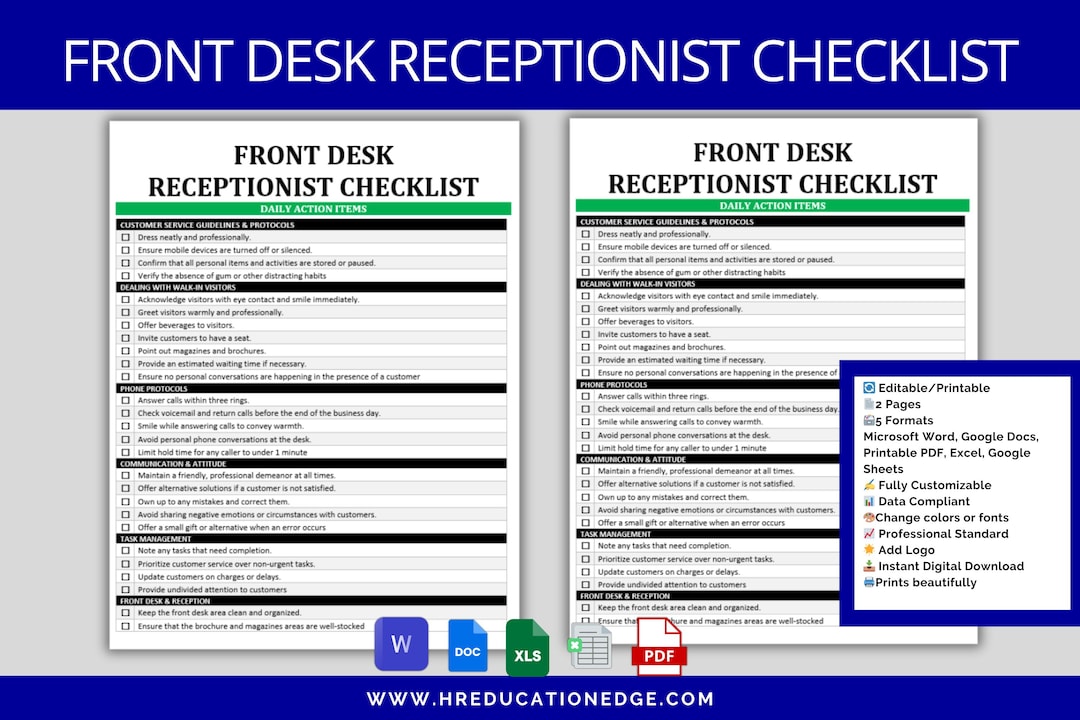
I spent about four years managing the front desk at a mid-size orthopedics clinic before moving into operations. We cycled through about seven different training approaches before we landed on something that actually stuck. The problem wasn't the people. It was the checklist we gave them. Most practices hand a new hire a binder full of PDFs and expect them to absorb it over two weeks while simultaneously answering phones, checking patients in, and figuring out which insurance portal is having issues that day. It doesn't work. The checklist approach does, but only if it's built right. Here's what I learned about building a Medical Front Desk Training Checklist that actually functions as a training tool instead of just another document that gathers dust in the shared drive.
Building a Medical Front Desk Training Checklist That Works
Start by breaking the role into modules based on frequency and risk, not by department. Most people organize around intake, scheduling, billing, and phones. That feels logical until you realize the person doing intake also handles phones and often touches billing data. Grouping by workflow sequence rather than title creates less context-switching. Module one should be software navigation. Not patient interaction, not HIPAA reminders, just navigating the EHR. Can they log in? Can they find the schedule grid? Can they pull up a patient chart without calling for help? This typically takes new hires three to five days of focused practice in a sandbox environment before they're safe to touch a live schedule. Don't rush this. I once had someone go live after one day of training and accidentally schedule forty-two patients under the same slot because they didn't understand how the time-block system worked. That cost us approximately two hours of cleanup and one very angry attending physician. Module two covers check-in workflows. Insurance verification, copay collection, consent forms, update captures. This is where most checklists fall apart because they list steps without specifying decision points. A good training checklist doesn't say "verify insurance." It says "ask for insurance card, run eligibility check in the portal, note any copay amount, collect if under fifty dollars, flag anything above that for the supervisor." Specificity matters here. When someone new is standing at a desk with a line of patients behind them, vague instructions create hesitation and errors.
Module three is scheduling protocols. Same-day requests, referral requirements, specialist coordination, cancellation rebooking. These are the highest-friction interactions and the ones where mistakes compound fastest. A missed referral requirement can delay a surgery by weeks. I learned this the hard way when a trainee scheduled a post-op imaging study without confirming the surgeon's referral was on file. The imaging center denied the claim. Patient had to come back. Everyone wasted half a day. After that, I added a mandatory double-check step specifically for any appointment that references a prior authorization or referral number. Module four handles phone triage and messaging. Call routing, after-hours protocols, message prioritization. This module needs actual phone practice, not just reading scripts. New hires should handle a simulated call queue for at least two hours before taking real calls. I set up a testing scenario with three simultaneous ringers and varied call types, and anyone who couldn't manage it within thirty minutes got additional training before touching the switchboard. This usually filters out about fifteen percent of trainees who look confident on paper but panic under mild pressure. Module five is the compliance and administrative stuff. HIPAA, OSHA, office policies, emergency procedures. I know this is boring and people want to skip it, but skipping it is how you get surveyed. Cover the material, but don't make it a week-long ordeal. Two focused sessions with brief quizzes works better than burying it in a forty-five-page handbook they'll never reference again.
Get the Full Details

The checklist itself should be structured as a series of verified competencies, not a reading list. Each item needs a clear pass or fail condition and a documented verification method. "Can schedule same-day referrals independently" is better than "Understands referral scheduling." You're training people, not collecting signatures on a form. Include a sign-off section where both the trainer and trainee initial each module. This creates accountability and gives you a paper trail for compliance audits. Your accreditation body will ask for this eventually, and when they do, you'll want the documentation ready.
The Parts Everyone Misses
Here's what most training checklists don't include, and why that matters. Patient escalation protocols. New hires need to know exactly when to stop handling a situation and bring in a manager. Angry patients, billing disputes over fifty dollars, insurance denials that require clinical documentation, any patient asking for something the front desk isn't authorized to approve. I've seen trainees waste twenty minutes trying to resolve a copay dispute that should have been handed off immediately. They were polite, they were trying, and they were costing the clinic real money in staff time. A clear escalation matrix changes this. Time management expectations. How long should a standard check-in take? What's acceptable for a first visit versus a follow-up? Without benchmarks, you have no way to gauge whether someone is performing adequately. A typical check-in should take under four minutes. First visits might run eight to ten minutes. If someone consistently exceeds these by more than fifty percent, there's a training gap somewhere.
Handoff procedures. Shift transitions are where everything breaks down. Leftover voicemails, unprocessed faxes, pending authorization requests. A proper checklist includes a mandatory end-of-shift handoff protocol with a standardized communication template. I implemented a simple two-minute verbal handoff requirement between outgoing and incoming staff, and our after-hours patient complaints dropped significantly within the first month.

When This Approach Doesn't Work
Let me be honest about the limitations. A training checklist only works if you have someone qualified to actually train the person. If your "trainer" is the most experienced front desk person who has no formal training in teaching and communicates primarily through frustration, no checklist will save you. Invest in training your trainers first. This alone has more impact than any document you write. Checklists also fail when they become too long. Anything beyond roughly forty-five to fifty distinct checkpoints starts losing effectiveness. People skimming the document won't engage with it deeply. If your checklist is running eighty items, you have a documentation problem, not a training problem. Consolidate. Merge related steps. Remove items that can be verified on the job rather than in a formal assessment. There's also a budget constraint to consider. Building a solid training program like this typically requires eight to twelve hours of an experienced staff member's time upfront, plus ongoing weekly review sessions for the first sixty days. Smaller practices with thin staffing may find this impractical. In those cases, consider partnering with a medical staffing agency that offers structured onboarding programs, or invest in a commercial training platform designed for medical front desk roles. It costs more per hire but spreads the development overhead across multiple locations.
Electronic health record systems vary significantly in how they handle scheduling, eligibility checks, and patient communication. A checklist built for Epic won't translate cleanly to a Practice Fusion environment. Make sure your training materials are specific to your actual software configuration, not a generic version you found online. Most importantly, remember that a checklist is a framework, not a substitute for judgment. New hires will encounter situations that don't fit any of your pre-written steps. Teach them how to think through problems, not just which buttons to press. The best front desk people I've worked with weren't the ones who memorized the checklist fastest. They were the ones who understood why each step existed and could adapt when the process didn't match the situation.