Why Your Medical History Form Keeps Failing Patients
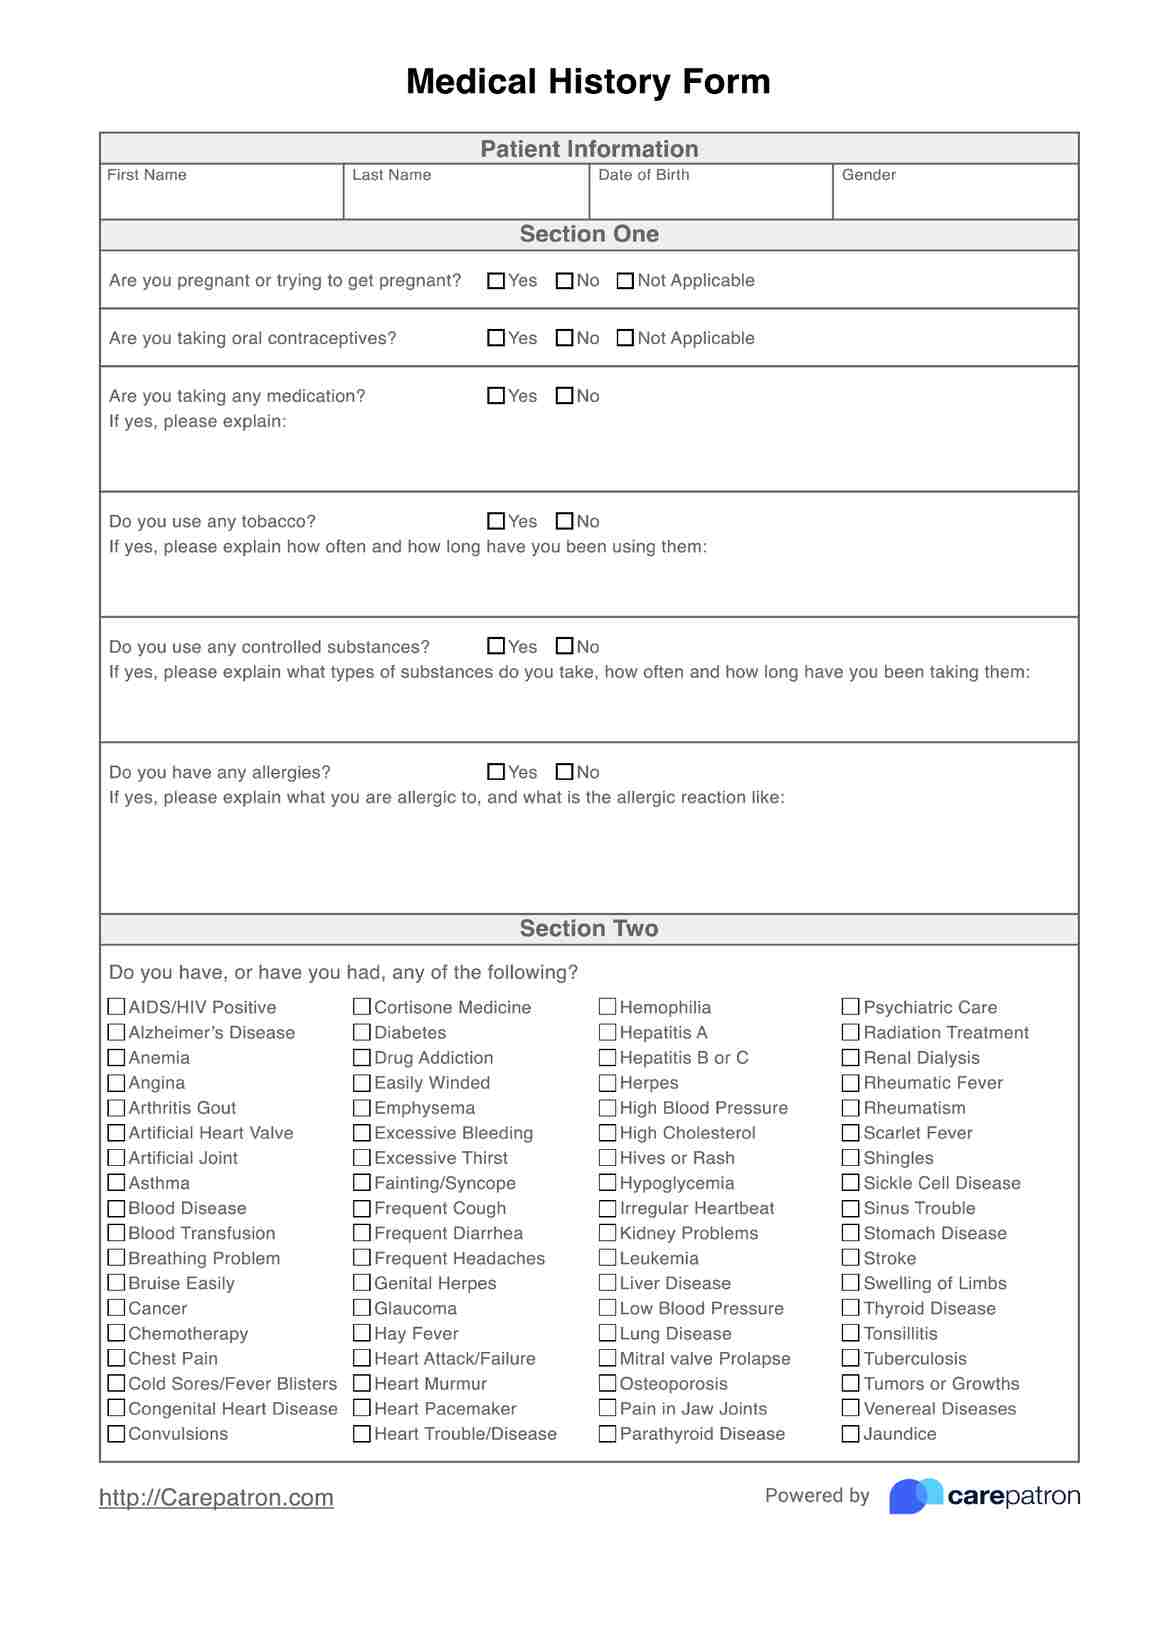
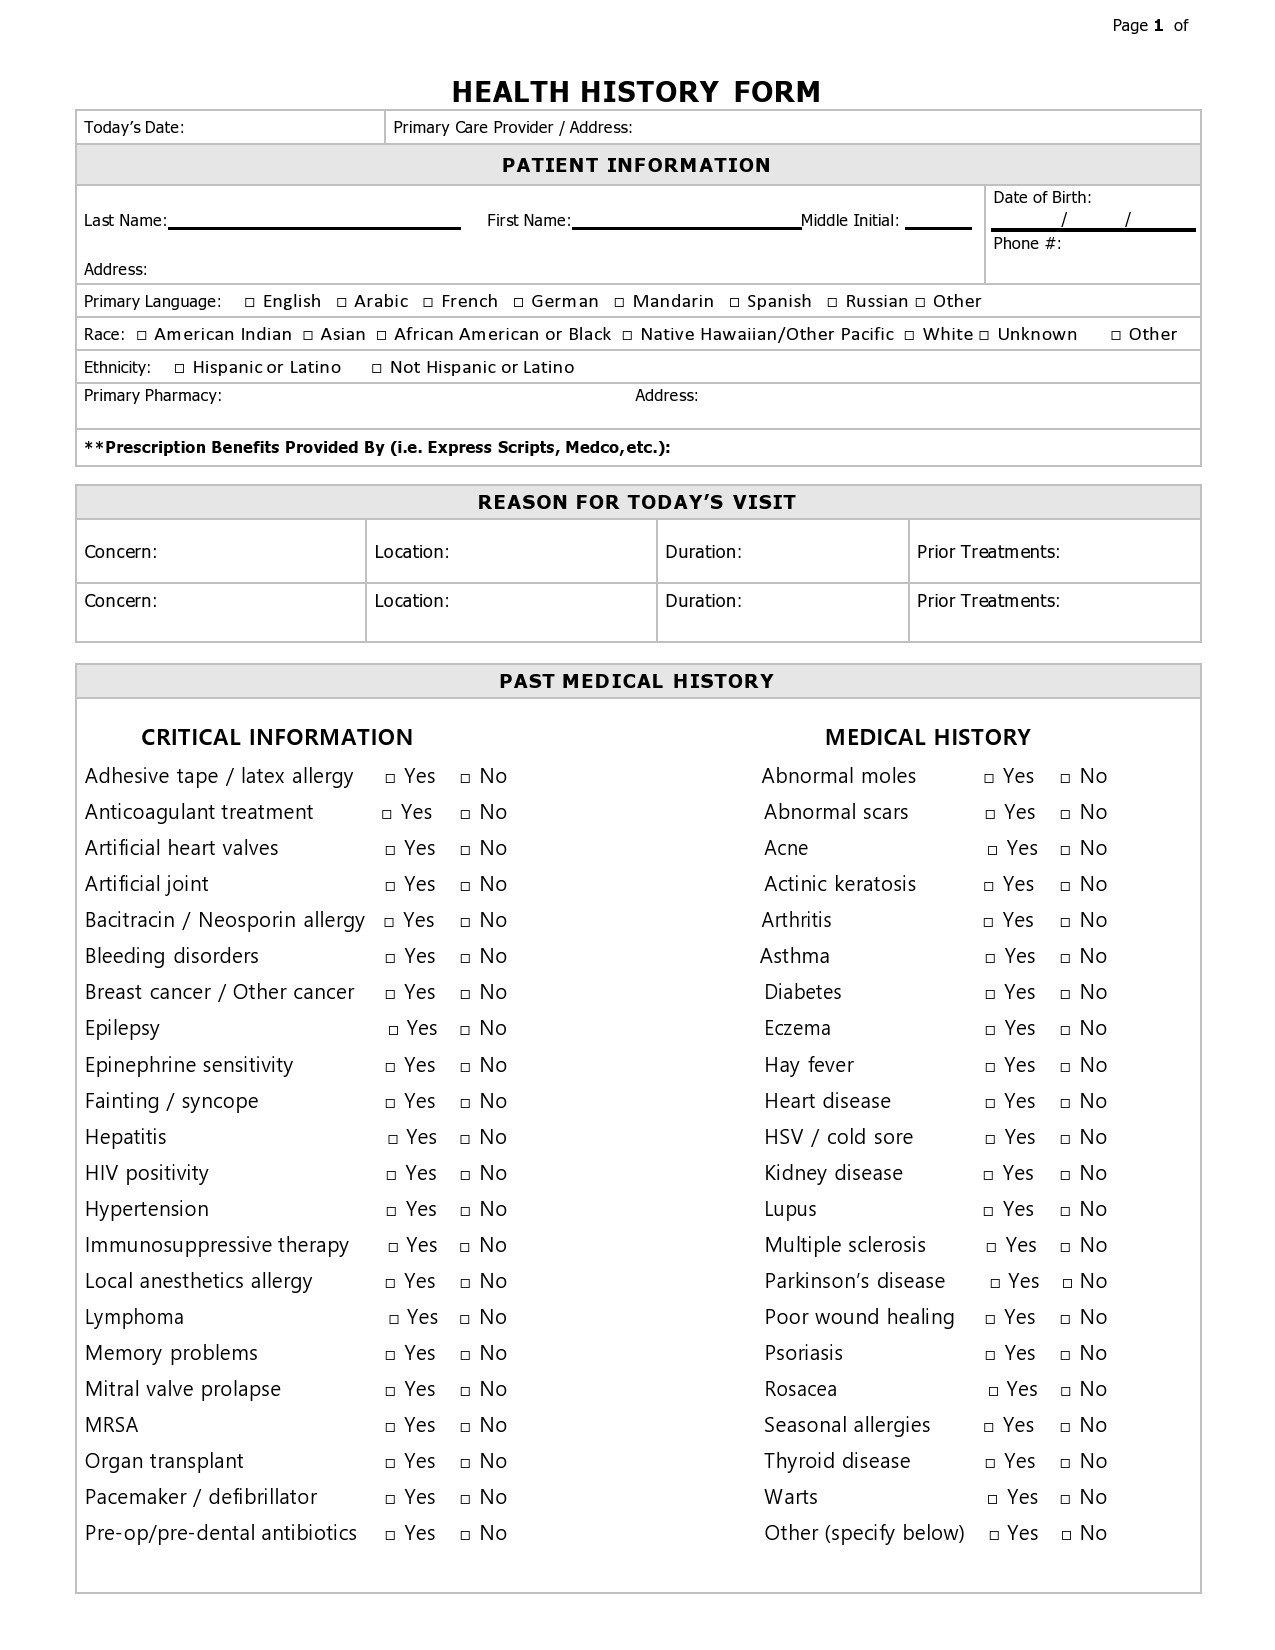
Most people treat the Medical History Form like a bureaucratic checkbox. You hand it to a patient, they scribble some answers, you file it away. That approach misses the entire point of what that document is actually supposed to do. I learned this the hard way about five years into practice when I nearly missed a contraindication that would have caused a serious reaction. The form itself is straightforward on paper. It captures past diagnoses, current medications, surgical history, family health patterns, allergies, and lifestyle factors. The problem isn't collecting the data. The problem is that patients don't read it correctly, they omit information they think is irrelevant, and they frequently fill out the medication section wrong because they don't understand the difference between a brand name and a generic, or they forget about supplements and over-the-counter drugs they've been taking for months.
Building a Functional Medical History Form
Start with the structure before you worry about design or software. I broke my current system down into six sections that follow the clinical interview flow: Chief Concern, Current Medications and Supplements, Past Medical and Surgical History, Family History, Allergies and Adverse Reactions, and Social and Lifestyle History. Everything else is formatting noise. The medication section is where most forms fall apart. I used to ask patients to list their medications. That produces garbage. Instead, I ask them to bring every bottle to the appointment or photograph every label clearly. The form then just has fields for medication name, dosage, frequency, prescriber, and start date. I built the form to force specificity. Vague answers get flagged during intake review. For the allergy section, I separate true allergic reactions from side effects. This distinction matters more than most providers realize. A patient listing "allergic to ibuprofen" because it gave them heartburn isn't allergic to ibuprofen. They have an intolerance. Writing that distinction into the form changes how I approach prescribing. I started adding a small text field next to each allergy entry asking "What happened?" and that one change alone caught three genuine anaphylactic histories that were buried under a list of fake allergies.
Family history needs more than a checkbox for diabetes and heart disease. I include a structured section for first-degree relatives with specific fields: relationship, condition diagnosed before age 50 or after, and current status. This catches early-onset conditions that change screening recommendations entirely. A father diagnosed with colon cancer at 42 doesn't just mean your patient is "at risk." It means colonoscopy screening starts at 40 or ten years before the diagnosis, whichever comes first. That's the kind of nuance a basic Medical History Form usually strips away. The social history section is where I got tripped up for years. I used to ask "do you smoke?" with yes or no boxes. That missed too much. Now I ask about nicotine in all forms, alcohol in standard drinks per week, recreational drug use, occupation and exposure history, and living situation including who they rely on for support. The tobacco question alone took my office from missing two active smoking histories per month to catching nearly all of them. Patients will say they quit when they haven't if you ask it casually. Structured questions with specific metrics change the conversation.
Get the Full Details
Common Pitfalls That Waste Everyone's Time
The biggest issue I see with Medical History Form implementations is that they're designed for data entry rather than clinical utility. I watched a clinic rollout a digital version that auto-populated from insurance records. It looked efficient until I realized the insurance data had six-month-old medication lists and zero supplement information. The form was technically complete and clinically useless. I had the staff revert to manual collection for medication history while keeping the insurance auto-fill for demographic data only. Another problem is the layout. I've seen forms that put family history before current medications. That seems minor until you realize the clinician reads top to bottom and often forms an early impression. Medication interactions should be visible immediately. Family history can wait. Structure the form in order of clinical priority, not alphabetical convenience. Paper forms create their own set of failures. Illegible handwriting, skipped sections, and patients who fill out one form and assume the previous visit's form is still current. I stopped using paper entirely after a patient showed up with a form from eighteen months ago and checked "no changes" without looking at it. Their blood pressure medication had been adjusted twice in that period. The old form said they were on lisinopril 10mg. They were actually on 40mg. This is the kind of error that causes real harm and is completely preventable with a dated revision check on every form.
Digital forms solve some of this but introduce new problems. Patients will click through screens without reading them. I implemented a required-fields system that blocks completion until every section has at least one entry, but even that doesn't catch people who type "none" for everything. For the medication section specifically, I added a photo upload requirement that triggered a flag for my staff to review before the provider sees the chart. That took about forty-five seconds per patient during intake and eliminated the entire class of errors from vague or omitted medication data.
What Works in Practice
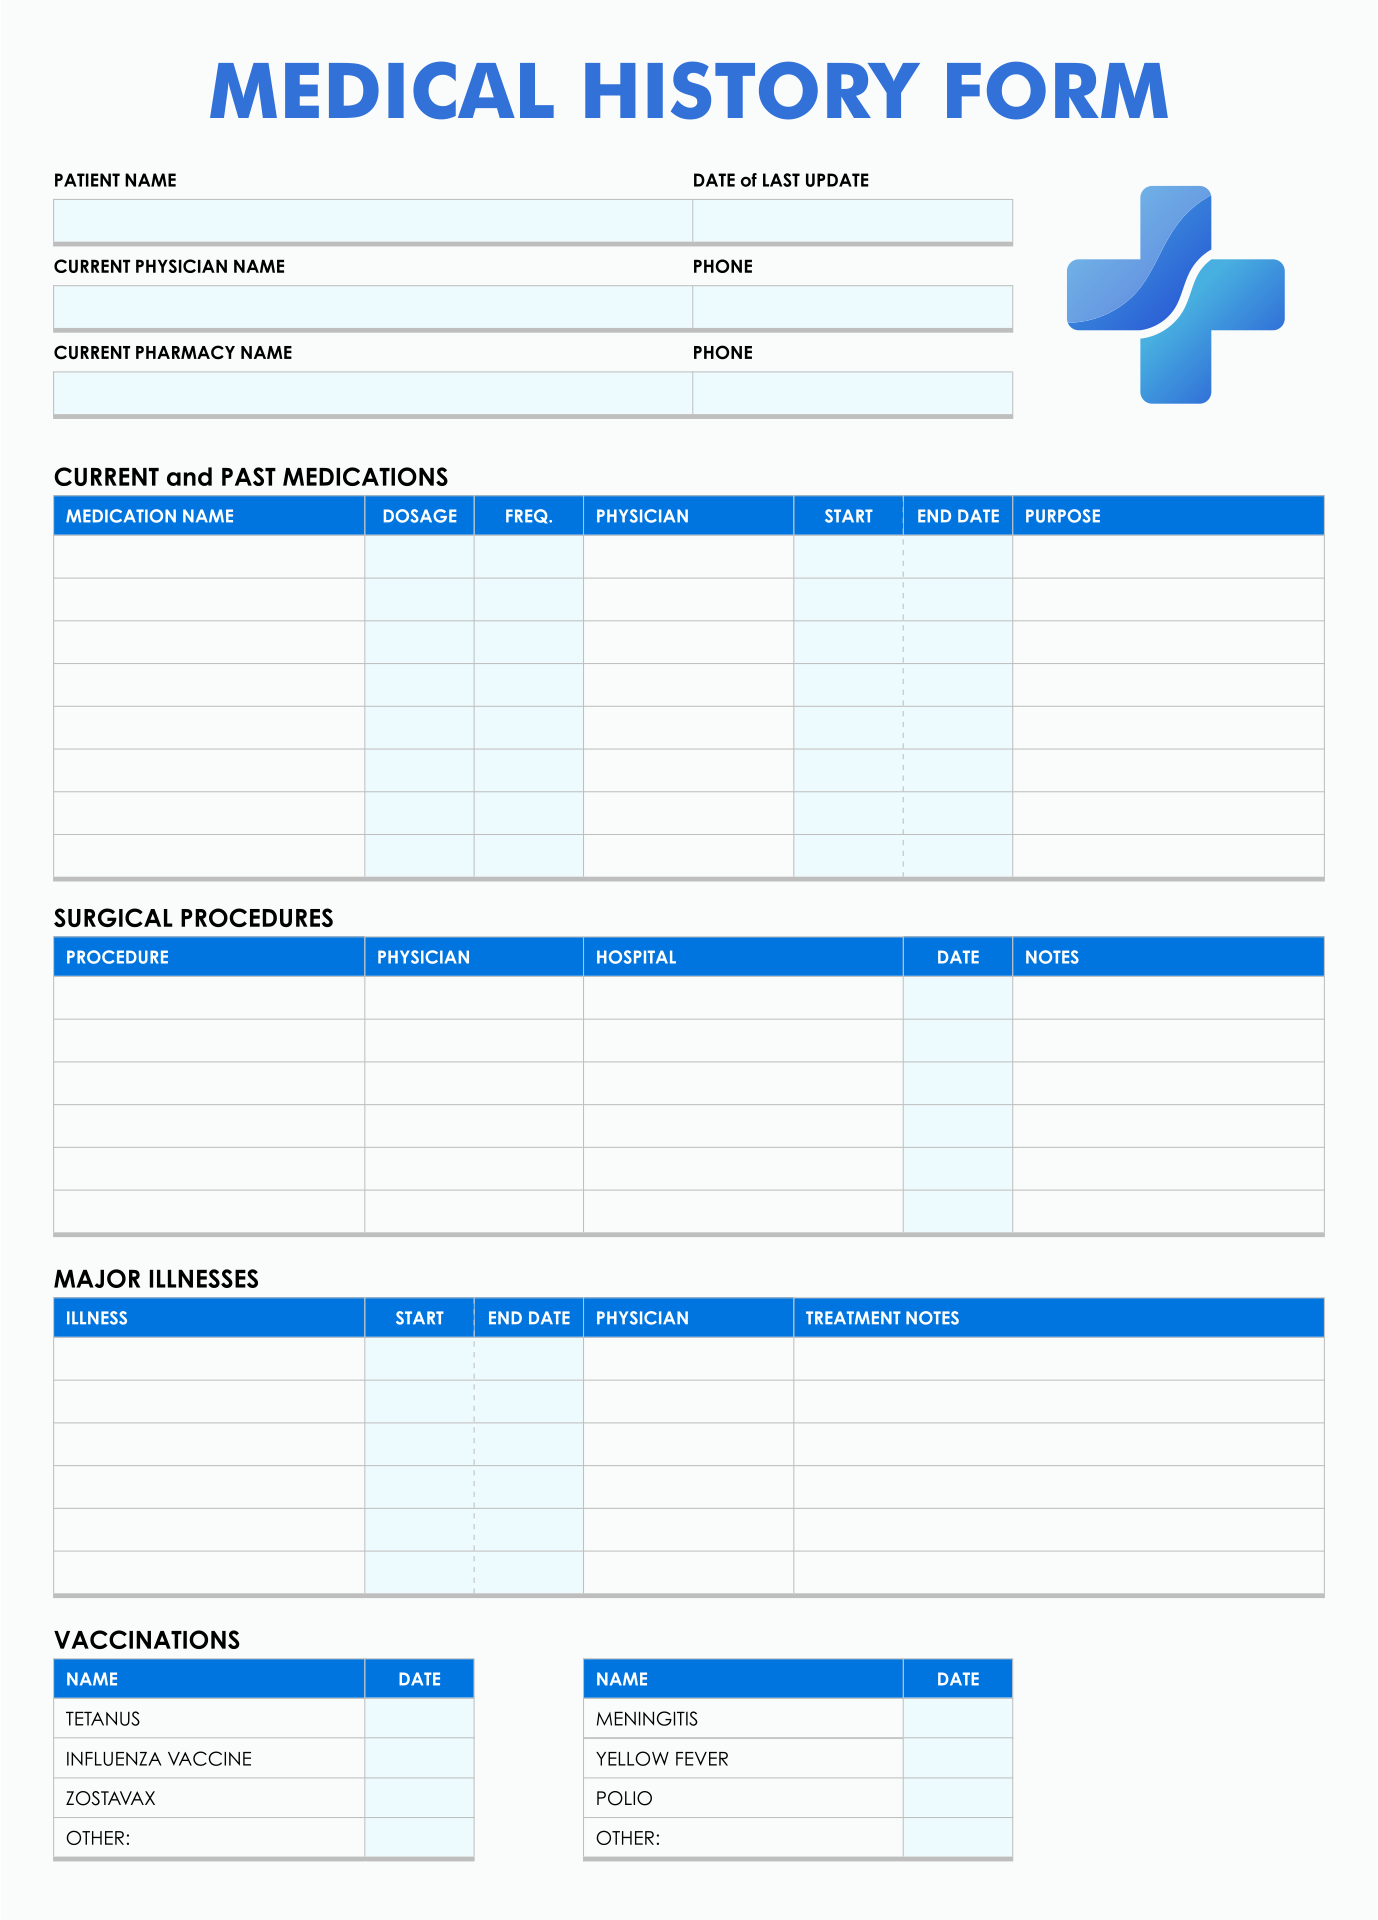
My current setup uses a hybrid approach. The form lives in our EHR as a structured template but the intake process has two stages. Stage one is the patient-facing form they complete before the appointment. Stage two is a five-minute verbal verification with the medical assistant who crosses off anything that looks inconsistent or incomplete. This verbal check catches an average of two incorrect or missing items per patient before the provider ever sees the record. The form takes patients approximately eight to twelve minutes to complete depending on complexity. A straightforward annual physical usually lands around eight minutes. A new patient with multiple chronic conditions and a full medication list can push it toward fifteen. I'd estimate this saves the provider roughly twelve to fifteen minutes of chart review time compared to piecing together history from memory and scattered prior records. That adds up across a full schedule without being dramatic about it. One edge case that costs me time and attention involves polypharmacy patients on nine or more medications. The standard medication table on the form breaks down at that point. Columns get cramped, dosages get lost, and interactions become harder to spot visually. I created a secondary medication log sheet that pulls out for those cases. It's a simple list format with columns for drug, dose, route, frequency, indication, and prescriber. The assistant fills it in while the patient reads through their bottles. It takes three minutes and gives me a clean view that the main form can't provide at that volume. If a patient is on nine or more regular medications, this secondary sheet becomes standard procedure rather than an exception.
Alternatives Worth Considering
Some clinics skip the paper form entirely and go straight to a tablet-based questionnaire that feeds into the EHR automatically. This works well for low-acuity practices but creates compliance gaps. Elderly patients or those with limited digital literacy will rush through a tablet form and produce worse data than a thoughtfully designed paper version. If your patient population skews older or less comfortable with technology, the paper or hybrid approach described above tends to outperform pure digital. There's no universal right answer here. It depends entirely on who sits in your waiting room. A few practices I know have tried using AI-powered pre-visit questionnaires that analyze responses and flag potential issues before the provider walks in. The technology exists but the accuracy is inconsistent. I tested this for about three months and found that the flags it generated were useful maybe sixty percent of the time. The other forty percent required follow-up that took longer than just reading the form myself. I discontinued that particular workflow. The core principle that makes any Medical History Form work is the same regardless of format: structure the questions so the patient cannot give a vague answer, build in verification steps that catch omissions, and design the layout to surface the most clinically critical information first. Everything else is decoration.