What This Job Actually Looks Like Day-to-Day
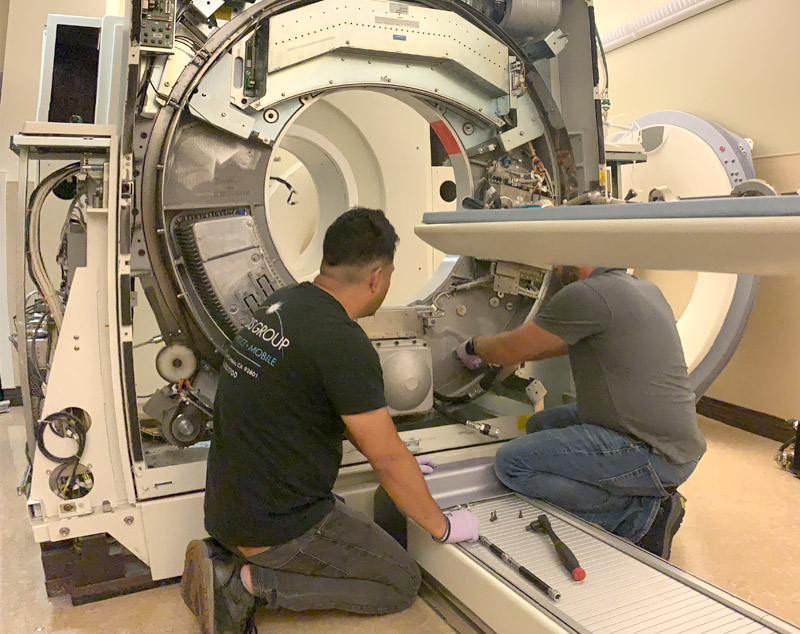
You walk into a hospital at 6 AM because the CT scanner in room 3 has been throwing error code 447 since last night, and the radiology department has a full schedule. You pull up the service manual on your laptop, dig through forty pages of schematics, and figure out that a $12 relay on the high-voltage generator board is intermittent. Replaced it, ran the test sequence, the scanner was back online by 7:45. That's the job. Most of it is reading documentation someone three states away wrote, cross-referencing with boards from three different manufacturers, and figuring out why the thing you just installed still isn't talking to the rest of the system. The training to get here isn't mostly classroom time. It's sitting next to someone who's done this for twelve years while they point at a multimeter and say "watch this" without explaining anything else. The real curriculum happens when the vendor rep leaves the building and you're alone with a machine that costs more than a house and a manual that assumes you already know things you don't know yet.How Medical Imaging Repair Technician Training Actually Works
Most formal programs are six months to two years, split between technical coursework and supervised field hours. Community colleges and vocational schools offer the closest thing to a standard path. You'll cover electronics fundamentals, circuit analysis, digital logic, and medical physics basics—enough to understand what's happening inside an MRI gradient coil or a CT X-ray tube without needing a physics degree. Radiology equipment courses come next: modality-specific breakdowns of how MR, CT, X-ray, fluoroscopy, and ultrasound systems actually function from an engineering standpoint. The part that separates people who last in this field from the ones who quit within six months is the hands-on component. A good program puts you in a lab with decommissioned or training units where you can take things apart without someone calling compliance on you. You should be soldering SMD components on actual imaging boards, running signal traces with an oscilloscope, and learning diagnostic software that manufacturers treat like proprietary religion. After that comes the field portion. You're paired with a senior technician and you ride along. First few months you're mostly fetching parts and holding the flashlight. By month six you're doing board-level replacements under supervision. The training clock doesn't truly stop until you've independently resolved at least thirty unique fault scenarios across multiple vendors and modalities. That timeline varies wildly depending on whether your employer lets you touch machines or just makes you watch.Specific thing most programs skip: PACS and modality integration. You'll be told this is "networking" and someone else handles it. It's not someone else's job. When a PET/CT loses DICOM connectivity to the archive, you need to know whether it's a network config issue, a SOP instance mismatch, or a corrupted routing table in the modality's interface engine. I learned this the hard way on a GE Signa 1.5T where the techs kept paging me saying the scanner was "down." It wasn't down. The worklist routing had been silently dropped after a firewall rule change in IT. Sat there for two hours before someone on my shift mentioned checking the HL7 gateway. Could have been twenty minutes if I'd thought to look there first.
There's also the certification question. The ARRT in RadTech is for technologists, not repair techs. The answer for equipment repair is the AART credential or the manufacturer-specific certifications—GE, Siemens, Philips each run their own training pipelines and they're not interchangeable. A Siemens field engineer can't just flip over to a Varian linac without going through that vendor's program. Some smaller hospitals and third-party service organizations accept a combination of education plus logged experience in lieu of formal certification, but the larger the contract, the more rigid the requirements become.The Real Skills You Need Beyond the Classroom
Reading an schematic for a (Philips) CT tube control board from 2008 requires a different mental muscle than troubleshooting a GE Discovery MR750 receiver coil array. The drawings aren't consistent. Wire color conventions change between manufacturers and sometimes between product lines from the same company. The symbol standards shift. You'll spend a lot of time figuring out that "J7" on page 312 of the service manual is the connector you've been calling "the big white thing near the bottom left" and that it maps to pin 4 on the daughter board, not pin 3 like the replacement manual says. You also need to understand patient safety implications of your work. A grounded chassis on a patient bed isn't a minor inconvenience. It's a class 1 electrical hazard. An arcing high-voltage connector in a CT gantry isn't a quality issue. It's a fire risk during a scan with a patient inside the bore. The training should hammer this into you repeatedly, and honestly the best way it gets hammered is watching a senior tech shut down a machine and walk away from it because a ground fault test came back at 0.8 milliamps instead of the required 5 milliamps or less.Here's the workaround I used that never showed up in any manual: on a Canon Aquilion One CT, the cooling system for the tube rotor kept throwing thermal faults every forty-five minutes during busy mornings. The error pointed at the oil cooler fan motor. Replaced the fan, same problem. Replaced the control board, same problem. What actually killed the tube was a degraded thermal paste on the stator temperature sensor—that sensor sits right against the winding pack and the paste had pumped out over seven years of thermal cycling. Temp readings lagged by twelve seconds, so the system thought the tube was fine while it was actually approaching threshold. Fresh paste plus recalibrating the sensor offset in the service menu solved it permanently. The service bulletin came out six months later acknowledging the exact same issue. I figured it out because I'd done the same repair on a Toshiba equivalent model a year earlier and the thermal behavior looked identical even though the error codes were completely different.
Common Pitfalls for People Starting Out
The biggest mistake is treating every symptom as a parts swap opportunity. A bad image artifact on an MRI isn't always a faulty shim coil. Sometimes it's a loose grounding strap on the RF shield door, sometimes it's a water chiller temperature drift of two degrees that throws off the gradient pre-emphasis, sometimes it's a firmware version that had a known phase-encoding bug in a specific pulse sequence. If you only swap parts, you'll burn through inventory and still not fix the underlying problem. The second mistake is skipping the safety checks because everyone's in a hurry. You will get called back to a machine you already signed off on because a patient is reporting a tingling sensation on the table. That tingling is almost always a leakage current issue. It comes from a missing ground, a cracked insulation layer on the patient couch wiring harness, or a ground loop between the scanner and the peripheral equipment. Going back to check those things takes forty-five minutes. Not doing it and getting sued takes forty-five years. The third mistake is trusting the error code more than your own measurements. Service manuals are written by engineers who tested the system under ideal conditions. Hospital environments are not ideal. Voltage sags from nearby equipment, EMI from faulty lighting ballasts, RF interference from wireless cameras—all of this shows up as equipment errors that have nothing to do with the actual hardware. I once spent three hours replacing a faulty analog-to-digital converter board on a linear accelerator before an electrician wandering by asked what the line voltage looked like during operation. It was brownout territory every time the HVAC kicked on. The ADC wasn't bad. The supply voltage was just too low for clean conversion. New board wouldn't have fixed anything.What Good Training Should Include
A solid program covers electrical safety standards—NFPA 70E, IEC 60601 series, facility grounding requirements. It teaches you how to read and interpret electromagnetic compatibility test results. It includes exposure to at least two major manufacturers' platforms so you're not locked into one ecosystem. It should give you real access to diagnostic software, not just simulations. And it should include the soft skills of dealing with frustrated clinicians who need their equipment working yesterday while you're waiting on a $4,000 part to arrive from a warehouse in another state.The downtime math matters more than anything else in this field. A single CT scanner out of service in a busy hospital costs roughly $2,000 to $5,000 per hour in lost revenue, not counting the downstream impact on patient scheduling and staff overtime. Getting good at diagnosis quickly isn't a nice-to-have. It's the difference between being the person they call and the person they replace.
Get the Full Details