Running the Numbers When the Patient Is at the Bedside
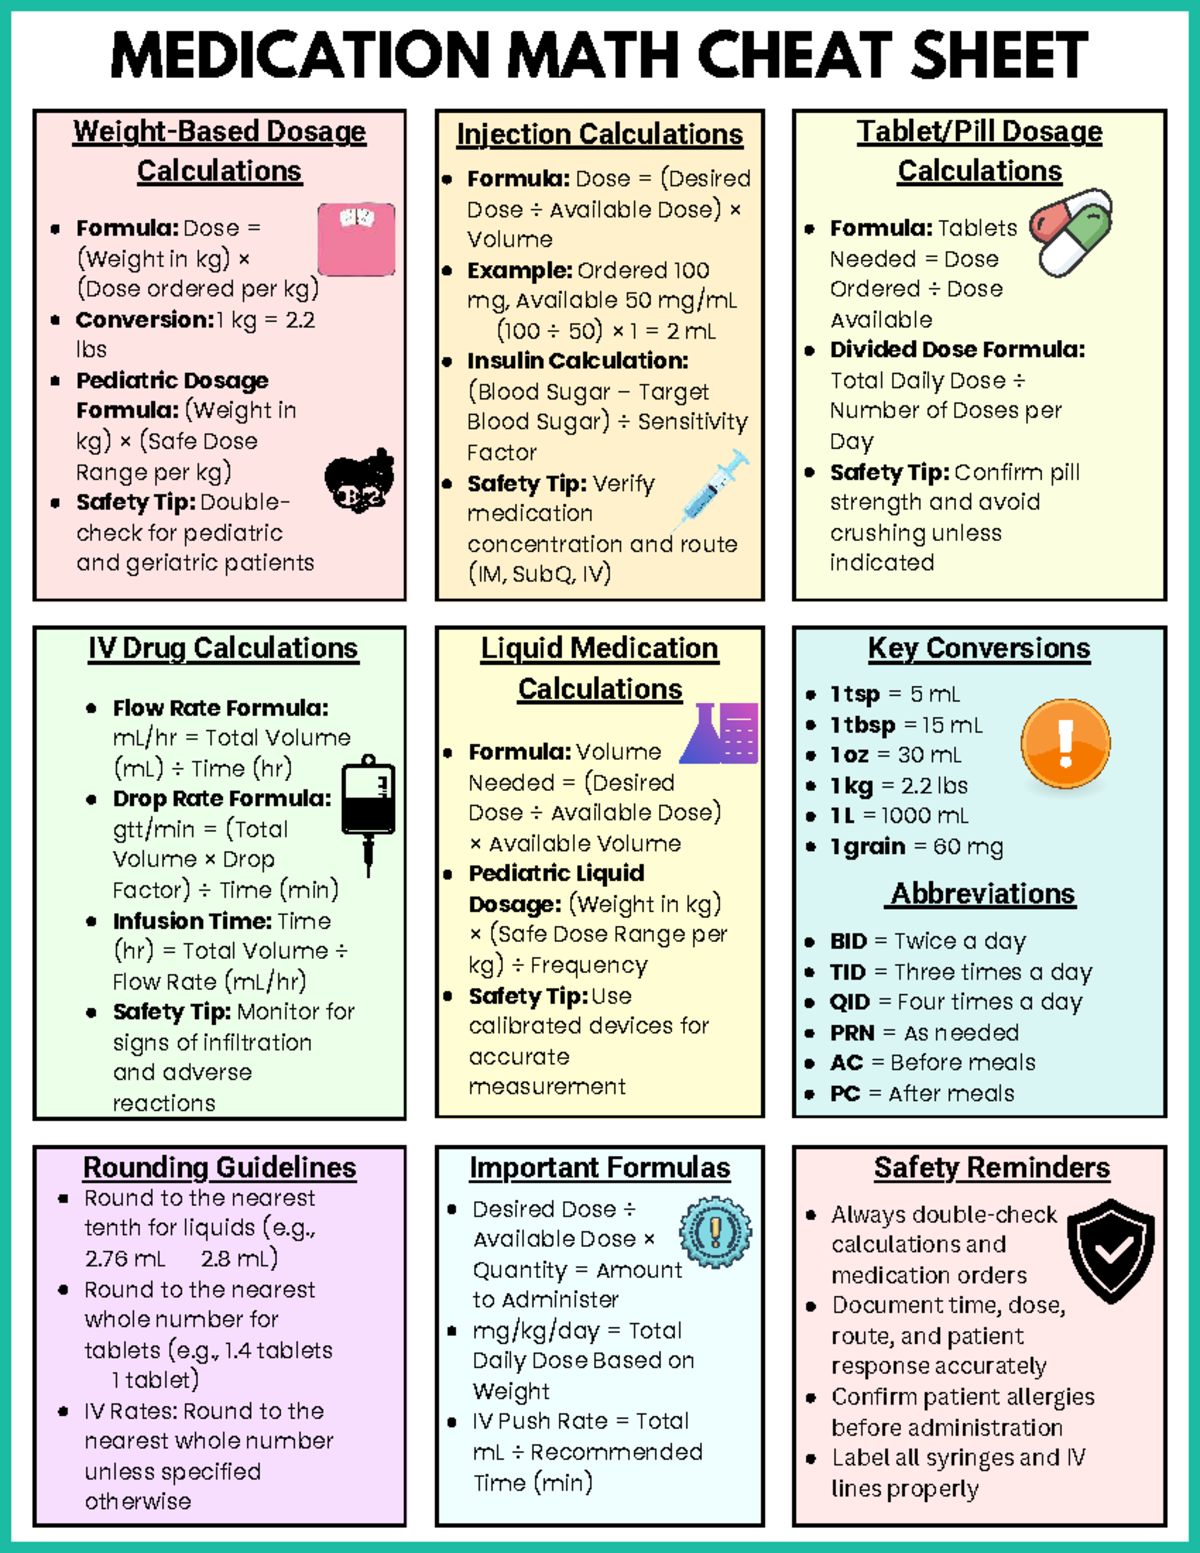
Dosage calculations are one of those things where everyone learns the basics in nursing school and then never thinks about them again until they need them at 2 AM with a code blue on the phone. That gap between the textbook example and the real thing is where mistakes happen. I want to talk about how Medical Mathematics And Dosage Calculations actually works when you are dealing with a real patient, not a diagram. The core of Medical Mathematics And Dosage Calculations comes down to three approaches. Dimensional analysis, the ratio and proportion method, and the formula method. Most people pick one and stick with it. I recommend learning all three because each one handles certain edge cases better than the others. The formula method is D over D times Q, which sounds helpful until you forget what D, D, and Q stand for under stress. Dimensional analysis is cleaner once you get it because it tracks units from start to finish. If your final unit is milliliters and your starting unit was milligrams and the order was in micrograms, the dimensional analysis chain will show you immediately that you missed a conversion step. That is its real value. Ratio and proportion is the method most people grew up with. It is straightforward but it can mask unit mismatches if you are not careful. The setup A over B equals C over D works fine when everything is in the same units. It fails silently when they are not. I have seen that happen. A physician ordered 0.5 mg of a drug and the vial was labeled in micrograms. The nurse set up the proportion correctly on paper but carried the wrong unit forward through the calculation. The result looked plausible until the pump was running.
Common Pitfalls That Cost Time and Sleep
The first category of error is unit conversion. Milligrams to grams, micrograms to milligrams, international units to milligrams. These are trivial conversions that become expensive when you are tired. The second category is decimal placement. A dose written as 0.05 mg is ten times smaller than 0.5 mg. On paper they look almost identical. The third category is concentration changes. A solution labeled 2 percent means 2 grams per 100 milliliters. That is 20 mg per mL. People memorize the shortcut and apply it to something that is not actually a weight per volume ratio. IV flow rate calculations introduce a fourth variable: drop factor. Macrodrop sets are usually 10, 15, or 20 drops per milliliter. Microdrop or minidrop sets are 60 drops per milliliter. If you use the wrong drop factor in the formula, your entire calculation is off by a factor of four or six. This is not theoretical. I watched a resident calculate a dopamine drip using 20 gtt per mL when the tubing in the cabinet was clearly marked 60 gtt per mL. The patient received a third of the intended dose. The error was caught before clinical effect became obvious, but it could have been worse.
A Problem I Actually Faced
Here is a specific case. A patient was on continuous renal replacement therapy. The order was for vancomycin dosing based on actual body weight, but the pharmacy supplied a formulation that needed reconstitution, and the concentration changed depending on which diluent you used. The order said 15 mg per kg every 24 hours. The patient weighed 82 kilograms. The math itself was simple. Eighty-two times 15 is 1230 milligrams. The problem was that the vancomycin vial was 500 mg and you had to draw from a stock solution that had been prepared at a non-standard concentration because the original manufacturer had changed the formulation. The Pharmacy had documented the concentration as 10 mg per mL in the system, but the preparation log showed 8.3 mg per mL. I pulled the actual preparation label, recalculated the volume needed at 8.3 mg per mL, and got 148 mL instead of 123 mL. That is roughly a 20 percent difference. If I had used the system concentration without verifying against the physical preparation, the patient would have received a significantly underdosed regimen for a drug with a narrow therapeutic index. Therapeutic drug monitoring changes the whole landscape. Vancomycin troughs, aminoglycoside peaks and troughs, phenytoin levels. These require you to understand pharmacokinetics, not just arithmetic. The half-life of a drug in a patient with normal renal function is very different from the half-life in a patient on hemodialysis. If you calculate a loading dose using standard kinetics in a dialysis patient, you will overdosing. The correction factor for CrCl less than 30 mL per minute on a standard vancomycin regimen is not in most quick-reference guides. You have to look it up or derive it. Burn patients are another category where standard calculations fail. Fluid shifts in major burns change the volume of distribution for many drugs. The standard dosing for heparin or insulin in a burn patient with greater than 20 percent total body surface area burns will be wrong because the patient is in a hyperdynamic state with increased capillary leak. I once calculated a heparin infusion for a burn patient using the standard weight-based nomogram and the partial thromboplastin time came back subtherapeutic on the first draw. The dose needed to be increased by about 40 percent because the volume of distribution was expanded. The textbook method did not account for this.
Get the Full Details

Pediatric dosing introduces body surface area as a second parameter. Many drug labels give adult doses only. The child's dose is not simply a fraction of the adult dose based on weight. The BSA method is more accurate. A child with a BSA of 0.6 square meters receiving a drug with an adult dose based on 1.73 square meters gets approximately 35 percent of the adult dose, not 50 percent even if the child weighs half an adult. Weight-based pediatric dosing is easier to calculate but less accurate for drugs with nonlinear pharmacokinetics.
Where These Methods Break Down Completely
Dimensional analysis fails when the relationship between variables is not linear. Warfarin dosing is a good example. There is no formula that takes INR and outputs the next dose. The relationship is logarithmic and patient-specific. Ratio and proportion fails when you are dealing with rates that change over time, like insulin drips where the glucose response is not proportional to the insulin rate. The formula method fails when you do not know which variables belong in the formula or when the formula assumes conditions that are not present in your patient. Drug calculations for medications with extremely narrow therapeutic windows, like digoxin or lithium, should never rely on mental math alone. The margin between a therapeutic dose and a toxic dose can be smaller than the rounding error in a quick calculation. Always verify these with a calculator or a validated dosing tool. The same applies to chemotherapeutic agents. Body surface area calculations for chemo are done twice by independent clinicians because the consequences of a single decimal error are catastrophic.
Practical Workflow That Actually Works
Here is how I approach a dosage calculation now. First, I write down the order exactly as written, including the unit. Second, I identify the available concentration from the package insert or the pharmacy label, not from memory. Third, I convert all units to the same system before doing any math. Fourth, I set up the calculation using dimensional analysis so the unit tracking is explicit. Fifth, I verify the result against a reasonable range. If the answer seems outside what I would expect for that drug and that patient, I redo the calculation. Sixth, I document the calculation in the chart if the dose is non-standard or requires a deviation from the usual range. This takes about two to three minutes per calculation once you are comfortable with it. It is slower than doing mental math for simple cases but it prevents the kind of errors that make you want to quit the profession. The time investment pays for itself the first time you catch a unit mismatch before it reaches the patient.

Resources That Are Actually Useful
The Lexicomp drug database has a built-in dosage calculator that handles renal adjustments and pediatric dosing. The Epocrates app has a quick calculator section. For IV pump programming, most hospitals use standardized order sets that lock out impossible flow rates. This is a safety feature, not an inconvenience. If your calculation gives a rate that the pump will not accept, the system is telling you something is wrong. For learning purposes, the Davis Drug Guide has worked examples with dimensional analysis shown step by step. The Nursing Drug Handbook does the same. These are not glamorous resources but they are reliable. Avoid relying on memory for conversion factors. Memorize the common ones. Know where to look up the uncommon ones. The most important thing I can say about Medical Mathematics And Dosage Calculations is that the math itself is usually the easy part. The hard part is knowing when the math might be wrong because the assumptions behind it do not match the patient in front of you. A formula is a tool, not an authority. Use it, verify it, and question it when something feels off. That habit has kept my patients safe and my sleep intact.