When I first started working in clinical practice, I was constantly tripping over ear-related terminology. The anatomy is compact but dense, and patients tend to describe symptoms in lay terms that don't map neatly to diagnostic categories. Learning the proper medical names for ear structures and conditions isn't about memorizing Latin labels. It's about building a mental map you can navigate when someone says "my ear hurts" and you need to figure out whether that pain is otalgia, referred from the throat, or actually originating in the tympanic membrane.
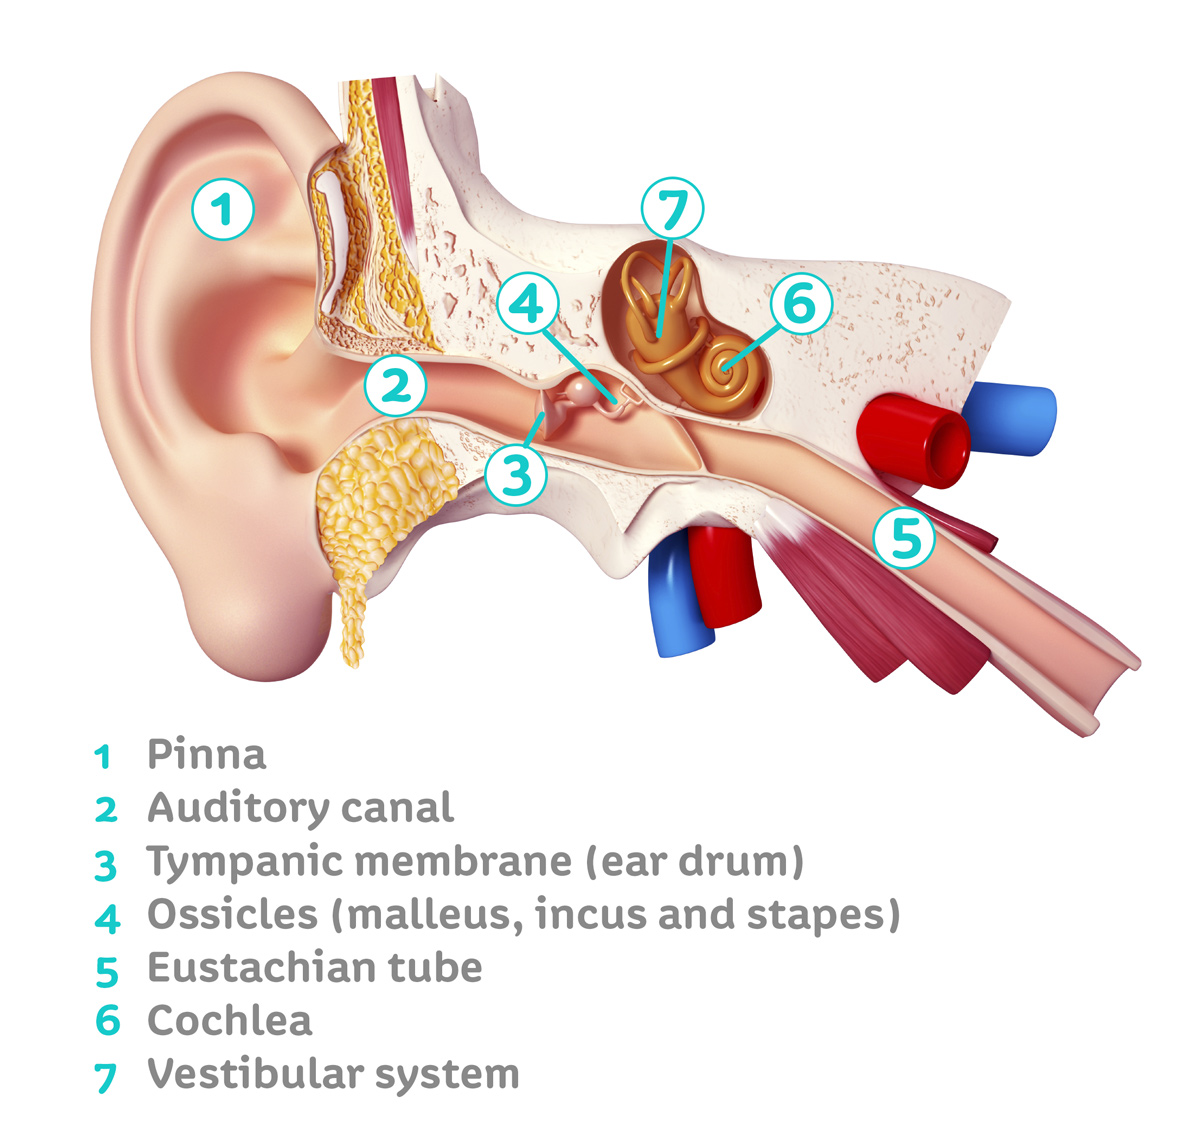
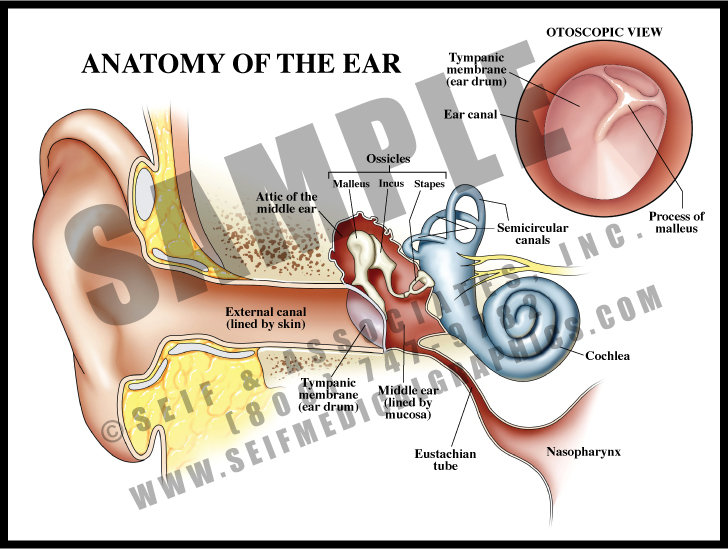
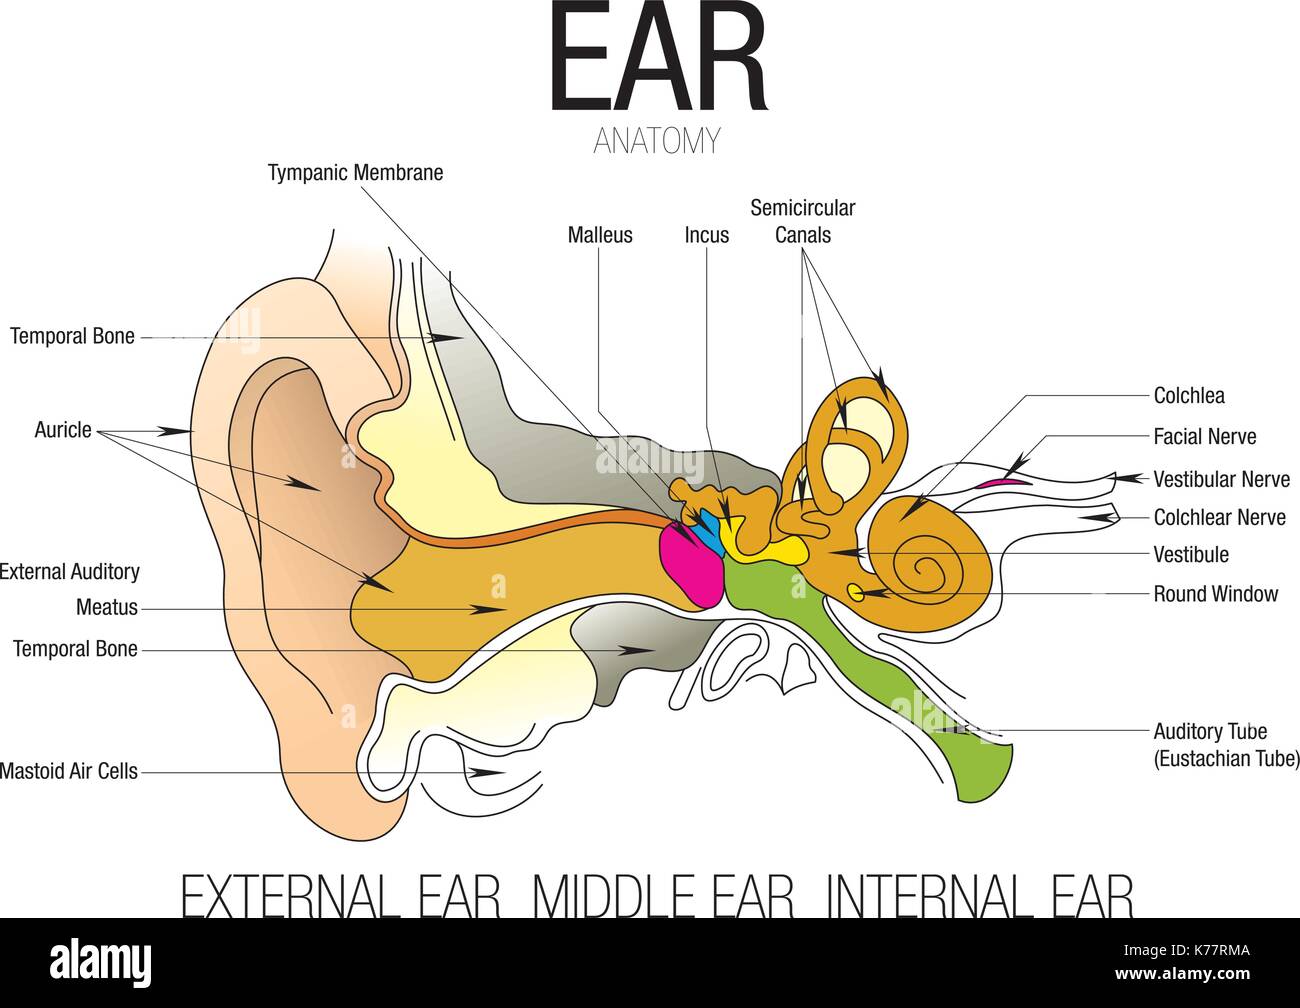
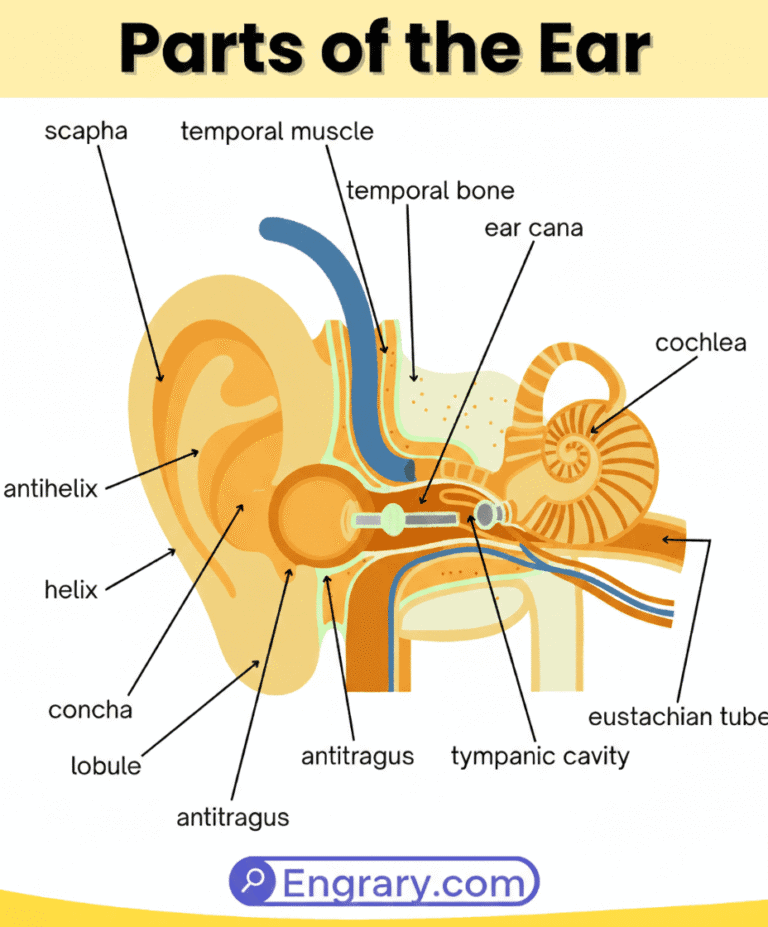
The ear divides into three main sections: external, middle, and internal. Each has its own vocabulary, and mixing them up leads to miscommunication. The external ear includes the pinna (that visible outer flap) and the external auditory canal. The middle ear contains the ossicles - malleus, incus, and stapes - plus the tympanic cavity and Eustachian tube. The internal ear houses the cochlea, vestibule, and semicircular canals, which handle hearing and balance respectively.
When I was in residency, I learned that medical students and even some rotating residents struggle with otitis media versus otitis externa distinctions. One afternoon, a patient came in complaining of "ear infection" with severe pain on pulling the pinna. That's a classic sign of otitis externa, not otitis media. Pulling the pinna stretches the inflamed skin of the external canal in otitis externa, causing sharp pain. In otitis media, the infection sits behind the eardrum, so manipulation of the outer ear doesn't change the pain level. This simple physical exam maneuver saved me from prescribing unnecessary antibiotics for a fungal case that needed topical antifungals instead.
Common Medical Name For Ear Infections and What They Actually Are
Otitis media is the most common ear condition I encounter, especially in pediatric clinics. The full medical term breaks down to "inflammation of the middle ear." Acute otitis media presents with fever, ear pain, and sometimes temporary hearing loss. Chronic otitis media with effusion involves fluid persistence without active infection, which is why some kids need ventilation tubes rather than more antibiotics.
Otitis externa, often called swimmer's ear, affects the canal skin. Pseudomonas and Staphylococcus are the usual bacterial culprits. I once had a diabetic patient whose otitis externa refused to resolve despite appropriate topical antibiotics. The issue was malignant otitis externa, an invasive infection spreading toward the skull base. We ended up referring to infectious disease for prolonged intravenous antipseudomonal therapy. Recognizing that risk factor early - diabetes in an older adult with refractory otitis externa - changes the entire treatment trajectory.
Tinnitus isn't a disease but a symptom. Patients describe it as ringing, buzzing, or hissing in one or both ears. Somatic tinnitus responds to jaw or neck manipulation, which tells you the generator sits somewhere in the sensorimotor pathways. I had a patient whose tinnitus changed pitch every time she clenched her teeth. That's a clear sign of somatic modulation, and treating the temporomandibular joint disorder reduced her tinnitus burden significantly.
Naming Ear Structures in Clinical Documentation
Proper documentation requires precise terminology. The tympanic membrane has four quadrants: anterior inferior, anterior superior, posterior inferior, and posterior superior. Anterior inferior quadrant perforations tend to be chronic and less likely to heal spontaneously. When I chart, I specify the quadrant, size, and whether the ossicles are visible through the perforation. This level of detail matters for surgical planning.
The Eustachian tube connects the middle ear to the nasopharynx. Its function isn't just pressure equalization. It also protects the middle ear from nasopharyngeal secretions and provides mucociliary clearance. When I explain this to patients with recurrent otitis media, they understand why adenoidectomy sometimes helps children whose Eustachian tube dysfunction stems from adenoid hypertrophy.
The cochlea contains approximately 16,000 hair cells. Outer hair cells amplify sound; inner hair cells transmit auditory signals to the brainstem. Sensorineural hearing loss affects these structures or the auditory nerve. Noise-induced hearing loss typically shows a characteristic dip at 4000 Hz on audiometry. I tell my patients that this 4000 Hz notch is the audiologist's fingerprint of acoustic trauma, appearing before it spreads to adjacent frequencies.
When Medical Names For Ear Procedures Matter
Tympanoplasty repairs tympanic membrane perforations. Myrin grafts use temporalis fascia to patch holes under 50% of the membrane surface. Cartilage tympanoplasty works better for larger perforations or when the middle ear mucosa is unhealthy. I prefer interpositional cartilage techniques for young patients because the cartilage remodels over years without re-perforating.
Mastoidectomy removes diseased air cells from the mastoid process. The cortical mastoidectomy preserves posterior canal wall anatomy. The canal wall down mastoidectomy removes the posterior canal wall, creating a common cavity between the ear canal and mastoid. I explain to patients that the canal wall down approach gives better visualization for cholesteatoma removal but requires lifelong ear canal cleaning.
Stapedotomy treats otosclerosis by replacing the fixed stapes footplate with a prosthesis. Modern practice uses hydroxyapatite or titanium pistons. The success rate for improving bone conduction thresholds exceeds 90 percent in experienced hands. I counsel patients that postoperative dizziness usually resolves within days, but persistent vertigo warrants MRI to rule out perilymph fistula.
Distinguishing Otalgia Sources
Primary otalgia originates in the ear. Referred otalgia comes from cranial nerves sharing sensory pathways. The glossopharyngeal nerve (CN IX) and vagus nerve (CN X) supply both the ear and the oropharynx, which explains why throat cancer sometimes presents as isolated ear pain. I learned this the hard way when a smoker complained of right ear pain with a normal otoscopic examination. A flexible nasopharyngoscopy revealed a concealed squamous cell carcinoma at the base of the tongue. Treating only the ear would have missed a life-threatening diagnosis.
Trigeminal neuralgia causes paroxysmal facial pain that sometimes references to the ear. Carbamazepine or oxcarbazepine typically control the seizures. If medications fail, microvascular decompression offers long-term relief. I always check dental sources before attributing ear pain to neuralgia. An abscessed mandibular molar can refer pain along V3, mimicking temporomandibular disorders.
Eagle syndrome results from elongated styloid processes irritating adjacent nerves and vessels. Patients describe throat pain, dysphagia, and referred otalgia. Lateral neck radiographs or CT angiography confirm the diagnosis. I once managed a patient whose symptoms persisted despite multiple antibiotic courses for presumed chronic otitis media. The styloid process measured 4 centimeters on CT - well beyond the 3 centimeter threshold. Styloidectomy resolved her symptoms completely.
Practical Tips For Accurate Terminology
Use ICD-10 codes when documenting for billing. H65.9 covers unspecified acute otitis media. H66.9 covers unspecified chronic otitis media. These codes matter less for clinical reasoning but affect reimbursement and epidemiological tracking.
When discussing conditions with patients, translate medical terminology into functional language. Saying "fluid behind your eardrum" conveys more than "otitis media with effusion." The medical name carries precision; the plain language carries understanding. I use both depending on who's listening.
Specialists in otolaryngology rely on standardized nomenclature from the American Academy of Otolaryngology. Keeping current with these updates prevents confusion when collaborating with colleagues. The terminology shifts gradually as imaging and surgical techniques evolve. What we called "chronic suppurative otitis media" twenty years ago now gets subdivided into safe and unsafe types based on cholesteatoma presence.
Common Pitfalls In Ear Diagnosis
Assuming all ear pain means infection. Otoscopic examination reveals normal tympanic membranes in most cases of referred otalgia. Don't prescribe antibiotics without confirming middle ear inflammation. Tympanometry showing type B curves indicates fluid or perforation; type A curves suggest normal middle ear function. When I see normal tympanograms paired with severe pain, I look elsewhere for the source.
Missing cerumen impaction behind an intact tympanic membrane. Bulky earwax can cause conductive hearing loss, tinnitus, and discomfort that mimics middle ear pathology. I use microscopic suction or irrigation to remove impacted cerumen before committing to further workup. One afternoon, a "chronic otitis media" case turned out to be just a wax plug. Removing it restored hearing immediately and eliminated the need for myringotomy.
Overinterpreting mild tympanic membrane erythema. Redness alone doesn't diagnose acute otitis media. The American Academy of Pediatrics criteria require bulging plus effusion signs. I learned this during quality improvement audits showing excessive antibiotic prescribing for viral upper respiratory infections with incidental erythema. Strict adherence to bulging criteria reduced our acute otitis media antibiotic rates by nearly forty percent over six months.
Ear Anatomy Quick Reference
Pinna or auricle collects sound waves. External auditory canal transmits them to the tympanic membrane. The membrane vibrates, transferring energy through ossicles to the oval window. Cochlear fluids move, stimulating hair cells that fire auditory nerve fibers. Signals travel through brainstem nuclei to the auditory cortex.
Eustachian tube opens during swallowing and yawning. This equalizes middle ear pressure and drains mucosal secretions. Dysfunction causes negative pressure, effusion, and susceptibility to infection. Adenoid hypertrophy obstructs the nasopharyngeal opening in children. Allergic inflammation thickens mucosal linings in adults.
The vestibular system includes three semicircular canals oriented in orthogonal planes. Each detects angular acceleration in its plane. The utricle and saccule sense linear acceleration and gravity. Lesions here cause vertigo, nystagmus, and imbalance. Caloric testing with warm and cold water or air stimulates each ear separately, revealing unilateral vestibular weakness.
Advanced Considerations
Congenital aural atresia requires staged reconstruction. Atresiaplasty through postauricular approach works when the external canal dimensions are favorable. Bone conduction implants provide hearing rehabilitation when surgery isn't appropriate. I follow patients from infancy through adolescence, coordinating with audiology and speech therapy.
Choledomalacia of the middle ear causes conductive hearing loss through ossicular discontinuity or fixation. CT imaging shows erosion patterns that guide surgical repair. Autologous ossicular reconstruction uses carved cortical bone or homologous prostheses. Long-term patency depends on graft stability and middle ear mucosal health.
Glomus tumors arise from paraganglion cells near the jugular bulb or along the middle ear skeleton. Pulsatile tinnitus and reddish retrotympanic mass are characteristic. Biopsy is contraindicated due to vascularity. Preoperative embolization reduces intraoperative bleeding. Radiation therapy controls small residuals when surgery would damage adjacent nerves.
I've found that mastering medical names for ear conditions comes from repeated exposure to real cases. Reading about otitis media is different from examining ten acute cases in one clinic session. The terminology sticks when you need it urgently, not when you're passively studying. Keep a pocket reference for ICD-10 codes and anatomical landmarks. Use them until they become second nature.
Gallery Medical Name For Ear
Ear Parts Name : Ultimate Guide to Ear Anatomy with all Parts, Names & Diagram – AZBWA
Anatomy Of The Ear Sa Medical Graphics
Ear Parts Names | Human face: anatomy, structure and function – USYVDH
Parts Of The Ear With Labeled Diagram And Names • Engrary
Ear Anatomy Parts Structure Outer Middle: Vector có sẵn (miễn phí bản quyền) 1716359071