What Actually Matters When You're Doing a Patient Assessment
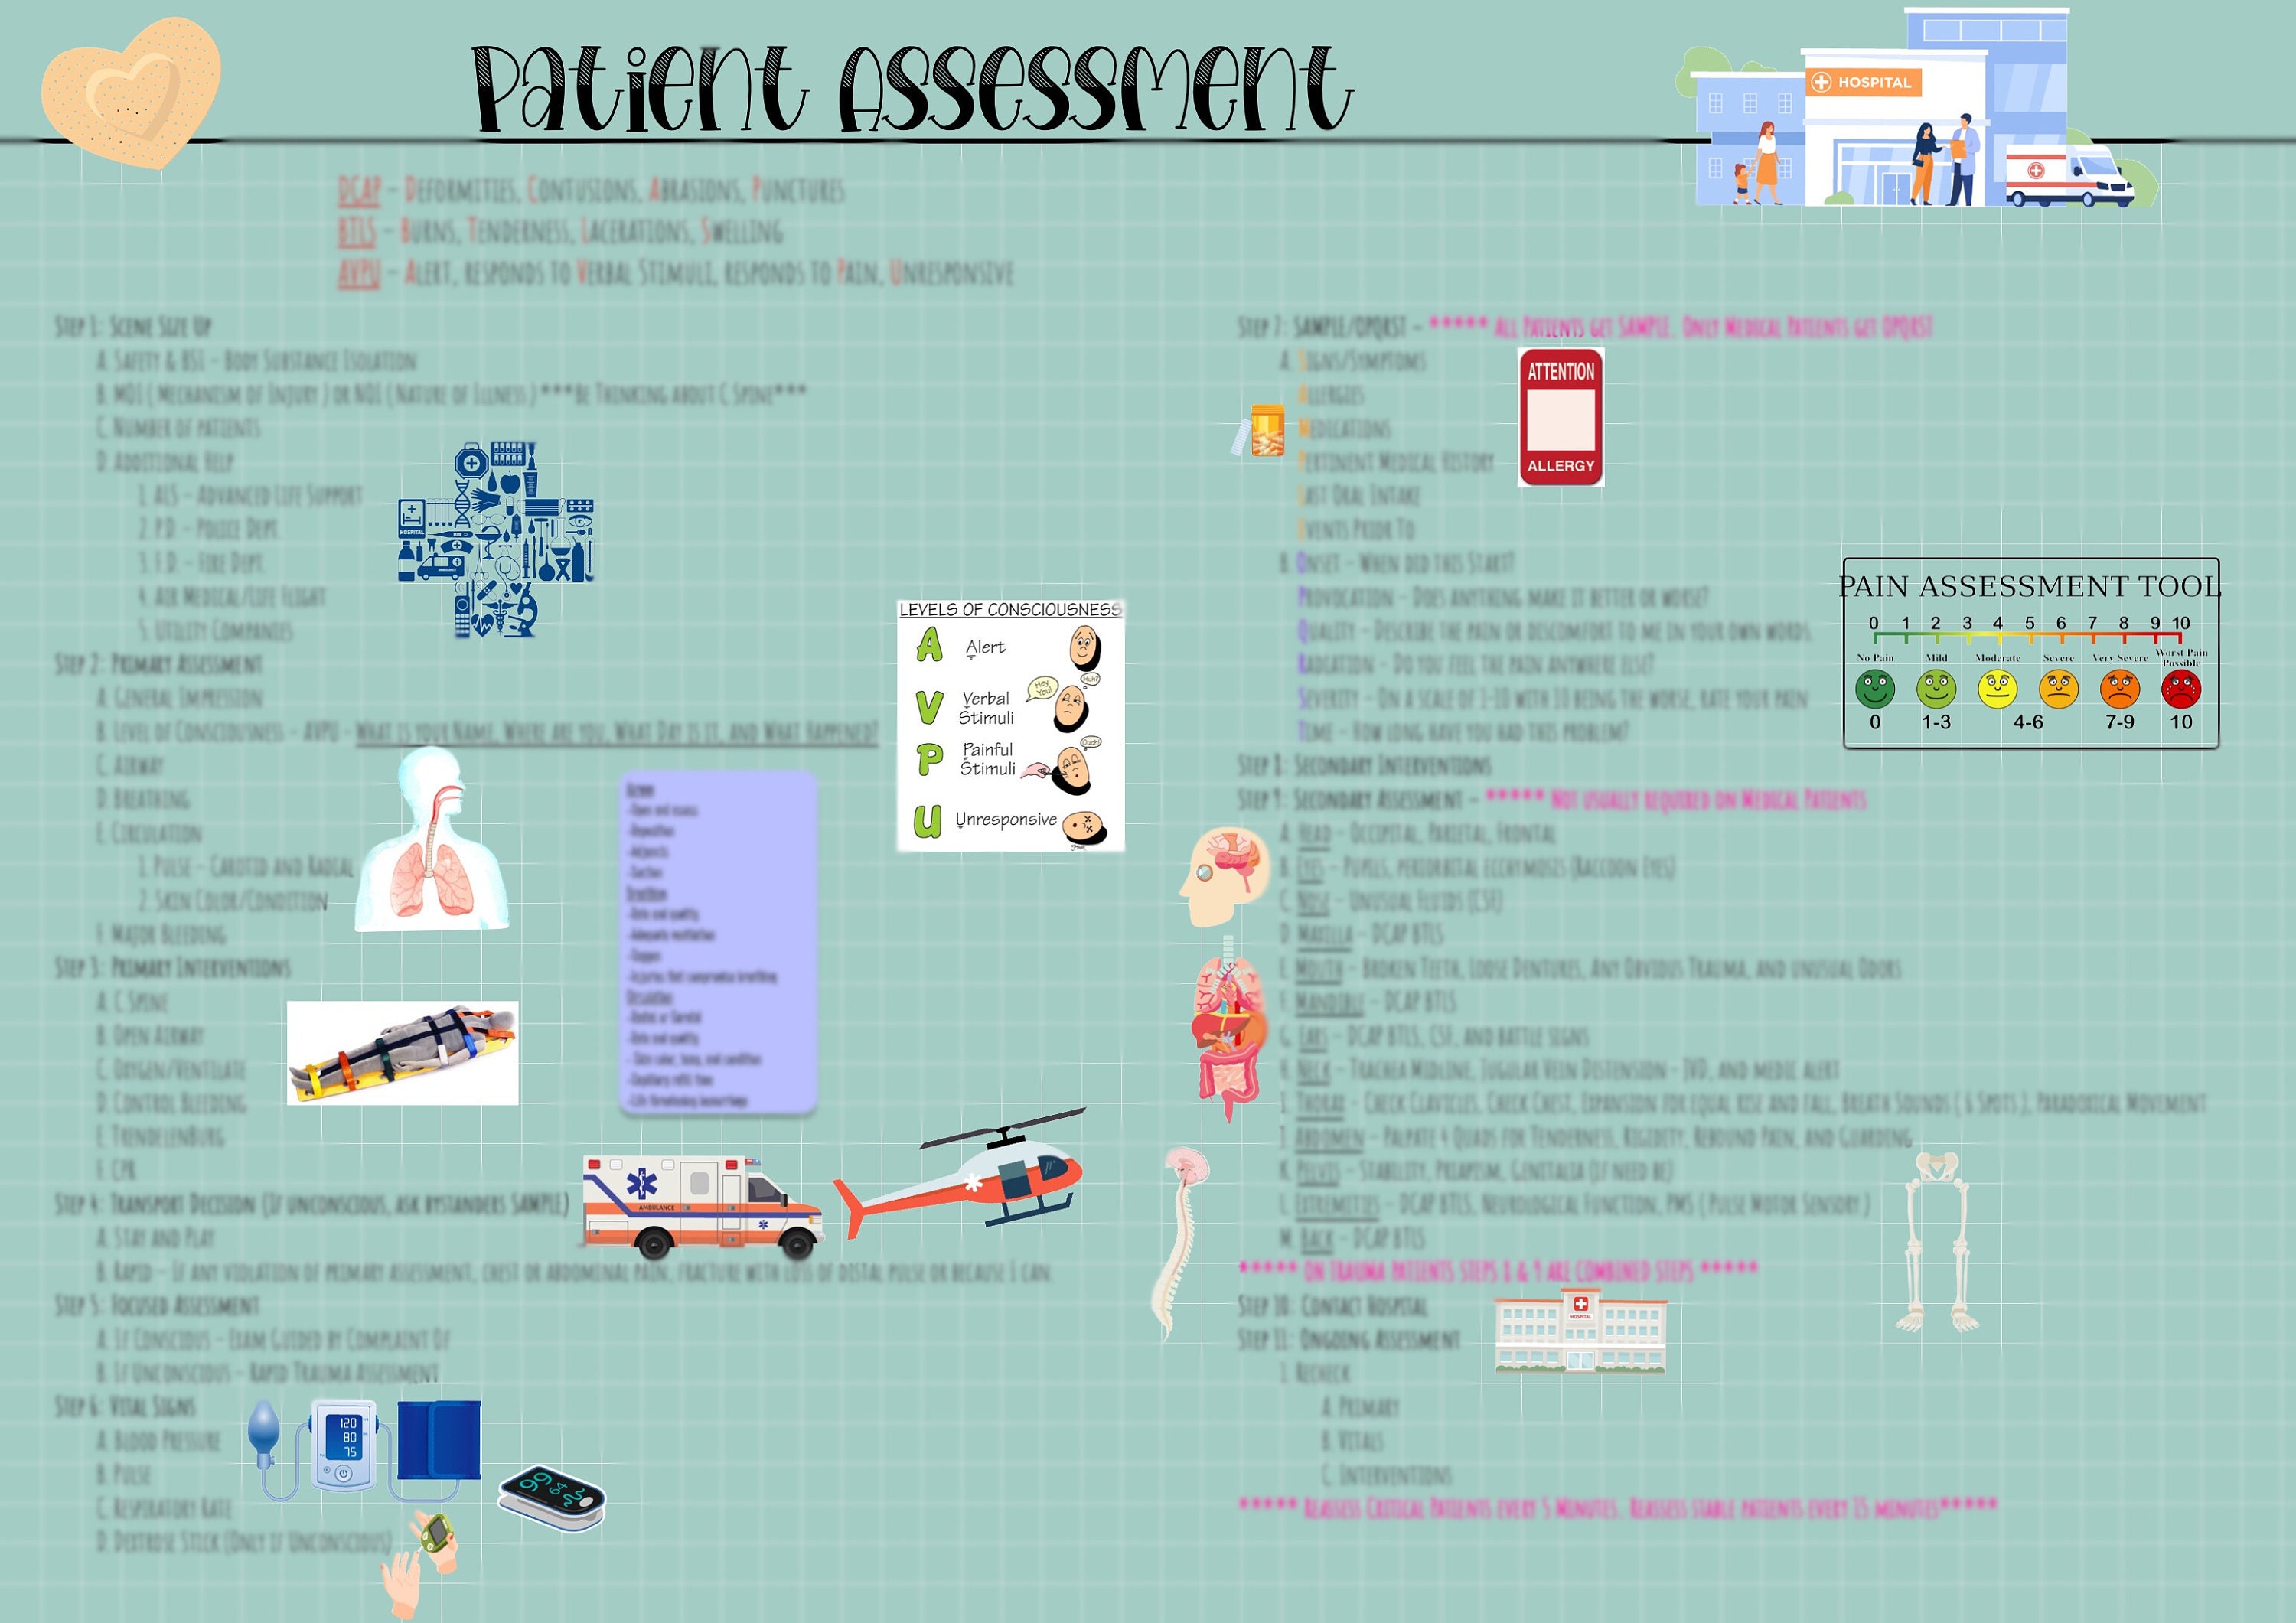
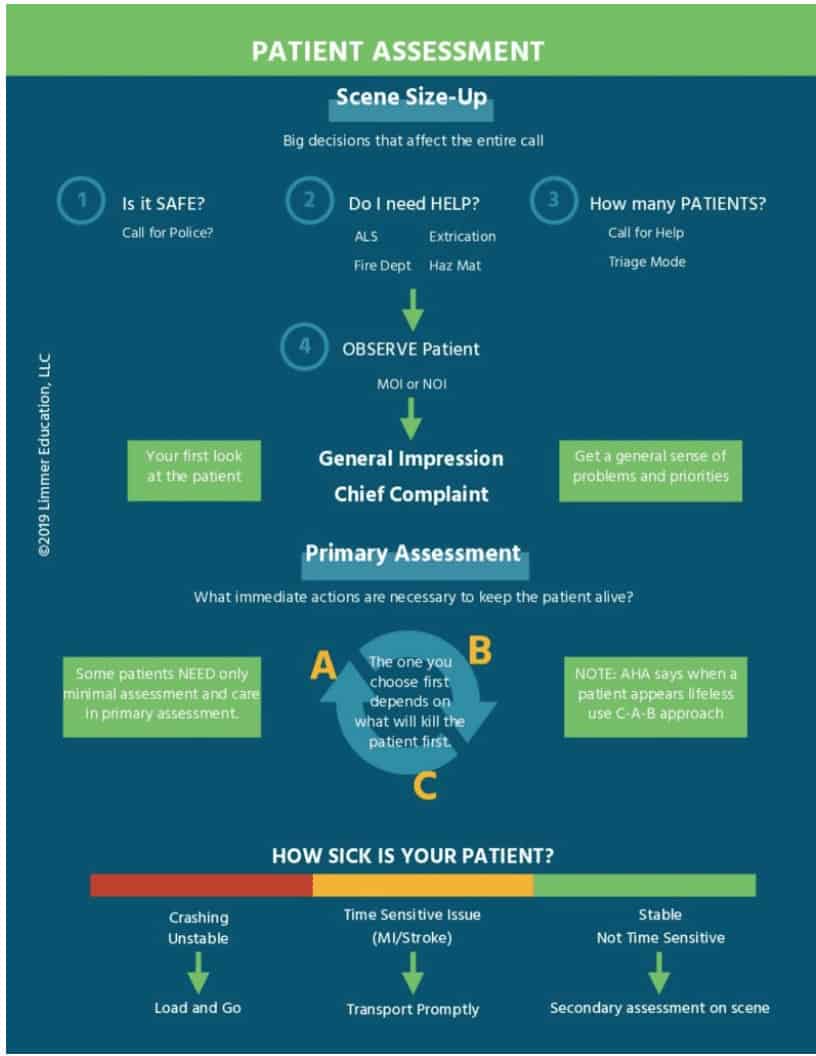
Most EMT programs teach you to run through the assessment like a checklist. Learn the order, memorize the steps, pass the test. The problem is that real calls don't care about your checklist. I learned this the hard way during my second year on the job, responding to a call for a diabetic patient who was listed as confused. Standard assessment would have you focus on blood glucose and airway. What I found was a patient with a partially dislodged trach who was barely moving air. Glucose was fine. If I had stayed on the script, I would have loaded and gone. Instead, I recognized the stridor early and stabilized the airway on scene. That assessment took eight minutes instead of thirty, and it was the only reason this patient made it out alive. The core of every medical patient assessment breaks down into three phases, though they overlap more than textbooks make them look. Primary assessment establishes immediate life threats and determines transport priority. Secondary assessment is the detailed head-to-toe and sample history. Ongoing reassessment is where most people lose focus because they think they are done after the secondary exam. It is not done until you hand off to the receiving facility. For the primary assessment, start with your general impression and level of consciousness. Use AVPU or Glasgow Coma Scale depending on what your protocol requires and what tools you actually carry. I have seen too many medics fumble with a penlight and reflex hammer when the patient is clearly unresponsive. Sometimes you just need to apply a sternal rub and move forward. Time matters here. Your initial impression should take under two minutes unless the scene is chaotic, which it often is.
Vital signs form the backbone of the secondary assessment. Blood pressure, pulse, respirations, oxygen saturation, skin condition, and blood glucose. That is six data points. Take them fast but do not rush the glucose check. I worked a call with an elderly female presenting with chest pain. Her glucose was 42. She also had cardiac symptoms. Treating only the heart without correcting the sugar first would have been a mistake. The hypoglycemia was masking and contributing to the overall picture. I gave D50 and then reassessed cardiac symptoms. They improved noticeably once the metabolic issue was addressed.
Common Mistakes That Cost Time and Clarity
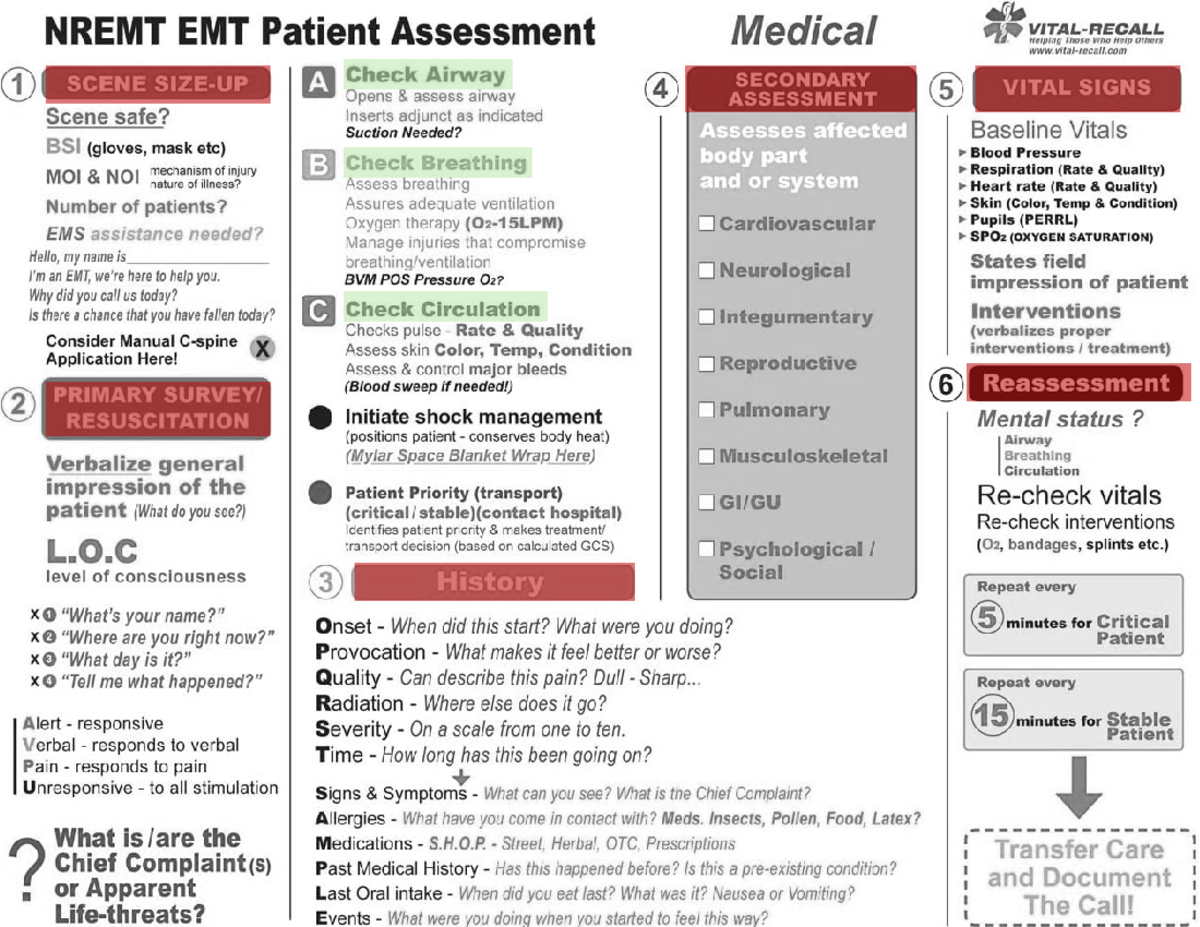
Beginners tend to document everything and understand nothing. You will write down a dozen normal findings and miss the one abnormal thing that matters. Focus on what deviates from baseline and why. A headache in a migraine patient is not useful to document. A headache in a hypertensive emergency patient with a blood pressure of 220 over 130 is the finding that drives your entire treatment plan. Another pitfall is skipping the SAMPLE history because you are impatient. SAMPLE stands for Signs and Symptoms, Allergies, Medications, Past medical history, Last oral intake, and Events leading up to the illness. It takes forty-five seconds if you do not treat it like an interrogation. I once missed a medication allergy because I asked about medications broadly instead of reading the actual pill bottles. The patient had been prescribed a new antibiotic the week before and had not mentioned it. The rash appeared twenty minutes after we administered morphine for pain. Not directly related to the morphine, but the delay in identifying the allergy cost us valuable time and changed our approach. Reading the bottles solved the problem on the next call and every call after that. Chief complaint drives everything. Do not let a distracting secondary problem pull your attention away from the primary reason the patient called. I handled a call where the chief complaint was shortness of breath but the patient kept complaining about a sprained ankle. The ankle injury was from a fall caused by the hypoxia. Treating the ankle first would have been backwards. Identify the root cause, manage the ABCs, then circle back to the associated injuries.
Get the Full Details
Reassessment Is Where Good EMTs Separate From Average Ones
Reassessment intervals depend on patient acuity. Unstable patients need reassessment every five minutes. Stable patients every fifteen minutes. This is standard, but the real skill is knowing what to compare each time. Are the vital signs trending in the right direction or the wrong one? Is the mental status improving or declining? Is the treatment you are giving having the expected effect? I ran a call with a septic patient whose blood pressure was dropping despite fluid resuscitation. On paper, the initial assessment looked manageable. But the ongoing reassessment showed a trend that did not match our interventions. Blood pressure went from 98 over 62 to 88 over 54 to 79 over 51 over twenty minutes. That trend forced a change in strategy. We escalated care, notified medical control earlier than we normally would, and prepared for a more aggressive transport plan. Trending matters more than any single number.
When Your Assessment Falls Short
There are situations where a standard Medical Patient Assessment Emt approach simply does not work well enough. Language barriers are a major limitation. Without an interpreter or translation tool, you are guessing at history and symptoms. I have used phone interpreter services on scene, but they take time you often do not have. A practical workaround is carrying a multilingual symptom card or using a translation app that works offline. Keep it simple. Common phrases in the top three languages spoken in your service area will cover most calls. Another limitation is pediatric assessments when the child is uncooperative or nonverbal. You cannot rely on history here. You have to read the body. Look at work of breathing, skin color, capillary refill, and behavior. A child who is quietly lying still is often more concerning than a crying child. I responded to a call for a two-year-old with fever. The parents said the child was just sleepy. Sleepy for this child meant lethargic and difficult to rouse. The assessment findings pointed toward meningitis, not a simple viral fever. We transported immediately and the diagnosis was confirmed at the hospital. Trust your eyes when the history is unreliable. Mass casualty incidents disrupt the normal assessment flow. You cannot do a full secondary assessment on every patient. Triage tags and START triage take priority. The assessment becomes rapid and gross. If the patient is breathing, has a pulse, and can follow simple commands, they are likely delayed rather than immediate. This is not ideal assessment, but it is the reality of the situation.
Practical Tools That Actually Help
A small notebook or voice memo app for scene documentation saves time compared to trying to write everything down on a cramped PCR form while the ambulance is moving. I record key findings verbally right after the assessment and fill out the paperwork properly at the station. It cuts documentation errors significantly and keeps my attention on the patient during transport. Your stethoscope, blood pressure cuff, and pulse oximeter should be checked and calibrated regularly. I once had a pulse ox that read ten points higher than the actual saturation because the sensor was failing. It took three calls before I noticed the discrepancy when comparing it to arterial blood gas results at the hospital. Test your gear before every shift. It takes thirty seconds and prevents embarrassing moments. Documentation should capture your clinical reasoning, not just your findings. Write down why you chose a certain intervention or why you changed your treatment plan. A receiving nurse or physician reading your PCR needs to understand your thought process. This protects you legally and improves continuity of care. It also helps you review your own performance later when studying for certifications or preparing for skill checks.
The assessment is a tool, not a ritual. Learn the framework thoroughly so it becomes automatic, but stay flexible enough to adapt when reality diverges from the textbook. The patients you serve will not thank you for checking boxes. They will benefit from the moments you notice what everyone else missed.