How We Actually Handle Patient Assessment Scenarios at Triage
Patient assessment scenarios are basically structured decision trees that run alongside your clinical judgment during admission and triage. They cover everything from chief complaint intake through discharge planning, and they exist so you're not making the same call from scratch every single time. The tool itself is just a framework — what matters is whether your team actually uses it or just fills it out as paperwork. I spend most of my day working through these scenarios with staff nurses and residents who are either too tired or too rushed to think through the whole pathway. Here's how it works in practice. You start with the chief complaint, map out the differential in real time, then layer in vitals and history before committing to any diagnostic order. The scenario format keeps you from skipping ahead and ordering the CT scan before you've actually listened to the lungs. The structure usually goes like this. Presenting symptom gets you into a branching path. Vital signs narrow it down. History and medications add constraints. Labs and imaging come last unless the patient is unstable, in which case you parallelize testing while you treat. I've seen people miss pulmonary embolism because they stayed too long in the pneumonia branch and never considered that the pleuritic pain with normal O2 saturation could still be a PE. That happens when you stop updating the differential instead of continuing to refine it.
One specific case that sticks with me involved a 63-year-old female presenting with fatigue and mild confusion. The scenario routing put her squarely in the UTI-sepsis pathway based on urinalysis showing leukocyte esterase. We started antibiotics and fluids. She got worse. Two days later I went back through the assessment tree and realized we'd never actually run a toxicology screen or check ammonia level. Turns out she had hyperammonemic encephalopathy from an undiagnosed urea cycle issue — the UTI was incidental. The workaround I used was to force a mandatory second-differential review at the 48-hour mark if the patient isn't improving on the initial treatment plan. Nobody likes doing it. It adds about eight minutes to the workflow. It caught that case and probably a dozen others before they deteriorated further.
The Mechanics of Running a Scenario Properly
Most hospitals use electronic health record modules that trigger scenario pathways based on ICD-10 codes or triage categories. The problem is the system assumes you'll engage with it. A lot of times you click through because the documentation requirement demands it, and the scenario becomes a checkbox exercise rather than a thinking tool. That defeats the whole purpose. Here's what I've found that actually works. Before you open any scenario template, write down your top three differential diagnoses on a scrap of paper or in the notes field. Not the system's defaults — yours. Then run through the scenario and check whether each branch acknowledges or contradicts your initial thinking. If the system pushes you toward a diagnosis that doesn't fit your patient, stop and explain why in the documentation. That friction is where learning happens. The scenario isn't there to tell you what to think. It's there to make sure you thought about something you might have missed. Documentation is another area where people go wrong. You need to capture your clinical reasoning, not just the outcomes. So instead of writing "assessed per scenario — no concerns," you write "rule out pulmonary embolism given pleuritic pain and recent surgery; Wells score 3.5; CTPA ordered." That tells someone reviewing the chart that a judgment was made and why. It also protects you legally, which is not a bad thing to factor in.
Get the Full Details
Pitfalls That Break the Whole Process
There are three common failure modes I see constantly. The first is anchoring bias. Once the scenario routes you to a diagnosis, staff stops looking for alternatives. This is especially dangerous in emergency departments where time pressure is already high. The second is scenario fatigue. When you've done 14 patient assessments in a row, the later ones get rushed through mechanically. You catch errors, but you miss the subtle ones. The third is poor integration between the scenario tool and the actual order set. If the scenario says to order a D-dimer but clicking through still requires five separate orders, people skip it. The path of least resistance wins every time. Another issue nobody talks about is the variation in scenario quality across different EHR platforms. Some pathways are built by clinicians who actually work in the environment they're modeling. Others are built by people who've never touched a patient. I've seen a sepsis scenario that triggered on a temperature of 37.8 degrees Celsius. That's borderline normal. It flagged nearly every post-op patient as septic and desensitized the entire unit to the alert. We ended up disabling that particular branch and writing a local protocol instead.
When Scenarios Don't Work
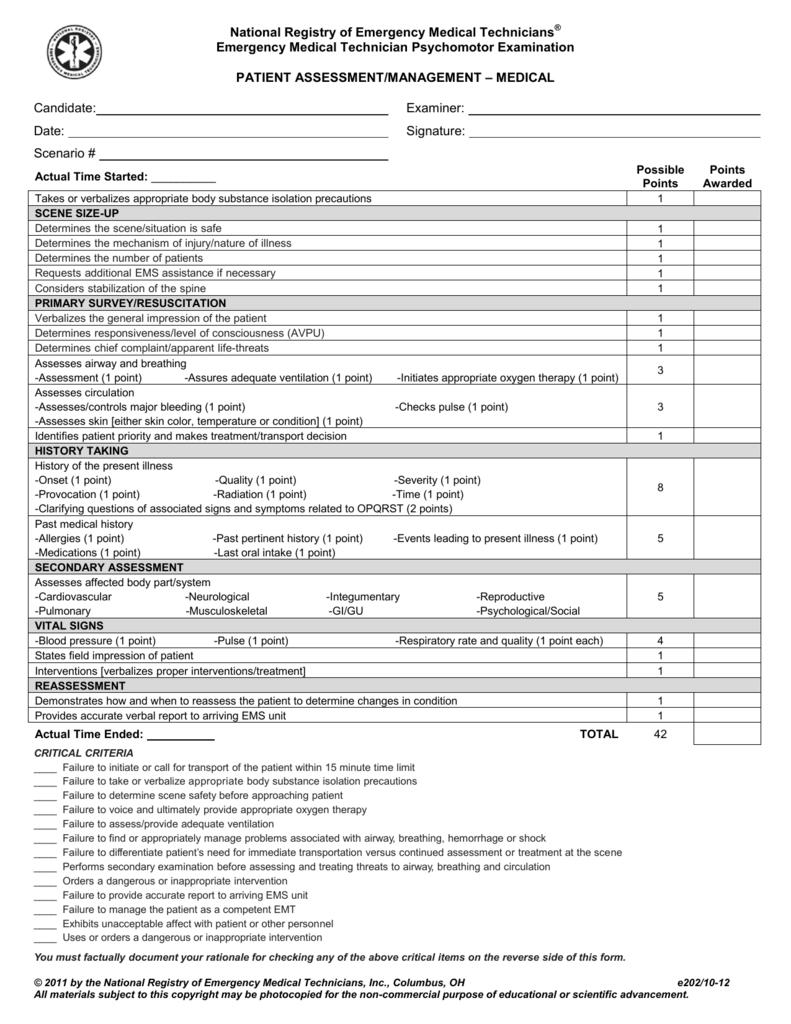
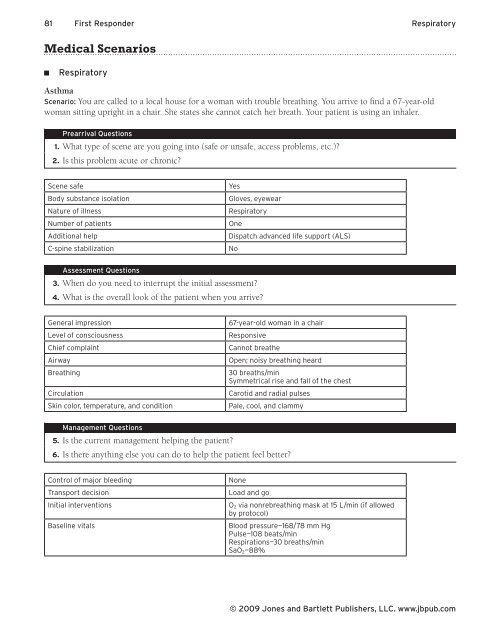
Medical Patient Assessment Scenarios are not a substitute for clinical judgment. They're especially weak with patients who have multiple chronic conditions, atypical presentations, or social complexity that affects their care. An elderly patient with heart failure, diabetes, and early dementia who presents with vague complaints doesn't fit neatly into any standard pathway. The scenario will push you toward common diagnoses and miss the uncommon ones that affect this population most. For complex multimorbid patients, I recommend using the scenario as a starting point rather than a guide. Run through it quickly to catch the obvious misses, then deliberately step outside the framework. Do a full head-to-toe assessment anyway. Talk to the patient about what they're actually experiencing rather than what the symptom checklist suggests. Involve case management early. These patients are the ones who fall through the cracks when everyone is checking boxes instead of watching the person. If you want a downloadable version of a basic scenario workflow, most hospital systems will pull one from your EHR's clinical decision support module. Third-party resources exist too, but they tend to be generic and not updated frequently enough to reflect current guidelines. I'd rather recommend something simpler: build your own one-page quick-reference based on the scenarios your unit uses most often. List the top ten chief complaints, the key decision points in each, and the red flags that should make you abandon the standard pathway. Laminate it. Keep it at the nurses' station. It'll be more useful than any software update your IT department rolls out next quarter.