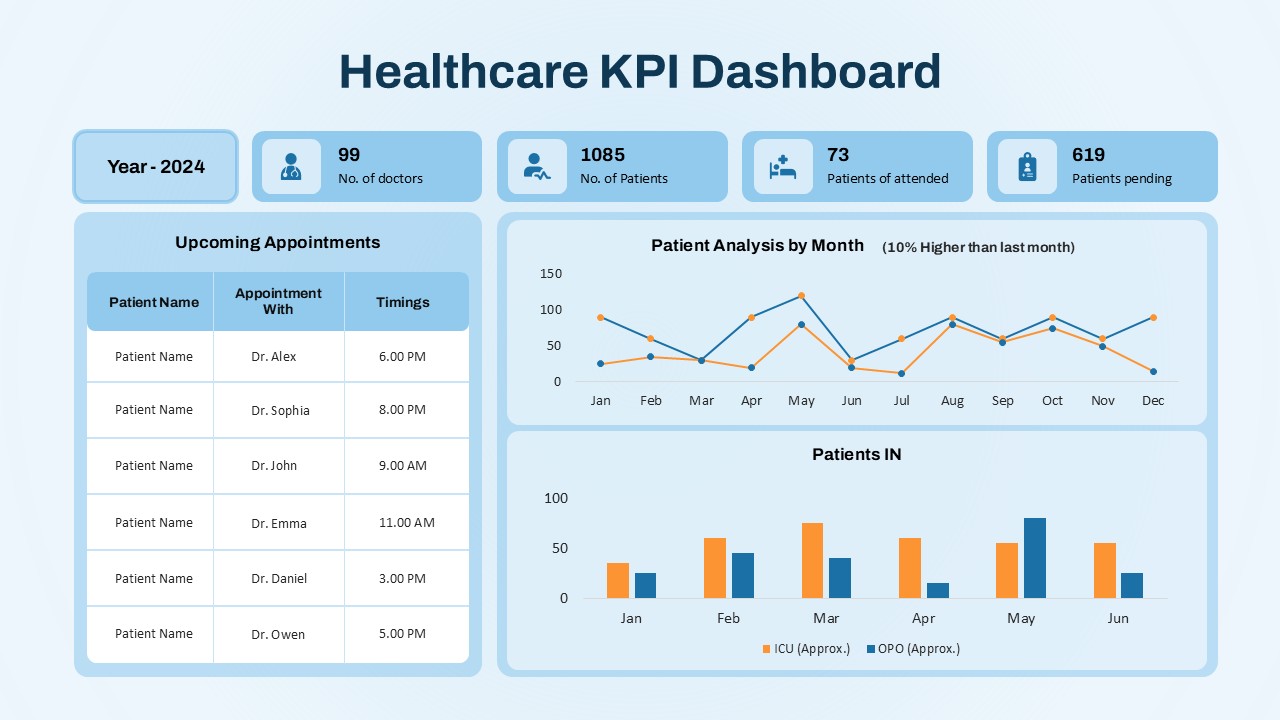
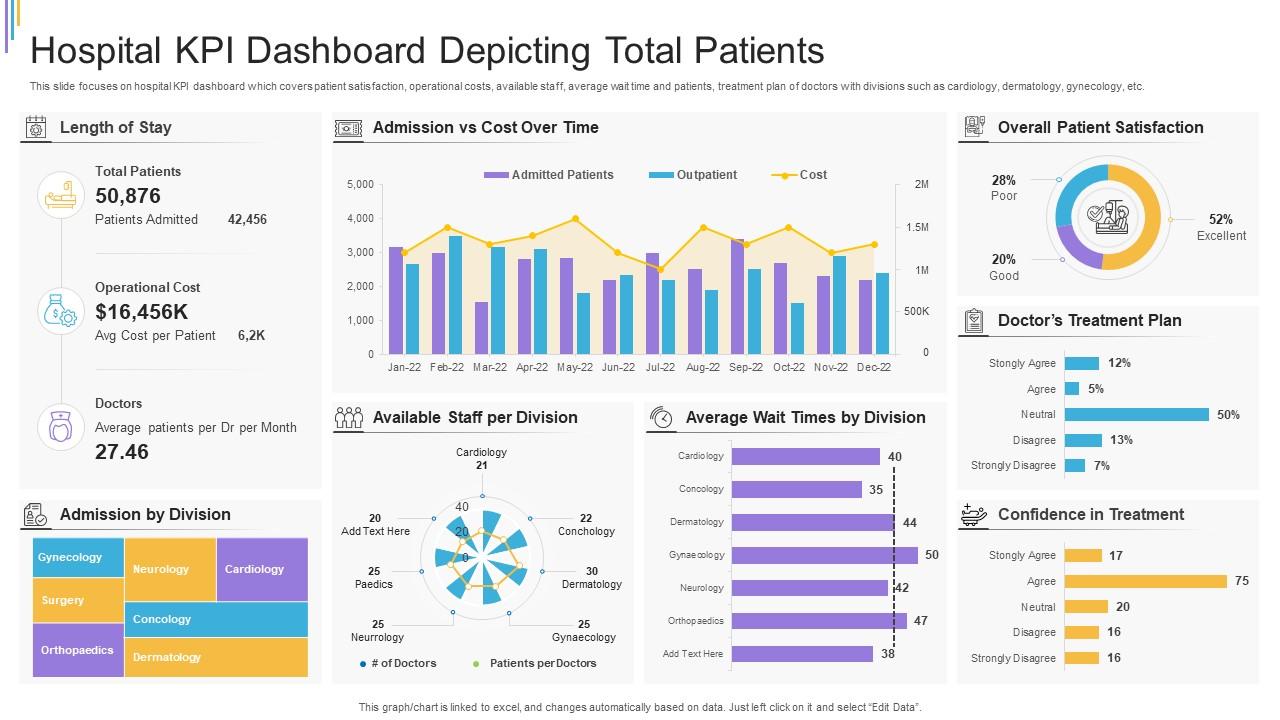
What Actually Shows Up on a Medical Practice Kpi Dashboard
A Medical Practice Kpi Dashboard is just a collection of metrics pulled from your EHR and billing system, arranged so you can answer a few operational questions without opening ten different reports. The ones that matter are revenue per provider, denial rate by payer, patient no-show percentage, average days in A/R, and net collection rate versus gross collection rate. Everything else is decoration unless someone is actually changing their behavior based on it. I built three of these over eight years across two clinics. The second one failed because I fed it every metric someone had ever requested, and by quarter two nobody looked at it. The third one works because I limited it to twelve numbers and tied each one to a specific person's weekly responsibility. That's the part nobody talks about: the dashboard is useless unless ownership is unambiguous. Here's how I actually do it now, step by step, after spending way too long doing it wrong.
Step one: decide what decisions the dashboard enables. Not what looks good. What changes. If you're not making a staffing call, a billing call, or a provider productivity call based on a number on that screen, remove it. We keep twelve. Twelve is the max before it becomes a billboard instead of a tool. Step two: map each metric to its data source. Every number needs a single source of truth. If your collection rate comes from one report in Epic and your A/R comes from a separate export in your billing software, those two numbers will disagree, and you'll waste two hours every month figuring out which one is wrong. I connect directly to the EHR for clinical throughput and to the practice management system for financials. When a metric requires both, I build it in a staging table, not in the dashboard itself. Step three: define the calculation before you build it. This is where most people mess up. "Net collection rate" alone is ambiguous. Is it collections divided by charges? Collections divided by adjustments plus charges? The standard definition I use is total payments received during the period divided by total billed charges minus adjustments for that same period. Write it down. If a new analyst can't replicate your number from that sentence, rewrite the sentence.
Step four: set refresh frequency by metric type. Financial metrics refresh daily. Clinical volume metrics can be weekly. Patient satisfaction scores are monthly. Don't give everything a real-time badge. It trains people to expect instant data that doesn't exist, and they'll second-guess any number that lags by a day. Step five: assign an owner per metric. One name. Not "billing team." Not "administrators." A person. If it breaks, you email that person. If it's ambiguous, it won't get fixed. I ran into a specific problem last year with a no-show tracking metric. Our EHR flagged a cancellation as a no-show if the patient didn't arrive within thirty minutes of the appointment time. But our scheduling system was recording walk-in overrides as no-shows too, which inflated the rate by about eight percentage points. The workaround was straightforward but took a weekend to implement: I added a flag in the data layer that excluded any record where the visit type code indicated a same-day override. Once that filter was in place, the metric dropped back to the actual 11 percent range. That difference changed how we staffed the afternoon block, so it wasn't just a cosmetic fix.
Get the Full Details

The Metrics That Actually Move the Needle
Gross collection rate. Net collection rate. Days in A/R. Denial rate. No-show rate. Schedule fill rate. Revenue per productive work unit. Patient acquisition cost. Provider utilization rate. Average handle time for calls. First contact resolution rate. These are the ones I've seen repeatedly prove their value. The rest are noise. Revenue per productive work unit is the metric most people misunderstand. It's not total revenue divided by total providers. It's revenue divided by RVUs or clinical contact hours, depending on whether you're in a procedural or non-procedural practice. If you use total headcount instead of productive FTEs, you'll hide the fact that two of your six providers are carrying half the load. I learned that the hard way when a partner asked why we were losing money despite record collection rates. The revenue was there. It was concentrated on three people. Days in A/R looks simple but has two versions that mean completely different things. Clean claims A/R days excludes rework and resubmissions. Total A/R days includes them. If you only report clean claims, you're lying to yourself about how long it actually takes to get paid. I report both, and the gap between them tells me whether our denial problem is a documentation issue or a front-end registration issue.
Tools and Build Options
You can buy a packaged Medical Practice Kpi Dashboard solution from vendors like MatrixCare, Waystar, or ModMed. Those work fine if your practice is already in their ecosystem. The problem is lock-in and customization limits. You get what they decided is important, not what you decided is important. Building it yourself in Power BI or Tableau gives you control but requires about forty hours of setup for a basic version and ongoing maintenance. I estimate that most practices will spend more time maintaining a custom build than they save in the first year. That changes after year two if you have the internal skill to support it. The middle ground is using an EHR-embedded dashboard with custom calculations layered on top. Epic has its own reporting workbench. Cerner offers PointClickChart analytics for post-acute but not acute settings. If your EHR has a reporting module, start there before outsourcing anything. I've seen practices skip this step and immediately subscribe to a third-party analytics platform that duplicatively costs $800 to $2,000 a month on top of their EHR contract.
For a downloadable template, I keep a basic Excel-based framework that maps metric definitions to source fields in Epic, Cerner, and Athenahealth. It's not a product. It's a starting point. I can share it if you need the field mappings rather than building from scratch.
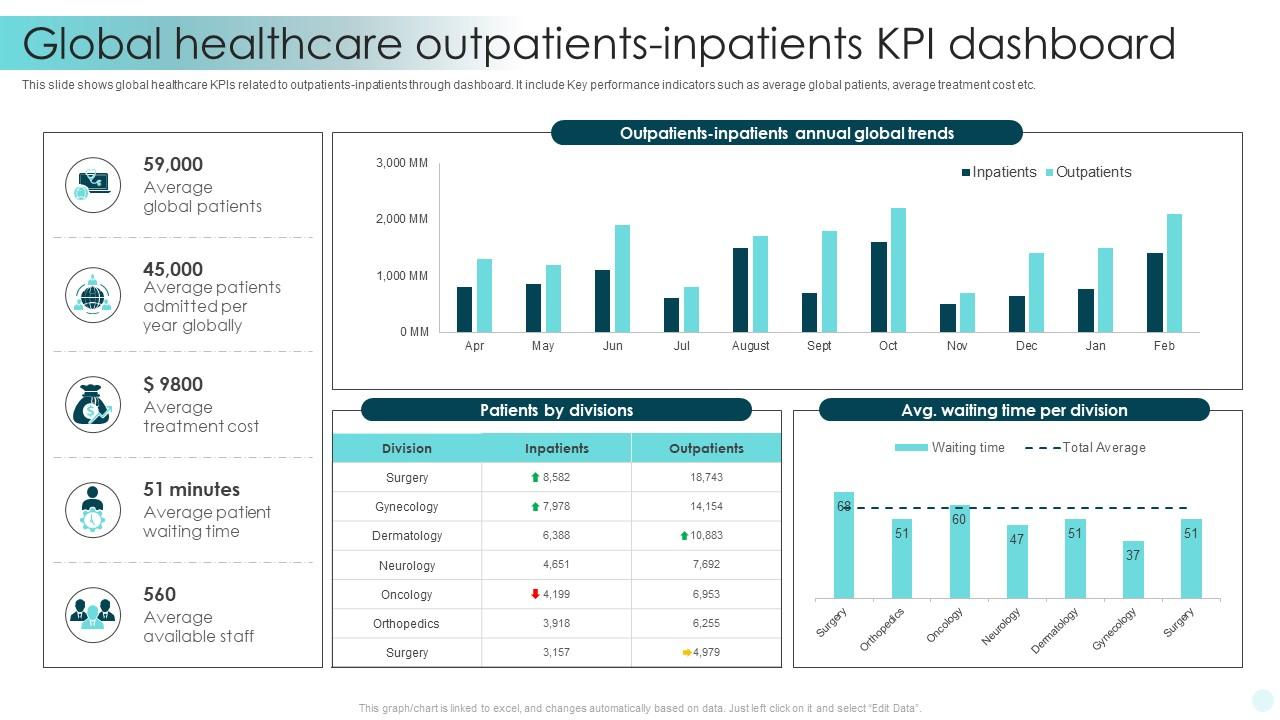
Where These Dashboards Completely Fail
Small practices. I'm talking under fifteen providers. The overhead of maintaining data pipelines, refreshing schedules, and policing metric definitions often exceeds the value the dashboard provides. For those setups, a weekly one-page summary generated by your billing company is faster and equally accurate. The dashboard model assumes you have someone who can interpret the data and act on it. If that person is the practice manager wearing five other hats, the dashboard becomes a background process that consumes time and produces nothing. Specialty practices with mixed payment models also struggle. A dermatology clinic doing both fee-for-service and high-deductible commercial plans will see distorted metrics if you don't separate payer types. Gross collection rate will look fine while net collection rate is actually deteriorating because patients are ignoring bills they don't understand. The dashboard will show green across the board until someone checks the patient financial responsibility line item separately. Another failure mode is volume-based dashboarding. If your primary use case is tracking patient volume trends for market analysis rather than operational management, stop building a Medical Practice Kpi Dashboard and build a reporting library instead. Dashboards push active monitoring. Reporting libraries serve periodic deep dives. Mixing the two creates confusion about whether a number needs attention or just documentation.
A Few Things I Wish Someone Had Told Me Earlier
Color coding is mostly performative. Green and red tell you nothing without defined thresholds. I switched from conditional formatting to explicit target lines on every chart. It looks uglier and actually works. Trend lines beat absolute numbers. A denial rate of 7 percent means nothing without knowing it was 4 percent three months ago. Show the direction. Show the slope. Remove one metric every quarter. Force it. If it survived six months without anyone asking about it, it's not driving a decision. Take it out. This keeps the dashboard honest and prevents drift toward that billboard problem I mentioned earlier.
The hardest part isn't building the dashboard. It's getting clinical leadership to agree on what success looks like before you write a single query. Once that happened in my third attempt, everything downstream became mechanical. Before that, I was optimizing for vanity, not operations.