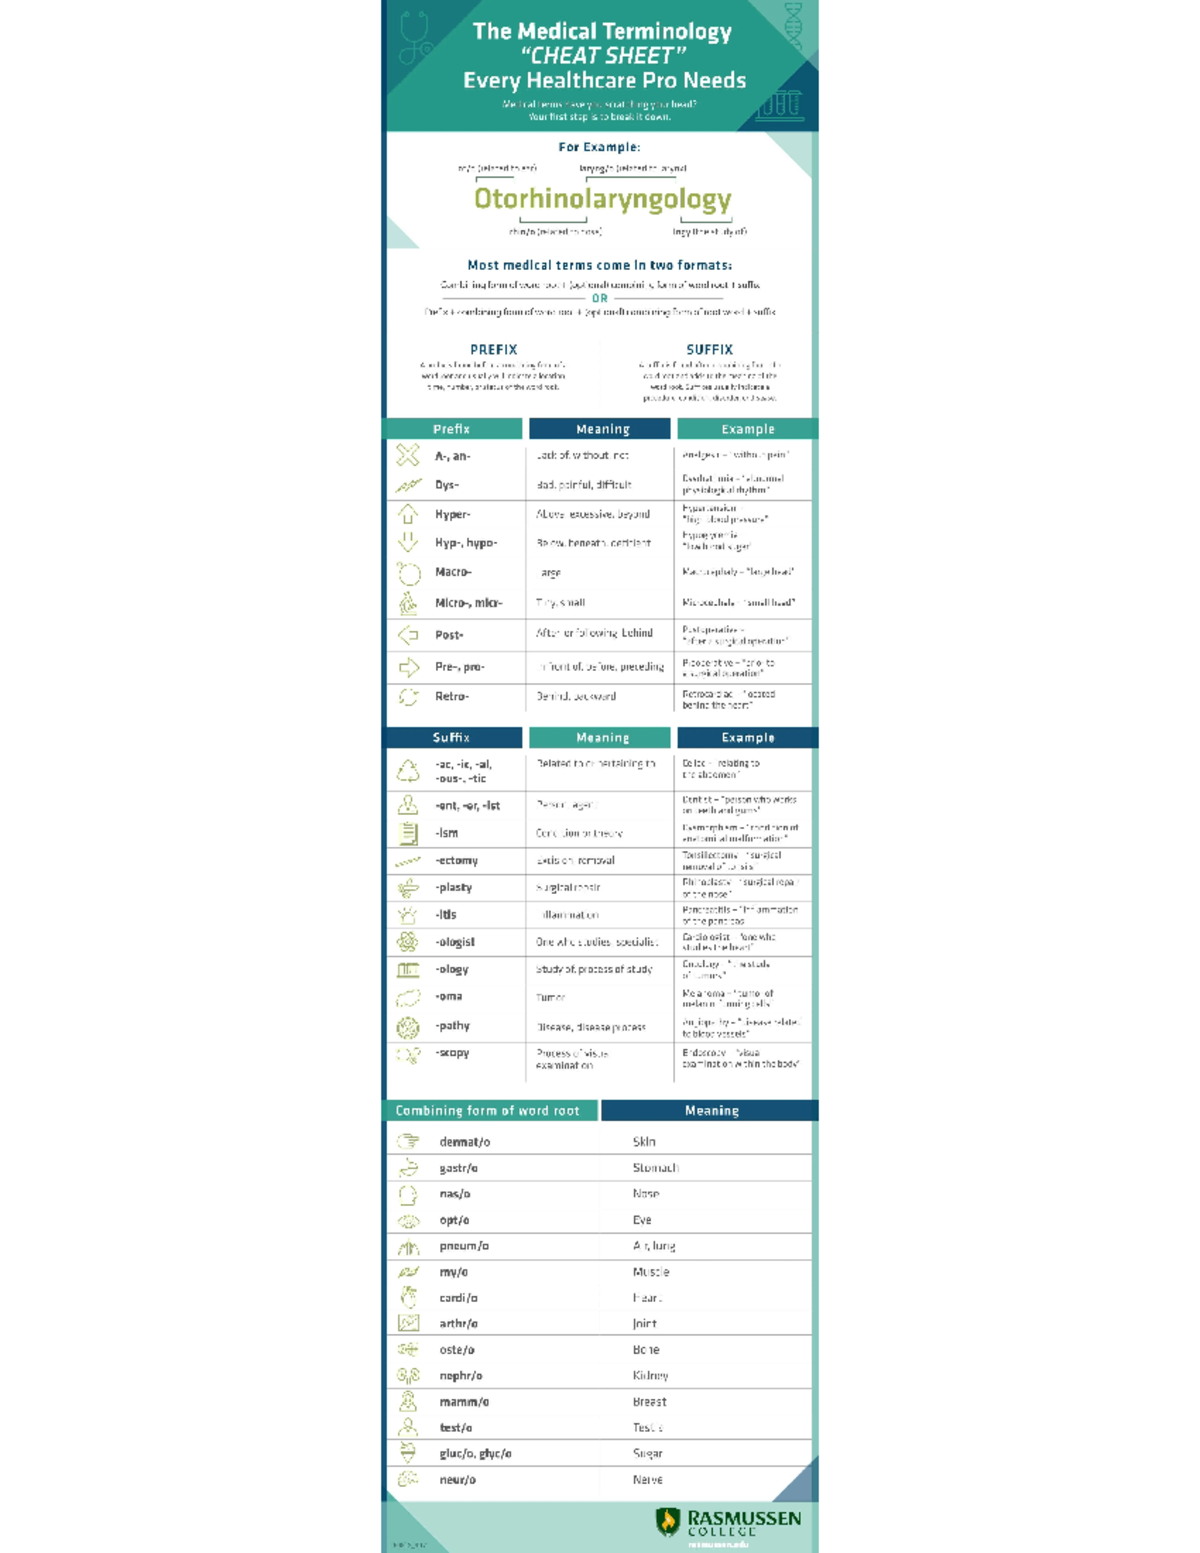
Building a Medical Scribe Cheat Sheet That Actually Works
I spent three years as an in-person scribe before moving to tele-scribing, and the cheat sheet was the only thing that kept me from burning out. A lot of people treat it as an afterthought — they grab whatever template their employer provides and leave it at that. That's how you miss things. Your cheat sheet needs to be the first thing you update every single day you work. A medical scribe cheat sheet is essentially your personal reference document for real-time clinical documentation. It contains the abbreviations, drug names, ICD-10 codes, CPT codes, common phrase templates, and workflow shortcuts that you reference constantly during patient encounters. The difference between a good one and a bad one shows up in your typing speed, your error rate, and how much you have to ask the physician to repeat themselves.
What Goes on the Sheet
Start with the things you find yourself looking up repeatedly. In my first month at a cardiology practice, I realized I was spending about forty-five seconds per encounter just looking up the standard post-MI medication regimen because everyone had a slightly different combination. I wrote it all out — aspirin dosing, statin protocols, beta-blocker naming conventions, ACE inhibitors versus ARBs with the standard drug names. Once that was on my sheet, I stopped second-guessing myself. That one section alone cut my post-encounter chart review time from about ten minutes down to roughly three. You need standard abbreviation lists. But here's the thing most people get wrong — don't copy the official list verbatim. Build your own. Some physicians will say "Hgb" and mean grams per deciliter. Others will use "Hb" interchangeably. Create a section that maps the variations you actually encounter so you're not flipping back and forth between sources mid-encounter. Drug references should include both brand and generic names, standard dosing ranges for common medications, and any abbreviations specific to that practice. A patient presenting with hypertension in an internal medicine clinic is getting a completely different medication conversation than one in a cardiology office, even though the ICD-10 codes overlap.
My Experience With a Problem I Never Expected
About eight months in, I hit a wall with a particularly challenging specialty — orthopedics. The problem wasn't the documentation itself. It was the procedural shorthand. The surgeons would describe a procedure as "L knee arthrotomy with meniscectomy and chondroplasty at 4 and 6 o'clock" and I'd have the terms individually in my head but couldn't assemble the standardized phrase quickly enough. My notes lagged behind by two or three minutes, which meant the physician had to wait for me to catch up before signing off, which created visible frustration in the room. The workaround was brutal but simple. I asked the attending surgeon if I could sit in on a procedure list review before clinic started each day. Thirty minutes of walking through the scheduled cases with him, learning the exact phrasing he preferred for each procedure type. I then built a separate subsection on my cheat sheet called "Surgical Language" that captured his preferred phrasing for every procedure in his rotation. It took two weeks to build, but after that my note lag dropped to under thirty seconds per encounter. The key insight was that a cheat sheet isn't just reference material — it's also a place to capture the individual preferences of the people you work with.
Get the Full Details

Organizing for Speed
Most scribes use Google Docs or Microsoft Word for their cheat sheets. I used a structured doc with hyperlinked sections. When you're mid-encounter and need to look up a CPT code for a joint injection, you shouldn't be scrolling. Hyperlinks from a table of contents to each section saved me maybe five seconds per lookup, which adds up over a hundred encounters a day. Number one priority section: Chief Complaint and HPI templates. These are the boilerplate phrases you use repeatedly. "Patient presents for evaluation of..." followed by condition-specific modifiers. "Denies chest pain, palpitations, syncope, orthopnea, PND." Learning these by heart is good. Having them typed out and searchable is faster. ICD-10 codes should be organized by specialty, not alphabetically. When you're documenting a diabetic patient with peripheral neuropathy, you need to pull the combination code quickly. If it's buried under "D" for diabetes instead of right next to "E" for neuropathy-related codes, you lose time you don't have.
Counter-Intuitive Things I Learned
One thing that surprised me: the cheat sheet should actively discourage certain shortcuts. I saw another scribe use an abbreviation for "left" that looked identical to "LI" (liver) when handwritten in the notes, which created confusion during provider sign-off. I started flagging ambiguous abbreviations on my own sheet with a notation like "Do NOT use this shorthand — provider rejected it last week." That kind of practical warning is worth more than any standardized abbreviation list. Another thing: don't include everything. I once had a coworker whose cheat sheet was twelve pages long. Twelve pages. She'd spend more time searching her document than the physician would spend telling you what to document. Your cheat sheet should fit on one screen if possible, with the most frequently referenced items on the first page. If something doesn't appear at least twice a week, move it to a secondary reference document.
Downsides You Should Know About
A cheat sheet has real limitations. It only helps with structured, predictable encounters. When a patient comes in with a complex presenting complaint that doesn't fit any of your templates, you're still flying blind. I had one encounter where a patient presented with symptoms spanning three organ systems and the physician was documenting a workup for something I'd never seen in my months of scribing. My cheat sheet was useless for that encounter. The workaround was simple — stop trying to use it and just listen. Take the notes raw, then fill in codes and standardized language after the encounter. The medical scribe cheat sheet is a tool for efficiency, not a crutch for situations where you need to actually pay attention. There's also a compliance issue you need to be aware of. Some facilities don't allow personal reference documents at the workstation. If you're working in a hospital setting, check with your coding department about what's permitted. I've seen scribes shut down for having unauthorized cheat sheets at the terminal. It happens more often than you'd think.

How to Build Yours
Create a new document and start with the four sections I mentioned above: abbreviation mappings, drug references, ICD-10 codes by specialty, and HPI/chief complaint templates. Fill in what you know from training. Then track every lookup you make for a full week. At the end of that week, the items you looked up most frequently belong at the top of your document. Everything else moves down or gets moved to your secondary reference file. Update it weekly. Add the abbreviations new physicians introduce. Remove the ones that caused confusion. The document should be living and changing, not a static artifact you create once and forget about. That's the difference between a reference that saves you time and one that becomes background noise.