What You Actually Need When Training New Scribes
The biggest mistake I see programs make is building training material around what looks right on paper instead of what happens in a real clinic at 2 PM on a Tuesday. The first time a trainee sits at a workstation and watches a physician type while speaking at 180 words per minute, everything they thought they understood about documentation evaporates. That gap between the training material and the actual job is where people quit or produce garbage documentation. I worked at a multi-specialty clinic for about four years, mostly building out scribe onboarding programs. We went through three major revisions of our core training deck before we stopped getting complaints from providers. The turning point was when I stopped treating the training as a presentation and started treating it as a reference document that a person would actually pull up at 3 AM before their first solo shift.
Medical Scribe Training Material That Actually Works
A solid training package should cover the fundamentals of clinical documentation, the specific EHR platform your organization uses, specialty-specific terminology patterns, and the exact workflows that matter during a patient encounter. Beyond that, it needs to address the things nobody thinks about until they are already in trouble. Things like how to handle a physician who codeswitches between languages mid-sentence, or how to document when the doctor is clearly working from memory and you need to fill in the gaps without inventing anything. Here is the thing that catches most people off guard. The EHR training component should not take up the majority of your instructional hours the way every program I have seen does. Physicians learn their own EHR muscle memory over months. Your scribe does not need to master every click path. They need to understand three things: how to pull up the patient chart quickly, how to navigate between the note editor and the order entry section, and where the problem list lives so they can reference it without asking the physician. Anything beyond that is wasted instruction time. I built a one-page cheat sheet for our Epic instances that covered exactly those three navigation points, and we cut the average first-note completion time from forty-five minutes down to about twelve. The terminology section is where specialty choice matters. A cardiology scribe and an orthopedics scribe will share maybe thirty percent of their vocabulary. Your training material needs to account for that. Rather than building a massive generic medical dictionary attachment, I found it more effective to provide each specialty track with its own focused glossary plus a running list of the ten most common chief complaints and their standard associated history elements. That list alone covers roughly sixty percent of daily encounters in most outpatient settings.
A Problem That Almost Broke Our Program
About two years in, we had a recurring issue where trainees were documenting "denies chest pain" in pulmonary patients who were being seen for dyspnea. The physicians would correct them, sometimes sharply, and the scribes would start second-guessing every negative finding. The root cause was not a lack of training on negatives. It was that our material presented negatives as a mechanical checkbox exercise instead of teaching the clinical reasoning behind which negatives matter contextually. The fix was adding a section called Contextual Relevance for Documented Negatives. It walked through scenarios where a negative finding is medically significant versus where it is just filler. Chest pain matters in a dyspnea workup because it rules out a cardiac contributor to the breathing difficulty. Denying headache in that same patient is usually noise unless the chief complaint includes neurological symptoms. The section included about forty paired examples drawn directly from our actual clinic encounters, anonymized but structurally identical to real notes. Trainees who worked through that section produced cleaner notes from week two onward. Those who skipped it, because we did not initially make it mandatory, regressed within a month. We also added a section on verbatim versus interpretive documentation. New scribes have a strong instinct to rewrite what the physician says in what they think sounds more professional. That instinct is wrong. If a patient says their knees feel like they are going to give out when they walk up stairs, that is a mechanical instability descriptor. If the scribe rewrites it as "patient reports knee weakness with ambulation," the physician has lost important clinical information. The training material needs to hammer this point early and repeatedly. I stopped trying to explain it with analogies and just showed side-by-side comparisons of rewritten notes versus verbatim notes, then had trainees grade each other on which version provided more diagnostic value. It took about twenty minutes and stuck better than any lecture I could have given.
Get the Full Details
Structure That Actually Holds Up
Our final iteration of the training material ran about eighty pages, but only the first twenty-five were consumed during formal instruction. The rest served as reference material that trainees accessed throughout their first ninety days. The structure looked roughly like this: Core documentation principles and compliance basics. This covered what belongs in a note, what does not, and why certain documentation patterns trigger audit flags. Not glamorous. Absolutely essential. Every scribe I have seen get into trouble with compliance did so because nobody explained the connection between their note language and billing verification. EHR navigation specific to our deployed platform. One section per major function: chart access, note creation, template selection, order placement, and sign-off workflows. Keep it platform-agnostic where possible so the material remains useful if the clinic switches systems, but anchor it to your current instance with screenshots.
Specialty-specific clinical patterns. Chief complaint clusters, standard HPI structures by condition type, relevant review of systems sequences, and expected physical exam focus areas. These vary enough by specialty that a one-size-fits-all approach produces scribes who sound like they are documenting encounters they never observed. Practice management and communication protocols. How to handle a provider who does not want a scribe, how to intervene when a patient requests privacy during documentation, what to do when the physician leaves the room mid-note, and escalation paths for technical failures. This last point is important. I had a trainee once spend forty-five minutes trying to force an Epic note to save while the physician was actively using the chart. The system was already saved. The trainee had been clicking the same button repeatedly out of anxiety. A two-sentence protocol in the training material about what to do when technology feels broken would have prevented that entire episode.
What to Leave Out
Most training packages inflate themselves with content that has no practical value in the first ninety days. Pathophysiology deep dives, pharmacology reference tables, extensive coding guideline explanations, and lengthy compliance modules that read like regulatory documents. None of that belongs in initial training material. A scribe needs to know how to document a medication list accurately. They do not need to memorize the mechanism of action for metoprolol. They need to understand that the HPI tells a chronological story. They do not need a fifty-slide deck on CPT modifier logic. If you want to keep the material lean, ask yourself whether a trained scribe would actually encounter this topic during a typical shift. If the answer is no, or if the answer is maybe but only after six months of experience, move it to a resource appendix instead of the core curriculum. The appendix should be searchable and formatted for quick lookups, not reading.
Delivery Method Matters More Than Content Volume
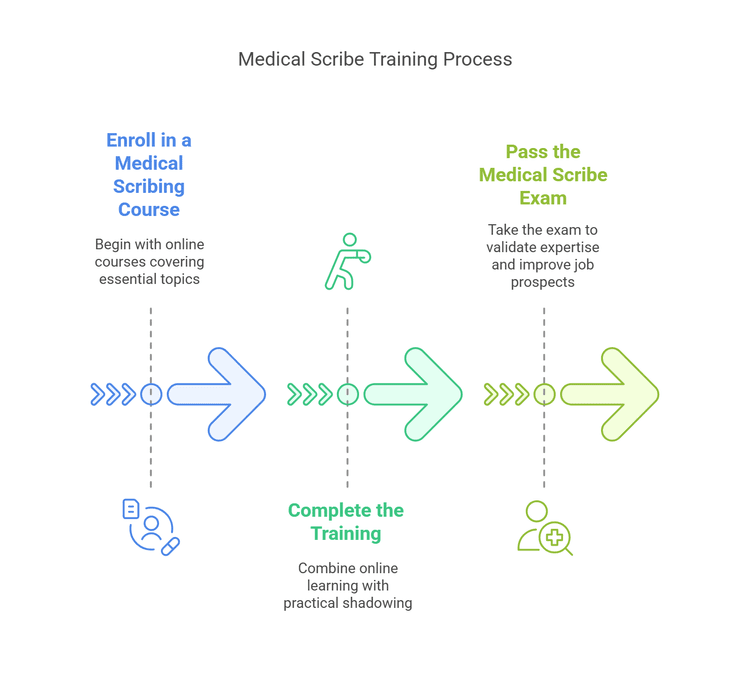
The format you deliver the training in affects retention more than the depth of the content. I have seen programs spend thousands on professionally designed courseware that nobody used past day three. The most effective delivery I found combined three elements: a condensed live session covering the core principles, a documented workflow reference that trainees kept at their workstation, and a paired observation period where the trainee shadowed an experienced scribe for at least ten shifts before attempting independent documentation. The live session should be short. Eighty minutes maximum. Anything longer and the retention curve flattens out completely. Use the time for discussion and scenario walkthroughs, not for reading slides aloud. The reference document should be the training material itself, printed or accessible on a second monitor, because the act of looking something up during practice reinforces the memory far more than passive review. The observation period is non-negotiable. No amount of training material replaces watching an experienced scribe handle a difficult encounter in real time. I remember one specific case where a pulmonary patient became visibly distressed while the scribe was typing, started repeating themselves, and then went silent for almost a full minute. The scribe did not stop typing. She finished the sentence she was on, flagged the silence in the margin with a notation that she would capture follow-up, and asked the physician a quiet clarifying question instead of interrupting the patient. That kind of judgment cannot be taught from a document. It can only be observed and discussed afterward.
Keeping the Material Current
EHR interfaces change quarterly. Clinical guidelines shift. Specialty coding requirements get updated. The training material you build today will be partially obsolete within eighteen months if you do not assign someone to maintain it. I recommend designating one person as the training material owner with a standing review cycle every six months. The review should check three things: whether the screenshots still match the active EHR version, whether any documented workflows have changed due to policy updates, and whether the clinical examples still reflect current patient populations and encounter types at your location. If you do not have a designated owner, the material drifts. Screenshots show buttons that do not exist anymore. Workflow steps reference deprecated template names. Trainees learn processes that were phased out six months ago. The cost of fixing this retroactively is higher than maintaining it proactively. The training material itself should include a version stamp and a change log on the inside cover or in a front matter section. When a new hire picks it up, they should be able to see at a glance whether they are working from the current edition. I once watched a senior scribe train a replacement using an outdated version of our own material. The replacement learned a note signing workflow that had been replaced three months earlier. The error went unnoticed until the provider's sign-off queue backed up and someone checked the logs. Three days of wasted time cleaning up documentation that was technically correct but procedurally wrong.
Bottom Line
Good Medical Scribe Training Material is not comprehensive. It is targeted, it is kept short enough to be referenced under pressure, and it is built around the actual problems scribes face in their first few months rather than the idealized version of the job. The content that matters most is the stuff nobody writes about: what to do when the system hangs, how to distinguish clinically significant negatives from filler, when to wait and when to document immediately, and how to read a room full of people who are trying to do their job while you sit in the corner with a laptop.