What actually sits on a lab floor
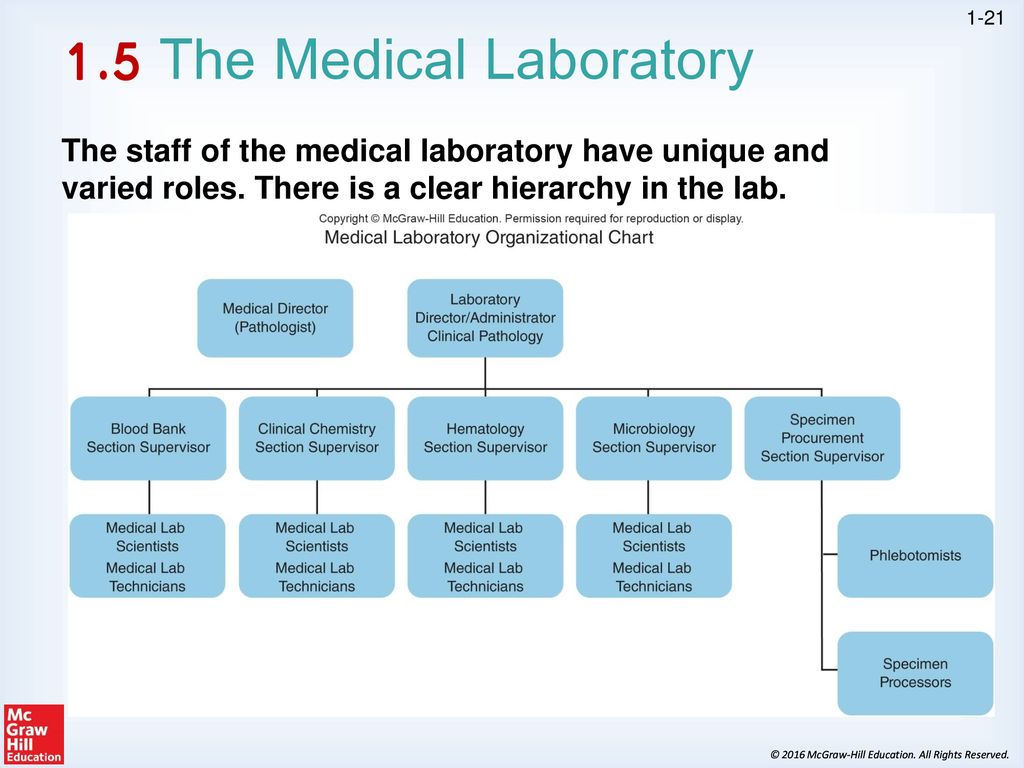
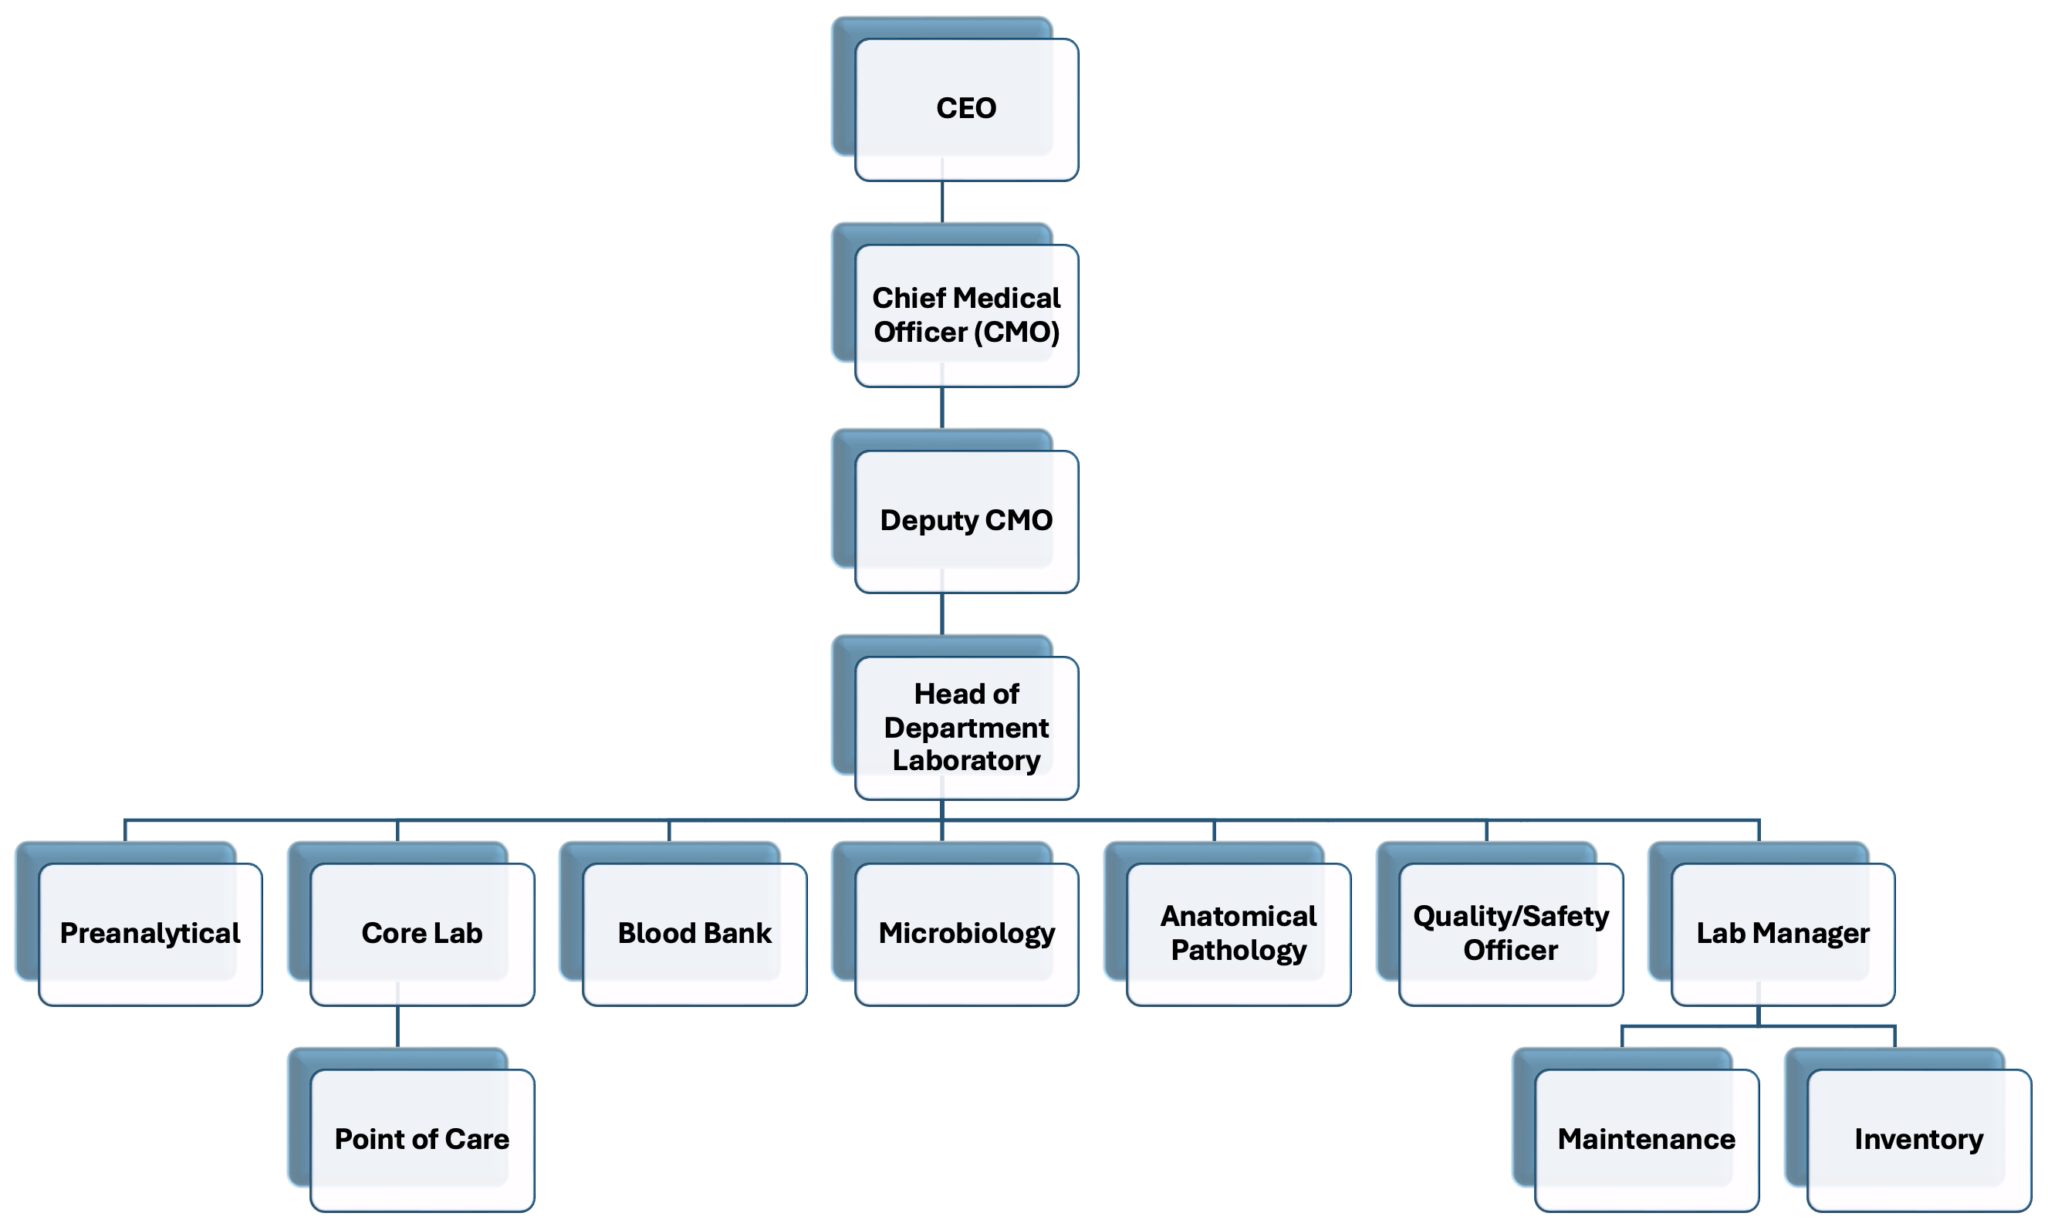
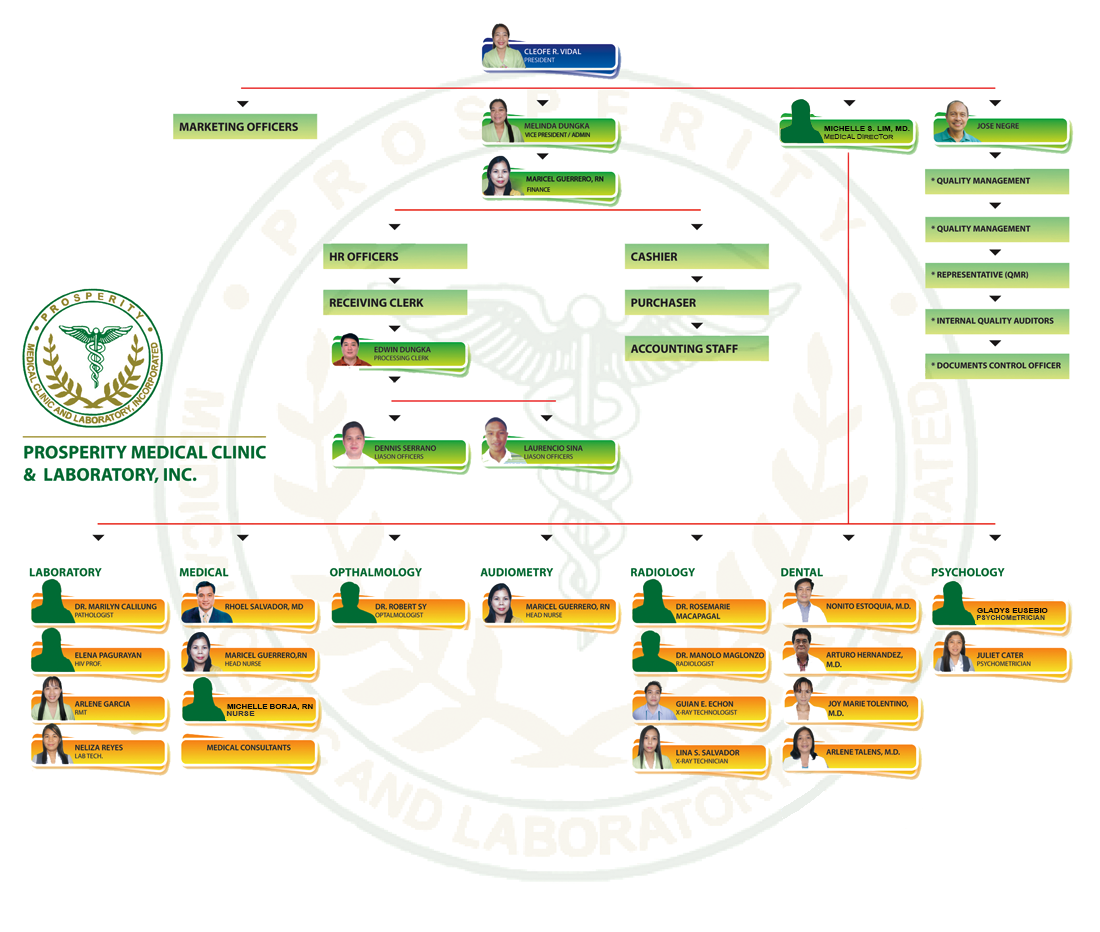
Most people assume a medical technology lab has one org chart, like it came out of a textbook. It does not work that way. I have watched three different hospital labs in Shenzhen, two university teaching labs, and one independent reference lab all use completely different structures even though they run the same instruments. The reason is not theory. It is who signs off on what, who controls the budget, and which department the lab legally belongs to. A Medical Technology Laboratory Organizational Chart is the document that shows reporting lines, signatory authority, and operational boundaries. That sounds simple until you have to explain to an auditor why your molecular biology senior tech reports to the pathology director instead of the lab manager, or why your hematology supervisor has a dotted line to quality control but a solid line to operations. The chart has to satisfy both the clinical staff who use the results and the regulators who audit the paper trail. I spent two months mapping one lab's structure last year. The headcount was forty-seven, four sections, three management layers. We started with a clean organogram from the hospital's central template, which looked fine on a slide but fell apart the moment we tried to match it to actual signatory authority. The problem was not the drawing. The problem was that two senior chemists had been running their own QC decisions for three years without being listed as section leads, and the quality manual still referenced the old director who retired in 2019. Fixing that took forty-eight hours of interviews, three draft cycles, and one argument with finance about whether a senior technician counts as middle management for budget purposes. The workaround I used was a two-layer chart: an operational layer for day-to-day reporting and a signatory layer for QC and method approval. They overlap but do not map one-to-one, and that is normal in practice.Who owns the chart and why it moves
The chart is usually owned by the lab director or the department head, depending on the institution. In public hospitals it often sits under the medical affairs office. In private labs it sits under operations. The difference matters more than people admit because it changes who can update the chart without a committee meeting, and who gets blamed when the chart does not match the actual workflow. I learned this the hard way. A reference lab in Dongguan asked me to review their org chart before an ISO 15189 audit. The chart looked professional on paper, but the quality manager was a mid-level admin with no technical background, and three section supervisors had been acting as de facto technical leads for over a year without being listed. The auditor flagged two non-conformities in the first hour. Not because the chart was wrong in appearance. Because the chart did not reflect signatory authority, and signatory authority is what matters during an inspection. We spent six hours rebuilding the chart from scratch, not by moving boxes around, but by interviewing every person who actually signs a result sheet, then mapping that to the chart. The result took longer than expected, but the audit passed on the second attempt with zero findings.The main layers you will see
A typical medical technology lab has four functional layers, though the titles change depending on the country and the institution type.Executive layer. Lab director, deputy director, sometimes a pathologist liaison. This layer owns the budget, the strategic direction, and the ultimate signatory authority on results. In most hospitals the director reports to the medical affairs vice president or the hospital CEO, not to the lab staff directly. Management layer. Section supervisors, quality manager, operations coordinator. This layer translates executive decisions into daily workflow. The quality manager is the most misunderstood role in any lab chart. They are not necessarily a technician, and they are not necessarily a manager in the traditional sense. They own the quality system, which means they sit between operations and compliance, often with no direct reportees of their own, which creates friction during audits. Technical layer. Senior technicians, section leads, instrument specialists. This layer runs the instruments, validates methods, and controls QC. Senior technicians in chemistry or hematology often have more practical authority than their title suggests, which means the chart usually understates their role unless you deliberately map signatory lines separately.
Support layer. Phlebotomists, specimen handlers, IT coordinators, procurement. This layer is not always shown on the chart because it sits outside the lab proper, but removing it entirely creates gaps in the audit trail for pre-analytical errors, which are the most common source of non-conformities in any lab inspection.
I have seen charts that combine technical and support layers because it simplifies the drawing, but that simplification hides accountability. When a specimen arrives degraded and the root cause is a phlebotomist who was not listed on the chart, the auditor asks who signed off on the training, and the answer is usually someone who has left the lab. Mapping support separately is not optional if you want the chart to survive an inspection.How to build a chart that actually works
The process is not about drawing boxes. The process is about identifying signatory authority, then mapping reporting lines, then resolving overlaps. I usually start with a blank spreadsheet, not a diagram tool, because spreadsheets force you to list names, titles, and actual responsibilities before you move anything visually. The diagram comes later. I interviewed the quality manager at a university lab in Guangzhou last month. She had been in the role for eighteen months, but her name was not on the org chart as a section lead, and the chart listed the lab director as the sole signatory for all QC decisions. The reality was that she had been signing off on instrument calibration and method validation for over a year, and the director was signing only as a formality. This created a hidden risk, because the director had not reviewed the actual calibration records, and the quality manual referenced a procedure that had been superseded three versions ago. The workaround was to add a signatory appendix to the main chart, listing every person who signs a result sheet, an instrument log, or a method validation report, and cross-referencing that to the operational reporting lines. The chart became more complex, but the compliance was real, and the next audit had zero findings in the signatory section.Where the chart fails and what to do about it
The chart fails most often in three scenarios, and knowing them in advance saves weeks of rework.Scenario one: rapid headcount change. A lab hires ten new technicians in three months, which is common in private labs expanding into new sections. The chart becomes outdated before the onboarding is complete, and new staff do not know who signs their results, which creates confusion during the first audit cycle. The fix is a living chart version, not a printed document, with a change log that tracks every addition, deletion, or title change within thirty days of the event. Scenario two: dual reporting lines. A senior chemist reports to both the chemistry supervisor and the quality manager, which happens when the quality system requires independent oversight of technical work. The chart cannot show this cleanly without creating visual clutter, so the workaround I use is a matrix annotation, listing dotted-line relationships in a footnote, not on the main diagram. This keeps the chart readable while preserving the compliance reality. Scenario three: regulatory mismatch. The chart satisfies the internal management structure but does not match the regulatory signatory requirements, which happens when the regulator requires a specific title that does not exist in the local job hierarchy. I encountered this at a lab in Foshan where the health commission required a designated quality officer, but the hospital only had a quality manager who was technically a mid-level supervisor. We resolved it by adding a dual-title notation on the chart, listing both the internal title and the regulatory designation, which satisfied the auditor without restructuring the entire department.
Get the Full Details