Medicare Chiropractic Billing Guide
If you're billing Medicare for chiropractic services, you've probably already hit a wall. The rules are narrow, the denials are specific, and there's almost no room for interpretation. This guide covers what actually works when you submit these claims, based on real experience filing them month after month. Medicare Part B covers chiropractic manipulative treatment (CMT) only when it's medically necessary to correct a subluxation. That's it. No adjunctive therapies like modalities, TENS, ultrasound, or exercise therapy are covered under Medicare for chiropractors. They can be provided to the patient, but they cannot be billed separately to Medicare. The scope is deliberately limiting. You will need to be enrolled in Medicare as a participating or non-participating provider. Most chiropractors enroll as non-participating. The reimbursement difference is minimal for CMT, but it affects whether you can balance bill the patient for the Medicare-approved amount above the 95% you'd receive as a participating provider. I always recommend non-participating status unless you have a specific reason to participate.
Which Modifier Do You Actually Need?
This is where most people mess up. Modifier 26 is for professional components in surgical situations. You do not use it for chiropractic. What you use is Modifier TC in some contexts, but the more relevant one is the HCPCS Level II code system paired with the correct documentation. The actual billing modifier that matters most is the 59 modifier for distinct procedural services when you're doing something beyond basic CMT, though Medicare rarely accepts it for chiropractic anyway. The real work is in the diagnosis code. You must have a documented spinal subluxation. ICD-10 codes in the M99 category are the standard. M99.0 through M99.3 cover subluxation by region. You cannot just bill M99.9 without support. I once had a claim denied three times with M99.9 because the Medicare contractor required a laterality code. The fix was switching to M99.00 for unspecified region with proper notation of left or right in the clinical documentation. It took two weeks of back-and-forth before I stopped resubmitting the same way and started using the precise codes.
Documentation Requirements That Actually Matter
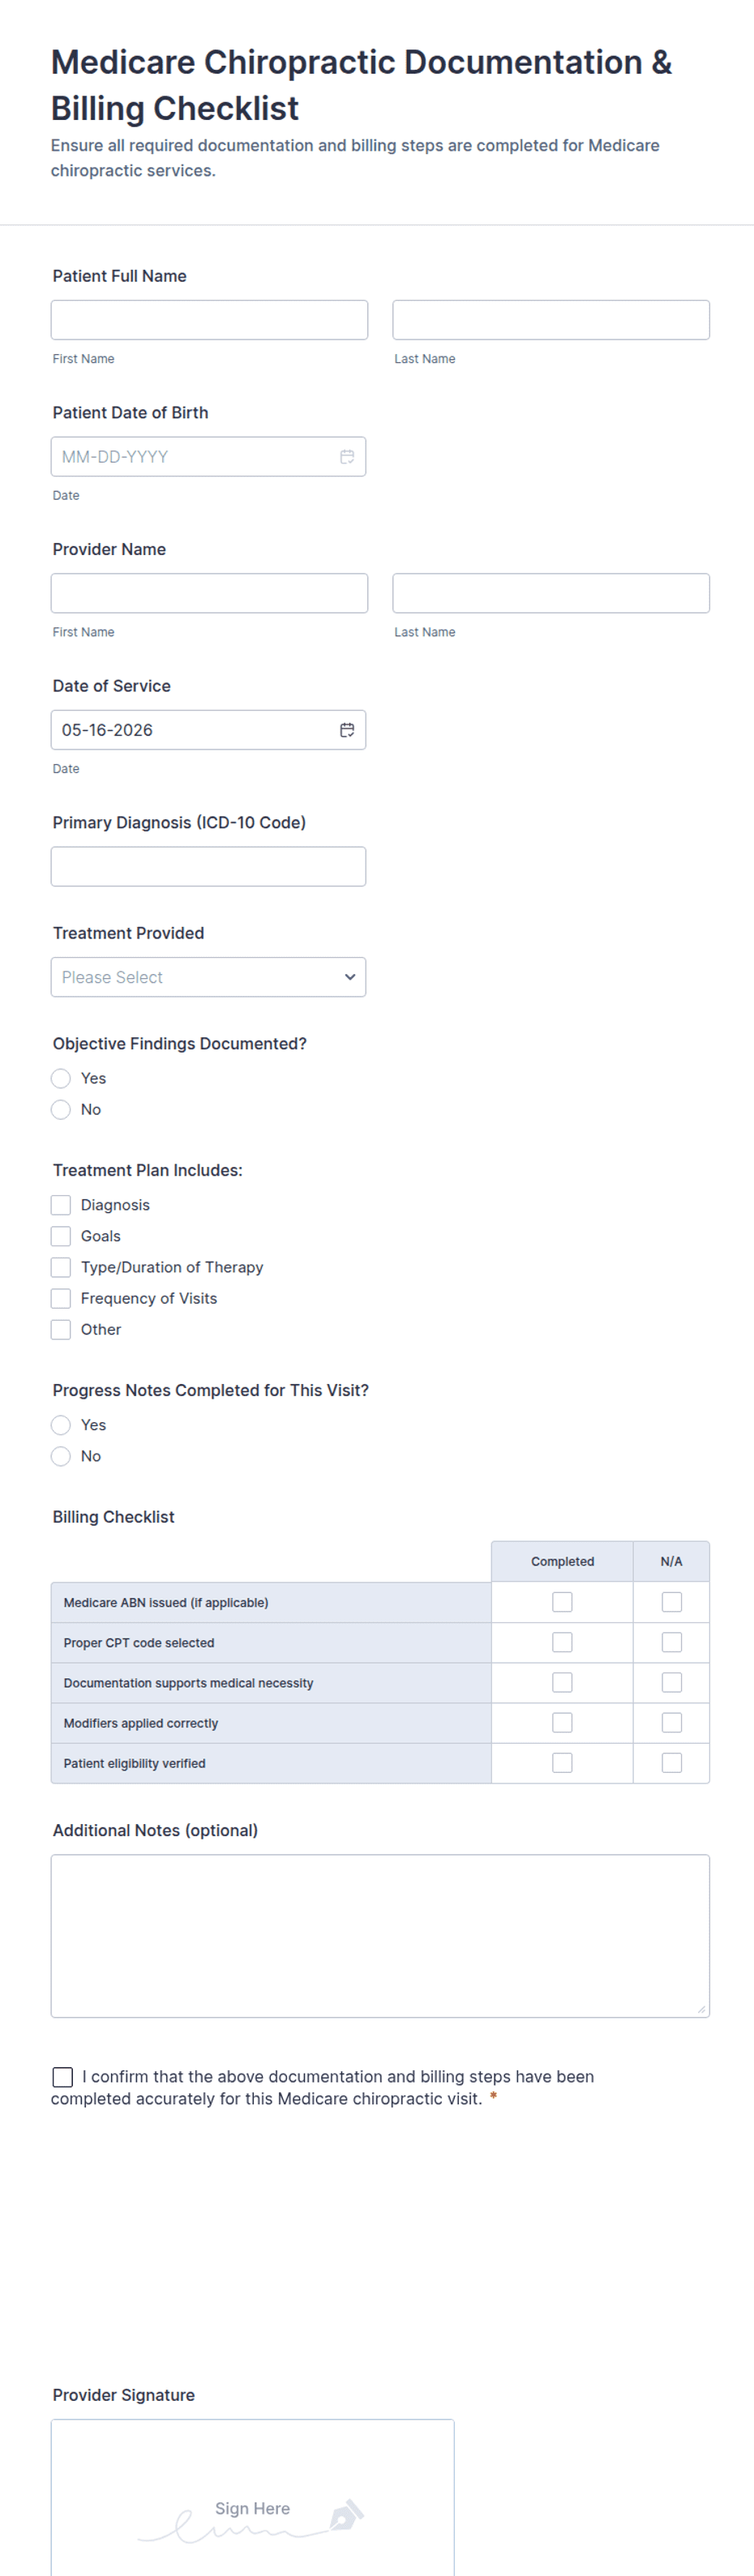
Medicare requires documentation that supports medical necessity. This means a thorough history, a physical exam findings section that notes the subluxation, and a plan of care. The plan of care must include the number of expected visits and the anticipated duration of treatment. Medicare does not pay for indefinite care. If your documentation reads like "patient returns as needed," the claim will be denied. I learned this the hard way when a patient had been coming in twice weekly for eight months and my documentation never specified a plan of care timeframe. The Medicare administrative contractor flagged the entire episode. The workaround was to go back, document a retrospective plan of care with specific visit estimates, and submit a corrected claim with an appeal. It took four months and three appeals to get paid. Don't skip the plan of care documentation at the first visit.
Get the Full Details

Claim Submission Workflow
Submit claims electronically whenever possible. Paper claims get lost and take significantly longer to process. Use the CMS-1500 form format, which is standard for outpatient services. Include the correct place of service code: 11 for office visits. Do not use 22 for hospital outpatient unless the service was actually rendered in a hospital setting, which is rare for chiropractic CMT. The NPI should be your individual NPI if you are the ones performing the service. Some practices use the group NPI for all submissions, but that can trigger issues with Medicare's fraud and abuse monitoring if the rendering provider's NPI doesn't match the billing NPI consistently. Keep them aligned.
Common Denial Reasons and How to Handle Them
The most frequent denial is "medical necessity not established." This happens when the documentation doesn't clearly link the subluxation to the treatment provided. Another common one is "service not covered," usually tied to adjunctive therapies being billed alongside CMT. Medicare sees those as bundled or non-covered services. When you get a denial, don't just resubmit the same claim. Request the detailed denial reason from the Medicare administrative contractor. They will send a remittance advice with a specific reason code. Codes like CO-16 or CO-97 indicate coverage issues that require a different approach than CO-50, which is a simple missing information problem. Knowing the difference saves you from wasting time on the wrong appeal path.
A Practical Example
A 68-year-old patient presents with lower back pain. You perform a chiropractic manipulation on the lumbar spine. You document the history, the exam findings showing tenderness and restricted motion at L4-L5, the subluxation diagnosis coded as M99.05, and a plan of care for six visits over three weeks. You bill CMT with the appropriate code from the chiropractic CMT code set, which ranges based on the number of regions treated. For one region, it's 98940. Two regions is 98941. Three or more regions is 98942. Medicare pays 80% of the Medicare-approved amount after the Part B deductible is met. The patient is responsible for the remaining 20%. If you accept assignment, you cannot balance bill. If you do not accept assignment, you can bill the patient the difference between your charge and the Medicare-approved amount, up to the limiting charge. In most cases, the limiting charge is 115% of the non-participating Medicare-approved amount, though this varies by state and year.

What This Approach Cannot Do
This system does not cover spinal cord stimulation, physical therapy codes billed by a chiropractor, or any diagnostic imaging beyond what Medicare considers reasonable. If your practice relies heavily on X-rays or lab work, those are typically billed separately by the imaging facility or laboratory. Chiropractors generally cannot bill Medicare for X-rays performed in their own office unless they meet specific enrollment and equipment requirements, which most do not. Medicare also does not cover maintenance care. If a patient's symptoms have stabilized and the goal is ongoing wellness rather than corrective treatment, the claim will be denied as not medically necessary. I have seen entire practices shut down because they were billing Medicare for maintenance care without realizing the distinction. Define "active treatment" versus "maintenance" clearly in your documentation, and keep them separate.
The Bottom Line on Medicare Chiropractic Billing Guide
The Medicare Chiropractic Billing Guide framework is straightforward in theory and frustrating in practice. The key points are accurate diagnosis coding, documented plan of care, no billing for non-covered services, and proper claim submission. Anything outside those boundaries gets denied. Most denials come from poor documentation, not from legitimate coverage issues. Fix the documentation first, before you appeal.