What Medicare Cognitive Test Questions Actually Look Like in Practice
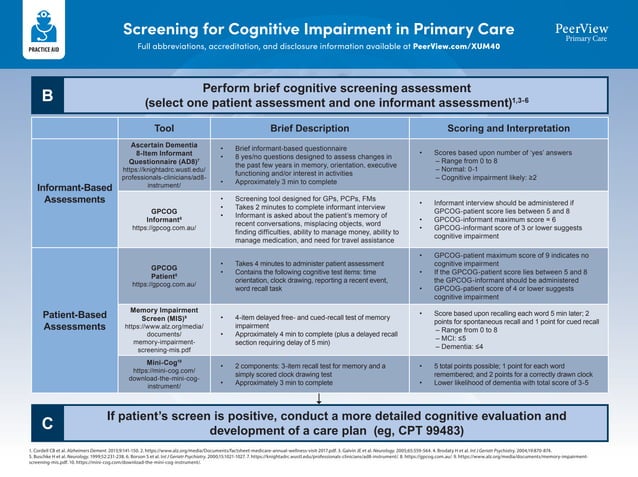
Most people thinking about these questions are either preparing a patient for an assessment or working through a care plan documentation issue. The cognitive test itself is usually the MMSE or the MoCA, and Medicare doesn't administer its own standalone exam. What Medicare does is cover an Annual Wellness Visit, and during that visit a physician or qualified provider may use a brief cognitive screening tool if they suspect impairment. The questions you'll encounter are standard. Here's a realistic set:
Medicare Cognitive Test Questions You Should Know
Orientation: What year is it? What season is it? What month is it? What day of the week is it? What state are we in? What county and city are we in? What is the address or location of the facility? Registration: I'm going to name three objects. Repeat them back to me: apple, penny, table. Attention and calculation: Spell WORLD backward. Or count backward from 100 by sevens: 93, 86, 79, 72, 65.
Recall: What three objects did I ask you to repeat earlier? Language: Name a watch and a pencil. Repeat: No ifs, ands, or buts. Read the sign and obey it. Follow a three-step command: Take this paper in your left hand, fold it in half, and put it on the floor. These are the core items on the Mini-Mental State Examination. The Montreal Cognitive Assessment adds a few more domains like visuospatial ability, executive function, and abstract reasoning, but the structure is similar.
Get the Full Details
I worked claims and care coordination for years and saw the same problem repeatedly. Providers would document a cognitive screening but not capture the specific scores or the tool used. Medicare audits flag this routinely. The workaround is simple: the chart note has to state which instrument was administered, the total score, and the breakdown of domain scores. Vague phrases like "cognition appears intact" without a tool and score will get denied or trigger a request for additional documentation. One edge case I ran into constantly involves patients with limited English proficiency. The standard MMSE isn't validated for non-English speakers at the same level of reliability. A Spanish-speaking patient might score well below the cutoff simply because of translation issues with words like "forfeit" or "seconds" on the attention section. I learned to document the language used and whether a certified interpreter was present during the assessment. When an interpreter isn't available, switching to a bilingual validated tool or noting the limitation in the medical record protects against inaccurate scoring. Another counter-intuitive thing most people miss: a normal cognitive screen doesn't rule out early dementia. The MMSE has poor sensitivity for mild cognitive impairment. It can catch moderate to severe deficits reliably but will frequently miss the early stages where memory complaints are subtle. If the clinical picture suggests MCI, the right move is to document the normal score and still note the concern with a referral for a more sensitive instrument like the MoCA or a neuropsychological evaluation. Medicare covers the initial preventive physical examination and the annual wellness visit, and those visits can include a health risk assessment that triggers a referral. The coding has to reflect the reason for the referral, not just the screening score.
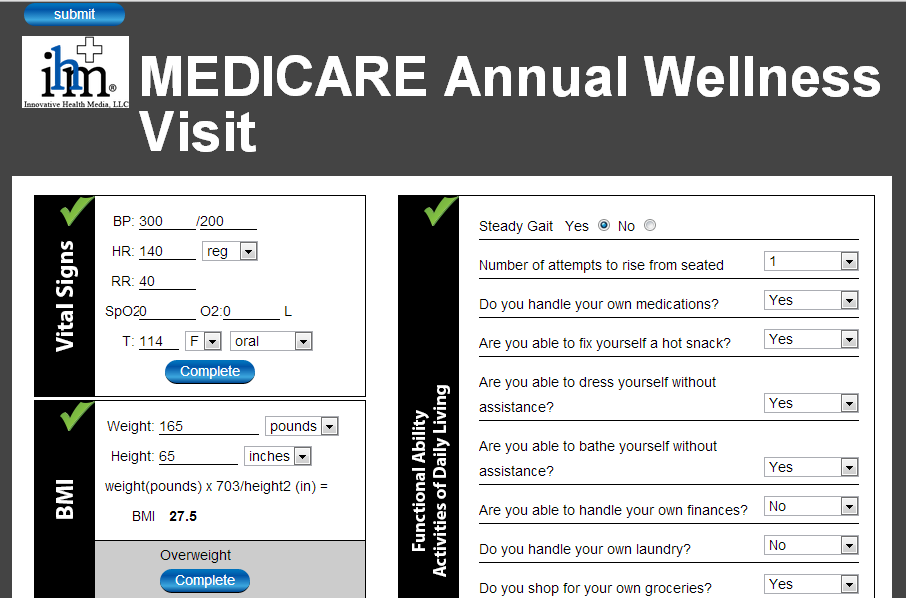
Here's how the coverage side works. Medicare Part B covers the Annual Wellness Visit once every 12 months. Within that visit, a cognitive assessment is considered part of the standard preventive services if it's ordered by your provider. There's no separate copay for the cognitive test itself when it's part of the AWV. However, if the screening is abnormal and leads to additional diagnostic testing, that's a separate claim. Diagnostic workups fall under standard Part B medical benefit, which means the usual 20% coinsurance applies after the deductible. Important detail: the Subjective Cognitive Decline visit. Medicare now covers a separate office visit code for SCD assessment when a patient reports memory concerns but hasn't been diagnosed with dementia. This is G0438. It's billed differently from the AWV and has different coverage requirements. I've seen providers mix these up and get claims rejected because they bundled SCD assessment into an AWV flow. The two visits serve different purposes and need distinct documentation and coding. If you're looking for practice materials or test forms, the official MMSE scoring sheet is publicly available through the original publisher's materials, and the MoCA form can be found on the MoCA website for clinical reference. Neither Medicare nor CMS publishes its own version of these questions. Be cautious of sites selling PDFs of the full cognitive tests for free download, as distributing the complete copyrighted instruments without a license can create legal issues for clinics and practices.
For most patients and caregivers, the practical takeaway is straightforward. Write down the questions you're asked before the appointment. Bring a list of all medications, including over-the-counter supplements, since polypharmacy is a common reversible cause of cognitive changes. Ask the provider which tool they used and what the score means in context. A raw score of 24 out of 30 on the MMSE falls in the borderline range, but the clinical interpretation matters more than the number alone. I also learned the hard way that documentation standards for geriatric assessments have tightened considerably. Medicare Advantage plans in particular audit cognitive screening documentation aggressively. If the provider's note doesn't include the baseline score, the tool name, and a clear plan for follow-up, the claim gets denied and the patient is stuck with the bill. Make sure the EHR note captures all three elements before the encounter closes. There are limitations to keep in mind. These screening tools are not diagnostic. They're designed to identify whether further evaluation is needed. A person with high education might score normally despite having early dementia, while someone with lower education or a learning disability might score below cutoff without any cognitive disorder. Age norms matter, and the standard cutoff scores don't always account for educational background adequately. The tools work best when combined with a thorough history from a family member or caregiver who can describe functional changes observed at home.
If you need the actual test forms for clinical use, the MMSE is available through the original authors' licensing process, and the MoCA is available on the vendor's website with a nominal fee. For educational and informational purposes, many resources provide abbreviated versions that show the question types without reproducing the full copyrighted instruments. That's usually sufficient for understanding what to expect during a Medicare-covered screening visit. The billing codes most relevant to this area are G0438 for the subjective cognitive decline assessment, G0402 for the initial preventive physical examination, and G0437 for the annual wellness visit. These codes determine what's covered and what requires cost-sharing. Knowing which code applies to your specific situation prevents surprises on the explanation of benefits statement. When I see people stressed about these tests, it's usually because they don't know what's being measured. The cognitive screen checks orientation, memory, attention, language, and visuospatial skills in about ten to fifteen minutes. It's not a comprehensive neurological exam. It's a screening tool, and its value depends entirely on what happens next based on the result. A normal score means continue monitoring. An abnormal score means the provider should recommend next steps, which may include blood work to rule out reversible causes, medication review, hearing or vision screening, and possibly a referral to neurology or geriatrics.
The whole process works best when the provider and patient are aligned on what the test can and cannot do. It catches problems early enough to intervene, but it doesn't diagnose. Understanding that distinction saves everyone time and prevents unnecessary anxiety when a score comes back lower than expected.